冠心病百年退缩史
究竟发生了什么、现代心脏病学贡献了多少、以及接下来应该怎么做
叙事性和系统性证据综述,约 1925–2026年
Peter Megdal, PhD 2026年8月24日
目录
究竟发生了什么、现代心脏病学贡献了多少、以及接下来应该怎么做 3
必须先被发现才能被统计的流行病(约 1900–1949 年). 7
模型的工作原理,以及它们能告诉你什么和不能告诉你什么.. 15
如果一个现代人口拥有落后的医疗护理——或者面临落后的风险因素,会怎么样?. 35
- 治疗累积终生暴露量,而非中年阈值. 41
- 终于有了治疗脂蛋白(a)的方法. 42
- 扩展降脂工具箱并解决依从性问题. 42
- 直接治疗心脏代谢驱动因素. 42
- 解决残余炎症风险. 43
- 在事件发生前找出处于危险中的人. 43
- 人口政策保留了异常强大的杠杆作用. 43
通俗易懂的执行摘要
在绝大多数医学史中,没有人被诊断为死于 心脏病发作 — 不是因为 心肌梗死 并没有发生,而是因为当时它尚未被识别为一个临床综合征。. 冠状动脉血栓形成 直到1912年才被描述为活体患者的临床综合征。1在短短四 decades 内,它已成为工业化世界的主要死因。而在又一个 four decades 内,它却在节节败退。这是最非寻常的事件之一 反转 在医学史上,而且通常被糟糕地解释。.
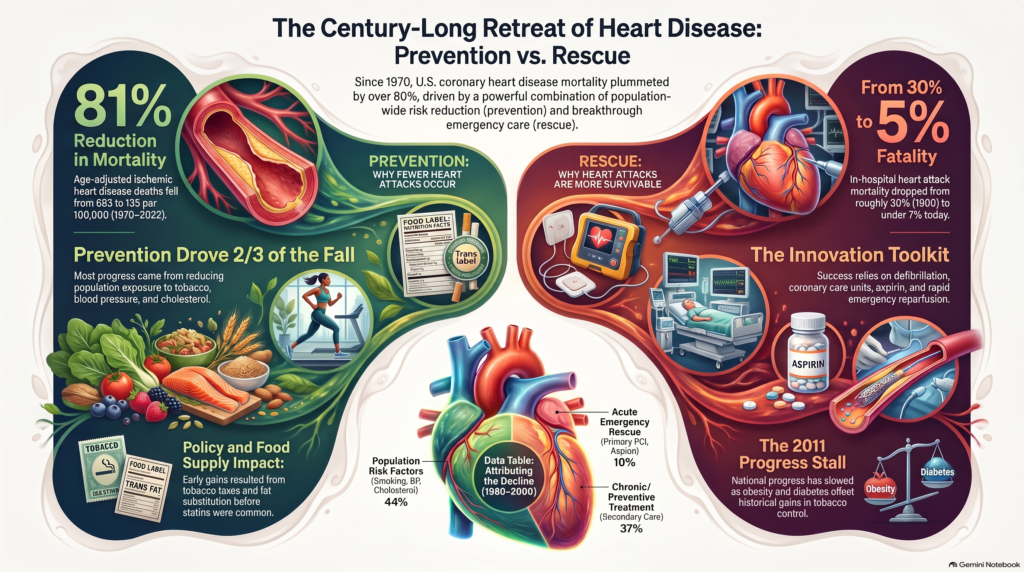
心脏病学界创造的流行版本 他汀类药物 以及 支架 从而征服了心脏病——单从时间顺序上来说就是错误的。美国的冠心病死亡率在1968年前后达到峰值,在第一种他汀类药物获批之前,死亡率就已经下降了大约三分之一,在此之前 血管紧张素转化酶抑制剂, ,在初选之前 血管成形术, ,在任何人进行随机试验之前 阿司匹林 在急性心肌梗死中。相反的看法则认为——这种下降纯粹是由于人们 吸烟 吃得少一点、吃得好一点,再加上药物的辅助——这种看法同样是错误的。现代疗法在死亡率下降的原因中占了相当大的比例,在某些国家和时期甚至接近一半。.
准确的版本是,两件不同的事情同时发生了,它们绝不应该被混为一谈:
首先,心脏病发作的人数减少了。. 人群减少了其一生中对三种主要的可改变驱动因素的暴露 动脉粥样硬化:烟草烟雾,升高的 血压, ,且具致动脉粥样硬化性 胆固醇. 这些并不是唯一的成因—— 糖尿病, ,肥胖和代谢功能障碍也很重要,它们的趋势朝着错误的方向发展。其中一部分源于个人行为,很大一部分源于政策和食品供应,而随着时间的推移,药物所占的比例越来越大—— 抗高血压药 自20世纪70年代起,他汀类药物则自20世纪90年代中期起。.
其次,那些确实发生心脏病发作的人不再因此而死亡。. 1960年,因急性心肌梗死入院的患者,约有三分之一至五分之一的人无法活着出院。 在高收入国家医疗体系中,ST段抬高型心肌梗死患者的当前院内死亡率通常在4–7%左右,尽管该数值因病例构成差异而变化显著,且并非适用于所有急性心肌梗死(AMI)病例的通用数值。冠心病监护室、除颤、心肺复苏、急救医疗系统、阿司匹林、, 溶栓治疗, ,而急诊经皮冠状动脉介入治疗起到了这一作用。这些急性抢救干预措施主要用于提高事件发生后的生存率,而不是预防首次心肌梗死。.
两项成就都降低了冠心病死亡率,仅凭死亡率本身无法说明到底是哪一项发挥了作用。最好的国际数据表明,在经典的下降数十年间,冠心病死亡率下降的大约三分之二归因于冠心病发作次数的减少,大约三分之一归因于患者幸存下来。.
故事中还有一部分尚未被写进教科书。. 跌势已止。. 在美国和英国,大约从2011年起,进展明显放慢,而在55岁以下的成年人中,一些严重的不良结果已经开始朝错误的方向发展。. 肥胖症 和2型糖尿病三十年来一直在透支健康;国民血压控制有所恶化;而控烟带来的轻松成效也大多已经兑现。未来一百年的进步将不会通过重复过去一百年来实现。它可能越来越取决于治疗累积的终生致动脉粥样硬化暴露,而不是中年时期的风险阈值,取决于 脂蛋白(a) 如果终点试验证实了其益处,随着当前正在进行的的心血管代谢革命 肠促胰素 疗法,在 残余炎症风险, ,最重要的是缩小我们已知有效的方法与患者实际获得的治疗之间巨大的实施差距。.
答案请写在一段话内
冠心病 在二十世纪上半叶持续上升,在大多数高收入国家于20世纪60年代达到顶峰,随后经历了针对主要死因的有记录以来最大规模、最持久的死亡率下降之一。在美国,经年龄调整的 缺血性心脏病 死亡率下降自 1970年至2022年间,每10万人口中的死亡人数从693人降至135人——减少了81% —虽然专门编码为急性心肌梗死的死亡率下降了 从每10万人口354例降至40例,降幅达89% [2]。目前最佳的归因模型并不支持将这一成就归功于单纯的“医学”或是单纯的“生活方式”。在美国和几个欧洲国家的 主要下降时期,大约 秋季44–73%的下降归因于人口风险因素的有利变化, ,而大约 23–47% 归因于内科和外科治疗; 急性冠状动脉治疗本身通常仅约占 4–12% 总体死亡率下降 在 IMPACT 型模型中 [3,4,5,6,7,8]。与此同时,世卫组织莫尼卡(WHO MONICA)的数据表明,大约 20世纪80至90年代冠心病死亡率下降的原因中,三分之二归因于冠心病发病事件的减少,三分之一归因于发病后生存率的提高, ,群体之间存在显著差异 [9].
实际结论是:历史上冠状动脉事件发生率的下降,很大程度上似乎源于人群对动脉粥样硬化风险因素(尤其是吸烟、 血压和胆固醇——而现代心脏病学则通过药物手段降低这些风险、预防复发,并将心脏病发作从一种短期死亡率约为20–30%的事件,转变为在当代高收入医疗体系中存活率显著提高的疾病,从而做出了巨大的额外贡献。.
核心定量结论
| 问题 | 最佳可辩护综合 | 信心 |
| 美国冠心病/缺血性心脏病死亡率下降了多少? | 年龄标化的缺血性心脏病死亡率下降 1970–2022年的81%; 急性心肌梗死编码的死亡率下降 89%. 在记录最详细的单一时期内,年龄调整后的冠心病死亡率大约下降了 1980年至2000年间的50%. 早期的历史系列数据表明,心脏病死亡率在达到本世纪中叶的峰值后,才开始持续下降。. | 高 |
| 心肌梗塞的发病率下降了多少? | 不存在有效的通用世纪长效数据。弗雷姆汉姆心电图定义的首次心肌梗死大约下降了 1960–1999年的50%; 冰岛心肌梗死发病率下降 1981–2006年的66%; ARIC 显示出大约年度下降 3–4% 在1987-2008年期间的大多数性别/种族群体中。日本表明,发病率完全没有必要下降:宫城县上升自 每10万人口7.4至27.0 在1979年至2008年之间。. | 适度 |
| 心肌梗塞(MI)的病死率下降了多少? | 弗雷明汉(Framingham)经年龄和性别调整后的30天、1年和5年病死率均分别下降了大约 1960–1999年的60%; 宫城县内的医院病死率从 20.0% 至 7.8% 在 1979–2008 年期间。冠状动脉监护病房建立前的院内死亡率约为 30% 相比于当代大约为……的院内STEMI死亡率 4–7%. | 高 以获取指引;; 适度 跨时代的体量 |
| 人群危险因素贡献率 | 通常 ~45–70%, ,个体 IMPACT 估计值范围从 44%(美国) 到 73%(冰岛). | 适度 |
| 所有医疗/外科治疗资助 | 通常 ~25–45%, ,大约从 23–47% 在重大的 IMPACT 分析中。. | 适度 |
| 急性/紧急治疗贡献 | 通常 ~5–10% 占冠心病死亡率总降幅的比例 在归因模型中(各国数据约为4–12%)。但病死率的下降——其中急性医疗体系的改进起到了重要作用——约占 冠心病死亡率下降的三分之一 在 MONICA 型分解中。. | 适度 |
| 其他/诊断/医疗体系贡献 | 无法独立识别。IMPACT 残差通常 ~5–10%, ,但这一残差必须 不 等同于EMS、诊断或卫生系统改进,因为许多此类效应已经嵌入在治疗估计值中。. | 低 |
| 进展是否仍在继续? | 不。. 在美国和英国,这种下降趋势在大约 2011 年后明显放缓,并在年轻成年人中陷入停滞,近期证据表明,18-54 岁成年人在首次 ST 段抬高型心肌梗死(STEMI)后的院内死亡率有所恶化。肥胖、糖尿病和 高血压 控制仍然是重要的群体层面制衡力量。. | 中等至高 |
一个关键的术语点决定了接下来的一切: “风险因素”这一类别并不是个人生活方式选择的同义词。. 吸烟率的下降反映了税收、无烟立法、广告限制、医生咨询以及个人决定的影响。人口胆固醇水平的下降则反映了食品供应配方的改良、饮食改变以及他汀类药物的使用。血压的下降既体现了人口层面的长期趋势,也体现了抗高血压药物的处方应用。最具说服力的分析会明确区分这些途径,而不是进行重复计算。例如,在瑞典的 IMPACT 研究中,人口胆固醇水平下降了 0.64 mmol/L,这一结果被分解为大约 通过饮食改变预防或推迟了5,210起死亡,通过服用他汀类药物预防或推迟了810起死亡, ,而收缩压下降了 2.6 mmHg,大约被分为 900例由于自然病程死亡,575例由于抗高血压治疗死亡 [10].
第一部分:故事:一种疾病的兴衰
必须先被发现才能被统计的流行病(约 1900–1949 年)
撰写心肌梗死百年史面临的第一个难关是,在这一历史的前四分之一时期里,这种诊断几乎尚不存在。詹姆斯·赫里克(James Herrick)在1912年对冠状动脉的描述 血栓形成 在活体患者中——在过去的十年里基本上被忽视了——证实了阻塞的冠状动脉 动脉 存活且因此可被诊断,而不仅仅是一个死后发现。1心电图使它在床边就能被辨认出来。直到那时,人们才开始计数。.
我们可以确信地说,心脏病成为美国人的头号死因是在 1921, 冠心病死亡率在20世纪30、40和50年代持续上升。我们无法确定的是,这种表面上的上升有多少是由于动脉粥样硬化事件的真实增加,又有多少归因于诊断水平的提高、死亡证明的规范化,以及一个简单的事实:即人们的寿命足够长了——熬过了传染病、结核病和生育关——从而能够患上冠心病。几乎可以肯定的是,这两方面原因兼而有之,其中大规模普及吸烟、血压的不良变化以及饮食结构的改变很可能起到了重要作用——尽管这一早期阶段的因果权重本质上是不确定的。.
有效且基于证据的冠状动脉治疗极其有限。急性梗死标准治疗是六周严格卧床休息,其理论基础是受损的 心肌 患者本可以免受这些折磨。当时没有任何监测手段,无法治疗在最初几个小时内夺走大量患者生命的致命心律失常,无法疏通闭塞的动脉,也没有经过验证的现代冠心病预防危险因素框架——尽管饮食、运动、烟草和血压都已被讨论过,但前瞻性的危险因素科学当时尚未诞生。活着到达医院的患者,大约有三分之二到五分之四的生还几率。.
顶峰与转折(1950–1969)
在疫情得以扭转之前,必须发生两件事,而这两件事都在这个时代发生了。.
这 风险因素 被发现。. 这 弗雷明汉心脏研究, 始于1948年的该研究向全世界提出了“危险因素”这一概念,并确定了血压、胆固醇和吸烟是几个主要的、可改变的危险因素。安塞尔·基斯(Ancel Keys)的“七国研究”则将人群饮食模式与血清胆固醇和冠心病发病率联系了起来。111964年美国外科医师总报告将烟草的致病作用确立为官方政策,而不再是学术观点。这些都没有治疗哪怕一个患者。但所有这些,让随之而来的一切成为可能。.
救援被发明了。. 冠心病监护病房——戴斯蒙德·朱利安(Desmond Julian)提出的设想,并于20世纪60年代初在堪萨斯城、多伦多、费城和悉尼的病房中付诸实现——是急性心肌梗死治疗中最重大的创新之一,而且它完全没有使用药物。它的洞见很简单:早期心肌梗死死亡的大部分是由 心室颤动, ,如果现场有除颤仪,室颤是可以瞬间逆转的,因此应该由受过电击培训的人员对患者进行持续监护。胸外心脏按压于1960年被描述;体外除颤在此之前的一个年代已被证实。历史序列表明,急性心肌梗死的住院死亡率从大约 30% 转向 15% 随着冠心病监护病房的到来。12]
支持这一点的证据基础比其重要性所暗示的要弱——大部分证据属于前后对照的观察性研究,而英国一项著名的研究曾主张,对于部分特定患者而言,居家护理并不比医院护理差。一项关于冠心病监护病房与普通病房收治情况的前瞻性随机对比研究发现,总体死亡率为 15.3%(17/111)对 29.3%(27/92), 与在单位相比,在普通病房死亡的风险 2.3 (95% CI 1.1–4.8), ,且在普通病房中猝死更为频繁。13该试验规模小、为单中心研究,且其所处的医疗环境与今天不同,而更广泛的证据基础大体上是观察性的;14] 但跨越多个机构的时间信号是一致且巨大的。.
与此同时,有效的抗高血压治疗方法出现了。退伍军人管理局合作研究(1967年,1970年)表明,治疗严重高血压以及随后的中度高血压可以预防 中风, 心力衰竭, ,以及死亡——具有里程碑意义的随机对照证据表明,通过药物干预心血管危险因素能够改变临床结局。15]
美国冠心病死亡率在左右达到峰值 1968 并开始落下。.
急剧下降 (1970–1989)
这个时代最有力地驳斥了“现代心脏病学创造了这一切”的说法,因为在其中的大部分时间里,现代心脏病学尚不存在。直到1987年才出现他汀类药物,直到1994年才开展他汀类药物的疗效试验。直到1987年才开展心力衰竭的血管紧张素转化酶抑制剂(ACEI)试验,直到1992年才开展心肌梗死后的相关试验。. 球囊血管成形术 于1977年首次实施,在长达十年的时间里一直是一项小众手术。直到1988年,阿司匹林在急性心梗中的疗效才得到证实。.
这种下降在得到解释之前就已经被注意到了。1978年的贝塞斯达会议由美国国家心肺血液研究所召集,其召开的明确目的就是记录并解释美国冠心病和中风死亡率意料之外的下降趋势——这一趋势此前无人预测,也无人能归因。那次会议正是下面将要回顾的整个归因文献的起点[16]。
然而,美国经年龄调整的缺血性心脏病死亡率,, 1970年每10万人中就有693人, ,在整个时期内急剧且持续地下降。真正发生改变的是暴露情况。在外科医生总报告发表以及随后的广告限制出台之后,男性的吸烟率大幅下降。随着食品供应的转变,血清胆固醇水平下降了。国家高血压教育计划(1972年)将高血压的筛查和治疗推向了常规初级保健。在芬兰的北卡累利阿——当时记录的冠心病死亡率居全球最高之列,特别是适龄工作男性——一项明确基于社区的预防计划于1972年启动,并证明了人群的危险因素特征是可以被刻意改变的。.
在该时代快结束时,治疗革命终于到来,并且它首先来到了急诊室。GISSI (1986)[17] 然后是 ISIS-2 (1988)[18] 确立了链激酶和阿司匹林均能独立减少急性心肌梗死患者的死亡率,并且两者合用能显著降低死亡率。1972至1984年间进行的冠状动脉旁路移植术随机试验确立了以下结论:生存获益主要集中于左主干病变和广泛的多支病变患者,而对于较局限的病变,几乎没有可证明的生存获益——尽管获益也随左心室功能和解剖结构的不同而有所差异。[19]
药理学巩固期(1990–2009)
如果说20世纪70年代和80年代属于人口预防和急性抢救,那么这个时代则属于慢性药物治疗和医疗照护体系。.
4S 试验(1994年)表明,辛伐他汀可降低冠心病患者的死亡率,在十年内,他汀类药物已成为地球上处方量最多的药物之一。20] ACE抑制剂从心力衰竭治疗拓展至心肌梗死后护理。β受体阻滞剂、阿司匹林和 降脂 合并为一个标准的一级预防和二级预防组合。与球囊血管成形术相比,冠状动脉支架减少了急性弹性回缩和急性闭塞,并大幅降低了再狭窄率——尽管再狭窄得到了减少但并未消除,而药物洗脱支架随后进一步降低了再狭窄率。双 抗血小板治疗 大幅减少了血栓并发症,并使常规支架植入术成为可能。直接PCI逐渐取代了溶栓治疗用于ST段抬高型心肌梗死21],并且有组织的 ST 段抬高型心肌梗死(STEMI)救治网络——院前心电图、救护车直接启动导管室、可量化的进门至球囊扩张时间——使得及时再灌注日益成为医疗系统可以优化的系统和后勤挑战。.
在此期间,发病率和病例病死率均明显下降,这也是定量归因最可靠的时期,因为当时记录了治疗的普及情况、已知试验疗效,且风险因素监测十分系统。这也是各种对抗因素显现的时期:肥胖和2型糖尿病开始削减成效,该时期的许多主要归因模型都将它们记录为负面贡献。.
停滞期(2010–2026)
死亡率仍远低于其历史峰值——美国缺血性心脏病死亡率达到 2022年每10万人中为135人 ——但其发展轨迹已发生了变化。在美国和英国,下降速度在大约2011年之后明显放缓。在55岁以下的成年人中,尤其是女性,长期的下降趋势已经放缓或陷入停滞,一些研究还报告了特定冠心病结果的不良趋势。22] 绝对负担依然巨大:美国记录了 2023年有915,973例心血管疾病死亡病例, ,经年龄调整的心血管疾病(CVD)死亡率为 每10万人口218.3人[23],且全球 GBD 2023 估计 1920万例心血管死亡[24],因为人口增长和老龄化会导致绝对死亡人数上升,即使个体年龄调整后的风险下降也是如此。.
造成停滞的候选解释并不光彩,且大多与技术无关:前代人从未面临过的肥胖和糖尿病水平;在吸烟本就不普遍的人群中,控烟所带来的轻易成效已经耗尽;并且在美国,有据可查的高血压控制情况恶化,源自 53.8%(2013–2014)至 43.7%(2017–2018)[25随后,COVID-19大流行导致了急剧的逆转——在25岁及以上的成年人中,美国经年龄调整的心血管疾病(CVD)死亡率从2019年的每10万人330.8人上升到2020年的346.0人和2021年的359.6人——在两年内抹去了数年的进展。. 该系列统计涵盖25岁及以上的成年人,无法与上面引用的经过不同标准化的全体成年人218.3/10万的比率直接进行对比;这两者绝不能被视为单一的发展趋势。.
表1 — 百年时间线
| 纪元 | 冠心病/心肌梗死 流行病学 | 人口与风险因素的发展 | 医疗与紧急情况进展 | 证据解释 |
| 1925–1949 | 冠心病发作率上升;缺乏可比人群的心肌梗死发病率监测数据。到1921年,心脏病已成为美国人的首要死因。. | 香烟消耗量和其他对冠状动脉产生不良影响的暴露因素急剧上升;风险因素理论当时尚未出现。. | 心电图在临床上应用日益广泛;心肌梗死的治疗则是卧床休息和支持性护理。. | 第 3/5 级。. 死亡率数据总体可靠;死因归类远不如1950年之后那样准确。. |
| 1950–1969 | 冠心病死亡率一直保持在高位,并在1968年前后达到美国历史上的最高峰。. | 弗 Framingham 研究和七国研究确定了吸烟、血压和胆固醇是可改变的危险因素;1964年美国外科医师报告。. | 体外除颤、心肺复苏、冠心病监护病房、有效的高血压治疗、首次冠状动脉旁路移植术。冠心病监护病房的设立使医院心肌梗死死亡率从约30%降至约15%。. | 2-5级。. 早期生存率的变化令人瞩目,但大体上仍属于观察性结果。. |
| 1970–1989 | 持续陡峭下降开始;美国年龄调整后的缺血性心脏病死亡率为 1970年为每10万分之693. | 吸烟率大幅下降;人口血压和胆固醇状况改善;北卡累利阿发起密集社区预防。. | 广泛的抗高血压治疗、冠状动脉旁路移植术(CABG)、经皮冠状动脉腔内成形术(PTCA)(1977年)、β受体阻滞剂、阿司匹林、, 心脏康复, ,溶栓治疗;他汀类药物在晚期时代的初期应用。ISIS-2确立了阿司匹林和链激酶的疗效。. | 1–4级。. 人群预防和循证心脏病学开始同时发挥作用。. |
| 1990–2009 | ARIC和弗 Framingham研究中,心肌梗死(MI)的发病率和病死率均大幅下降,且这种下降是可以测量的。. | 吸烟、胆固醇和血压的进一步改善,正越来越被肥胖和糖尿病所抵消。. | 他汀类药物、ACE抑制剂、支架、双联抗血小板治疗、现代急救医疗服务(EMS)、直接PCI成为主流。在随机综合研究中,直接PCI优于溶栓治疗。. | 1–4级。. 量化归因的最强时代。. |
| 2010–2026 | 死亡率远低于峰值,但 下降停滞;年轻成年人处于停滞状态,近期18至54岁住院首发ST段抬高型心肌梗死(STEMI)患者的死亡率有所恶化. 美国缺血性心脏病死亡率 2022年为每10万人口135人. | 高收入地区的烟草使用持续下降;肥胖、糖尿病和代谢风险抵消了这些成效;美国的血压控制情况恶化。. | 强化他汀类药物治疗, 依折麦布, PCSK9 抑制,优化的ACS系统,经桡动脉PCI,高灵敏度 肌钙蛋白, GLP-1 受体激动剂, 秋水仙碱. | 1–3级。. 强有力的证据证明个体治疗效果;而关于因素拆分的证据则弱得多 最近 全国趋势. |
图 1 — 美国年龄调整冠心病死亡率轨迹
观测到的国家死亡率数据。历史系列与现代系列刻意未进行数值拼接,因为年龄标准和疾病编码发生了变化。.
图表 A — 关键观测数据点
| 系列 | 年 | 每10万人口年龄调整率 | 更改 |
| 心脏病(1940年标准) | 1950 | 307.4 | — |
| 心脏病(1940年标准) | 1996 | 134.6 | −56% |
| 缺血性心脏病(现代系列) | 1970 | 693 | — |
| 缺血性心脏病(现代系列) | 2022 | 135 | −81% |
| 急性心肌梗死 | 1970 | 354 | — |
| 急性心肌梗死 | 2022 | 40 | −89% |
| 所有心血管疾病,25岁及以上成人 | 2019 | 330.8 | — |
| 所有心血管疾病,25岁及以上成人 | 2020 | 346.0 | +4.6% |
| 所有心血管疾病,25岁及以上成人 | 2021 | 359.6 | +8.7% 与 2019 年相比 |
图B — 轨迹的形状
心脏病成为美国首要死因 ………. 1921年
死亡率在20世纪30年代至60年代期间不断上升
PEAK(冠心病)……………………………………………. ~1968
持续陡峭下降 ……………………………. 1968-2010
年轻成人的衰退速度放缓/停滞;;
部分选定的急性结局恶化 …………………….. ~2011年及以后
疫情中断 ……………………………… 2020-2021
缺血性心脏病,年龄标化,每10万人口:
1970 693 ####################################
2022 135 #######
急性心肌梗死,年龄调整后,每100,000人:
1970 354 ##################
2022 40 ##
资料来源:美国历史全国死亡率分析 (CDC/NCHS)26]; King 等人 2025[2]适用于 1970–2022 年 IHD 和 AMI 系列。.
图 2 — 工具到达时
大约临床应用时间表。日期表示出现或主要证据的到来,而不是单一的普遍开始日期。.
| 句号 | 预防和慢性治疗 | 急性救援与系统 |
| 20世纪50年代 | 新型抗高血压药物不断涌现 | 体外除颤 |
| 20世纪60年代初 | 建立危险因素概念(弗雷明汉研究) | 心肺复苏术;冠心病监护病房与持续心律监测 |
| 20世纪60年代末 | 1964年美国外科医师总报告:吸烟与健康 | 冠状动脉旁路移植术进入临床实践 |
| 20世纪70年代 | β受体阻滞剂;国家高血压教育项目;北卡累利阿 | 球囊冠状动脉成形术(1977年);有组织的急诊医疗服务(EMS)扩展 |
| 20世纪80年代 | 他汀类药物问世(1987年);心脏康复规范化 | 阿司匹林和溶栓疗法在急性心肌梗死中的确立(GISSI 1986, ISIS-2 1988) |
| 20世纪90年代 | 他汀类药物终点试验(4S 1994);以血管紧张素转换酶抑制剂为基础的 二级预防 | 冠状动脉支架;直接PCI正日益取代溶栓治疗 |
| 2000年代 | 强化他汀治疗;复方制剂概念 | 公共自动体外除颤器(AED)项目;现代 ST 段抬高型心肌梗死(STEMI)救治网络;院前心电图 |
| 2010年代 | 依折麦布 结局研究(2015); PCSK9 抑制剂 (2017–18); SGLT2 抑制剂 | 高灵敏度肌钙蛋白广泛应用;桡动脉径路为标准 |
| 2020年代 | 极低LDL二级预防;秋水仙碱;GLP-1受体激动剂(SELECT 2023); 英克西兰; 贝普多酸 | 成熟的综合ACS/EMS系统;旨在降低Lp(a)水平的药物临床终点试验 |
第二部分:准确衡量衰退
关于这个主题的几乎每一个常见错误,都源于把四个不同的量混为一谈。它们虽然相关,但各自独立变动,原因也各不相同。.
冠状动脉事件发病率 人们心脏病发作的频率。. 病死率 一旦患上该病后的死亡比例。. 冠心病死亡率 大约是两者的乘积,再加上复发事件和院外猝死。. 心血管疾病总死亡率 此外,它还包括中风、心力衰竭和其他血管性死亡,因此是一个更广泛且特异性较低的指标。一种使病例病死率减半的疗法与一项使发病率减半的政策可以产生相同的冠心病死亡率降幅,但代表着完全不同的成就。.
全程有四个方法论注意事项适用。.
必须进行年龄标准化。. 随着人口老龄化,粗死亡率可能会上升,而个体的风险却急剧下降。本综述中的每一个趋势陈述,除非明确说明,否则均经过年龄调整或针对特定年龄段。这也是为什么全球心血管疾病的绝对死亡人数继续增加,而年龄标准化率却在下降的原因。.
诊断标准反复更改,这绝不是一个小问题。. 心肌梗死经历了连续的 生物标志物 20世纪70年代的AST、LDH和总CK;80和90年代的CK-MB质量和活性测定;21世纪初的常规心脏肌钙蛋白I和T;以及2010年代的高敏感肌钙蛋白测定——这些与历次心肌梗死全球定义(2000年、2007年、2012年、2018年)相叠加。27随着分析检测限从每升微克级下降到亚纳克级,肌钙蛋白的升高开始在以前不符合任何生物标志物标准的患者中被检测到。这些类别必须保持区分。. 心肌损伤 —任何超过第99百分位数的肌钙蛋白升高——本身并不是心肌梗死;只有当伴随急性心肌缺血的临床证据时,它才成为心肌梗死 缺血. 1型心肌梗死 反映粥样血栓形成;; 2型心肌梗死 需要肌钙蛋白的急性升高和/或降低 加 供需失 衡引起的缺血的临床证据; 非缺血性心肌损伤 (脓毒症,, 心肌炎, ,肾脏疾病,心力衰竭)仍然是损伤,根本不是心肌梗死。该检测方法的转变所做的是扩大了肌钙蛋白可测且异常的人群,在增加记录的NSTEMI诊断的同时,也加深了对非梗死性损伤的认识。这有时被称为 肌钙蛋白诱导的诊断 重新分类, ,并且它具有两种相反的效果:它人为地 筹集 行政数据库中记录的 NSTEMI 发病率,并且它 降低 通过纳入低危患者扩大分母,从而降低了表观总体病例病死率。当纵向应用标准化历史算法(如MONICA研究中的严格Q波心电图标准和恒定的生物标志物阈值)时,标准化心电图定义的梗死下降趋势表现为 更陡峭 比原始行政编码显示的要多。弗 Framingham 直接展示了其规模:在 1960 年至 1999 年间,, 经心电图确诊的心肌梗死发生率下降了约50%,而主要通过灵敏度日益提高的生物标志物检测出的心肌梗死病例数则大约翻了一番.[28因此,采用标准化心电图标准或明确针对生物标志物时代进行调整的监测研究(如弗雷姆汉姆心脏研究、ARIC、MONICA),比未经调整的出院编码更值得信赖。.
竞争风险至关重要。. 随着癌症、中风和其他死因的转变,面临冠心病死亡风险的人群也在发生变化。冠心病死亡率的下降并没有消灭死亡,而是将其部分重新分配到了其他死因和更高年龄段;“避免或推迟的死亡”是一个科学上诚实的表述。.
不存在长达一个世纪的心肌梗死发病率序列,也不应该人为制造这样的序列。. 诚实的说法是,可靠的国家发病率监测始于 20世纪60年代至80年代(视国家而定),在此之前的一切都是死亡率数据加上推断。.
监控实际显示的内容
美国,死亡率。. 1970年至2022年间,经年龄调整的缺血性心脏病死亡率从每10万人口693例降至135例(−81%),而编码为急性心肌梗死(AMI)的死亡率从354例降至40例(−89%) [2]。在此期间,记录最完整的一个时间段是 1980年至2000年,在此期间,年龄调整后的冠心病死亡率从 男性从每10万人口542.9下降至266.8,女性从263.3下降至134.4 [3]. 使用较旧的1940年年龄标准,“心脏病”死亡率从 从1950年的每10万人307.4人下降到1996年的134.6人; ;这些值绝不能在数值上拼接到现代2000标准系列上。26]
美国,发病率与病死率。. 弗雷明汉研究对 9,824 名参与者进行了为期 212,539 人年的随访,发现心电图定义的首发心肌梗死发病率大约下降了 1960–1999年的50%, ,而粗30天病死率从 20% 至 14%, ,一年期从24%降至21%,五年期从45%降至41%;在调整年龄和性别因素后,这三个时间段的病死率均下降了约 60% [28]。ARIC研究对四个美国社区从1987年至2008年进行了监测,并对酶到肌钙蛋白的转变进行了明确的生物标志物校正,发现每年因急性心肌梗死(MI)住院的事件发生率下降了约 白人男性的4.3%,白人女性的3.8%,黑人女性的3.4%——但黑人男性仅为1.5%, ,28天病例病死率大约下降 每年 2.6–3.6% 按群组 [29]. ARIC研究还记录到,随着时间的推移,梗死本身变得更小、更不严重。30]
当代负担. 尽管有所下降,但美国仍记录了 2023年有915,973例心血管疾病死亡病例, ,经年龄调整的心血管疾病(CVD)死亡率为 每10万人口218.3人 而2022年为224.3。[23] 全球范围内,GBD估计大约 2021年缺血性心脏病死亡人数达900万 其年龄标准化缺血性心脏病死亡率约为 每10万人中有108.7人, ,代表大约 32%:自1990年以来,年龄标准化率呈下降趋势 — 与 2023年总共发生1920万例心血管死亡.[24] 年龄标化风险正在下降;绝对负担并没有下降。.
第三部分:原因探究:归因文献
模型的工作原理,以及它们能告诉你什么和不能告诉你什么
关于“多少归功于医疗,多少归功于预防”这一问题,最直接的有力回答来自 IMPACT 型模型, ,由凯普韦尔(Capewell)及其同事于1996年开发,并已应用于二十多个国家[3,4]. 该方法基于观察到的人口风险因素变化、治疗接受情况、临床试验得出的疗效估计值、患者数量以及病死率,探讨相对于基准年,可将多少“预防或推迟的死亡”归因于每个组成部分。 研究表明,这些模型能够解释英格兰、苏格兰、爱尔兰、新西兰、芬兰、瑞典和美国大部分观察到的死亡率变化——具体而言,模型中各组成部分的总和通常能再现85–100%的观察变化。 这属于校准和内部核算,而非对因果归因本身的独立验证:模型可能再现了总和,却在各组成部分之间的分配上存在偏差。.
这些是 引入了外部估计因果效应大小的第四层归因模型,而非随机实验, ,并且它们产生的百分比取决于模型。它们的价值在于,同样的宏观发现在历史背景截然不同的群体中不断重复: 风险因素的变化通常比治疗更能解释死亡率的下降,但这两者的作用都很大。.
重复计算问题及其处理方法
这是该领域最核心的方法论问题,也是大多数随意分析出错的地方。人群平均血压的下降部分是由降压药引起的[10部分源于饮食和钠摄入量,部分源于体重,部分源于其他长期趋势。人群胆固醇水平的下降,部分归功于他汀类药物,部分归功于饮食改变,部分归功于食品中反式脂肪的去除。如果你把药物的作用归功于“医学”,又把整个观察到的风险因素变化单独归功于“生活方式”,你就重复计算了同一种生物学改善。.
实施良好的 IMPACT 模型 处理方式有三。首先,在诸如瑞典分析等定义明确的实施方案中,接受相关治疗的个体被从人群风险因素计算中剔除,因此服用他汀类药物患者的胆固醇下降归功于他汀类药物,而非“饮食”。这种处理方式因实施方案而异,并未在所有IMPACT模型中得到完全相同的应用。其次,采用Mant–Hicks方法,将并发疗法的益处以相乘而非相加的方式结合起来,从而使同时服用阿司匹林、β受体阻滞剂和他汀类药物的患者不会被计入这三种药物的算术总和 相对危险度 缩减。第三,对重叠的处理人群进行了明确列举和调整。.
瑞典的分析是最透明的演算实例。在1986年至2002年期间,, 总胆固醇 在瑞典人群中下降了 0.64 mmol/L。该模型将大约 因饮食改变而避免或推迟的死亡人数为5,210人,因服用他汀类药物而避免或推迟的死亡人数为810人. 吸烟量的减少大约减少了1,195例死亡。收缩压下降2.6毫米汞柱大致相当于 900例由于自然病程死亡,575例由于抗高血压治疗死亡. 大约四分之三归因于这三个主要危险因素的死亡率下降发生在未诊断出冠心病的人群中——也就是说,在 一级预防.[10]
模型也适用 合规折扣 反映真实世界的持久性,而不仅仅是试用 坚持 — 通常假设急性住院期间的依从性为100%,有症状门诊患者约为70%,无症状一级预防人群约为50%。这一点很重要:若在将试验疗效应用于处方数据时未进行折扣调整,就会系统性地高估治疗比例。.
即使在优秀的实施方案中,残余重复计算仍然可能发生,这是一个既定的局限性,而非一个已解决的问题。.
生物滞后时间:为什么归因窗口很重要
另一个很少被明确处理的复杂之处在于,不同的干预措施在不同的时间尺度上起作用,因此根据其采用的时间,同一个日历窗口可能会美化或贬低某项特定的干预措施。.
数周至数月。. 戒烟和抗血小板治疗能迅速降低冠心病风险——在主要解剖学改变发生之前 斑块 预计会有所改变。.
一到两年。. 在随机对照试验中,药物降脂在大约 12-18 个月内即可使事件曲线分离开来31],这比预期管腔几何形状发生大变化的时间要早——该机制通常归因于 斑块稳定 而不是解剖学上的消退,尽管试验证据确立了结果效应,而非其机制。.
数十年. 累积 载脂蛋白B 曝光32] 以及长期血压负荷在数十年间发挥作用,影响动脉粥样硬化的发展和血管损伤。这就是20世纪70年代和80年代人口水平胆固醇下降所依据的时间尺度——这也是为什么比较1980年和2000年的模型可能捕捉到 死亡后果 始于二十年前的饮食结构变化,却将其归因于错误的时间窗口。.
表 2 — 主要归因研究
| 研究 / 人群 | 句号 | 观察到的冠心病死亡率下降 | 风险因子贡献 | 治疗贡献 | 其他/未解释 | 访问,层级,标识符 |
| 福特 等人,美国 | 1980–2000 | 男性 542.9→266.8/10万;女性 263.3→134.4/10万; 2000年减少了341,745例死亡 | 44% | 47% | ~9% | 全文已审阅;; 第四级. 新英格兰医学杂志 2007; DOI 10.1056/NEJMsa053935; PMID 17554120[3] |
| 乌纳尔等人,英格兰与威尔士 | 1981–2000 | −62% 男性,−45% 女性; 减少了 68,230 例死亡 | 58% | 42% | 经历不利趋势后,模型大致完成 | 摘要已审阅;; 第四级. 循环 2004; PMID 14993137[4] |
| Laatikainen 等人,芬兰 | 1982–1997 | −63% | 53–72% | 23% | 残差/模型不确定性 | 摘要已审阅;; 第四级. 美国流行病学杂志 2005; DOI 10.1093/aje/kwi274; PMID 16150890[5] |
| 比约克等人,瑞典 | 1986–2002 | −53.4%(男性),−52.0%(女性); 减少 13,180 例死亡 | 55% | 36% | ~9% | 摘要 + 开放式后续全文;; 第四级. DOI 10.1093/eurheartj/ehn554; PMID 191415626] |
| 阿斯佩隆德等,冰岛 | 1981–2006 | −80%; 心肌梗死发病率 −66% | 73% (灵敏度 54–93%) | 25% (8–40%) | ~2% | 已审阅摘要/结果,打开全文;; 第四级. DOI 10.1371/journal.pone.0013957; PMID 21103050[7] |
| 爱尔兰 IMPACT | 1985–2000 | −47% | 48.1% | 43.6% | ~8.3% | 摘要已审阅;; 第四级. PMID 16537349[8] |
| Bandosz 等人,波兰 | 1991–2005 | −54%; 2005年减少了26,200人死亡 | 54% (胆固醇/膳食脂肪 39%,身体活动 10%,男性吸烟 15%) | 37% | 余数 | 摘要已审阅;; 第四级. 英国医学杂志 2012 |
| 科普曼等人,荷兰 | 1997–2007 | −48% (269→141/100,000); 减少约 11,200 例死亡 | ~36% (SBP 30%、胆固醇 10%、吸烟 5%) | ~37% | ~27%(型号说明:~72%) | 摘要已审阅;; 第四级. PLoS One 2016 |
| 北卡累利阿(社区内) | 1972–1986 | 早期缺血性心脏病发病率显着下降 | 三大危险因素的可观测变化预测了绝大多数早期发病率的下降,远超参考区域(具体百分比归因需要原始资料验证) | 未单独分配 | — | 二级/四级 自然实验. 国际流行病学杂志 1989;DOI 10.1093/ije/18.3.59535] |
这些百分比绝对不能平均得出一个通用常数。. 它们之所以不同,是因为基线吸烟、胆固醇和高血压的患病率不同;因为治疗普及率不同;因为各个国家是在技术扩散的不同阶段被研究的;因为年龄范围不同;并且因为模型包含略有不同的组成部分。英格兰和威尔士看起来受吸烟影响为主,是因为英国的吸烟流行情况异常严重且其逆转速度异常迅速。美国显示出最大的治疗占比,部分原因正在于它恰好是在美国治疗普及率增长最快的几十年里被研究的。.
一个可辩护的综合
对于在20世纪70年代至2000年代主要下降期间的高收入国家:
- 人口风险因素变化:约45–70%
- 预防和长期治疗(包括二级预防、心力衰竭护理、高血压和血脂治疗、, 血运重建 用于慢性 心绞痛): 约 15–40%
- 急性心肌梗死/急性冠状动脉综合征的直接治疗:约5–10%,偶尔可达~12%
- 显式模型残差:从几个百分点到约10%
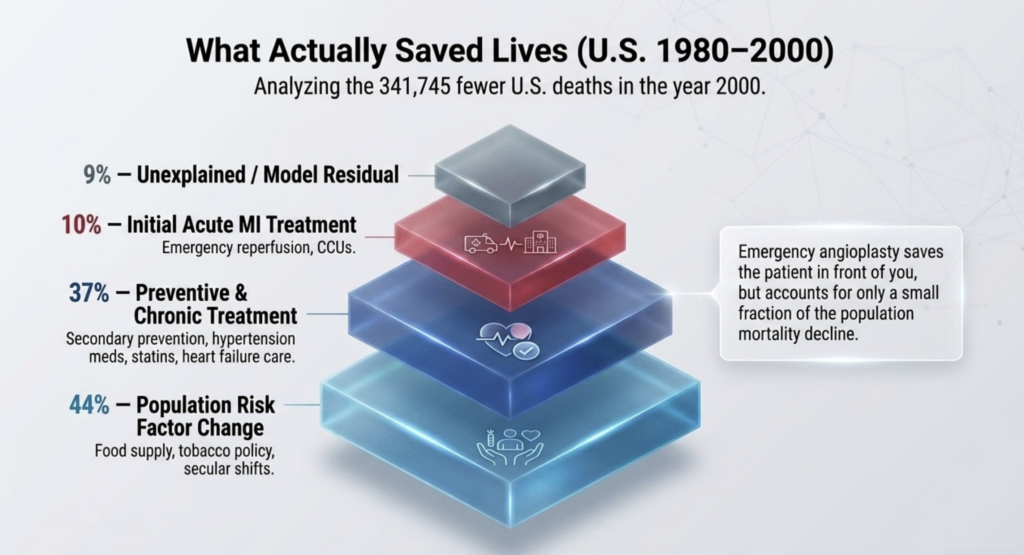
A组与全部治疗的比较要比B/C分组更为可靠,因为后者在不同研究中并未采用统一标准。就美国而言,已公布的47%总治疗占比中,包含10%用于急性心肌梗死(AMI)的初始治疗,以及 不稳定型心绞痛, ,允许美国本土的—— 不通用 — 重新分类大约 44% A、37% B、10% C、9% D. 37% 这一数字是一个 通过减去福特等人(Ford et al.)的数据衍生出的作者重新分类., ,并非该论文中公布的类别。.
图3 — 具体分解(美国,1980–2000年)
模型估计,并非随机分解,也不是通用的百年饼图。.
A 人群风险-风险因子变化 44% ######################
B 预防性/慢性治疗* 37% ###################
C 急性心肌梗死/不稳定型心绞痛 10% #####
D 无法解释的 / 模型残差 9% ####
* 作者重新分类,并非已出版的分类。.
B = 已发表的 47% 总治疗量减去已发表的 10%
急性心肌梗死/不稳定型心绞痛成分。因此,它包括
二级预防,心力衰竭护理,高血压
治疗,以及慢性心绞痛血运重建——不仅
预防首次心肌梗死的药物.
在急性类别中,福特及其同事分别计算出 仅初期急性心肌梗死(AMI)治疗就避免或推迟了约21,570例死亡,占死亡总数下降幅度的6.3%。, ,敏感度边界为 2.6–11.0%.[3] 这是纠正“急诊血管成形术解释了冠心病死亡率在人群层面下降”这一直觉的最有用的纠正方法。在人群层面,它显然没有——无论它对你面前的个体患者产生多么巨大的影响。.
哪些风险因素最重要?
这三项风险因素——胆固醇、吸烟和血压——始终存在,但其排名会因当地历史背景而发生显著变化。在美国1980–2000年的模型中,总胆固醇水平的降低占降幅的24%,而较低的 收缩压 202TP9T,吸烟率下降12%,以及久坐行为减少5%;身体质量指数(BMI)上升和糖尿病的增加抵消了相当于 8% 和 10% 分别。在冰岛,胆固醇、吸烟和血压分别导致了32%、22%和22%。在英格兰和威尔士,仅吸烟一项就导致了48%。[4]
表3 — 各独立危险因素的贡献
| 风险因素 | 近似总体均值漂移(见注) | 各大 IMPACT 分析中观察到的冠心病 (CHD) 死亡率下降的大致份额 | 解释 | 信心 |
| 总胆固醇人群下降 (部分反映了较低的致动脉粥样硬化脂蛋白暴露) | 美国及其他高收入国家系列数据出现实质性长期下降 | 关于 10–45%: 美国 24%、冰岛 32%、爱尔兰 30.2%、波兰 39%;在瑞典占主导地位 | 这是最大的累积贡献者之一,尽管其排名因国家而异。由食物环境与药物所占的比例随时代显著变化——在20世纪90年代中期之前,主要为非他汀类药物,且可能在很大程度上与饮食和食物供应的变化有关;此后,药物治疗的作用日益增加。. | 中等至高 |
| 减少吸烟 | 美国成年人的患病率从1965年的约42%降至近年来约12% | 大约 9–48%: 美国 12%,冰岛 22%,爱尔兰 25.6%,英格兰/威尔士 48% | 巨大的异质性,反映了不同的流行病学起点和烟草控制步伐。在因果关系上,它是所有危险因素中最确凿的。. | 高 为了因果关系;; 适度 为了准确标明出处 |
| 降血压 | 在许多高收入人群中,平均收缩压大幅下降 | 大约 6–22%: 美国 20%,冰岛 22%,英格兰/威尔士 9.5%,爱尔兰 6% | 包含世俗人口下降,除非药物效应已被单独分割,如瑞典所示。. | 高 为了因果关系;; 适度 对于历史份额 |
| 体力活动 / 不活动 | 不活动人群比例呈轻微下降趋势 | 通常 1–10% (如模型所示);美国 5%,波兰 10%简体中文(大陆) | 自我报告和常规监测明显弱于吸烟、血压或胆固醇。. | 低至中等 |
| 与胆固醇和血压无关的饮食 | 未单独量化 | 不安全的可加性 对胆固醇和血压贡献 | 瑞典分解法将大部分由胆固醇介导的益处归因于饮食。计算“饮食” 加 它引起的胆固醇下降重复计算了一个生物学途径。. | 适度 |
| 肥胖症 | 平均BMI显著上升;截至2020年,美国成年人肥胖人数已超过42% | 负面: −1.5% 至 −8% 跨模型;美国不断上升的 BMI 增加了相当于 8% 本应发生的下降 | 肥胖削弱了这种下降趋势,但并没有导致它。. | 适度 |
| 糖尿病 | 美国确诊病例数增长了数倍,超过11% | 负面: −2% 至 −10% 跨模型;相当于美国抵消额 10% | 糖尿病发病率的上升阻碍了冠心病死亡率的进一步大幅下降。. | 中等至高 |
第二列说明:这些是基于不同国家序列、年龄范围和时期(主要为美国和其他高收入国家的数据)得出的长期变化的数量级总结。它们旨在传达方向和大致规模,而非来自单一来源数据集的合并测量值,亦不应被引作精确的人口统计数值。.
有一个观察值得强调,因为它对整个论证具有决定性意义: 在大规模使用他汀类药物之前,相当一部分人群的胆固醇水平就已经在下降。 — 他汀类药物直到1987年才上市,直到20世纪90年代末才在初级预防中得到广泛应用。一个重要的促成因素似乎是膳食脂肪成分和食品供应的变化——用多不饱和脂肪替代了 单不饱和脂肪 对于饱和动物脂肪,以及后来的工业监管淘汰 反式脂肪, ,从2003年的丹麦开始,随后是欧盟的法规以及美国食品药品监督管理局(FDA)撤销GRAS(公认安全)地位36]。在IMPACT模型中,人口胆固醇水平的下降约占 24–39% 在几个国家的总降幅中;在有明确分解的研究中,他汀类药物普及前的大部分降幅归因于非药物因素的变化,而截至2000年,他汀类药物对人群胆固醇变化的贡献率仅为百分之几。.
同样,全人群血压下降的相当大一部分发生在未服用抗高血压药物的人群中。该非药物成分背后的机制在文献中尚未明确划分,不应盲目归因于任何单一的饮食或环境原因。.
简报所强调的那种区别值得重申:这些是 人群暴露, ,而不是道德范畴。烟草税收、无烟立法、工业反式脂肪的消除、加工食品中钠含量的重新配方,以及食品供应和成分的更广泛变化,都不是“生活方式的选择”。它们是政策和供应链干预措施,改变了整个人群中风险的分布,它们与个人行为改变一样,属于风险因素这一栏。.
第四部分:预防:随机化证据的真实证明
历史归因询问什么 做 发生在人群中。随机试验则回答了关于某种疗法的作用的互补问题 可以 因为它对接受治疗的患者所产生的疗效。这些是不同的问题,绝不能混为一谈。一种药物对于个别患者可能极其有效,却几乎无法解释历史上的任何死亡率下降,这仅仅是因为在死亡率下降发生时该药物尚未问世。.
降低血压
血压 降低 治疗 临床试验 合作组织 汇总了来自以下机构的个体参与者数据 48项随机试验中的344,716名参与者. 对于每一个 收缩压降低 5 mmHg, 主要心血管事件减少了约 10%: 风险比 0.91(95% 置信区间 0.89–0.94) 在之前没有参与过的参与者中 心血管疾病 以及 0.89 (0.86–0.92) 在既往患病者中亦是如此。无论基线血压分层如何,均能获益,包括那些血压传统上不属于“高血压”的人群37] (一级). 根据本研究及BPLTTC相关研究得出的各组成部分估计值显示,每降低5 mmHg,中风风险可降低约13%,缺血性心脏病风险可降低7%,心力衰竭风险可降低14%,心血管死亡风险可降低5%。.
这赋予了历史关联以因果解释。归因模型中归因于“血压变化”的部分死亡率改善,确实归功于药物;部分则是由于长期的群体人口结构转变。瑞典之所以极其宝贵,恰恰是因为它试图将这两者区分开来。.
降低低密度脂蛋白和载脂蛋白B
斯堪地那维亚辛伐他命生存研究(4S,1994)开启了这个时代,降低了 全因死亡率 由 30% 以及冠心病死亡率 42% 在已确诊冠心病的患者中20] — 一项具有里程碑意义的试验,证明了他汀类药物介导的胆固醇降低延长了生命,而不仅仅是改变了实验室检查值。.
胆固醇治疗试验协作组随后对这种关系进行了定量分析。在26项试验和大约17万名参与者中,每一 低密度脂蛋白胆固醇(LDL-C)降低 1.0 mmol/L (38.7 mg/dL) 生产了一个 22% 可降低主要血管事件的发生率(RR 0.78,95% 置信区间 0.76–0.80), a 20%可降低冠心病死亡率(RR 0.80,99% 置信区间 0.74–0.87), ,和一个 10%可降低全因死亡率(RR 0.90,95% 95% CI 0.87–0.93) ——后者完全由血管性死亡驱动,癌症或非血管性死亡并无增加。31] 在个体参与者 元分析 的 27项随机试验 专注于低风险参与者,主要血管事件的率比为 每1.0 mmol/L为0.79(95% 置信区间 0.77–0.81); ;在没有既往血管疾病的参与者中,血管相关死亡率随着相对风险(RR)下降 0.85 (0.77–0.95) 以及全因死亡率的相对风险(RR) 0.91 (0.85–0.97) 每 1 mmol/L38] (一级)在不同的基线风险、年龄和性别中,成比例的获益非常一致,且在随机试验测试的范围内未显示出获益的下限阈值。.
非他汀类药物临床试验证实,其获益程度与以下因素相关: 低密度脂蛋白 降低而不是代表他汀类药物的特异性。在 IMPROVE-IT, ,随后加用依折麦布 急性冠状动脉综合征 将七年复合事件发生率从 34.7% 至 32.7%, ,HR 0.936(95% 置信区间 0.89–0.99) [39]. 在 傅里叶, 依洛尤单抗 降低了主复合材料 11.3% 至 9.8%, ,HR 0.85 (0.79–0.92), ,以及心血管死亡/心肌梗死/卒中复合终点来自 7.4% 至 5.9%, ,HR 0.80 (0.73–0.88) [40]. 在 奥德赛 结果, 依洛尤单抗 ACS减少后 主要不良心血管事件 从 11.1% 至 9.5%, ,HR 0.85 (0.78–0.93) [41]。全部都是 一级.
这正是 chronology 最重要的地方。. 这些疗法是当代实践中最重要的工具之一,它们不可能因为在其问世几十年前就开始的下降趋势而获得事后的功劳。冰岛模式涵盖1981年至2006年期间,仅指定了 他汀类药物治疗导致的历史死亡率下降幅度为0.5% 在赋值时 32%可使胆固醇水平总体下降[7] ——因为在该时间窗口的大多数时间内,人群胆固醇水平的下降在很大程度上是非药物性的,并且很可能在很大程度上与饮食和食物供应的变化有关。正确的解读并不是他汀类药物不重要;而是他汀类药物很重要 现在, ,且基本不存在 然后. 任何将二十世纪死亡率下降归功于他汀类药物的分析,都是将时间的方向弄颠倒了。.
抗血小板治疗与二级预防综合干预措施
ISIS-2 仍然是心血管医学中最明确的结果之一。在 17,187 名疑似急性心肌梗死患者中,单用链激酶将五周时的血管性死亡率降低了 12.0% 至 9.2%; ;仅阿司匹林来自于 11.8% 至 9.4%; 以及大约组合 13.2% 至 8.0%, ,胜算降低约 42% [18] (一级)。一种成本仅需几美分的药物能带来如此幅度的死亡率获益,对于抑制人们对昂贵替代疗法的盲目热情,依然是一个有益的警示。.
对于长期使用,抗栓试验者协作组织在预防背景之间作出了决定性的区分。在 二级预防, ,阿司匹林使严重血管事件减少了 19% (每年6.7%与8.2%相比),其绝对获益远大于出血风险。在 一级预防, ,减少幅度仅为 12% 在主要血管事件方面(每年0.51%与0.57%),这一差异完全由非致死性心肌梗死所致,对血管死亡率无显著影响,且被大约一个 42% 主要胃肠道和颅外出血风险增加[42]。这就是为什么现代指南不再推荐常规使用阿司匹林进行一级预防——这是一个罕见的证据基础缩小而非扩大适应症的例子。.
归因模型估计,联合指南指导的二级预防方案(抗血小板药物、他汀类药物、ACE抑制剂或ARB以及β受体阻滞剂)在各成分以相乘而非相加的方式结合时,可产生巨大的累积相对风险降低。已发表的复合数据应被视为汇总了异质性终点和试验年代的模型估计值,而非实测值。出院后多年内,现实世界对多药方案的依从性会显著下降,这就是复方单片药(polypill)的理论基础。.
在人群层面,二级预防 捆绑 作出了重大贡献。在美国,心肌梗死或血运重建后进行的治疗约占 1980–2000年期间冠心病死亡人数下降总量的11% ——比单纯的初始急性心肌梗死治疗更多。固定剂量复方疗法的主流试验证实了该治疗包的价值,并证明了依从性作为一个主要可调整限制因素的重要性: 安全 心肌梗死后多效复方药(阿司匹林、雷米普利、, 阿托伐他汀) 使主要复合终点降低了 24%(HR 0.76,95% CI 0.60–0.96),心血管死亡降低了 33%(HR 0.67,0.47–0.97)[43]
表 4 — 重大医学进展
| 干预 | 采纳/证据时代 | 对心肌梗死发病率的影响 | 对心肌梗死死亡率的影响 | 证据与标识符 |
| 抗高血压治疗 | 自20世纪60年代起开始实施;自20世纪70年代起广泛普及 | 强力预防: 收缩压每降低5毫米汞柱,主要心血管事件风险降低约9–11% | 减少致死性和非致死性血管事件;历史上对人群健康作出了巨大贡献 | 一级 RCT荟萃分析。DOI 10.1016/S0140-6736(21)00590-0;PMID 3393320537] |
| 他汀类药物 | 1987年推出;1994年获得结果证据;20世纪90年代末至21世纪大规模普及 | 强力预防: 每降低1 mmol/L的LDL,主要血管事件的风险比(RR)为0.79(0.77–0.81);在整个项目中,每降低1 mmol/L的风险比约为22% | 适宜人群的心血管及全因死亡率获益 | 一级 个体参与者数据荟萃分析。DOI 10.1016/S0140-6736(12)60367-5;PMID 2260782238] |
| 依折麦布 | 结果证据 2015 | 急性冠状动脉综合征(ACS)后的增量预防:7年时复合终点为34.7%→32.7% | 综合效益;并非主要表现为死亡率结果 | 一级. DOI 10.1056/NEJMoa1410489; PMID 26039521[39] |
| PCSK9抑制 | 结果证据 2017–2018 | FOURIER HR 0.85;ODYSSEY HR 0.85(ACS后) | 强有力的事件预防;死亡率效应取决于人群和随访时间 | 一级. PMID 28304224; DOI 10.1056/NEJMoa1801174[40] |
| 阿司匹林(急性期和二级预防) | 1988年决定版 | 减少复发性缺血事件;广泛的一级预防受出血限制 | ISIS-2:阿司匹林可将急性血管性死亡风险降低约23%;链激酶可降低约42% | 一级. PMID 2899772[18] |
| 阿司匹林(一级预防) | 重新评估 2009–2019 年 | 主要血管事件仅减少了12%,这主要归因于非致死性心肌梗死 | 对血管性死亡率无显著影响;但因多发生约42%例重大出血而抵消了这一效果 | 一级, ,抗栓试验合作组织,, 柳叶刀 2009[42] |
| β受体阻滞剂,ACE抑制剂 / ARB | 20世纪80年代 / 90年代 | 对发 incidence 的影响不大 / 对发生率的影响较小 | 随机试验和荟萃分析已证实其对心肌梗死后(post-MI)及射血分数减低型心力衰竭(HFrEF)历史患者的生存获益;当代的长期心梗后适应证取决于左心室(LV)功能及其他适应证 | 一级[44,45,46] |
| 溶栓疗法 | 1986–1990年代 | 无 — 在事件发生后重新打通动脉 | 在符合条件的ST段抬高/束支传导阻滞患者中,0–6小时内每治疗1,000人减少约30例死亡;7–12小时内每1,000人减少约20例死亡 | 一级, ,纤溶疗法临床试验协作组;PMID 790514347] |
| ST段抬高型心肌梗死急诊经皮冠状动脉介入治疗 | 20世纪90年代及以后 | 无 在首次事件中;与溶栓相比,可减少再梗死 | 23项试验综合分析:短期死亡率 7% 与 9%; 再梗死 3% 与 7%; 中风 1% 与 2% | 一级. doi: 10.1016/S0140-6736(03)12113-7; PMID 1251746021] |
| CCU / 遥测 / 除颤 | 20世纪60年代初及以后 | 无 | 历史医院死亡率 30%→15%;一项随机对照研究:15.3% 与 29.3% 对比(普通病房的相对风险为 2.3,95% 置信区间为 1.1–4.8)[13] | 二级 (单项小型RCT)13] 加 第5层 历史剧14] |
| 公共自动体外除颤器 | 20世纪90年代–2000年代 | 无 | PAD 试验: 128起确定逮捕中的30名幸存者 配合CPR+AED与 107分之15 仅凭心肺复苏术 | 一级. DOI 10.1056/NEJMoa040566[48] |
| 冠状动脉旁路移植术 | 1968年及以后;1972–1984年审判 | 减少特定解剖结构患者的自发性心肌梗死 | 生存获益集中于左主干和三支病变;一至两支病变者获益极小或无 | 一级, ,Yusuf 等人[19] 柳叶刀 1994[19] |
| 稳定型冠状动脉疾病的经皮冠状动脉介入治疗 | 20世纪80年代及以后 | 无针对普通人群的预防作用 | 缺血:在中位 3.2 年的随访期内,缺血性事件或全因死亡没有减少;死亡风险比(HR) 1.05 (0.83–1.32) | 一级. DOI 10.1056/NEJMoa1915922; PMID 32227755[49] |
| GLP-1 受体激动剂 | 2016–2023年成果证据 | 预防 在肥胖中 没有 糖尿病(SELECT):MACE 6.5% 与 8.0%,HR 0.80(0.72–0.90);在 2 型糖尿病中存在单独的心血管结局证据 | 减少主要不良心血管事件(MACE);SELECT研究证实了这一点 不 证实仅就心血管死亡而言,其发生率出现了具有统计学意义的下降(2.5% 对比 3.0%,HR 0.85,95% CI 0.71–1.01) | 一级. 新英格兰医学杂志 2023; DOI 10.1056/NEJMoa230756350] |
| 秋水仙碱 | 成果证据 2019–2020 | 减少既往疾病的复发事件 | COLCOT 将其主要复合指标降低了约 23%(HR 0.77,95% 置信区间 0.61–0.96)[51]; LoDoCo2 作者:~31%(HR 0.69)[52] | 一级, ,但 CLEAR SYNERGY/OASIS-9 的结果为中性(HR 0.99,95% 置信区间 0.85–1.16)[53] |
第五部分:营救:心脏病是如何不再成为死刑判决的
将预防与救援区分开来的方程式
在群体水平:
冠心病死亡率 ≈ 冠心病事件发生率 × 病死率
加上循环事件、院外猝死、竞争风险以及编码带来的额外贡献。这就是使核心问题得以解答的方程式。如果病死率下降而发病率持平,则收益来自抢救。如果病死率下降而病死率(致死率)持平,则收益来自预防。通常两者都在变化。.
这 WHO MONICA 项目 恰好利用了这一点跨越 21个国家中的37个种群 在大约1983至1993年期间,通过标准化的冠心病事件判定——这是一项规模空前且从未被再次复制的非凡而后勤成就。核心发现是,在死亡率下降的人群中,, 约三分之二的下降可归因于冠心病事件发生率的下降,约三分之一归因于病例病死率的改善, ,国家和性别之间存在显著差异 [9] (第三层级). 一项配套分析将冠心病治疗和二级预防水平的提高直接归因于病死率的下降:当治疗评分出现常见的20分变化时, 男性病例死亡率下降约19%,女性下降约16%;事件发生率分别下降约25%和23%;冠心病死亡率分别下降约42%和34%。[54]
由于 MONICA 研究的年龄范围主要在 25–64 岁,这些比例不应被机械地推算到当代的老年人口中,在这些老年人群中,各比例的平衡可能会有所不同。.
表 5 — 不同年代的急性心梗生存率
说明性历史区间 — 不具直接可比性。本表为示意性的历史综合,而非单一来源的数据集。. 这些区段由跨越七个年代的异质队列、诊断标准和人群组合而成,因此各个年代的数值仅具指示性,而非可直接比较的测量结果。跨年代的比较必须谨慎解释,因为现代的高灵敏度肌钙蛋白能够检测出早期年代根本无法计入的较小面积心梗——这本身就会降低测得的病例病死率。下方图表中单独来源的队列承载着证据的分量;而年代区段则用于引导读者。.
| 纪元 | 住院病例病死率 | 28/30天病死率 | 早期死亡的主要方式 | 治疗环境 |
| CCU前,1950–1961年 | ~30% | ~40% | 心脏性猝死原发性心室颤动 | 严格卧床休息,吗啡,吸氧 |
| 早期冠心病监护病房,1962–1975年 | ~15% | ~25% | 心源性休克;进行性泵衰竭 | 持续遥测,直流电除颤,利多卡因 |
| 早期再灌注,1976–1989 | ~10% | ~15–20% | 心源性休克;游离壁破裂 | 静脉溶栓,急性口服阿司匹林,β受体阻滞剂 |
| 直接经皮冠状动脉介入治疗与支架植入术,1990–2009年 | ~5–7% | ~10% | 心源性休克;多器官功能衰竭 | 直接PCI(进门-球囊扩张时间<90分钟)、双联抗血小板治疗(DAPT)、ACE抑制剂 |
| 当代网络,2010–2026年 | ~4–6% | ~7–9% | 非心脏合并症;难治性休克 | 经桡动脉优先急诊PCI、选择性机械循环支持、强效P2Y12受体抑制剂、指南导向的二级预防 |
验证社群和队列数据
| 来源 | 发现 |
| 伍斯特心脏病发作研究,1975–2005年 | 初次急性心肌梗死(AMI)后的医院生存率从 81%(1975年)至 91%(2005年) — 即院内死亡人数从大约 19% 降至 9% — 这是全社区范围的数据,而非特定医疗机构的统计[55]。年龄调整的住院病死率此前已经从 22.2%(1975年)至 15.1%(1984年) 在同一个社区内56] |
| 弗雷明汉,20世纪60年代→90年代 | 30天粗病死率 20%→14%;经年龄和性别调整后的30天、1年和5年病死率分别为约~60% 下部 |
| ARIC,1987–2008 | 28天病例病死率下降约每年 2.6–3.6% 根据性别/种族群体 |
| 日本宫城,1979→2008 | 年龄调整的院内死亡率 20.0%→7.8% — 同时发病率 玫瑰 |
| 随机 CCU 比较[13] | 15.3%(17/111,CCU)与 29.3%(27/92,普通病房); 普通病房死亡的相对风险为 2.3(95%,置信区间 1.1–4.8) |
另一个独立的增长来自于 SHOCK 试验,[57] 显示了与最初药物稳定治疗相比,早期血运重建能够带来长期的生存获益,尽管其主要终点即30天死亡率的比较未达到统计学显著性。它解决了这样一种失效模式:一旦冠心病监护病房在很大程度上解决了心律失常问题,这种失效模式便取代了心室颤动,成为了院内死亡的主要原因。.
从因果关系的视角来看,干预措施
冠心病监护病房 针对在最初几小时内夺去人命的故障模式——室颤进行了攻击。它不需要药物,只需要持续观察和房间内的一个除颤器。其证据基础不如其合理性那么强,但时间信号既明显又一致。.
心肺复苏术与公众除颤 在院外攻克同样的失效模式,而大多数 心脏性猝死 发生。随机公共交通除颤试验发现 128名确诊患者中有30名医院幸存者 心脏骤停 在接受了心肺复苏加自动体外除颤器(CPR+AED)培训的社区中,相比于 107分之15 在仅进行心肺复苏(CPR)的社区中48] (一级) 这是一个在医院统计数据中看不见的效益类别,因为相关的患者在此之前甚至在到达医院之前就已经死亡了——它在不降低潜在动脉粥样硬化事件发生率的情况下,降低了冠心病死亡率。.
纤维蛋白溶解 是一项真正的死亡率突破性进展。纤维蛋白溶解治疗试验协作组(Fibrinolytic Therapy Trialists’ overview)对大约 58,600 名随机患者的综合分析发现,绝对获益约为 每千人减少30例死亡 当在六小时内开始治疗并且大约 每千分之二十 在7-12小时内,适用于有ST段抬高或束支传导阻滞的患者——而对于没有这些情况的患者则无益,且可能有害47] 35天死亡率的相对降低幅度约为18%。.
直接PCI 随后对纤维蛋白溶解进行了改进。Keeley及其同事对23项试验和7,739名患者进行的荟萃分析发现,短期死亡率为 7%(联合初级血管成形术)与9%(联合溶栓治疗)的比较, ,再梗死 3% 与 7% 的对比, ,中风 1% 与 2% 的对比, ,以及死亡、再次心肌梗死或卒中的复合终点 8% 与 14% 的对比 [21]
急诊医疗服务体系、院前心电图与ST段抬高型心肌梗死(STEMI)救治网络 不是治疗本身,而是决定治疗是否能及时送达的输送机制。它们的贡献是真实的,且在很大程度上无法被归因模型所察觉,因为它们融入了观察到的病死率改善之中,而不是作为一个单独的项目出现。.
日本:具有决定性的反例
任何认为冠心病死亡率下降必然意味着心脏病发作减少的说法都被日本的情况所反驳。在包含22,551名患者的MIYAGI-AMI登记研究中,经年龄调整的急性心肌梗死发病率 在1979年至2008年期间,从每10万人口7.4上升至27.0, ,而经年龄调整的住院死亡率 从 20.0% 降至 7.8% 随着救护车的使用和直接经皮冠状动脉介入治疗的普及58]。该登记处还报告称,2008年女性的死亡率明显高于男性—— 12.2% 与 6.3% —这一性别差异在其他人群中也有报道,包括当代美国年轻人的数据。59]
秋田-大阪研究60] 同样发现了异质性的日本长期趋势,在城市男性中,经年龄调整的心肌梗死(MI)发病率从 1964–1971 年的每 10 万人 45 例上升到 1996–2003 年的每 10 万人 90 例,伴随着胆固醇水平和 BMI 的恶化,但吸烟率有所下降。西方的发展轨迹并非普遍适用,一个国家可以在预防方面失守的同时,实现生存率的大幅提升。.
第六部分:血运重建术:同名异义的三种不同手术
“血运重建”并不是一个单一的因果类别,将其视为单一类别是该文献中最常见的分析错误之一。.
ST段抬高型心肌梗死急诊经皮冠状动脉介入治疗 是对当前正在发生梗死患者的闭塞动脉进行紧急再灌注。如上所述,它可以挽救生命。.
特定解剖结构下的冠状动脉旁路移植术 延长生命。两个不同的证据基础不应合并。在 冠状动脉解剖, ,CASS和退伍军人事务部合作研究证实了左主干病变患者的生存获益 狭窄 以及伴有前降支(LAD)近端病变的三支病变。在 缺血性 心肌病 伴有严重左心室功能障碍 — STICH 及其长期随访显示,通过由心室功能而非解剖结构定义的另一类人群,在药物治疗的基础上加用外科血运重建术,可带来长期的生存获益。61] FREEDOM 随后表明,在糖尿病多支血管病变中,与支架植入术相比,CABG 降低了死亡率和心肌梗死发生率。62Yusuf对1972年至1984年间7项随机试验和2,649名患者的荟萃分析发现,生存获益集中在 左主干病变(五年比值比 0.32) 以及 三支血管病变 (OR 0.58), ,在单支或双支血管病变中疗效甚微或无疗效,且10年时的总体绝对生存优势约为4%。[19]
择期经皮冠状动脉介入治疗用于稳定型冠心病 主要是缓解症状的手术。COURAGE(2007)研究发现,与最佳药物治疗相比,它并未能降低死亡率或心肌梗死发生率。63] ORBITA 研究采用假手术对照设计,发现其症状改善效果远小于预期。64] 缺血 —规模最大且最具有决定性的试验——将中度或重度缺血患者随机分组,并发现五年主要结局估计值为 16.4% 与 18.2% 对于侵入性与保守性策略,差异为 −1.8 个百分点(95% 置信区间 −4.7 至 1.0), ,全因死亡风险比 1.05 (0.83–1.32) [49] ISCHEMIA-EXTEND, ,在中位 5.7 年的随访中,显示全因死亡率没有差异,其中心血管死亡率有小幅下降,但被非心血管死亡率的增加所抵消。65]
在所有 IMPACT 模型中,慢性心肌梗死和心肌梗死后队列中的 CABG 约占 3–5% 占冠心病总死亡率下降的比例,而针对稳定型疾病的选择性 PCI 的贡献大约为 1–2%.
这解释了一个原本令人费解的发现:尽管手术量巨大增长,, 针对慢性心绞痛的血运重建治疗,仅占1980年至2000年美国冠心病死亡率下降幅度的约5% 在 IMPACT 模型中。手术量的大幅增长主要发生在尚未确立人群生存获益的医疗场所中。.
表 6 — 预防与救援
| 干预 | 预防首次心肌梗死? | 预防复发性心肌梗死? | 降低心肌梗死期间/之后的死亡率? | 主要历史角色 |
| 控烟与戒烟 | 是 | 是 | 间接地 | 人口预防 |
| 通过食品供应和饮食降低人群的低密度脂蛋白(LDL)/载脂蛋白B(ApoB)水平 | 是 | 是 | 间接地 | 人口预防 |
| 减盐 / 替代盐 | 是 (通过BP) | 是 | 间接地 | 人口预防 |
| 他汀类药物与强化低密度脂蛋白降胆固醇治疗 | 是 在适当的一级预防中 | 强烈赞同 | 是,通过减少事件 | 预防医学/慢性病医学 |
| 抗高血压治疗 | 是 | 是 | 是的,通过减少血管事件 | 预防医学/慢性病医学 |
| GLP-1 受体激动剂 | 降低特定高风险肥胖/2型糖尿病人群的主要心血管不良事件(MACE)发生率 | 是 | 间接地 | 预防/心脏代谢 |
| 阿司匹林 | 受出血限制;并非普遍适用 | 是 | 是的,用于急性心肌梗死 | 二级预防加急性治疗 |
| 心脏康复与综合性二级预防 | 对正在发生的事件没有影响 | 是 | 改善后续预后 | 二级预防 |
| CCU与遥测 | 不 | 不直接 | 是 | 急性抢救 |
| 心肺复苏术、自动体外除颤器、除颤 | 不 | 不 | 是的,在可电击的心脏骤停中情况急剧恶化 | 紧急救援 |
| 急救医疗服务(EMS)、院前心电图、ST段抬高型心肌梗死(STEMI)网络 | 不 | 不直接 | 是的,通过减少治疗延迟 | 医疗系统 / 紧急救援 |
| 溶栓疗法 | 不 | 减少急性再梗死后果 | 是 | 再灌注抢救 |
| ST段抬高型心肌梗死急诊经皮冠状动脉介入治疗 | 不 | 减少再梗死率(对比溶栓) | 是 | 急性再灌注 |
| 稳定性冠心病择期经皮冠状动脉介入治疗 | 未展示出种群作用 | 不能替代密集的医疗预防措施 | 与优秀的药物治疗相比,没有明显的生存优势 | 症状缓解;精选解剖结构 |
| 冠状动脉旁路移植术 | 非全人群首发心肌梗死预防 | 改善特定高危解剖结构患者的预后 | 是,用于特定疾病;同时也用于缓解症状 | 慢性疾病血运重建术 |
| 肌钙蛋白与改进的诊断 | 无生物预防 | 启用靶向治疗 | 可能会间接改善护理 | 诊断;也 测量的变化 发病率与病死率 |
第七部分:反事实与挽救的生命
如果一个现代人口拥有落后的医疗护理——或者面临落后的风险因素,会怎么样?
这两个问题从未被随机化过,也无法精确回答。最接近且站得住脚的计算来自美国 IMPACT 模型,该模型独特地报告了绝对数字。接下来是 从该归因模型派生的算术反事实 — 将模型估计的避免或推迟的死亡人数加回到观察到的死亡人数中。这是一种说明性的重建,并非对如果取消干预会发生什么情况的验证性模拟。.
现代风险因素,1980年代的治疗方法。. 2000年模型年龄范围内观察到的冠心病死亡人数约为337,658人。剔除1980年以来治疗改进的估计收益,将会大约增加 159,330人死亡, ,产生约 496,988 — 关于 47% 高于观测值, ,同时保留经模型修正的风险因素改善效果。.
现代疗法,1980年代的风险因素。. 保留2000年的治疗水平,但逆转1980至2000年间模拟的风险因素改善情况,大约增加了 149,635人死亡, ,产生约 487,293 — 关于 44% 高于观测值.
有两个注意事项至关重要。首先,这些是 1980年代的关怀与1980年代的风险反事实,而不是20世纪50年代的反事实. 20世纪中叶的医疗缺乏冠心病监护病房、现代除颤系统、溶栓治疗、经皮冠状动脉介入治疗(PCI)、他汀类药物以及基本上所有的循证二级预防,因此真实的20世纪50年代反事实情况会糟糕得多——但没有任何经过验证的模型支持具体数字,向后外推将是凭空捏造。同样,恢复真实的20世纪50年代吸烟、胆固醇和血压分布,其产生的影响将大于仅仅逆转1980至2000年间变化的影响。.
其次,更有趣的是,, 这两个反事实几乎是对称的. 在1980年至2000年期间的美国,无论是剔除现代治疗带来的收益,还是剔除有利风险因素带来的收益,都会抹去相当大比例的进展。这种对称性为反对整个“医学与生活方式”的二元对立框架提供了有力的论据:两者都作出了相当巨大的贡献,而将这段历史呈现为 要么 医学 或 危险因素的改变具有误导性。它并不能证明任一途径单独作用会失效——每一条途径单独作用依然能带来显著的死亡率降幅。.
挽救了多少生命?
科学上站得住脚的术语是 避免或推迟的死亡人数, 因为没有任何模型能够确定在某一年避免了冠心病死亡的人究竟具体延长了多少年的寿命。.
三个美国反事实观点体现了其规模:
- 如果1980年各年龄段的冠心病死亡率持续到2000年的人口中,将会增加 当年冠心病死亡人数达 341,745 人. 其中,大约 159,330 归因于治疗和 149,635 to risk-factor change; the model explained about 90% of the observed difference.
- Had the 1963S. peak CHD mortality rate persisted, there would have been roughly 1.076 million CHD deaths in 1994 rather than about 482,000 — approximately 594,000 deaths avoided or postponed in that year alone.
- CDC’s historical analysis similarly estimated approximately 621,000 fewer CHD deaths in 1996 than if the 1963 peak rate had persisted.
The decline in cardiovascular mortality also contributed materially to gains in adult longevity: cardiovascular disease was the dominant cause of adult death, and its retreat is among the largest contributors to twentieth-century adult survival gains in high-income countries. This review does not estimate a global cumulative number of deaths prevented, nor a specific number of life-years gained, because it cites no dedicated demographic decomposition capable of supporting such a figure. The aggregate global “deaths prevented” figure is far softer, depends entirely on the counterfactual baseline chosen, and should not be quoted as a precise number without independent verification.
These figures must not simply be summed across years to produce a cumulative count of unique people saved. The same individual can have death postponed across many counterfactual years; the population’s age structure changes; competing non-coronary mortality changes; and the baseline rate is itself a counterfactual. A rigorous century-long cumulative “lives saved” total is therefore unspecified rather than falsely precise. What can be said is that single-year estimates against the 1963 peak-rate counterfactual are of the order of half a million to six hundred thousand deaths prevented or postponed in the mid-1990s — a scale of benefit with few parallels in the history of medicine. No verified continuous annual series exists across the following three decades, and none is asserted here.
第八部分:国际自然实验
Attribution models are inference. Natural experiments — where a population’s risk factors changed sharply and mortality followed — provide stronger triangulating evidence, although they remain non-randomized and potentially confounded by concurrent secular change.
芬兰和北卡累利阿
The Finnish experience is one of the most informative population-level natural experiments in the field, because the risk-factor changes were deliberately engineered, documented prospectively, and preceded the mortality change.
In the early 1970s, North Karelia recorded among the highest coronary mortality rates then documented anywhere, particularly among middle-aged working-age men in eastern Finland. A community-based program launched in 1972 — working through village organizations, schools, food producers, dairy cooperatives, and eventually national legislation — systematically reduced smoking, 饱和脂肪 intake, and blood pressure. Working-age male coronary mortality in eastern Finland fell from 643 to 118 per 100,000 between the early 1970s and 2012 (−82%), and female mortality from 114 to 17 (−84%).[66]
The within-community analyses estimated that observed reductions in the three classical risk factors predicted the great majority of the first-period decline in ischemic heart disease incidence in North Karelia — far more than in the reference area[35] — evidence about incidence, not merely mortality, and therefore evidence about prevention rather than rescue.[67] Even in the later decades of follow-up, the three classical risk factors continued to explain a substantial share of the ongoing decline. The national Finnish IMPACT analysis nevertheless assigned treatment a meaningful 23% share for 1982–1997[5], demonstrating once again that this is not an either/or.
冰岛
Iceland offers the cleanest quantitative demonstration that fewer events, not merely better survival, drove the mortality fall: coronary mortality fell 80% and MI incidence fell 66% between 1981 and 2006. The model attributed 73% of the mortality decline to risk-factor change and 25% to treatment, with cholesterol contributing 32%, smoking 22%, and systolic blood pressure 22%.[7] Within the treatment share: secondary prevention 8%, heart-failure treatment 6%, acute coronary syndrome treatment 5%, revascularization 3%, hypertension treatment 2%, and statins 0.5%.
瑞典
Coronary mortality fell approximately 53% in men and 52% in women from 1986–2002, with 55% attributed to risk-factor reduction and 36% to treatment.[6] The detailed follow-up analysis provides the field’s best worked example of separating diet from pharmacology within a single risk factor, and established that roughly three-quarters of the risk-factor-attributable benefit occurred in people 没有 diagnosed coronary disease.
英格兰和威尔士
The 1981–2000 decline was 62% in men and 45% in women aged 25–84, with treatment explaining 42% and risk-factor change 58%.[4] The distinguishing feature is that smoking reduction alone accounted for 48% of the modeled decline — a reminder that where a population’s dominant exposure is unusually severe, its reversal dominates everything else. Acute MI treatment contributed about 8%.
美国
The most complete accounting, and the one with absolute numbers, as described above: 44% risk factors, 47% treatment, ~9% unexplained, 341,745 deaths prevented or postponed in the year 2000 alone.
波兰:食品供应领域的一次偶然国家实验
Poland provides a particularly informative natural experiment bearing on the dietary hypothesis, because the change was economic rather than medical and was not primarily initiated as a cardiovascular health-service intervention. It was emphatically not a controlled test: the post-communist transition changed incomes, employment, healthcare, and much else simultaneously. After the 1991 economic transition, consumer subsidies on butter and lard were removed while trade liberalization made imported rapeseed and soybean oils cheap and available. Within roughly three years, animal fat consumption fell about 20%, vegetable oil consumption doubled, and fruit and vegetable intake rose.
Between 1991 and 2005, age-adjusted coronary mortality in Poland fell 54%, corresponding to approximately 26,200 deaths avoided in 2005. The Polish IMPACT model attributed roughly 54% of the decline to dietary fat substitution and increased physical activity, and 37% to medical therapy [33] Poland matters because the change in exposure was abrupt, externally imposed, not designed as a health-service intervention, and followed by a mortality change of the predicted direction and magnitude.
俄罗斯与后苏联时期的激增:逆向进行的实验
The dissolution of the Soviet Union produced the mirror image. Economic collapse, social disruption, hazardous binge consumption of high-proof spirits, and the breakdown of routine chronic disease care were followed by a very large increase in cardiovascular mortality during the 1990s in the Russian Federation, with reported increases of roughly 35–45%.[68] Comparable directional deterioration occurred in several neighboring post-Soviet states, though the precise magnitude there requires country-specific sources.
This provides especially compelling evidence that the century’s gains are not automatic, irreversible, or purely technological. A population with essentially unchanged medical knowledge lost decades of cardiovascular progress in under ten years because its social and behavioral conditions deteriorated. Any account that treats the coronary decline as a ratchet driven by accumulating medical capability cannot explain Russia.
荷兰
Coronary mortality fell 48% between 1997 and 2007 (269 to 141 per 100,000), with approximately 37% attributed to treatment and 36% to risk-factor change — notable for systolic blood pressure dominating the risk-factor share at about 30%. The model explained roughly 72% of the observed decline, leaving an unusually large residual.[34]
日本
Discussed above: rising incidence, sharply falling case fatality. Japan also illustrates the limits of extrapolating Western attribution percentages to populations with different baseline diets, lipid distributions, and stroke-versus-coronary disease balance.
全球分化
The high-income experience is not the world’s experience. While high-income countries recorded large declines in age-standardized cardiovascular mortality in recent decades, the picture elsewhere is heterogeneous by GBD region rather than a simple high-income/low-income binary. Many countries have seen rising absolute cardiovascular burden from population growth and aging while their age-standardized rates fell; in some regions age-standardized rates have also stagnated or risen, driven by urbanization, tobacco, the penetration of processed foods, and limited access to both prevention and acute care.[24] The global coronary epidemic is not uniformly ending; in much of the world it is still ascending in absolute terms.
表 7 — 心血管流行病学中的自然实验
| Region / context | Window | Structural driver | Mortality trend | Principal factors identified |
| North Karelia and Finland | 1972–2012 | Designed community intervention; dairy fat replaced with plant oils; salt reduction | >80% decline in working-age CHD mortality | Cholesterol reduction dominant; smoking cessation; BP control |
| Poland | 1991–2005 | Removal of animal-fat subsidies; imported vegetable oils | −54% | Saturated fat replaced by PUFA; increased physical activity |
| 冰岛 | 1981–2006 | Modernization, universal healthcare, tobacco and diet policy | −80%; incidence −66% | Cholesterol −32%, smoking −22%, SBP −22%; treatment 25% |
| Russian Federation | 1990–1998 | Socioeconomic collapse; disruption of chronic care | +35% to +45% increase | Hazardous 酒精 use; socioeconomic disruption; health-system deterioration |
| Japan (Miyagi) | 1979–2008 | Westernizing risk profile with rapidly modernizing acute care | Incidence +265%; in-hospital mortality −61% | Rescue improved while prevention deteriorated |
| Global regional divergence | 1990–2026 | Divergent risk transition and health-system capacity | Large age-standardized declines in high-income regions; heterogeneous elsewhere, with absolute burden rising in most regions | Prevention and guideline-directed therapy uptake versus urbanization, tobacco, processed foods; see GBD region-specific estimates[24] |
第九部分:停滞与被抛下的人
Three uncomfortable observations belong in any honest account.
Progress has slowed and, in places, reversed. The rate of decline in U.S. and U.K. coronary mortality attenuated markedly after roughly 2011. Adults under 55 — particularly women — show flattening or reversal. Wilmot and colleagues documented stagnation in young adults through 2011,[22] and a 2026 analysis of 945,977 first acute myocardial infarction hospitalizations in U.S. adults aged 18–54 found that adjusted in-hospital mortality after a first STEMI 玫瑰 by 1.2 percentage points in absolute terms between 2011 and 2022, while first-NSTEMI mortality was essentially unchanged.[59] Young women fared worse than young men (STEMI 3.1% vs 2.6%; NSTEMI 1.0% vs 0.8%), and non-traditional risk factors — low income, 肾病, non-tobacco drug use — were more strongly associated with death than traditional ones. Note that this measures case fatality among those hospitalized, not a population death rate. The causes of this worsening in-hospital STEMI mortality are not established; the study itself found non-traditional factors more strongly associated with death than traditional ones. At the population level, obesity and type 2 diabetes remain major counterweights to long-term coronary progress, and many major attribution models have flagged them as negative contributions since the 1990s — but they should not be assumed to explain the specific rise in young-adult in-hospital STEMI mortality.
Hypertension control has deteriorated in the United States. Using the traditional <140/90 mmHg threshold, control among U.S. adults with hypertension peaked around 2013–2014 at approximately 53.8% and fell to 43.7% by 2017–2018.[25] Under the stricter 2017 ACC/AHA definition (<130/80 mmHg), only 20.7% of U.S. adults with hypertension were controlled during August 2021–August 2023, with no significant change from 2017–March 2020.[69] The threshold and denominator must always be specified, because these figures are not interchangeable — a reversal of decades of improvement in one of the largest population-attributable cardiovascular risks globally.[24] This is substantially an implementation and health-system failure rather than a lack of effective therapy — and it is reversible, though socioeconomic, measurement, and biological factors also contribute.
The gains have not been shared equally. ARIC found incident MI declining at only 1.5% per year in Black men versus 3.4–4.3% in other groups over 1987–2008.[29] The Miyagi registry found in-hospital mortality of 12.2% in women versus 6.3% in men in 2008.[58] Socioeconomic and geographic gradients in coronary mortality persist and in several countries have widened, even as national averages improved. A national average that improves while a subgroup stagnates is a partial success being reported as a complete one.
Globally, GBD identifies high systolic blood pressure, dietary risk, high 低密度脂蛋白胆固醇, and air pollution among the largest contributors to cardiovascular burden, while high BMI and 高血糖 have worsened.[24] In much of the world, the coronary epidemic is not in retreat at all — it is in its ascending phase, in countries with far less capacity to deploy either prevention or rescue.
第 X 部分。接下来要做什么:做得比今天更好
The last hundred years were won with tobacco control, the food supply, blood pressure, cholesterol, and the emergency reperfusion of occluded arteries. Future progress cannot rely solely on repeating those strategies — though substantial gains remain available from implementing them better, particularly outside high-income countries.
One structural fact should govern planning. The marginal population gains available from further reducing already-low in-hospital STEMI mortality are likely smaller than those available from prevention. With in-hospital STEMI case fatality compressed to roughly 4–7%, even halving it again would move population coronary mortality only modestly. This does not mean acute care is finished: substantial opportunity remains in out-of-hospital cardiac arrest survival, cardiogenic shock, reperfusion delay, systems of care, and the disparities documented above — and the 2026 young-adult data show acute outcomes can deteriorate. But a larger share of future gains will probably need to come from preventing events rather than surviving them.
Seven directions have the strongest claim.
1. Treat cumulative lifetime exposure, not middle-aged thresholds
This is an important conceptual shift, and it requires no new drug. 孟德尔随机化 studies indicate that genetically mediated lifelong lower LDL confers a risk reduction several-fold greater per unit of LDL than the same reduction achieved for five years in a middle-aged trial population — the difference between roughly 22% per mmol/L over a trial[31] and a far larger effect over a lifetime.[32] Atherosclerotic risk depends strongly on cumulative atherogenic-particle exposure over time — along with blood pressure, smoking, glycemia, 炎症, and genetic factors — rather than on a cholesterol value measured on a given morning at age 55.
The practical implications are substantial: consider 载脂蛋白 B in addition to LDL-C — particularly where LDL-C and ApoB are discordant, or in metabolically high-risk patients — since ApoB counts 致动脉粥样硬化颗粒 directly;[32] initiate treatment earlier in people with clearly elevated lifetime exposure rather than relying solely on a ten-year risk threshold that is strongly age-dependent and can understate lifetime risk in younger patients; and use short-term risk scores alongside an assessment of cumulative lifetime exposure, rather than allowing the score alone to determine treatment.
2. Finally treat lipoprotein(a)
Roughly one in five people carries an elevated Lp(a) depending on the threshold used, it is almost entirely genetically determined, it is causally associated with atherosclerotic disease and 主动脉瓣狭窄, and neither statins nor ezetimibe lower it meaningfully. It is a major common causal risk factor for which outcome-proven targeted therapy remains unavailable, and it remains substantially undermeasured in routine practice — despite requiring, in most people, only a single lifetime test.
RNA-targeted therapeutics now lower it dramatically: 培拉卡生 (antisense) by roughly 80%, 奥帕西兰 and lepodisiran (siRNA) by approximately 90–94%, with oral small-molecule approaches such as muvalaplin in earlier development.[70,71,72,73,74] Phase 3 cardiovascular outcome trials are ongoing; as of August 2026, definitive cardiovascular outcome results have not been reported, and the field should not pre-commit to a result. One-time measurement in adulthood is already endorsed by major contemporary society and consensus statements;[75] the outcome trials are needed principally to establish whether targeted treatment improves outcomes. Positive results would strongly reinforce systematic one-time measurement and could make Lp(a) lowering a major addition to preventive cardiology.
3. Extend the lipid-lowering toolkit and solve adherence
Inclisiran offers siRNA-based LDL lowering with twice-yearly maintenance dosing after initial and three-month doses, converting adherence from a daily behavioral problem into a scheduled clinical event; a direct cardiovascular outcome benefit has not yet been established, with ORION-4 ongoing. Bempedoic acid provides a non-statin option with demonstrated outcome benefit for the statin-intolerant.[76] Obicetrapib and other agents remain investigational, with cardiovascular outcome data still pending.
Fixed-dose combination therapy addresses the same problem from the other direction. 安全 (post-MI polypill) reduced the primary composite by 24%;[43] PolyIran reduced major cardiovascular events with HR 0.66 in a primary-prevention population;[77] TIPS-3 showed HR 0.69 for polypill plus aspirin.[78] The consistent finding is that adherence is one of the major limiting factors in secondary prevention — alongside 剩余风险, undertreatment, clinical inertia, and access.
4. Treat the cardiometabolic driver directly
Obesity and diabetes have been major counterweights to progress for thirty years, and until recently there was no pharmacotherapy producing 减肥 of this magnitude while also improving cardiometabolic risk and cardiovascular outcomes. SELECT changed that: in 17,604 patients with obesity and cardiovascular disease but without diabetes, 司美格鲁肽 reduced major adverse cardiovascular events from 8.0% to 6.5%, HR 0.80 (95% CI 0.72–0.90).[50] Cardiovascular death alone was not significantly reduced (2.5% vs 3.0%; HR 0.85, 95% CI 0.71–1.01), so the benefit is established for the composite rather than for cardiovascular mortality specifically. SGLT2 inhibitors reduce heart failure events and cardiovascular death in heart-failure and 慢性肾脏病 populations, including people without diabetes; they are not established as generic primary prevention in all non-diabetic adults. Dual and triple incretin agonists are in outcome trials.
If these agents can be deployed at population scale — which is at present a pricing, supply, and health-system question far more than a scientific one — they address the specific factor that has been subtracting from the ledger since 1990. That is one plausible route to helping restart the stalled decline.
5. Address residual inflammatory risk
坎托斯 provided randomized evidence supporting the inflammatory hypothesis: 卡纳单抗 reduced recurrent events by roughly 15% with no lipid change, though without an all-cause mortality benefit and without ever being approved for this indication.[79] Colchicine at 0.5 mg daily reduced the primary composite by about 23% in COLCOT (HR 0.77, 95% CI 0.61–0.96)[51] and about 31% in LoDoCo2 (HR 0.69)[52]. The subsequent CLEAR SYNERGY (OASIS-9) trial in 7,062 patients after acute MI was neutral (9.1% vs 9.3%; HR 0.99, 95% CI 0.85–1.16),[53] introducing genuine uncertainty about which patients benefit. 齐替韦单抗, targeting interleukin-6, is in outcome trials. Residual inflammatory risk is real; the optimal agent and the right patient are not yet settled.
6. Find the people at risk before the event
Coronary artery calcium scoring can refine risk classification when conventional ten-year estimates leave treatment decisions uncertain, and a score of zero is a powerful negative predictor.[80] 多基因风险评分 add independent information, particularly in the young, though their clinical utility across ancestries remains uneven.
More consequentially: 家族性高胆固醇血症 affects roughly one in 250 people, causes premature coronary death, is readily screenable with a lipid panel, is highly treatable, and remains largely undiagnosed.[81] Diagnosis requires clinical, family, and often genetic context plus exclusion of secondary causes, but screening itself is simple. Universal lipid screening in childhood with cascade screening of families is recommended by several professional societies, though guideline consensus and implementation both remain incomplete.
7. Population policy retains exceptionally large leverage
Population policies shift exposure across entire distributions rather than acting only on the motivated minority who attend clinics, and therefore carry unusually large potential leverage. The evidence base is not uniform across them: industrial trans-fat elimination, sodium reduction, and tobacco control have the strongest support for hard cardiovascular outcomes, whereas sugar taxation and some dietary reformulation policies currently rest on more indirect evidence.
这 SSaSS trial demonstrated this with randomized evidence: in 20,995 participants followed a mean 4.74 years, replacing salt with a 75% sodium chloride / 25% potassium chloride substitute reduced stroke (rate ratio 0.86, 95% CI 0.77–0.96, P=0.006), major cardiovascular events by 13%, and all-cause death by 12%.[82] In this high-risk rural population, a low-cost dietary substitution produced clinically important outcome benefits; generalizability to lower-risk settings is less certain.
最重要的是:弥合执行差距
One of the largest potentially available gains today is not a new molecule. It is the distance between what the evidence supports and what patients actually receive. Fewer than half of American adults with hypertension are controlled to conventional targets.[25] European registry surveillance of coronary patients has repeatedly documented large shortfalls in risk-factor control and low uptake of cardiac rehabilitation after an acute event.[83] Many high-risk patients leave hospital after an infarction without guideline-recommended intensive lipid lowering; Lp(a) remains undermeasured in routine practice; and familial 高胆固醇血症 commonly goes undiagnosed for decades.[81]
The awareness–treatment–control cascade for hypertension and lipids leaks at every stage, and many of these gaps are amenable to established policy and delivery interventions. Closing those gaps with drugs that came off 专利 years ago would plausibly yield a very large mortality benefit. No model is cited here comparing that benefit against the expected yield of the next decade of pharmaceutical innovation, and the comparison should be read as an unquantified judgment rather than an estimate.
表 8 — 后续议程
| Lever | 机制 | Current evidence status | Plausible scale of benefit |
| Lifetime ApoB/LDL exposure reduction, earlier initiation | Reduces cumulative atherogenic particle-years | 孟德尔 随机化 plus trial extrapolation; no long-horizon RCT | Potentially very large; hardest to prove |
| Lp(a) lowering | Targets a major common causal lipid risk not addressed by conventional LDL-lowering therapy | Potent lowering proven; phase 3 outcome trials ongoing, definitive results not reported as of August 2026 | Large if positive; unknown until then |
| GLP-1 and incretin therapies | Addresses the obesity/diabetes counterweight | 一级 (SELECT); more trials reading out | Large; constrained by cost and access |
| Polypill and adherence engineering | Converts proven efficacy into realized benefit | 一级 (SECURE, PolyIran, TIPS-3) | Moderate–large, especially in secondary prevention |
| Anti-inflammatory therapy | Addresses residual inflammatory risk | 一级 but heterogeneous; patient selection unresolved | 适度 |
| Salt substitution and sodium policy | Population-wide BP reduction | 一级 (SSaSS) | Large at population scale, very low cost |
| Tobacco endgame policy | Reduces residual smoking burden | Strong policy evidence | Moderate in high-income, very large globally |
| CAC, polygenic scores, FH cascade screening | Finds high-risk individuals before events | Good evidence; poor implementation | Moderate; concentrated in the young |
| Closing the control cascade | Delivers existing therapy to existing patients | Strong; implementation is a major limiting factor | Potentially very large near-term gain |
证据等级与证据分类账
Tier 1 — randomized trials and meta-analyses establish that lowering LDL, lowering blood pressure, giving aspirin and reperfusion in acute MI, and providing primary PCI promptly rather than fibrinolysis in appropriate STEMI patients, causally reduce events or death. They do 不 tell us how much of a country’s forty-year mortality decline came from each intervention, because that additionally requires population uptake data.
Tier 2 — cohorts and natural experiments (Framingham, North Karelia) reveal long-term changes in incidence, risk factors, and survival, and strengthen causal interpretation of population prevention.
Tier 3 — surveillance (CDC/NCHS, ARIC, MONICA, national registries) provides the strongest evidence that population event and mortality rates actually changed.
Tier 4 — IMPACT attribution models, which incorporate externally estimated causal effect sizes rather than independently identifying causal effects, are the only practical way to partition an observed national decline among dozens of treatments and risk factors simultaneously. Their percentages are model-dependent and must never be presented as though they came from randomized experiments.
Tier 5 — historical inference is unavoidable for the early CCU era and for 1925–1950, when modern event definitions and surveillance did not exist.
证据台账
| 学习 | Main quantitative finding used here | Access status | Tier | Identifier |
| Ford et al., 新英格兰医学杂志 2007 | U.S. 1980–2000: 47% treatment, 44% risk factors; 341,745 fewer deaths | Full text reviewed | 4 | DOI 10.1056/NEJMsa053935; PMID 17554120 |
| Unal et al., 循环 2004 | England/Wales: 42% treatment, 58% risk factors; smoking 48% | Abstract reviewed | 4 | PMID 14993137 |
| Laatikainen et al., 美国流行病学杂志 2005 | Finland: treatment 23%, risk factors 53–72% | Abstract reviewed | 4 | DOI 10.1093/aje/kwi274; PMID 16150890 |
| Björck et al., 欧洲心脏病学杂志 2009 | Sweden: 36% treatment, 55% risk factors | Abstract reviewed | 4 | DOI 10.1093/eurheartj/ehn554; PMID 19141562[6] |
| Björck et al., PLoS One 2015 | Swedish diet/statin/BP partition; double-counting method | Full text reviewed | 4 | DOI 10.1371/journal.pone.0124769; PMID 25942424[10] |
| Aspelund et al., PLoS One 2010 | Iceland: mortality −80%, incidence −66%; risk factors 73%, treatment 25%, statins 0.5% | Full text openly available | 4 | DOI 10.1371/journal.pone.0013957; PMID 21103050[7] |
| Tunstall-Pedoe et al., 柳叶刀 1999 | MONICA: ~two-thirds event rates, ~one-third case fatality | Abstract/reference record reviewed | 3 | DOI 10.1016/S0140-6736(99)04021-0; PMID 10334252 |
| Parikh et al., 循环 2009 | Framingham: ECG-MI incidence −50%; adjusted case fatality −60% | Full PMC text reviewed | 2 | DOI 10.1161/CIRCULATIONAHA.108.825364; PMID 19237656[28] |
| Rosamond et al., 循环 2012 | ARIC incidence and 28-day case-fatality declines; Black men 1.5%/yr | Open full text | 3 | DOI 10.1161/CIRCULATIONAHA.111.047480; PMID 22420957[29] |
| King et al., 美国心脏协会杂志 2025 | U.S. 1970–2022: IHD −81%, AMI mortality −89% | Full/open article record reviewed | 3 | DOI 10.1161/JAHA.124.038644; PMID 40557798[2] |
| BPLTTC, 柳叶刀 2021 | ~10% MACE reduction per 5 mmHg SBP; 344,716 participants | Detailed record; free PMCID | 1 | DOI 10.1016/S0140-6736(21)00590-0; PMID 33933205[37] |
| CTT 合作, 柳叶刀 2012 | MVE RR 0.79 per 1 mmol/L LDL reduction | Abstract/full-text metadata reviewed | 1 | DOI 10.1016/S0140-6736(12)60367-5; PMID 22607822[38] |
| ISIS-2, 柳叶刀 1988 | Aspirin and streptokinase acute-MI mortality effects | Abstract/results reviewed | 1 | PMID 2899772 |
| Fibrinolytic Therapy Trialists, 柳叶刀 1994 | ~30 fewer deaths/1,000 treated within 6 h | Abstract reviewed | 1 | PMID 7905143 |
| Keeley et al., 柳叶刀 2003 | Primary PCI vs thrombolysis: death 7% vs 9% | Complete abstract reviewed | 1 | DOI 10.1016/S0140-6736(03)12113-7; PMID 12517460[21] |
| PAD Trial, 新英格兰医学杂志 2004 | CPR+AED roughly doubled survivor count vs CPR-only | Publisher abstract/methods reviewed | 1 | DOI 10.1056/NEJMoa040566 |
| Maron et al. (ISCHEMIA), 新英格兰医学杂志 2020 | No death/ischemic-event advantage from routine invasive strategy | Full text reviewed | 1 | DOI 10.1056/NEJMoa1915922; PMID 32227755[49] |
| Yusuf et al., 柳叶刀 1994 | CABG survival benefit in left main and three-vessel disease | Abstract reviewed | 1 | CABG Trialists Collaboration |
| Cannon et al. (IMPROVE-IT), 新英格兰医学杂志 2015 | Ezetimibe + statin 32.7% vs 34.7% at 7 years | Complete abstract reviewed | 1 | DOI 10.1056/NEJMoa1410489; PMID 26039521[39] |
| Sabatine et al. (FOURIER), 新英格兰医学杂志 2017 | Evolocumab HR 0.85 primary endpoint | Complete abstract reviewed | 1 | PMID 28304224 |
| Schwartz et al. (ODYSSEY OUTCOMES), 新英格兰医学杂志 2018 | Alirocumab HR 0.85 MACE after ACS | Complete abstract reviewed | 1 | DOI 10.1056/NEJMoa1801174; PMID 30403574 |
| Lincoff et al. (SELECT), 新英格兰医学杂志 2023 | Semaglutide MACE 6.5% vs 8.0%, HR 0.80 | Complete abstract reviewed | 1 | DOI 10.1056/NEJMoa2307563[50] |
| Neal et al. (SSaSS), 新英格兰医学杂志 2021 | Salt substitute: stroke RR 0.86; all-cause death −12% | Complete abstract reviewed | 1 | DOI 10.1056/NEJMoa2105675[82] |
| Castellano et al. (SECURE), 新英格兰医学杂志 2022 | Polypill post-MI: composite HR 0.76; CV death HR 0.67 | Complete abstract reviewed | 1 | DOI 10.1056/NEJMoa2208275[43] |
| Takii et al. (MIYAGI-AMI), Circ J 2010 | Incidence 7.4→27.0/100k; hospital death 20.0→7.8% | Complete abstract reviewed | 3 | DOI 10.1253/circj.CJ-09-0619; PMID 19942783[58] |
| Antithrombotic Trialists’ Collaboration, 柳叶刀 2009[42] | Aspirin: secondary 19% event reduction; primary 12%, offset by bleeding | Abstract reviewed | 1 | ATT Collaboration |
| Bandosz et al., 英国医学杂志 2012 | [33] Poland 1991–2005: −54%; 54% risk factors, 37% treatment | Abstract reviewed | 4 | 英国医学杂志 2012;344:d8136 |
| Worcester Heart Attack Study | Hospital survival after initial AMI 81% (1975) → 91% (2005); age-adjusted in-hospital case fatality 22.2% (1975) → 15.1% (1984) | Abstract level | 3 | Floyd et al.[55]; Goldberg et al.[56] |
| Leon et al., 柳叶刀 1997 and GBD | Post-Soviet CVD mortality surge of ~35–45% in the 1990s | Secondary/abstract level | 3 | PMID 9269215 |
| GBD 2023 CVD Collaborators, JACC 2025 | 19.2 million CVD deaths in 2023; risk-factor burden | Publisher record reviewed | 3 | DOI 10.1016/j.jacc.2025.08.015[24] |
使用了摘要级证据的结构化摘要
England and Wales IMPACT — Unal, Critchley & Capewell. The IMPACT mortality model was applied to national treatment uptake, clinical effectiveness data, and population risk-factor trends from 1981–2000. CHD mortality declined 62% in men and 45% in women aged 25–84, corresponding to 68,230 fewer deaths in 2000. Treatment was assigned 42% and population risk-factor reduction 58%; smoking alone contributed 48%, with blood pressure and cholesterol about 9.5% each, and obesity, diabetes, and inactivity offsetting some gains. Abstract-level evidence; no numerical detail beyond the reported abstract was inferred.
Finland IMPACT — Laatikainen et al. Finnish national death, hospital, and social-insurance records were combined with random-sample risk-factor surveys and IMPACT treatment-effect estimates for 1982–1997. CHD mortality declined 63%. Treatment explained approximately 23%; risk-factor changes approximately 53–72%. Abstract-level evidence.
MONICA — Tunstall-Pedoe et al. The project standardized coronary-event ascertainment across 37 populations and assessed how changes in event rates and survival related to falling CHD mortality over approximately a decade. The central result, as summarized in the subsequent peer-reviewed literature, is that roughly two-thirds of the mortality decline arose through reduced coronary-event rates and one-third through improved case fatality, with substantial population and sex heterogeneity. Bibliographic/abstract record plus later peer-reviewed summary; no unsupported subgroup extraction was made.
MIYAGI-AMI Registry. Among 22,551 acute MI patients registered from 1979–2008, age-adjusted incidence increased from 7.4 to 27.0 per 100,000 while age-adjusted hospital mortality declined from 20.0% to 7.8%; ambulance use and primary PCI increased over the period. The abstract also reports 2008 mortality of 12.2% in women versus 6.3% in men. Complete abstract reviewed.
证据空白与残留不确定性
No valid single decomposition exists for the entire period 1925–2026. IMPACT analyses typically compare two years 15–25 years apart and are concentrated in high-income countries after 1980. Extrapolating their percentages backward through the pre-CCU era, or forward into the PCSK9 and high-sensitivity troponin era, is unjustified.
Diagnostic drift is a first-order problem, not a footnote. A modern high-sensitivity troponin assay detects infarctions that would have gone entirely unrecognized decades ago, simultaneously inflating apparent incidence and deflating apparent case fatality. Framingham demonstrated the effect directly. Biomarker-adjusted or ECG-standardized surveillance therefore deserves substantially greater weight than unadjusted hospital discharge coding.
The boundaries between categories are causally porous. A statin lowers a population cholesterol measurement; antihypertensive prescribing lowers population mean blood pressure; physician counseling changes smoking; EMS enables earlier aspirin and PCI; troponin changes both diagnosis and treatment eligibility. Good IMPACT implementations adjust known overlaps, but residual double-counting remains possible.
The “unexplained” residual is not the health-system contribution. Better ambulance networks, catheterization laboratory availability, nursing, time-to-treatment, prevention clinics, and diagnostic recognition are partly embedded in observed treatment uptake and case-fatality change. The honest statement for that category is “not separately quantifiable from the current attribution literature.”
Averages conceal disparities. Slower decline in Black men; higher case fatality in women; persistent and in places widening socioeconomic and geographic gradients.
Sex-specific evidence is weaker than it should be. Women were under-represented in the foundational trials of the 1980s and 1990s; the proportional benefits of lipid and blood-pressure lowering appear consistent by sex, but data on presentation, diagnosis, and acute management in women remain less complete, and the outcome gap has not closed.
The epidemic is not over. Rising obesity and diabetes repeatedly subtract from the benefits of reduced smoking, cholesterol, and blood pressure in many major attribution models. Globally, cardiovascular disease is still ascending in much of the world.
Figures deliberately removed or constrained in this version. An unverifiable pooled cross-cohort attribution estimate has been deleted rather than retained with a caveat. The global cumulative “deaths prevented” figure is stated non-numerically. The claim of rising heart-attack mortality in adults under 55 has been replaced with the specific 2026 in-hospital STEMI finding.[59] Two quantities remain flagged: the population mean risk-factor shifts in Table 3 are order-of-magnitude summaries across differing populations and periods rather than values from a single sourced series, and the era bands in Table 5 are a schematic synthesis rather than a single dataset.
Key quantities that remain genuinely unknown: the effect size of very early, lifelong lipid lowering; whether Lp(a) lowering translates into event reduction; which patients benefit from anti-inflammatory therapy; and whether incretin therapies can be deployed at sufficient scale to substantially reduce the cardiometabolic counterweight.
主要结论的置信度等级
High confidence. Coronary and acute-MI mortality have fallen extraordinarily — roughly 80–90% from late-twentieth-century U.S. reference levels — and 两者都 lower event incidence and lower case fatality contributed.
High confidence. Lowering LDL/ApoB, lowering blood pressure, stopping smoking, antiplatelet therapy in appropriate acute and secondary settings, and timely reperfusion causally reduce coronary events and/or death.
Moderate confidence. In the high-income populations best studied during the main 1970s–2000s decline, roughly one-half to two-thirds of the coronary mortality improvement arose from population risk-factor change and roughly one-quarter to two-fifths from treatment, with substantial country-specific departures.
Moderate confidence. Acute treatment itself typically explains only ~5–10% of the total historical CHD mortality decline in attribution models, even though acute care is responsible for a far larger share of improved survival among patients who actually have an infarction.
Moderate–high confidence. The direction of the international evidence is stable across the country-specific IMPACT analyses: risk factors somewhat ahead of treatment, with both large. No verified pooled point estimate is relied upon here.
Moderate–high confidence. Natural experiments in both directions — North Karelia and Poland downward, post-Soviet Russia upward — support a causal rather than merely associational reading of the population risk-factor contribution.
Moderate–high confidence. Progress has stalled since approximately 2011 in the U.S. and U.K., with stagnation in younger adults and recent evidence of worsening in-hospital mortality after first STEMI among adults aged 18–54,[59] and deteriorating hypertension control is a plausible contributor.
Low confidence. Any precise 1925–2026 partition into risk factors versus treatment; any exact cumulative century-long or global “lives saved” figure; any specific mortality estimate for a hypothetical modern population treated with literal 1950s medicine.
中心合成
- How much has CHD mortality declined? U.S. age-adjusted ischemic heart disease mortality fell 81% between 1970 and 2022, and AMI-coded mortality 89%; age-adjusted CHD mortality fell roughly 1980年至2000年间的50% alone. Comparable declines of 47–84% are documented across high-income countries. Globally, age-standardized IHD mortality fell approximately 32% between 1990 and 2021 while absolute deaths rose.
- How much has MI incidence declined? Substantially, but with no valid universal figure and with major measurement caveats. Framingham ECG-defined first MI fell ~50% (1960–1999); Icelandic incidence fell 66% (1981–2006); ARIC found ~3–4% annual declines in most groups (1987–2008). Japan is the counterexample where incidence rose. Falling incidence was nonetheless the larger contributor during the classic MONICA era, averaging roughly two-thirds of the mortality decline.
- How much has MI case fatality declined? Dramatically. Pre-CCU hospital mortality of roughly 30% compares with contemporary in-hospital figures of ~3–7%. Framingham found age- and sex-adjusted case fatality at 30 days, one year, and five years each about 60% 下部 across 1960–1999.
- Of the fall in CHD mortality, what fraction is explained by each source? 大约 45–70% population risk-factor improvement; approximately 15–40% preventive and chronic medical treatment; approximately 5–10% (up to ~12%) direct acute and emergency cardiac care; and a few percent to ~10% unexplained residual, which should not be interpreted as the health-system contribution. For the United States 1980–2000 specifically: 44% / 37% / 10% / 9%.
- Within risk-factor improvement, what were the contributions? Population total cholesterol approximately 10–45% (U.S. 24%) — historical models measured serum total cholesterol rather than ApoB; smoking approximately 9–48% (U.S. 12%, England/Wales 48%); blood pressure approximately 6–22% (U.S. 20%); physical activity and diet approximately 5–10% where separately modeled and not double-counted against cholesterol and blood pressure. Obesity and diabetes contributed negatively, offsetting the equivalent of roughly 8% 和 10% of the U.S. decline respectively.
- The five advances that have probably prevented or postponed the most coronary (CHD) deaths. Note that the underlying attribution literature concerns coronary mortality specifically, not all cardiovascular mortality. This is inference from repeated attribution studies rather than a measured league table, and the ranking is order-of-magnitude rather than precise.
| 排名 | Advance | 基础 | 信心 |
| 1 | Reduced serum cholesterol exposure — food supply and diet first, lipid-lowering pharmacotherapy later | 24% of the U.S. decline, 32% Iceland, ~30% Ireland, dominant in Sweden; randomized LDL lowering causally reduces major vascular events ~20% per mmol/L | 高 |
| 2 | Smoking reduction and tobacco control | 12% (U.S.) to 48% (England/Wales); acts directly on first-event incidence | 高 |
| 3 | 降血压, from both population change and medication | 6–22% across models; ~10% fewer major CV events per 5 mmHg in randomized evidence | 高 |
| 4 | Comprehensive secondary prevention — antiplatelet therapy, lipid lowering, BP treatment, ACE inhibition, rehabilitation | 8–11% of entire national mortality declines despite applying only to those with established disease | 中等至高 |
| 5 | The acute coronary rescue system — CCU and defibrillation, aspirin and reperfusion, EMS and primary PCI | Smaller effect on incidence, transformative effect on case fatality; ~5–10% of total mortality decline, but a major reason short-term MI survival improved dramatically | 中等至高 |
Ranks 1 and 2 could reasonably be reversed in a population such as England and Wales where smoking dominated. The acute rescue system would rank first if the outcome of interest were survival after a heart attack rather than population coronary mortality.
归根结底
People today are dramatically less likely to die of coronary heart disease than their grandparents for two fundamentally different reasons, and the failure to distinguish them is the source of nearly every misconception about this history.
First, they became less likely to have a heart attack at all. Smoking fell. Average blood pressure fell. Atherogenic cholesterol exposure fell. Food environments changed, tobacco policy changed, and, increasingly from the 1970s and 1990s, antihypertensive and lipid-lowering medicines pushed those biological risks lower still. In the international attribution literature, these changes generally explain more of the historical decline than acute cardiology does.
Second, when a heart attack does occur, medicine is vastly better at preventing it from being fatal. Coronary care units and defibrillation attacked malignant arrhythmia. Aspirin and antithrombotic therapy limited thrombosis. Thrombolysis and then primary PCI restored coronary flow. Emergency medical systems shortened delay. Secondary prevention lowered the probability of the next event.
The proposed summary — that the decline arose from fewer cardiovascular insults across the population, plus increasingly effective preventive medications, plus dramatic improvements in survival when heart attacks occurred — is therefore supported by the evidence, with three amendments:
- 是 not a timeless 50/50 law. The balance shifts by country and, decisively, by era. Risk-factor change probably accounted for a larger share before 1980, because most modern therapy did not yet exist — but coronary care units, hypertension treatment, and CABG were already contributing, and a precise partition for that period is unavailable.
- Acute rescue deserves both more and less credit than it usually receives — more, because it is a major reason heart attacks are now far more survivable; less, because it explains only around 5–10% of the population-level mortality decline.
- The story does not end in triumph, and it is not a ratchet. The decline has stalled, and in adults under 55 in-hospital mortality after a first STEMI rose between 2011 and 2022.[59] Post-Soviet Russia demonstrated that a population can lose decades of cardiovascular progress in under ten years without losing any medical knowledge at all. Progress is contingent on social and behavioral conditions, not guaranteed by accumulated technology.
The fairest quantitative summary is this:
During the best-studied decades of the coronary mortality decline, favorable population risk-factor changes commonly explain about 45–70% of the fall, while medical and surgical treatment explains about 25–45%. Within the treatment contribution, direct acute-MI rescue commonly represents only around 5–10% of the total population mortality decline; the remainder comes largely from chronic treatment, secondary prevention, and management of established cardiovascular disease. Approximately two-thirds of the decline in coronary mortality during the classic MONICA era reflected fewer coronary events, and about one-third better survival after them.
In other words: modern cardiology has prevented an enormous number of deaths, but the century’s cardiovascular achievement is broader than cardiology alone. Population prevention reduced how often the coronary catastrophe happened; modern medicine transformed what happened next.
And the corollary matters more than the history. A large share of the twentieth century’s gains came from reducing population exposure to smoking, elevated blood pressure, and atherogenic cholesterol — alongside the transformation of acute care. Future gains are likely to depend increasingly on treating cumulative lifetime exposure rather than middle-aged thresholds, on addressing 脂蛋白(a) and residual inflammatory risk, on countering the obesity and diabetes counterweight that has been eroding progress for thirty years — and, most of all, on the unglamorous work of actually delivering to patients the therapies that were proven to work decades ago.
参考文献
Numbered in order of first appearance in the text.
- Herrick JB. Clinical features of sudden obstruction of the coronary arteries. 1912;59:2015–2020.
- King SJ, Wangdak Yuthok TY, Bacong AM, Khandelwal A, Kazi DS, Mussolino ME, Wong SS, Martin SS, Lewis EF, Rodriguez F, Palaniappan LP. Heart disease mortality in the United States, 1970 to 2022. J Am Heart Assoc. 2025;14(13):e038644. DOI 10.1161/JAHA.124.038644. PMID 40557798. (Adults aged 25 and older; National Vital Statistics System/CDC WONDER.)
- Ford ES, Ajani UA, Croft JB, et al. Explaining the decrease in U.S. deaths from coronary disease, 1980–2000. N Engl J Med. 2007;356:2388–2398. DOI 10.1056/NEJMsa053935. PMID 17554120.
- Unal B, Critchley JA, Capewell S. Explaining the decline in coronary heart disease mortality in England and Wales between 1981 and 2000. 2004;109:1101–1107. PMID 14993137.
- Laatikainen T, Critchley J, Vartiainen E, Salomaa V, Ketonen M, Capewell S. Explaining the decline in coronary heart disease mortality in Finland between 1982 and 1997. Am J Epidemiol. 2005;162:764–773. DOI 10.1093/aje/kwi274. PMID 16150890.
- Björck L, Rosengren A, Bennett K, Lappas G, Capewell S. Modelling the decreasing coronary heart disease mortality in Sweden between 1986 and 2002. Eur Heart J. 2009;30:1046–1056. DOI 10.1093/eurheartj/ehn554. PMID 19141562.
- Aspelund T, Gudnason V, Magnusdottir BT, et al. Analysing the large decline in coronary heart disease mortality in the Icelandic population aged 25–74 between 1981 and 2006. PLoS One. 2010;5:e13957. DOI 10.1371/journal.pone.0013957. PMID 21103050.
- Bennett K, Kabir Z, Unal B, et al. Explaining the recent decrease in coronary heart disease mortality rates in Ireland, 1985–2000. J Epidemiol Community Health. 2006;60:322–327. PMID 16537349.
- Tunstall-Pedoe H, Kuulasmaa K, Mähönen M, Tolonen H, Ruokokoski E, Amouyel P. Contribution of trends in survival and coronary-event rates to changes in coronary heart disease mortality: 10-year results from 37 WHO MONICA Project populations. 1999;353:1547–1557. DOI 10.1016/S0140-6736(99)04021-0. PMID 10334252.
- Björck L, Capewell S, O’Flaherty M, et al. Decline in coronary mortality in Sweden between 1986 and 2002: comparing contributions from primary and secondary prevention. PLoS One. 2015;10:e0124769. DOI 10.1371/journal.pone.0124769. PMID 25942424.
- Dawber TR, Meadors GF, Moore FE. Epidemiological approaches to heart disease: the Framingham Study. Am J Public Health. 1951;41:279–281. Keys A. Seven Countries: A Multivariate Analysis of Death and Coronary Heart Disease. Cambridge, MA: Harvard University Press; 1980.
- Julian DG. The history of coronary care units. Br Heart J. 1987;57:497–502; and Kouwenhoven WB, Jude JR, Knickerbocker GG. Closed-chest cardiac massage. 1960;173:1064–1067.
- Hu JS. The impact of coronary care unit on mortality from acute myocardial infarction in Hong Kong. A prospective randomized controlled study. Chin Med J (Engl). 1990;103(2):101–106. PMID 2118025.
- Killip T, Kimball JT. Treatment of myocardial infarction in a coronary care unit: a two year experience with 250 patients. Am J Cardiol. 1967;20:457–464. Mather HG, Pearson NG, Read KL, et al. Acute myocardial infarction: home and hospital treatment. Br Med J. 1971;3:334–338. Hill JD, Hampton JR, Mitchell JR. A randomised trial of home-versus-hospital management for patients with suspected myocardial infarction. 1978;1:837–841.
- Veterans Administration Cooperative Study Group on Antihypertensive Agents. Effects of treatment on morbidity in hypertension. 1967;202:1028–1034; and 1970;213:1143–1152.
- Havlik RJ, Feinleib M, eds. Proceedings of the Conference on the Decline in Coronary Heart Disease Mortality. NIH Publication No. 79-1610. Bethesda, MD: National Heart, Lung, and Blood Institute; 1979.
- Gruppo Italiano per lo Studio della Streptochinasi nell’Infarto Miocardico (GISSI). Effectiveness of intravenous thrombolytic treatment in acute myocardial infarction. 1986;1:397–402.
- ISIS-2 (Second International Study of Infarct Survival) Collaborative Group. Randomised trial of intravenous streptokinase, oral aspirin, both, or neither among 17,187 cases of suspected acute myocardial infarction. 1988;2:349–360. PMID 2899772.
- Yusuf S, Zucker D, Peduzzi P, et al. Effect of coronary artery bypass graft surgery on survival: overview of 10-year results from randomised trials by the Coronary Artery Bypass Graft Surgery Trialists Collaboration. 1994;344:563–570.
- Scandinavian Simvastatin Survival Study Group. Randomised trial of cholesterol lowering in 4444 patients with coronary heart disease (4S). 1994;344:1383–1389.
- Keeley EC, Boura JA, Grines CL. Primary angioplasty versus intravenous thrombolytic therapy for acute myocardial infarction: a quantitative review of 23 randomised trials. 2003;361:13–20. DOI 10.1016/S0140-6736(03)12113-7. PMID 12517460.
- Wilmot KA, O’Flaherty M, Capewell S, Ford ES, Vaccarino V. Coronary heart disease mortality declines in the United States from 1979 through 2011: evidence for stagnation in young adults, especially women. 2015;132:997–1002. PMID 26302759.
- American Heart Association. Heart Disease and Stroke Statistics — 2025 Update: A Report from the American Heart Association. 2025.
- GBD 2023 Cardiovascular Diseases Collaborators. Global, regional, and national burden of cardiovascular diseases and risk factors, 1990–2023. J Am Coll Cardiol. DOI 10.1016/j.jacc.2025.08.015.
- Muntner P, Hardy ST, Fine LJ, et al. Trends in blood pressure control among US adults with hypertension, 1999–2000 to 2017–2018. 2020;324:1190–1200.
- National Center for Health Statistics / Centers for Disease Control and Prevention. Decline in deaths from heart disease and stroke — United States, 1900–1999. MMWR Morb Mortal Wkly Rep. 1999;48:649–656.
- Thygesen K, Alpert JS, Jaffe AS, et al. Fourth Universal Definition of Myocardial Infarction (2018). 2018;138:e618–e651.
- Parikh NI, Gona P, Larson MG, et al. Long-term trends in myocardial infarction incidence and case fatality in the National Heart, Lung, and Blood Institute’s Framingham Heart Study. 2009;119:1203–1210. DOI 10.1161/CIRCULATIONAHA.108.825364. PMID 19237656.
- Rosamond WD, Chambless LE, Heiss G, et al. Twenty-two-year trends in incidence of myocardial infarction, coronary heart disease mortality, and case fatality in four US communities, 1987–2008. 2012;125:1848–1857. DOI 10.1161/CIRCULATIONAHA.111.047480. PMID 22420957.
- Myerson M, Coady S, Taylor H, Rosamond WD, Goff DC. Declining severity of myocardial infarction from 1987 to 2002: the Atherosclerosis Risk in Communities (ARIC) study. 2009;119:503–514.
- Cholesterol Treatment Trialists’ (CTT) Collaboration. Efficacy and safety of more intensive lowering of LDL cholesterol: a meta-analysis of data from 170,000 participants in 26 randomised trials. 2010;376:1670–1681.
- Ference BA, Ginsberg HN, Graham I, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease: evidence from genetic, epidemiologic, and clinical studies. A consensus statement from the European Atherosclerosis Society Consensus Panel. Eur Heart J. 2017;38:2459–2472.
- Bandosz P, O’Flaherty M, Drygas W, et al. Decline in mortality from coronary heart disease in Poland after socioeconomic transformation: modelling study. 2012;344:d8136. PMID 22279114.
- Koopman C, Vaartjes I, van Dis I, et al. Explaining the decline in coronary heart disease mortality in the Netherlands between 1997 and 2007. PLoS One. 2016;11:e0166139.
- Salonen JT, Puska P, Kottke TE, Tuomilehto J, Nissinen A. Decline in mortality from coronary heart disease in Finland from 1969 to 1979. Int J Epidemiol. 1989;18:595–601. DOI 10.1093/ije/18.3.595.
- Restrepo BJ, Rieger M. Denmark’s policy on artificial trans fat and cardiovascular disease. Am J Prev Med. 2016;50:69–76.
- Blood Pressure Lowering Treatment Trialists’ Collaboration. Pharmacological blood pressure lowering for primary and secondary prevention of cardiovascular disease across different levels of blood pressure: an individual participant-level data meta-analysis. 2021;397:1625–1636. DOI 10.1016/S0140-6736(21)00590-0. PMID 33933205.
- Cholesterol Treatment Trialists’ (CTT) Collaborators. The effects of lowering LDL cholesterol with statin therapy in people at low risk of vascular disease: meta-analysis of individual data from 27 randomised trials. 2012;380:581–590. DOI 10.1016/S0140-6736(12)60367-5. PMID 22607822.
- Cannon CP, Blazing MA, Giugliano RP, et al. Ezetimibe added to statin therapy after acute coronary syndromes (IMPROVE-IT). N Engl J Med. 2015;372:2387–2397. DOI 10.1056/NEJMoa1410489. PMID 26039521.
- Sabatine MS, Giugliano RP, Keech AC, et al. Evolocumab and clinical outcomes in patients with cardiovascular disease (FOURIER). N Engl J Med. 2017;376:1713–1722. PMID 28304224.
- Schwartz GG, Steg PG, Szarek M, et al. Alirocumab and cardiovascular outcomes after acute coronary syndrome (ODYSSEY OUTCOMES). N Engl J Med. 2018;379:2097–2107. DOI 10.1056/NEJMoa1801174. PMID 30403574.
- Antithrombotic Trialists’ (ATT) Collaboration. Aspirin in the primary and secondary prevention of vascular disease: collaborative meta-analysis of individual participant data from randomised trials. 2009;373:1849–1860.
- Castellano JM, Pocock SJ, Bhatt DL, et al. Polypill strategy in secondary cardiovascular prevention (SECURE). N Engl J Med. 2022;387:967–977. DOI 10.1056/NEJMoa2208275.
- Freemantle N, Cleland J, Young P, Mason J, Harrison J. Beta blockade after myocardial infarction: systematic review and meta regression analysis. 1999;318:1730–1737.
- Pfeffer MA, Braunwald E, Moyé LA, et al. Effect of captopril on mortality and morbidity in patients with left ventricular dysfunction after myocardial infarction (SAVE). N Engl J Med. 1992;327:669–677.
- SOLVD Investigators. Effect of enalapril on survival in patients with reduced left ventricular ejection fractions and congestive heart failure. N Engl J Med. 1991;325:293–302.
- Fibrinolytic Therapy Trialists’ (FTT) Collaborative Group. Indications for fibrinolytic therapy in suspected acute myocardial infarction: collaborative overview of early mortality and major morbidity results from all randomised trials of more than 1000 patients. 1994;343:311–322. PMID 7905143.
- Hallstrom AP, Ornato JP, Weisfeldt M, et al. Public-access defibrillation and survival after out-of-hospital cardiac arrest (PAD Trial). N Engl J Med. 2004;351:637–646. DOI 10.1056/NEJMoa040566.
- Maron DJ, Hochman JS, Reynolds HR, et al. Initial invasive or conservative strategy for stable coronary disease (ISCHEMIA). N Engl J Med. 2020;382:1395–1407. DOI 10.1056/NEJMoa1915922. PMID 32227755.
- Lincoff AM, Brown-Frandsen K, Colhoun HM, et al. Semaglutide and cardiovascular outcomes in obesity without diabetes (SELECT). N Engl J Med. 2023;389:2221–2232. DOI 10.1056/NEJMoa2307563.
- Tardif JC, Kouz S, Waters DD, et al. Efficacy and safety of low-dose colchicine after myocardial infarction (COLCOT). N Engl J Med. 2019;381:2497–2505.
- Nidorf SM, Fiolet ATL, Mosterd A, et al. Colchicine in patients with chronic coronary disease (LoDoCo2). N Engl J Med. 2020;383:1838–1847.
- Jolly SS, d’Entremont MA, Lee SF, et al. Colchicine in acute myocardial infarction (CLEAR SYNERGY / OASIS-9). N Engl J Med. 2025;392:633–642. DOI 10.1056/NEJMoa2405922.
- Tunstall-Pedoe H, Vanuzzo D, Hobbs M, et al. Estimation of contribution of changes in coronary care to improving survival, event rates, and coronary heart disease mortality across the WHO MONICA Project populations. 2000;355:688–700. PMID 10703800.
- Floyd KC, Yarzebski J, Spencer FA, Lessard D, Dalen JE, Alpert JS, Gore JM, Goldberg RJ. A 30-year perspective (1975–2005) into the changing landscape of patients hospitalized with initial acute myocardial infarction: Worcester Heart Attack Study. Circ Cardiovasc Qual Outcomes. 2009;2:88–95. DOI 10.1161/CIRCOUTCOMES.108.811828. PMID 20031820.
- Goldberg RJ, Gore JM, Alpert JS, Dalen JE. Incidence and case fatality rates of acute myocardial infarction (1975–1984): the Worcester Heart Attack Study. Am Heart J. 1988;115:761–767.
- Hochman JS, Sleeper LA, Webb JG, et al. Early revascularization in acute myocardial infarction complicated by cardiogenic shock (SHOCK). N Engl J Med. 1999;341:625–634.
- Takii T, Yasuda S, Takahashi J, et al. Trends in acute myocardial infarction incidence and mortality over 30 years in Japan: report from the MIYAGI-AMI Registry Study. Circ J. 2010;74:93–100. DOI 10.1253/circj.CJ-09-0619. PMID 19942783.
- Satish M, Walters RW, Wenzl FA, Safford M, Kini V. Sex differences in outcomes of young adults hospitalized with first myocardial infarction from 2011 to 2022. J Am Heart Assoc. 2026;15(5):e046517. DOI 10.1161/JAHA.125.046517. PMID 41744115. (National Inpatient Sample; 945,977 weighted first-AMI hospitalizations, ages 18–54.)
- Kitamura A, Sato S, Kiyama M, et al. Trends in the incidence of coronary heart disease and stroke in Japan: the Akita–Osaka study. J Am Coll Cardiol. 2008;52:71–79.
- Velazquez EJ, Lee KL, Jones RH, et al. Coronary-artery bypass surgery in patients with ischemic cardiomyopathy (STICH Extension Study). N Engl J Med. 2016;374:1511–1520.
- Farkouh ME, Domanski M, Sleeper LA, et al. Strategies for multivessel revascularization in patients with diabetes (FREEDOM). N Engl J Med. 2012;367:2375–2384.
- Boden WE, O’Rourke RA, Teo KK, et al. Optimal medical therapy with or without PCI for stable coronary disease (COURAGE). N Engl J Med. 2007;356:1503–1516.
- Al-Lamee R, Thompson D, Dehbi HM, et al. Percutaneous coronary intervention in stable angina (ORBITA): a double-blind, randomised controlled trial. 2018;391:31–40.
- Hochman JS, Anthopolos R, Reynolds HR, et al. Survival after invasive or conservative management of stable coronary disease (ISCHEMIA-EXTEND). 2023;147:8–19.
- Vartiainen E. The North Karelia Project: cardiovascular disease prevention in Finland. Glob Cardiol Sci Pract. 2018;2018(2):13. Vartiainen E, Laatikainen T, Peltonen M, et al. Thirty-five-year trends in cardiovascular risk factors in Finland. Int J Epidemiol. 2010;39:504–518.
- Salonen JT, Puska P, Mustaniemi H. Changes in morbidity and mortality during a comprehensive community programme to control cardiovascular diseases during 1972–77 in North Karelia. Br Med J. 1979;2:1178–1183. DOI 10.1136/bmj.2.6199.1178.
- Leon DA, Chenet L, Shkolnikov VM, et al. Huge variation in Russian mortality rates 1984–94: artefact, alcohol, or what? 1997;350:383–388. PMID 9269215.
- Fryar CD, Kit B, Carroll MD, Afful J. Hypertension prevalence, awareness, treatment, and control among adults age 18 and older: United States, August 2021–August 2023. NCHS Data Brief511. Hyattsville, MD: National Center for Health Statistics; October 2024.
- Tsimikas S, Karwatowska-Prokopczuk E, Gouni-Berthold I, et al. Lipoprotein(a) reduction in persons with cardiovascular disease (pelacarsen, phase 2). N Engl J Med. 2020;382:244–255.
- O’Donoghue ML, Rosenson RS, Gencer B, et al. Small interfering RNA to reduce lipoprotein(a) in cardiovascular disease (OCEAN[a]-DOSE, olpasiran). N Engl J Med. 2022;387:1855–1864.
- Nissen SE, Linnebjerg H, Shen X, et al. Lepodisiran, an extended-duration short interfering RNA targeting lipoprotein(a). 2023;330:2075–2083.
- Nicholls SJ, Nissen SE, Fleming C, et al. Muvalaplin, an oral small molecule inhibitor of lipoprotein(a) formation. 2023;330:1042–1053.
- Phase 3 cardiovascular outcome trials of Lp(a)-lowering therapy — Lp(a)HORIZON (NCT04023552), OCEAN(a)-Outcomes (NCT05581303), and ACCLAIM-Lp(a) (NCT06292013) — were registered as ongoing without reported outcome results as of August 2026.
- Kronenberg F, Mora S, Stroes ESG, et al. Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: a European Atherosclerosis Society consensus statement. Eur Heart J. 2022;43(39):3925–3946.
- Nissen SE, Lincoff AM, Brennan D, et al. Bempedoic acid and cardiovascular outcomes in statin-intolerant patients (CLEAR Outcomes). N Engl J Med. 2023;388:1353–1364.
- Roshandel G, Khoshnia M, Poustchi H, et al. Effectiveness of polypill for primary prevention of cardiovascular diseases (PolyIran): a pragmatic cluster-randomised trial. 2019;394:672–683.
- Yusuf S, Joseph P, Dans A, et al. Polypill with or without aspirin in persons without cardiovascular disease (TIPS-3). N Engl J Med. 2021;384:216–228.
- Ridker PM, Everett BM, Thuren T, et al. Antiinflammatory therapy with canakinumab for atherosclerotic disease (CANTOS). N Engl J Med. 2017;377:1119–1131.
- Greenland P, Blaha MJ, Budoff MJ, Erbel R, Watson KE. Coronary calcium score and cardiovascular risk. J Am Coll Cardiol. 2018;72:434–447.
- Nordestgaard BG, Chapman MJ, Humphries SE, et al. Familial hypercholesterolaemia is underdiagnosed and undertreated in the general population: consensus statement of the European Atherosclerosis Society. Eur Heart J. 2013;34:3478–3490.
- Neal B, Wu Y, Feng X, et al. Effect of salt substitution on cardiovascular events and death (SSaSS). N Engl J Med. 2021;385:1067–1077. DOI 10.1056/NEJMoa2105675.
- Kotseva K, De Backer G, De Bacquer D, et al. Lifestyle and impact on cardiovascular risk factor control in coronary patients across 27 countries: results from the European Society of Cardiology ESC-EORP EUROASPIRE V registry. Eur J Prev Cardiol. 2019;26(8):824–835.

