
1. The Hypothesis and How This Review Tests It
The proposition under examination is that a nutritionally adequate, entirely whole-food पौधारोपण-आधारित आहार, very low in total fat (hereafter VLF-WFPB), offers cardiovascular protection beyond that of other high-quality dietary patterns, for prevention, for treatment of established disease, and for regression. Four separate questions are kept apart throughout: (Q1) Does VLF-WFPB improve outcomes compared with a typical Western diet? (Q2) Does it outperform other high-quality diets, such as DASH, Mediterranean, or Portfolio? (Q3) Are complete exclusion of animal foods, very low total fat, and minimal processing each independently necessary for any advantage? (Q4) Do such diets protect arteries through pathways beyond lowering ApoB-containing लाइपोप्रोटीन? Q4 is treated as the central question (Section 5), because a benefit that runs entirely through अपोबी could in principle be matched by any equally effective means of lowering ApoB.
The positive case rests on convergence. Randomized trials show that plant-based diets lower causal जोखिम कारक; intensive lifestyle trials that included very-low-fat शाकाहारी आहार showed functional and angiographic improvement; and populations with lifelong low animal-food intake had low कोलेस्ट्रॉल and low coronary mortality. Each line is weak alone. Together they make it more credible that sustained dietary lowering of ApoB-containing lipoproteins can slow coronary disease, which bears mainly on Q1. They cannot answer Q2 or Q3, because in every line the diet travels with other exposures—वजन घटाना, physical activity, co-interventions, drugs—that also change risk. Convergence is therefore used here to judge plausibility, not to enlarge sample sizes or to compute a probability of superiority. Unrelated populations are not pooled.
Narrative reviews by Wang and colleagues, Freeman and colleagues, and Kahleova and colleagues served as background and as routes to original studies; numerical claims are taken from the original reports, and repeated citation of the same cohort is not treated as independent corroboration [1–3].
1.1 Scope and methods
This is a targeted critical review, not a registered व्यवस्थित समीक्षा. Sources were identified through PubMed-indexed records, publisher pages, full-text articles where accessible, guideline repositories, and reference tracing, with a final update search on 12 September 2026. Numerical claims were checked against original reports where accessible; where only an abstract or an official summary could be obtained, that is stated at the relevant passage. No new मेटा-विश्लेषण or patient-level reanalysis was performed.
Interests deserve attention without being disqualifying. Several lifestyle programs were evaluated by the investigators who developed them; the direct vegan–Mediterranean comparison was conducted by an organization that advocates plant-based diets; and the major Mediterranean secondary-prevention trial was funded principally by olive-oil foundations. These are reasons to emphasize allocation, retention, prespecification, blinded outcomes, and independent replication, not reasons to reject results.
1.2 How to read the evidence: five tiers of data
Not all evidence answers the same question. This review sorts studies into five tiers according to how well each design can show cause and effect, not according to whether its results support the hypothesis. Lower tiers still count—evidence is evidence—but they answer different questions and carry different risks of misleading us (Figure 1).
Tier 1: randomized trials with clinical events. People are assigned to a diet by chance, and दिल के दौरे, स्ट्रोक्स, or deaths are counted. Chance assignment reduces भ्रम में डालने वाला in expectation, though not necessarily in any single trial, so a difference in events is the strongest available evidence that the diet caused it. Examples in this review are PREDIMED, कार्डियोप्रेव, और ल्योन डाइट हार्ट स्टडी.
Tier 2: randomized trials of intermediate outcomes. Assignment is still by chance, but the outcome is a measurement that predicts events: LDL-C, ApoB, रक्तचाप, coronary narrowing, तख्ती की मात्रा, or myocardial blood flow. These trials show that a diet changes the measurement; they do not by themselves show fewer events. Examples are the लाइफ़स्टाइल हार्ट ट्रायल, EVADE CAD, and the lipid meta-analyses.
Tier 3: संभावित समूह studies. Large groups of individuals report what they eat and are followed for years. These studies capture real disease in real people over decades, which trials rarely can, but they show association: people who choose a diet differ in many other ways, and statistical adjustment can only partly remove those differences (Section 9.1). Examples are Adventist Health Study-2, एपिक-ऑक्सफोर्ड, and the Danish nitrate cohort.
Tier 4: population comparisons, cross-sectional studies, and uncontrolled case series. Whole populations are compared (rural China, Okinawa, the त्सिमाने), people are measured once, or treated patients are followed without a comparison group (the Esselstyn cohorts). These data generate hypotheses and show what is achievable, but many explanations can fit the same pattern.
Tier 5: mechanistic studies in cells and animals. Experiments can isolate a single pathway under controlled conditions, which makes them the best way to test how something might work. Whether the same pathway matters in human arteries over decades has to be shown separately.
Design is a starting point, not a verdict: confidence also depends on risk of bias, precision, how directly the comparison addresses the question, and how outcomes were ascertained. Tiers also apply to outcomes rather than to whole studies, so a trial can sit in one tier for imaging and another for clinical events. The case for a whole-food plant-based diet is strongest where several tiers point the same way and weakest where it rests on one tier alone. Section headings throughout the review note the main tier of evidence discussed.

Figure 1. Five tiers of evidence used in this review, the question each tier can answer, and examples of studies in each tier. Higher tiers are better at showing cause and effect; lower tiers add breadth, duration, and biological explanation.
2. Defining the Diets and the Comparisons
The proposed diet. VLF-WFPB consists of vegetables, legumes, intact whole grains, fruit, and minimally processed starchy foods, with no animal foods and little or no added oil, operationally about 10–15% of energy from fat. The 2014 Esselstyn protocol also excluded avocado, nuts, excess salt, and sugary foods, later also caffeine and fructose, and advised a multivitamin, vitamin B12, and flaxseed meal [4]. The earlier 1985 Esselstyn cohort was not vegan: patients eliminated oil, fish, fowl, meat, and dairy products except skim milk and nonfat yogurt, targeted 10% of energy from fat, and received individualized cholesterol-lowering medication [5]. ऑर्निश लाइफस्टाइल हार्ट ट्रायल diet was a 10%-fat whole-foods vegetarian diet that permitted nonfat dairy and egg whites [6, 7]; achieved fat intake was 6.2% of energy at one year and 8.5% at five years [6].
Related but different diets. Higher-fat whole-food vegan diets include nuts, seeds, avocado, or जैतून का तेल; the low-oil phase of the 2024 Recipe for Heart Health trial still provided 32% of energy from fat [8], and the vegan arm of the EVADE CAD trial ended at about 30% [9]. Generic vegan diets exclude animal foods without constraining food processing or fat. Conventional low-fat diets are omnivorous; the low-fat arm of CORDIOPREV prescribed less than 30% fat with lean meat and low-fat dairy, and achieved 32.1% [10].
Comparators. The DASH combination diet emphasized fruits, vegetables, and low-fat dairy with reduced saturated and total fat [11]. भूमध्यसागरीय आहार tested in randomized trials were substantially higher in fat: the PREDIMED arms were supplemented with extra-virgin olive oil or nuts [12]; the CORDIOPREV Mediterranean arm prescribed at least 35% fat and achieved 40.5% [10]; and the Lyon intervention supplied an alpha-linolenic-acid-rich margarine in place of butter and cream, alongside advice to follow a Mediterranean-type pattern [13, 14]. पोर्टफोलियो डाइट adds nuts, plant प्रोटीन, viscous फ़ाइबर, and plant स्टेरॉल to a low-saturated-fat background [15]. Table 1 summarizes the patterns as they were actually tested.
Table 1. Dietary patterns as tested.
| पैटर्न | Defining features in the key trials | Fat, % of energy | What the label alone does not establish |
| VLF-WFPB | Legumes, intact grains, vegetables, fruit, starchy foods; no animal foods; little or no oil; Esselstyn 2014 also excluded nuts and avocado [4] | Target ~10–15%; Ornish (vegetarian, not vegan) achieved 6.2–8.5% [6] | Adequate B12, protein, essential fats, or sustained अनुपालन |
| Higher-unsaturated-fat whole-food vegan | Animal-free, with nuts, seeds, avocado, or olive oil | 32–48% [8]; ~30% in EVADE CAD [9] | Inferiority to an oil-free vegan pattern |
| डैश | Fruit, vegetables, low-fat dairy; reduced saturated and total fat; sodium reduction in DASH-Sodium [11, 16] | Reduced, not very low | That benefit depends on dairy; event reduction in a trial |
| मेडिटेरेनियन (भूमध्यसागरीय) | Vegetables, legumes, whole grains, nuts, extra-virgin olive oil, fish [10, 12] | 40.5% achieved in CORDIOPREV [10] | A fixed macronutrient ratio or unlimited energy |
| पोर्टफोलियो | Nuts, plant protein, viscous fiber, plant sterols added to a low-saturated-fat diet [15] | Varied across trials; includes nuts but not necessarily high in fat | Event reduction; core evidence is लिपिड कम करने वाला; tested patterns were not restricted to 10–15% fat |
| Conventional low-fat (omnivorous) | Lean meat, low-fat dairy, complex कार्बोहाइड्रेट [10] | <30% prescribed; 32.1% achieved [10] | Equivalence to VLF-WFPB |
3. Three Levers: Animal-Food Exclusion, Total Fat, and Food Processing (Tiers 2–3)
VLF-WFPB bundles three changes that can be separated: excluding animal foods, restricting total fat to about 10–15% of energy, and building the diet from whole or minimally processed foods. The Esselstyn and Ornish programs push fat restriction and whole-food eating to their extremes and remove all or nearly all animal foods (their early protocols permitted nonfat dairy, and Ornish’s also egg whites). That makes them the natural test bed for the whole package and, for the same reason, unable on their own to apportion credit among its parts (Figure 2). The label “plant-based” describes only the first lever, and the evidence shows it is not sufficient on its own.
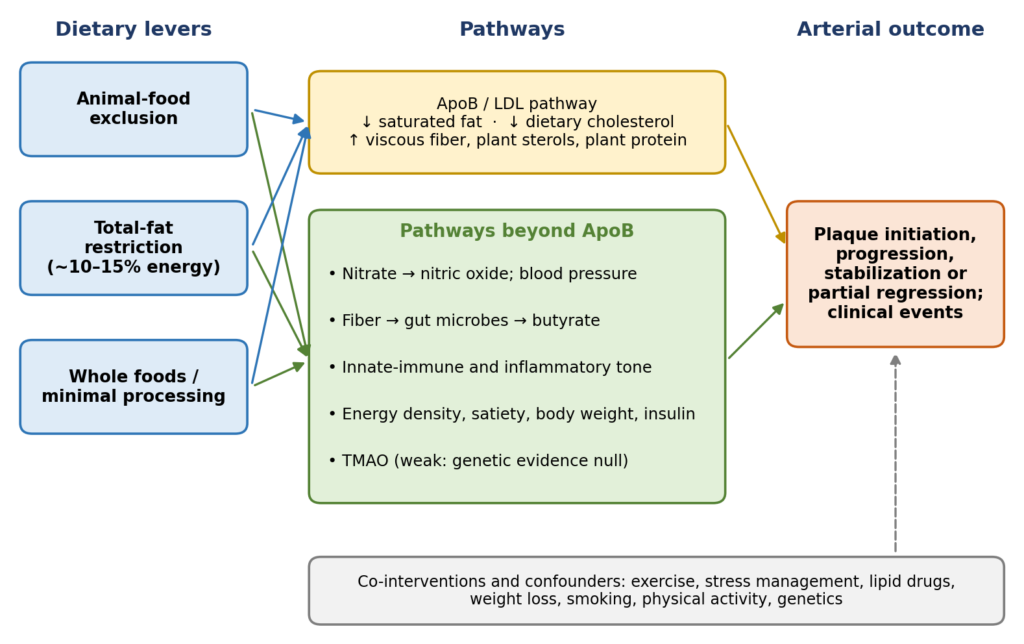
Figure 2. Three separable dietary levers and the pathways by which they could affect coronary धमनी काठिन्य. Most intervention programs change all three levers together and add co-interventions, so trials cannot attribute benefit to a single lever.
Diet quality within plant-based eating. In three US cohorts totalling about 209,000 health professionals with 8,631 incident coronary events, an overall plant-based diet index was only weakly associated with lower risk (Hazard ratio का हिंदी में अनुवाद है: **खतरा अनुपात** (या 'हेजर्ड रेशियो') for extreme deciles 0.92; 95% CI 0.83 to 1.01). A healthful index that rewarded whole grains, fruits, vegetables, nuts, legumes, oils, tea, and coffee was associated with 25% lower risk (0.75; 0.68 to 0.83), whereas an unhealthful index that rewarded refined grains, potatoes, sweetened beverages, juices, and sweets was associated with 32% higher risk (1.32; 1.20 to 1.46) [17]. दो बातें सामने आती हैं। पौधे-आधारित भोजन अपने आप में सुरक्षात्मक नहीं है; गुणवत्ता दिशा निर्धारित करती है। और स्वास्थ्यवर्धक सूचकांक ने नट्स और वनस्पति तेलों को फायदेमंद माना है, इसलिए यह प्रमाण विशेष रूप से बहुत कम वसा वाले पैटर्न के बजाय संपूर्ण-खाद्य (whole-food) पैटर्न का समर्थन करता है।
पादप खाद्य पदार्थों के भीतर प्रसंस्करण (Processing)। 1,26,842 में यूके बायोबैंक प्रतिभागियों पर औसतन 9 वर्षों तक नज़र रखी गई, पौधों से प्राप्त खाद्य पदार्थों जो अल्ट्रा-प्रोसेस्ड नहीं थे, उनसे मिलने वाली ऊर्जा में प्रत्येक 10-प्रतिशत-अंक की वृद्धि 7% कम से जुड़ी थी हृदय रोग जोखिम (खतरा अनुपात 0.93; 95% CI 0.91 से 0.95) और 13% कम हृदय संबंधी मृत्यु दर (0.87; 0.80 से 0.94)। पौधे से प्राप्त अति-प्रसंस्कृत खाद्य पदार्थ विपरीत संबंध दिखाया (बीमारी के लिए 1.05; 1.03 से 1.07 और मृत्यु दर के लिए 1.12; 1.05 से 1.20), और प्रसंस्करण को अनदेखा करते हुए कुल पादप-खाद्य सेवन ने कोई संबंध नहीं दिखाया [18].
प्रसंस्करण पर रैंडमाइज्ड (Randomized) प्रमाण। प्रसंस्करण के भी रैंडमाइज्ड प्रमाण हैं, हालांकि एथेरोस्क्लेरोसिस के बजाय ऊर्जा संतुलन के लिए। एक इनपेशेंट क्रॉसओवर परीक्षण में, 20 वजन-स्थिर वयस्कों को दो-दो सप्ताह के लिए अल्ट्रा-प्रोसेस्ड या अनप्रोसेस्ड आहार दिया गया, जिसमें भोजन को प्रस्तुत कैलोरी के लिए मिलान किया गया था, ऊर्जा घनत्व, मैक्रोन्यूट्रिएंट्स, चीनी, सोडियम और फाइबर। अल्ट्रा-प्रोसेस्ड आहार पर उन्होंने 508 ± 106 किलो कैलोरी/दिन अधिक खाया और 0.9 किलोग्राम वजन बढ़ाया; अनप्रोसेस्ड आहार पर उन्होंने 0.9 किलोग्राम वजन कम किया [19].
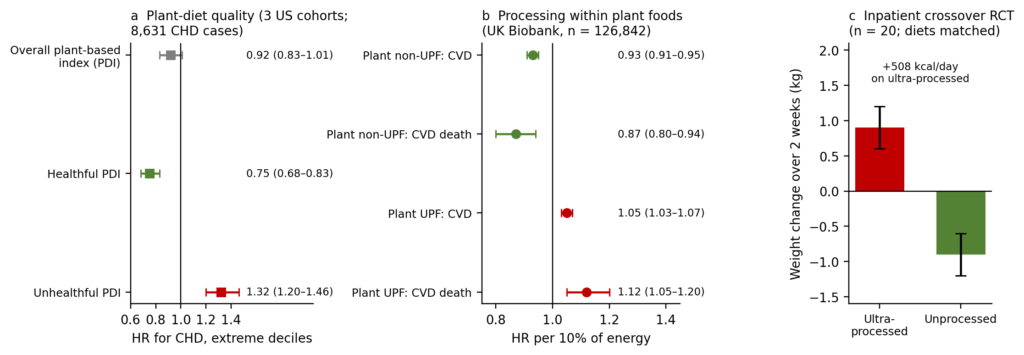
चित्र 3. आहार की गुणवत्ता और प्रसंस्करण। (a) पौधे-आधारित आहार सूचकांक और घटना कोरोनरी हृदय रोग, चरम डेसाइल। (b) प्रसंस्करण द्वारा पौधे-स्रोत वाले खाद्य पदार्थ, ऊर्जा के प्रति 10%, यूके बायोबैंक। (c) अल्ट्रा-प्रोसेस्ड बनाम अनप्रोसेस्ड आहार के इनपेशेंट क्रॉसओवर परीक्षण में वजन परिवर्तन (औसत ± SE)। पैनल अलग-अलग डिज़ाइन से आते हैं और परिमाण में तुलनीय नहीं हैं। स्रोत: सतिजा 2017; रौबर 2024; हॉल 2019।
यह क्या बदलता है। प्रसंस्करण पर प्रमाण दिशा में सुसंगत हैं: पौधों के खाद्य पदार्थों के संबंध प्रसंस्करण के साथ उलट जाते हैं, और एक रैंडमाइज्ड फीडिंग ट्रायल में अल्ट्रा-प्रोसेस्ड पैटर्न ने अनप्रोसेस्ड पैटर्न के सापेक्ष ऊर्जा सेवन और वजन में वृद्धि की, जिसमें पोषक तत्वों का मिलान डिजाइन की अनुमति के अनुसार किया गया था। ये निष्कर्ष भोजन की गुणवत्ता और प्रसंस्करण पर ध्यान देने का समर्थन करते हैं; वे पशु-खाद्य बहिष्कार के सापेक्ष प्रसंस्करण के महत्व को स्थापित नहीं करते हैं, एक तुलना जो किसी परीक्षण ने नहीं की है। यह एसेलस्टीन और ऑर्विश कार्यक्रमों को पुनर्गठित करता है। वे एक-दूसरे के साथ, और ग्रामीण चीन, ओकिनावा और सिमाने (अनुभाग 6-8) के साथ जो साझा करते हैं, वह शून्य पशु भोजन नहीं है, बल्कि लगभग पूरी तरह से संपूर्ण, न्यूनतम संसाधित खाद्य पदार्थों से बना आहार है। वह विशेषता, और क्या इसके लाभ केवल ApoB (अनुभाग 5) के माध्यम से चलते हैं, यह आगे के अध्ययन का मुख्य विषय है।
4. जैविक मामला: ApoB और लिपिड पाथवे (स्तर 1-2)
4.1 संगठनात्मक ढांचा: ApoB-युक्त कणों के प्रति संचयी जोखिम
एलडीएल और अन्य ApoB-युक्त लिपोप्रोटीन एथेरोस्क्लेरोटिक हृदय रोग का कारण बनते हैं, और अनुवांशिक, महामारी विज्ञान और परीक्षण साक्ष्य संकेत देते हैं कि जोखिम परिमाण और जोखिम की अवधि दोनों के साथ बढ़ता है [20]। कण धमनी में प्रवेश करते हैं इंटिमा उनकी सांद्रता के अनुपात में और संवेदनशील स्थानों में बने रहते हैं, इसलिए प्रासंगिक मात्रा है संचयी संपर्क न कि एक एकल माप। इस ढांचे का उपयोग यहां एक संगठनात्मक सिद्धांत के रूप में किया जाता है, न कि एक मान्य संख्यात्मक जोखिम समीकरण के रूप में।
आहार के लिए ढांचे के दो निहितार्थ हैं। पहला, शुरुआती वयस्कता से निरंतर मामूली कमी रोग स्थापित होने के बाद शुरू की गई समान कमी से अधिक मायने रख सकती है; धारा 6 से 8 में जनसंख्या साक्ष्य के पीछे यही तर्क है। दूसरा, स्थापित रोग में प्रासंगिक बेंचमार्क स्टैटिन-ट्रायल स्लोप है: लगभग पांच वर्षों में LDL-C में प्रति 1 mmol/L (38.7 mg/dL) की कमी पर प्रमुख संवहनी घटनाओं में लगभग 22% सापेक्ष कमी [21]। यदि वह स्लोप नीचे बताए गए 0.30 mmol/L के एकत्रित आहार संबंधी LDL-C अंतर पर लागू होता है, तो यह पांच वर्षों में लगभग 7% (1 − 0.78^0.30) की सापेक्ष कमी की भविष्यवाणी करेगा। वह आंकड़ा एक एक्स्ट्रापोलेशन (extrapolation) है, न कि मापा गया आहार प्रभाव: आहार परीक्षण हफ्तों से महीनों तक चलते हैं, पालन (adherence) कम हो जाता है, और आहार शरीर के वजन, रक्तचाप और अन्य कारकों को भी बदलता है जिन्हें स्टैटिन स्लोप कैप्चर नहीं करता है।
4.2 लिपिड और जोखिम कारकों पर रैंडमाइज्ड साक्ष्य
शाकाहारी या वीगन आहार की तुलना मिश्राहारी आहार से करने वाले रैंडमाइज्ड परीक्षणों के सबसे बड़े मेटा-विश्लेषण में 30 परीक्षण शामिल थे। पौधे-आधारित आहार ने कुल कोलेस्ट्रॉल को 0.34 mmol/L (95% CI 0.23 से 0.44; लगभग 13 mg/dL) और LDL-C को 0.30 mmol/L (95% CI 0.19 से 0.40; लगभग 11.6 mg/dL) कम किया। ApoB में 12.92 mg/dL (95% CI 3.20 से 22.63) की गिरावट आई, जो कि 14% की कमी है, लेकिन केवल छह परीक्षणों ने ApoB डेटा में योगदान दिया और विषमता (heterogeneity) काफी अधिक (I² = 71.7%) थी; ट्राइग्लिसराइड्स कुल मिलाकर अलग नहीं थे [22]। ApoB का आंकड़ा प्रकाशित संयुक्त अनुमान है; क्योंकि यह छह परीक्षणों पर आधारित है, इसकी सटीकता उन परीक्षणों के केवल आहार की स्वतंत्र रैंडमाइज्ड तुलना होने पर निर्भर करती है, जिसकी पुष्टि सुलभ स्रोतों से नहीं की जा सकी; इस साहित्य के संयुक्त विश्लेषणों में एकल कोहोर्ट (cohort) की कई रिपोर्टों की जांच करने की भी आवश्यकता होती है। ये परिणाम लिपिड-मध्यस्थता वाली संभावना का समर्थन करते हैं। वे घटना में कमी को स्थापित नहीं करते हैं, पट्टिका प्रतिगमन, किसी व्यक्ति की प्रतिक्रिया, या वर्जित करने से होने वाला विशेष लाभ असंतृप्त वसा, क्योंकि परीक्षण आहार और तुलनाकर्ता व्यापक रूप से भिन्न थे।
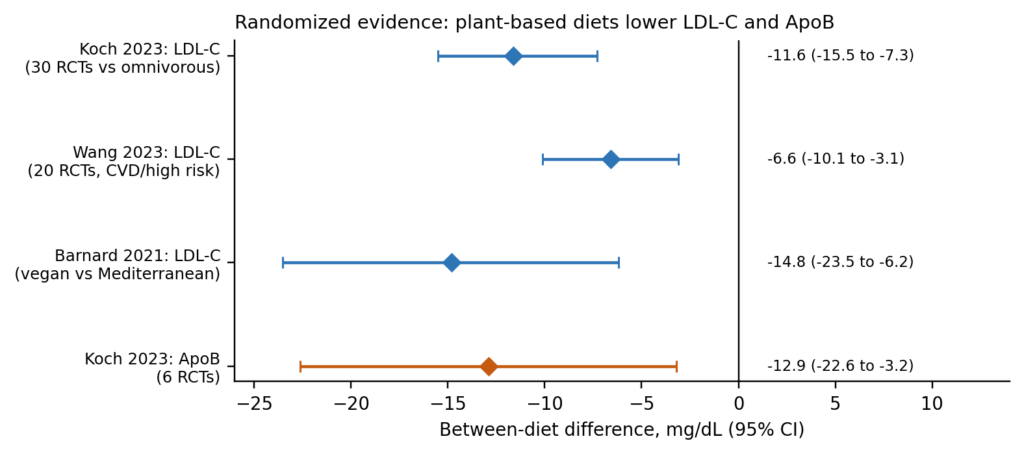
चित्र 4. रैंडमाइज्ड साक्ष्य कि पौधे-आधारित आहार LDL-C और ApoB को कम करते हैं। 95% के साथ आहारों के बीच अंतर कॉन्फिडेंस इंटरवल (विश्वास अंतराल); Koch 2023 मानों को mmol/L (× 38.67) से परिवर्तित किया गया है। अनुमान घटक परीक्षणों को साझा करते हैं और योगात्मक नहीं हैं। स्रोत: Koch 2023; Wang 2023; Barnard 2021 (दवा में बदलाव के बिना प्रतिभागी)।
हृदय रोग वाले या उसके उच्च जोखिम वाले लोगों तक सीमित एक दूसरे मेटा-विश्लेषण ने 20 परीक्षणों (1,878 प्रतिभागी; औसत अवधि 25.4 सप्ताह) को संयोजित किया। शाकाहारी आहार ने LDL-C को 6.6 mg/dL (95% CI 3.1 से 10.1), HbA1c को 0.24 प्रतिशत अंक (95% CI 0.07 से 0.40), और शरीर के वजन को 3.4 kg (95% CI 2.0 से 4.9) कम किया, जिसका सिस्टोलिक रक्तचाप (−0.1 mm Hg; 95% CI −2.8 से 2.6) [7] पर कोई प्रभाव नहीं पड़ा। लेख का की-पॉइंट्स बॉक्स 6.8 mg/dL और 0.25% बताता है; परिणाम अनुभाग और फॉरेस्ट प्लॉट 6.6 mg/dL और 0.24% देते हैं, जिनका उपयोग यहाँ किया गया है। प्रश्न 2 के लिए दो और विवरण महत्वपूर्ण हैं। सामान्य आहार के विरुद्ध, LDL-C 12.9 mg/dL कम हुआ; सक्रिय आहार तुलनाकर्ताओं के विरुद्ध, LDL-C अंतर सांख्यिकीय रूप से महत्वपूर्ण नहीं था। और बेसलाइन LDL-C ने परीक्षणों के बीच की विषमता को स्पष्ट किया [7]। केवल चार परीक्षणों में स्थापित हृदय रोग वाले रोगियों को नामांकित किया गया था, जिनमें से तीन ओर्निश-प्रकार के कार्यक्रम थे।
रक्तचाप। वांग और उनके सहयोगियों द्वारा सारांशित पहले के मेटा-विश्लेषणों में शाकाहारी आहार के साथ सिस्टोलिक रक्तचाप में लगभग 2.5 mm Hg की कमी की रिपोर्ट की गई थी [7]। उच्च जोखिम वाले रोगियों में शून्य परिणाम संभवतः पृष्ठभूमि रक्तचापरोधी थेरेपी और परीक्षणों के दौरान दवाओं में कमी से स्पष्ट होता है, जिसे लेखक बताते हैं कि यह आहार के प्रभावों को छिपा सकता है। रक्तचाप का लाभ केवल पौधों के सेवन तक सीमित नहीं है: डैश डाइट, जिसमें कम वसा वाले डेयरी उत्पाद शामिल हैं, ने नियंत्रित फीडिंग में रक्तचाप को काफी कम किया [11, 16], और प्रत्यक्ष क्रॉसओवर तुलना में भूमध्यसागरीय आहार ने कम वसा वाले वीगन आहार की तुलना में सिस्टोलिक रक्तचाप को अधिक कम किया [23]। इसलिए रक्तचाप VLF-WFPB का सिद्ध लाभ नहीं है। दो लिपिड मेटा-विश्लेषणों के अनुमानों को एक साथ नहीं जोड़ा जाता है; वे परीक्षणों को साझा करते हैं।
4.3 आहार संबंधी कोलेस्ट्रॉल
आहार कोलेस्ट्रॉल सीरम कोलेस्ट्रॉल को स्वतंत्र रूप से बढ़ाता है संतृप्त वसा। फ्रीमैन और उनके सहयोगियों द्वारा उद्धृत अंडा-खिलाने वाले अध्ययनों के मेटा-विश्लेषण में, प्रत्येक अतिरिक्त 100 मिलीग्राम/दिन ने LDL-C को लगभग 1.9 mg/dL और HDL-C को लगभग 0.3 mg/dL बढ़ा दिया; बेसलाइन सेवन कम होने पर प्रतिक्रिया अधिक होती है और आंतों की अवशोषण क्षमता वाले व्यक्तियों के बीच भिन्न होती है [2]। बहुत कम सेवन के आदी लोग भी प्रतिक्रिया देते हैं: आठ ताराहुमारा पुरुषों में, जिनका सामान्य आहार बहुत कम कोलेस्ट्रॉल प्रदान करता था, एक 1,000 मिलीग्राम/दिन के आहार ने कोलेस्ट्रॉल मुक्त चरण के बाद प्लाज्मा कोलेस्ट्रॉल को 113 से बढ़ाकर 147 mg/dL कर दिया [24]। VLF-WFPB अनिवार्य रूप से कोई कोलेस्ट्रॉल प्रदान नहीं करता है; EVADE CAD में, आहार कोलेस्ट्रॉल वीगन शाखा में घटकर 0 मिलीग्राम/दिन के औसत पर आ गया, जबकि AHA शाखा में यह 142 मिलीग्राम/दिन था [9]। LDL-C को कम करने में औसत योगदान मामूली है; व्यक्तिगत योगदान अधिक हो सकता है। AHA का 2026 आहार मार्गदर्शन कहता है कि, अधिकांश लोगों के लिए, हृदय जोखिम कम करने के लिए आहार संबंधी कोलेस्ट्रॉल अब प्राथमिक लक्ष्य नहीं है [25]; इसलिए इसे हटाना VLF-WFPB के पक्ष में एक मामूली हिस्सा है, न कि निर्णायक हिस्सा।
4.4 संतृप्त वसा और इसके स्थान पर क्या लिया जाता है
वर्तमान कोचरेन (Cochrane) समीक्षा में, संतृप्त वसा को कम करने से संयुक्त हृदय संबंधी घटनाओं में कमी आई (जोखिम अनुपात 0.83; 95% CI 0.70 से 0.98; 12 परीक्षण, 53,758 प्रतिभागी), और संतृप्त वसा में बड़ी कटौती, जो कोलेस्ट्रॉल में बड़ी कटौती के रूप में परिलक्षित हुई, उससे अधिक लाभ प्राप्त हुए। उपसमूह विश्लेषणों में संतृप्त वसा को निम्न के साथ बदलने के बीच कोई महत्वपूर्ण अंतर नहीं दिखा बहुअसंतृप्त वसा या कार्बोहाइड्रेट के साथ [26]। उस समीक्षा के मई 2020 के अंक में 0.79 का जोखिम अनुपात बताया गया था; यहाँ रिकॉर्ड के संशोधित संस्करण का उपयोग किया गया है। VLF-WFPB संतृप्त वसा को बहुत कम कर देता है (EVADE वीगन शाखा में ऊर्जा का 4.5% बनाम AHA शाखा में 6.6% [9]), और यह मुख्य रूप से इसे साबुत खाद्य पदार्थों से प्राप्त स्टार्च और फाइबर के साथ बदल देता है। वनस्पति प्रोटीन, विस्कस फाइबर और प्लांट स्टेरोल्स LDL को कम करने वाले अन्य संभावित घटक हैं; वर्तमान डिस्लिपिडिमिया मार्गदर्शन रोगियों को संतृप्त वसा कम करने और फाइबर युक्त पादप खाद्य पदार्थों को बढ़ाने की ओर इंगित करता है [27].
पोर्टफोलियो साक्ष्य एक ही लक्ष्य के लिए एक अलग रास्ता दिखाते हैं। नियंत्रित परीक्षणों (439 प्रतिभागियों) के मेटा-विश्लेषण में, कोलेस्ट्रॉल कम करने वाले NCEP स्टेप II आहार में नट्स, वनस्पति प्रोटीन, विस्कस फाइबर और प्लांट स्टेरोल्स जोड़ने से LDL-C में लगभग 17% की कमी आई, साथ ही ApoB और नॉन-एचडीएल कोलेस्ट्रॉल में भी कमी आई [15]। चूंकि पोर्टफोलियो आहार में नट्स शामिल होते हैं, इसलिए यह दर्शाता है कि आहार के माध्यम से LDL-C में पर्याप्त कमी लाने के लिए नट्स को बाहर करना कोई पूर्व शर्त नहीं है।
5. ApoB से परे: मुख्य प्रश्न (स्तर 2–5)
यदि VLF-WFPB का प्रत्येक लाभ कम ApoB के माध्यम से प्राप्त होता, तो यह आहार ApoB को कम करने के कई विनिमेय तरीकों में से एक होता, जिसमें दवाएं भी शामिल हैं, और इसके विशेष नियमों का आधार केवल इस बात तक सीमित रह जाता कि यह कितनी सीमा तक और कितनी निरंतरता के साथ एथोजेनिक कणको कम करता है। साबुत खाद्य आधारित पादप चिकित्सा (whole-food plant-based medicine) का विशिष्ट दावा यह है कि यह इससे अधिक कार्य करती है: कि साबुत पादप खाद्य पदार्थ एंडोथेलियम, आंत, प्रतिरक्षा संकेतन, रक्तचाप और ऊर्जा संतुलन पर उन तरीकों से कार्य करते हैं जिनसे स्टैटिन नहीं करता। वह दावा जैविक रूप से गंभीर है, और यह इस समीक्षा का केंद्रीय प्रश्न है।
चार प्रकार के साक्ष्य इस पर प्रभाव डालते हैं, जो मजबूती के बढ़ते क्रम में हैं: (1) कोशिकाओं या जानवरों में प्रदर्शित एक तंत्र ऐसी स्थितियों में जहाँ लिपिड अपरिवर्तित या नियंत्रित होते हैं; (2) मानव शारीरिक या बायोमार्कर्स प्रभाव जिन्हें LDL-C परिवर्तन द्वारा नहीं समझाया गया है; (3) मानव परिणाम संघ जो लिपिड के समायोजन के बाद भी बने रहते हैं; और (4) समान ApoB पर आहारों का रैंडमाइज्ड (यादृच्छिक) तुलना। नीचे दिए गए उपखंड ग्रेड इन मानदंडों के विरुद्ध प्रत्येक संभावित मार्ग का मूल्यांकन करते हैं (चित्र 6)। अभी तक कोई भी अध्ययन चौथे प्रकार का प्रमाण प्रदान नहीं करता है।
5.1 फाइबर, आंत के सूक्ष्मजीव, और ब्यूटायरेट
विस्कस फाइबर LDL-C को कम करता है, लेकिन किण्वन योग्य पादप पॉलीसेकेराइड भी आंत माइक्रोबायोमके माध्यम से कार्य कर सकते हैं। 83 आनुवंशिक रूप से विविध, एथेरोस्क्लेरोसिस-संवेदनशील चूहों की प्रजातियों में, ब्यूटायरेट-उत्पादक जीनस रोज़बुरिया की प्रचुरता घाव के आकार के विपरीत आनुपातिक थी और कोलेस्ट्रॉल के साथ सहसंबद्ध नहीं थी। रोगाणु मुक्त एपोलिपोप्राटीन E-की कमी वाले चूहों में जिन्हें परिभाषित बैक्टीरिया समुदायों के साथ रखा गया था, रोज़बुरिया इंटेस्टाइनलिस ने प्रणालीगत सूजन और एथेरोस्क्लेरोसिस को केवल तभी कम किया जब आहार पादप पॉलीसेकेराइड से भरपूर था, और ब्यूटिरत की आंतों में आपूर्ति ने स्वयं एंडोटॉक्सिमिया और एथेरोस्क्लेरोसिस को कम किया [28]। यह इस समीक्षा में आहार-निर्भर, कोलेस्ट्रॉल-स्वतंत्र एथेरोप्रोटेक्टिव तंत्र का सबसे स्पष्ट प्रदर्शन है। यह चूहे के मॉडल से प्राप्त हुआ है, और किसी भी मानव परीक्षण ने यह नहीं दिखाया है कि ब्यूटायरेट उत्पादन बढ़ाने से पट्टिका या घटनाओं में बदलाव आता है।
5.2 हरी पत्तेदार सब्जियों का नाइट्रेट, नाइट्रिक ऑक्साइड और एंडोथेलियम
हरी पत्तेदार सब्जियां, जो एसेल्स्टीन के प्रोटोकॉल का केंद्र हैं, अकार्बनिक नाइट्रेट का मुख्य आहार स्रोत हैं, जिसे शरीर नाइट्रिक ऑक्साइड में एक एंटरोसैलिरी (enterosalivary) मार्ग के माध्यम से परिवर्तित कर सकता है। 53,150 डैनिश वयस्कों में, जिनका 23 वर्षों तक अनुवर्ती अध्ययन किया गया (14,088 हृदय संबंधी घटनाएं), निम्नतम पंचमक (मध्यिका 23 मिलीग्राम/दिन) की तुलना में मध्यम सब्जी-नाइट्रेट सेवन (मध्यिका 59 मिलीग्राम/दिन, लगभग एक कप हरी पत्तेदार सब्जियां) 15% कम हृदय रोग जोखिम (खतरा अनुपात 0.85; 95% CI 0.82 से 0.89) से जुड़ा था, और इस्केमिक हृदय रोग (0.88; 0.82 से 0.94), इस्केमिक स्ट्रोक (0.83; 0.76 से 0.91), और परिधीय धमनी रोग (0.74; 0.67 से 0.83)। यह संबंध लगभग 60 मिलीग्राम/दिन से ऊपर जाकर स्थिर हो गया और रिपोर्ट किए गए समायोजन के बाद भी बना रहा हाइपरकोलेस्ट्रॉलएमीया और अन्य आहार संबंधी कारक, जो मापे गए, संचयी ApoB जोखिम को नियंत्रित करने के समान नहीं है; एक मीडिएशन एनालिसिस (मध्यस्थता विश्लेषण) अनुमान लगाया कि बेसलाइन सिस्टोलिक रक्तचाप ने इसका 21.9% स्पष्ट किया [29]। लेखक ध्यान देते हैं कि सबसे बड़े नाइट्रेट परीक्षण ने उच्च रक्तचाप वाले वृद्ध वयस्कों में रक्तचाप कम नहीं किया, और यह कि अवलोकन संबंधी डेटा सामान्य रूप से सब्जियों के सेवन से नाइट्रेट को अलग नहीं कर सकता; इस कोहॉर्ट में लेट्यूस और आलू ने अधिकांश सब्जी नाइट्रेट की आपूर्ति की [29]। यह निष्कर्ष संपूर्ण-खाद्य लीवर के पत्तेदार-हरे तत्व का समर्थन करता है; यह वीगन आहार के लिए विशिष्ट नहीं है।
एन्डोथेलियल फ़ंक्शन (तीव्र और अल्पकालिक मानव शरीर क्रिया विज्ञान; घटनाओं से प्रासंगिकता अप्रमाणित)। एक उच्च वसा वाले भोजन ने स्वस्थ स्वयंसेवकों में क्षणिक रूप से ब्रेकियल फ्लो-मीडिएटेड फैलाव को खराब कर दिया [30]। उन्हीं जांचकर्ताओं के दस व्यक्तियों के प्रयोग में, जैतून के तेल वाले भोजन ने फ्लो-मीडिएटेड फैलाव को तीव्रता से 31% तक कम कर दिया, और यह कमी तब कम थी जब भोजन में शामिल था एंटीऑक्सीडेंट विटामिन या बालसामिक विनेगर के साथ सलाद [31]। निरंतर भोजन इसके विपरीत संकेत देता है: आठ परीक्षणों के मेटा-विश्लेषण में, जैतून के तेल के हस्तक्षेप ने फ्लो-मीडिएटेड फैलाव को 0.76 प्रतिशत अंक (95% CI 0.27 से 1.24) तक बढ़ा दिया [32], और 805 CORDIOPREV प्रतिभागियों में एक भूमध्यसागरीय आहार ने एक वर्ष के बाद कम वसा वाले आहार की तुलना में फ्लो-मीडिएटेड फैलाव में अधिक सुधार किया [33]। EVADE CAD में आठ हफ्तों के दौरान, EndoPAT-मापा गया एंडोथेलियल कार्य किसी भी समूह में नहीं बदला [9]। न तो तीव्र और न ही अल्पकालिक संवहनी-कार्य के निष्कर्ष घटनाओं पर प्रभाव स्थापित करते हैं।
5.3 सूजन और जन्मजात-प्रतिरक्षा स्मृति
सूजन (मानव यादृच्छिक बायोमार्कर साक्ष्य)। EVADE CAD ने एंजियोग्राफिक कोरोनरी बीमारी वाले 100 रोगियों को आठ सप्ताह के वीगन या AHA-अनुशंसित आहार के लिए यादृच्छिक किया, जिसमें दोनों के लिए किराने का सामान, नमूना मेनू और आहार विशेषज्ञ सहायता दी गई थी। बेसलाइन पर 94–96% लोग स्टैटिन ले रहे थे और आधे से अधिक लोग उच्च खुराक वाले स्टैटिन ले रहे थे। वीगन आहार ने 32% कम उच्च-संवेदनशीलता उत्पन्न की सी-रिएक्टिव प्रोटीन (β 0.68; 95% CI 0.49 से 0.94; P = 0.02), समायोजन के बाद भी सुसंगत। LDL-C 13% कम था (समायोजित β 0.87; 95% CI 0.78 से 0.97), जिसे जांचकर्ताओं ने माध्यमिक एंडपॉइंट्स के लिए अपने बोनफेरोनी थ्रेशोल्ड (α = 0.0015) के तहत महत्वहीन के रूप में वर्गीकृत किया। वजन, HbA1c, अन्य लिपिड, ल्यूकोसाइट सक्रियण मार्कर और जीवन की गुणवत्ता समूहों के बीच भिन्न नहीं थे [9]। महत्वपूर्ण रूप से, EVADE ने बहुत कम वसा वाले भोजन का परीक्षण नहीं किया: आठ सप्ताह में रिपोर्ट की गई औसत वसा का सेवन वीगन समूह में ऊर्जा का 29.9% और AHA समूह में 30.2% था, दोनों समूहों को असंतृप्त तेलों का उपयोग करने के लिए प्रोत्साहित किया गया था और जैतून का तेल दोनों के व्यंजनों में दिखाई दिया, और मुख्य आहार विपरीतता पादप बनाम पशु प्रोटीन थी, जिसमें वीगन समूह में कम संतृप्त वसा और उच्च फाइबर था [9]। hs-CRP परिणाम एक बायोमार्कर निष्कर्ष है; यह कम घटनाओं या ApoB-स्वतंत्र नैदानिक लाभ को स्थापित नहीं करता है।
पशु कार्य सुझाव देते हैं कि आहार कैसे एक स्थायी सूजन संबंधी छाप छोड़ सकता है। LDL-रिसेप्टर-कमी वाले चूहों में, पश्चिमी-आहार खिलाने से प्रणालीगत सूजन पैदा हुई जो मानक भोजन पर लौटने के बाद रक्त से गायब हो गई, फिर भी माइलॉयड प्रोगेनिटर कोशिकाएं फिर से प्रोग्राम की हुई बनी रहीं, जिससे जन्मजात-प्रतिरक्षा प्रतिक्रियाएं बढ़ गईं; चूहे जिनमें इसकी भी कमी थी NLRP3 वे सुरक्षित थे [34]। क्योंकि ये चूहे गंभीर रूप से हाइपरकोलेस्ट्रोलेमिक हैं और ऑक्सीकृत एलडीएल अध्ययन के मानव समूह में शामिल था [34], यह तंत्र लिपोप्रोटीन से स्वतंत्र नहीं है; इसके बजाय यह सुझाव देता है कि आहार के जोखिम का इतिहास, न कि केवल वर्तमान लिपिड स्तर, पट्टिका जीव विज्ञान को आकार दे सकता है। सिमाने (Tsimane) दूसरी ओर इशारा करते हैं: संक्रमण के बोझ के कारण लगभग आधे लोगों में hs-CRP 3 मिलीग्राम/लीटर से अधिक था, फिर भी कोरोनरी कैल्शियम सबसे कम दर्ज किया गया था, जिसे जांचकर्ताओं ने व्याख्या किया है कि जब LDL कम होता है तो सूजन संभवतः एथेरोस्क्लेरोसिस को बढ़ावा नहीं देती है [35].
5.4 ऊर्जा घनत्व, प्रसंस्करण, शरीर का वजन, और ग्लाइसीमिया
शरीर का वजन और ऊर्जा घनत्व (मानव यादृच्छिक बायोमार्कर साक्ष्य)। शाकाहारी आहार ने उच्च जोखिम वाले रोगियों में वजन 3.4 किलोग्राम कम कर दिया [7], और एक क्रॉसओवर परीक्षण में लो-फैट वीगन डाइट ने मेडिटेरेनियन डाइट की तुलना में अधिक वजन कम किया [23]. लाइफस्टाइल हार्ट ट्रायल में, प्रयोगात्मक समूह ने एक वर्ष में 10.9 किलोग्राम वजन कम किया और पांच वर्षों में बेसलाइन से 5.8 किलोग्राम नीचे रहा [6]. वजन कम होना स्वयं LDL-C, रक्तचाप और ग्लाइसेमिया को कम करता है, इसलिए ये प्रभाव लिपिड पथ के साथ ओवरलैप होते हैं और इन्हें इसमें जोड़ा नहीं जा सकता।
इंसुलिन संवेदनशीलता और ग्लाइसेमिया (मानव रैंडमाइज्ड बायोमार्कर साक्ष्य)। HbA1c कुल मिलाकर 0.24 प्रतिशत अंक गिरा और टाइप 2 वाले लोगों में 0.36 अंक मधुमेह [7]. यह मधुमेह वाले लोगों में लिपिड प्रभावों को बढ़ा सकता है, लेकिन फिर से आंशिक रूप से वजन के माध्यम से।
प्रसंस्करण परीक्षण (अनुभाग 3) सीधे एक गैर-लिपिड मार्ग दिखाता है: अल्ट्रा-प्रोसेस्ड भोजन के बजाय अनप्रोसेस्ड के रूप में दिए गए समान पोषक तत्व लक्ष्यों ने स्वतः ऊर्जा सेवन को लगभग 500 किलोकैलोरी/दिन कम कर दिया [19]. रक्तचाप एक और अलग, कारण मार्ग है। यह केवल पौधों पर आधारित खान-पान (अनुभाग 4.2) का प्रदर्शित लाभ नहीं है, लेकिन नाइट्रेट युक्त सब्जियां और पोटेशियम युक्त, कम सोडियम वाले पैटर्न जैसे कि DASH इसे कम करते हैं [11, 16, 29].
5.5 ट्राइमेथिलैमाइन N-ऑक्साइड
गट माइक्रोबायोम और ट्राइमेथिलैमाइन N-ऑक्साइड (मानव जुड़ाव और यंत्रवत परिकल्पना)। गट माइक्रोब्स आहार के पूर्ववर्तियों को परिवर्तित करते हैं जिनमें शामिल हैं कोलीन और कार्नेटिन को ट्राइमेथिलैमाइन में, जिसे होस्ट लिवर एंजाइम फिर इसमें ऑक्सीकृत कर देते हैं TMAO [36]; कोहोर्ट डेटा में सर्कुलेटिंग TMAO ने हृदय संबंधी घटनाओं की भविष्यवाणी की [37]. मेंडेलियन रैंडमाइजेशन विश्लेषणों में आनुवंशिक रूप से अनुमानित TMAO को इसके साथ संबद्ध नहीं पाया गया है कोरोनरी धमनी रोग, मायोकार्डियल इंफार्क्शन, या स्ट्रोक [38], जो एक कारण व्याख्या को कमजोर करता है, और कोई भी परीक्षण यह नहीं दिखाता है कि TMAO को कम करने से घटनाएं कम होती हैं। 2014 की एसेल्स्टिन रिपोर्ट का दावा है कि इसके प्रतिभागियों में TMAO-उत्पादक फ्लोरा होने की संभावना नहीं थी, लेकिन उस कोहोर्ट में TMAO को नहीं मापा गया था [4].
5.6 मानव संकेत जिन्हें ApoB पूरी तरह से स्पष्ट नहीं करता है—और जिन्हें यह करता है
पौधों पर आधारित आहार के अधिकांश मापे गए लाभ ApoB, वजन, रक्तचाप और ग्लाइसेमिया के माध्यम से हो सकते हैं। एक आहार का वास्तविक कुल प्रभाव हो सकता है भले ही इन मध्यस्थों पर कंडीशनिंग के बाद कुछ भी न बचे; अतिरिक्त प्रभाव का प्रश्न अलग है। तीन अवलोकन इस पर प्रभाव डालते हैं। पहला, लाइफस्टाइल हार्ट ट्रायल में, प्रयोगात्मक-समूह का ApoB बेसलाइन पर 1.000 g/L से गिरकर एक वर्ष में 0.769 g/L हो गया, लेकिन पांच वर्षों में 1.014 g/L था, जबकि प्रतिशत व्यास स्टेनोसिस में सुधार जारी रहा; पांच वर्षों में LDL-C बेसलाइन से 20% नीचे रहा [6]. क्योंकि कार्यक्रम में व्यायाम, तनाव प्रबंधन और समूह सहायता भी शामिल थी, और क्योंकि 5वें वर्ष का स्नैपशॉट पिछले वर्षों के दौरान कम संचयी जोखिम को कैप्चर नहीं करता है, इसे ApoB से स्वतंत्र रूप से कार्य करने वाले आहार के रूप में नहीं पढ़ा जा सकता है। दूसरा, STARS के भीतर, प्रगति LDL-C के समायोजन के बाद संतृप्त और कुल वसा सेवन के साथ सहसंबद्ध थी, जो एक अवलोकन संबंधी इन-ट्रायल विश्लेषण है [39]. तीसरा, कोहोर्ट डेटा में शाकाहारी-IHD जुड़ाव का लगभग पांचवां हिस्सा इसके द्वारा मध्यस्थ हो सकता है बॉडी मास इंडेक्स [40], और EPIC-Oxford में स्व-रिपोर्ट किए गए कोलेस्ट्रॉल, रक्तचाप, मधुमेह और बॉडी मास इंडेक्स के समायोजन के बाद शाकाहारी-IHD जुड़ाव काफी कमजोर हो गया [41]. किसी भी परीक्षण ने मेल खाने वाले ApoB, रक्तचाप और वजन पर आहार पैटर्न की तुलना नहीं की है, जो कि मध्यस्थों से परे प्रभाव स्थापित करने के लिए आवश्यक डिजाइन है।
चित्र 5 लाइफस्टाइल हार्ट ट्रायल डेटा प्रदर्शित करता है। यद्यपि यह ApoB से स्वतंत्र आहार प्रभाव स्थापित नहीं कर सकता है, यह परिकल्पना के लिए सबसे अच्छा नैदानिक प्रदर्शन बना हुआ है: प्रयोगात्मक समूह ने कोई लिपिड दवाएं नहीं लीं, और प्रतिशत में परिवर्तन स्टेनोसिस एक वर्ष में −1.75 अंक से बढ़कर पांच वर्ष में −3.07 अंक तक जारी रहा, जब ApoB 101.4 mg/dL (बेसलाइन 100.0) पर वापस आ गया था, जबकि नियंत्रण समूह की स्थिति खराब हो गई [6]. दो और अवलोकन स्थिति को स्पष्ट करते हैं। पहला, स्कैनिंग के समय सिमाने (Tsimane) का औसत ApoB 97 mg/dL था, जो विशेष रूप से कम नहीं था, फिर भी लगभग कोई कोरोनरी कैल्शियम नहीं था; उनका LDL-C 2004 से 2011 तक औसतन लगभग 71 mg/dL (1.84 mmol/L) रहा और तब से बढ़ा है, और वे दिन में घंटों शारीरिक गतिविधि में बिताते हैं [35], इसलिए जीवनभर का जोखिम और गतिविधि इसे किसी भी आहार कारक की तरह ही समझा सकती है। दूसरा, एसेलस्टिन 1995 कोहॉर्ट, जिसे अक्सर इस तर्क के लिए उद्धृत किया जाता है, इसका समर्थन नहीं कर सकता: प्रत्येक रोगी ने कोलेस्ट्रॉल कम करने वाली दवाएं लीं और औसत LDL-C 71.6 mg/dL था [42], इसलिए सहवर्ती लिपिड कमी सुधार के एक हिस्से के लिए एक प्रशंसनीय स्पष्टीकरण है, और अनियंत्रित डिज़ाइन आहार के योगदान को अलग नहीं कर सकता है या यह नहीं दिखा सकता है कि ApoB से परे कोई अन्य मार्ग शामिल था।
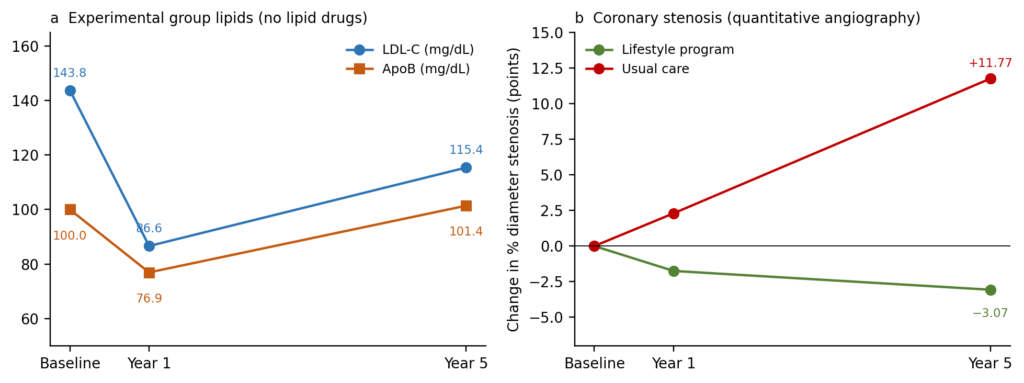
चित्र 5. लाइफस्टाइल हार्ट ट्रायल। (a) प्रयोगात्मक समूह में LDL-C और ApoB, जिसने कोई लिपिड-कम करने वाली दवाएं नहीं लीं (ApoB g/L × 100 से परिवर्तित)। (b) मात्रात्मक एंजियोग्राफी पर प्रतिशत व्यास स्टेनोसिस में परिवर्तन, पांच साल की एंजियोग्राफी वाले 35 प्रतिभागियों के लिए 1998 की पांच साल की रिपोर्ट से प्लॉट किया गया; 1990 की एक साल की रिपोर्ट सभी 48 प्रतिभागियों को कवर करती है और थोड़े अलग बेसलाइन देती है, इसलिए इसके मान यहां प्लॉट नहीं किए गए हैं। 60% नियंत्रण समूहों ने पहले और पांचवें वर्ष के बीच लिपिड दवाएं शुरू कीं।
5.7 ApoB से परे मामले का आकलन
अतिरिक्त-लाभ की परिकल्पना इसलिए सशर्त है: एक सख्त पैटर्न दूसरे स्वस्थ आहार से बेहतर प्रदर्शन कर सकता है यदि यह ApoB, रक्तचाप, वजन, या चयापचय स्वास्थ्य खराब पालन या पोषण संबंधी नुकसान के बिना। “वीगन,” “कोई तेल नहीं,” और “10% वसा” अपने आप में मान्य नहीं हैं सरोगेट एंडपॉइंट्स। न ही अल्पकालिक आहार लिपिड परिवर्तन को दवा-परीक्षण ढलानों का उपयोग करके यंत्रवत् रूप से एसेलस्टिन-विशिष्ट घटना कमी में परिवर्तित किया जा सकता है।
कुल मिलाकर, ApoB से परे का मामला जैविक रूप से प्रशंसनीय है और आंशिक रूप से समर्थित है। पशु मॉडल एक आहार-निर्भर, कोलेस्ट्रॉल-स्वतंत्र तंत्र (फाइबर और ब्यूटायरेट) और स्थायी भड़काऊ स्मृति के एक तंत्र को प्रदर्शित करते हैं; मानव समूह हाइपरकोलेस्ट्रोलेमिया के समायोजन के बाद पत्तेदार-हरे नाइट्रेट को कम हृदय जोखिम से जोड़ते हैं, और न्यूनतम प्रसंस्कृत पादप खाद्य पदार्थों को कम जोखिम से जोड़ते हैं; और एक रैंडमाइज्ड ट्रायल से पता चलता है कि केवल प्रसंस्करण ही ऊर्जा सेवन को बदल देता है [18, 19, 28, 29, 34]। इसके विपरीत, पारंपरिक जोखिम कारकों के समायोजन के बाद EPIC-Oxford में शाकाहारी-कोरोनरी संबंध काफी कमजोर हो गया [41], आनुवंशिक साक्ष्य TMAO को कारण के रूप में समर्थन नहीं करते हैं [38], और किसी भी परीक्षण ने मिलान किए गए ApoB पर आहार की तुलना नहीं की है। चित्र 6 पथ के आधार पर साक्ष्यों का सार प्रस्तुत करता है; प्रस्तावित परीक्षण (अनुभाग 17) लापता परीक्षण की आपूर्ति के लिए डिज़ाइन किया गया है।
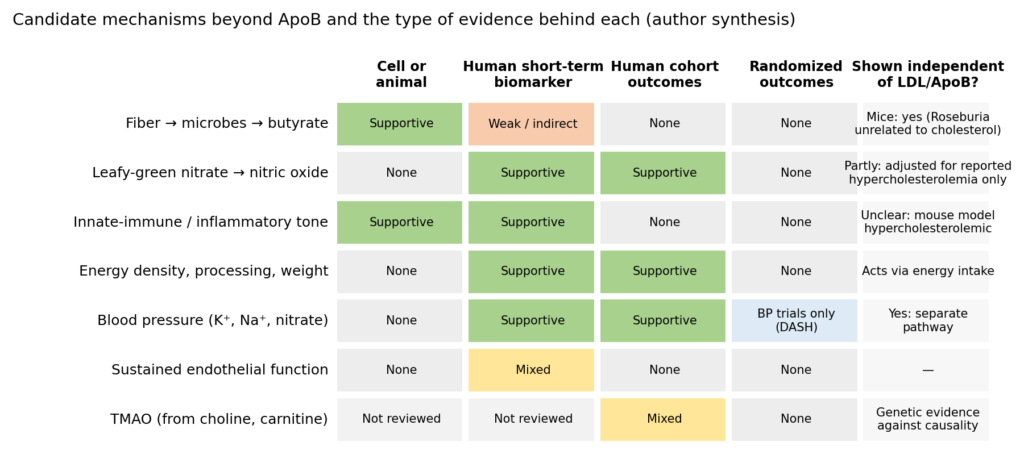
चित्र 6. ApoB से परे उम्मीदवार तंत्र और प्रत्येक के लिए साक्ष्य का प्रकार। अनुभाग 5 में उद्धृत स्रोतों का लेखक संश्लेषण; “सहायक” साक्ष्य की दिशा को इंगित करता है, न कि मानव एथेरोस्क्लेरोसिस पर कारण प्रभाव का प्रमाण।
6. ग्रामीण चीन (टियर 4)
6.1 क्या मापा गया था
चाइना स्टडी I ने 65 ग्रामीण काउंटियों और 130 गांवों में आहार, रक्त और मूत्र सर्वेक्षणों के साथ काउंटी मृत्यु दर डेटा को जोड़ा, जिसमें प्रति गांव 50 वयस्कों का नमूना लिया गया; आहार और रक्त 1983-1984 में एकत्र किए गए थे [43]। औसत ग्रामीण आहार में 14% ऊर्जा वसा से, 71% कार्बोहाइड्रेट से, 5% शराबसे, और 10% प्रोटीन से प्राप्त होती थी, जिसमें से लगभग 11% पशु मूल का था (कुल ऊर्जा का लगभग 1%); फाइबर का सेवन 33 g/day था और औसत बॉडी मास इंडेक्स 20.5 [43]। औसत सीरम कुल कोलेस्ट्रॉल 127 mg/dL था, जिसकी तुलना में 20-74 वर्ष की आयु के अमेरिकी वयस्कों में यह 203 mg/dL था [43]। आहार में पशु खाद्य पदार्थों की मात्रा कम थी, यह वीगन नहीं था; लेखक 1950-1980 के ग्रामीण आहारों का वर्णन 3-6% पशु-आधारित खाद्य पदार्थों के रूप में करते हैं [43].
6.2 कोरोनरी आंकड़े क्या हैं
व्यापक रूप से उद्धृत कोरोनरी तुलना मृत्यु दर का उपयोग करती है, न कि घटना दर का, जो 1973-1975 में दर्ज की गई थी और 0-64 वर्ष की आयु पर सीमित थी: ग्रामीण चीन में प्रति 1,00,000 पुरुषों पर 4.0 और प्रति 1,00,000 महिलाओं पर 3.4, जबकि संयुक्त राज्य अमेरिका में 66.8 और 18.9, जो 1989 की WHO सांख्यिकी वार्षिक पुस्तक से लिया गया है, जिससे 16.7 और 5.6 का अनुपात प्राप्त होता है [43]. Four features limit interpretation. The mortality period precedes the dietary and blood survey by about a decade. Excluding deaths after age 64 removes the ages at which most coronary deaths occur. Death certification and coronary diagnosis in rural China in the 1970s differ from US practice, so under-ascertainment cannot be excluded. And competing mortality from infections and other causes of death, which the authors describe as clustering in the same counties, removes people before coronary disease manifests [43]. No प्लाक का बोझ was measured.
6.3 What the county correlations show
Across counties, coronary mortality correlated positively with plasma ApoB (r = 0.37) and with an index of salt intake (r = 0.42), and inversely with green-vegetable intake; ApoB in turn correlated with animal protein and meat intake [43]. Coronary mortality also correlated with wheat flour intake (r = 0.67), which the authors attribute partly to co-varying milk, salt, triglycerides, and body weight [43]. The authors themselves note that the county, not the individual, is the unit of analysis, so the data cannot show whether low disease rates reflect uniformly low animal-food intake or fewer individuals eating more [43].
6.4 Confounding and alternative explanations
Energy intake per kilogram was about 30% higher than in the United States with far less मोपापन, which the authors attribute to greater daily energy expenditure such as cycling to work [43]. Physical activity, body weight, tobacco use, socioeconomic conditions, health care access, and diagnostic ascertainment all differ between these populations and the United States. The coronary paper does not report ischemic or हेमरेजिक स्ट्रोक, and this review makes no claim about stroke subtypes in these counties. This review also did not re-verify post-1990 trend data; claims that China’s later dietary transition proves a causal diet effect should rest on contemporaneous individual-level cohorts.
6.5 Checking the secondary summary
Freeman and colleagues’ 2017 review is a useful route to these data but should not be quoted in place of them [2]. Its table correctly gives the 0–64 age restriction and the 127 mg/dL cholesterol, but lists macronutrients of 14% fat, 71% carbohydrate, and 10% protein, which sum to 95% because the 5% alcohol in the original is omitted [2, 43]. Its Tarahumara entry reports 528 people surveyed and a mean adult cholesterol of 136 mg/dL [2]; the original abstract reports 523 people aged 5 to 70 with a mean of 125 mg/dL overall and 116 mg/dL in children, a diet of 12% fat, 2% saturated fat, 71 mg/day cholesterol, and 75% carbohydrate, and a virtual absence of उच्च रक्तचाप, obesity, and the usual age-related rise in cholesterol [44]. The difference in denominators could not be resolved without the full text. The Tarahumara study measured lipids and diet, not coronary outcomes.
6.6 What rural China contributes
The rural Chinese data are consistent with the cumulative-exposure hypothesis: populations with lifelong low animal-food and saturated-fat intake had low cholesterol, and county coronary mortality tracked ApoB. That strengthens plausibility for Q1. It says nothing decisive about Q2 or Q3, because the diet was neither vegan nor compared with a high-quality alternative, and because activity, body size, and competing mortality are inseparable from diet in these data.
7. Traditional Okinawa (Tier 4)
The traditional ओकिनावन आहार is known chiefly from a 1949 survey, conducted during post-war scarcity and US administration, as analyzed by the Willcox group. Sweet potato supplied about 69% of energy; total energy intake was about 1,785 kcal/day; fat supplied roughly 6% of energy; and meat intake was a few grams per day, with small amounts of fish, soy, and seaweed [45, 46]. The Willcox group estimates that adults ate about 11% fewer calories than needed to maintain weight until the late 1960s, with a lean average body mass index of 21 [47]. Interpretation is contested: one critic has argued that the Okinawan data reflect severe malnutrition, whereas Gavrilova and Gavrilov, responding, attribute the later loss of longevity advantage to westernization of the diet and note that a low infectious burden may also have contributed [48]. A single post-war survey cannot establish lifelong intake.
Coronary outcomes should be judged directly rather than through longevity. The same group reports that older Okinawans have about 80% less coronary mortality than the US population, based on age-adjusted vital statistics rather than individual dietary linkage [47]. The advantage has not persisted: Okinawans who did not experience the energy-restricted era now have higher body mass index, more type 2 diabetes, and worse cardiovascular risk factors than other Japanese, and the prefecture’s life-expectancy advantage is now confined to older ages [47]. That transition is compatible with a dietary contribution but equally with changes in energy balance, activity, and other exposures.
Okinawa informs the hypothesis in a limited way. It shows that a very-low-fat, high-carbohydrate, plant-predominant diet is compatible with low coronary mortality. It does not show that complete exclusion of animal foods is necessary, because the traditional diet included pork and fish, and it cannot separate low fat from caloric restriction, low body size, physical labor, or आनुवंशिकी. Its shared features with DASH and Mediterranean patterns are high vegetable and legume intake, low saturated fat, and low energy density; its distinctive features are very low total fat, a single dominant starchy staple, and chronic mild energy restriction.
8. Other Traditional Populations: The Tsimane and Kitava (Tier 4)
The Tsimane. The Tsimane, forager-horticulturalists of the Bolivian Amazon, provide the only traditional-population data in this review with direct कोरोनरी इमेजिंग. Of 705 adults aged 40 to 94 scanned in 2014–2015, 596 (85%) had no coronary धमनी calcium, 89 (13%) had scores of 1–100, and 20 (3%) had scores above 100; among those older than 75, 31 (65%) had none and four (8%) had scores of 100 or more [35]. Mean LDL-C was 91 mg/dL and HDL-C 39.5 mg/dL, and obesity, hypertension, हाइपरग्लाइसीमिया, and regular धूम्रपान were rare. Compared with the US MESA cohort, the Tsimane reached a nonzero कैल्शियम स्कोर about 24 years later and a score of 100 or more about 28 years later [35] (Figure 7).
The Tsimane diet is low in fat and minimally processed but not plant-exclusive: about 14% of energy from protein, 14% from fat, and 72% from carbohydrate, an estimated 38 g of fat per day including 11 g of saturated fat and no ट्रांस फैट, with rice, plantain, manioc, and corn as staples and meat and fish obtained by hunting and fishing [35]. Men and women average 6–7 and 4–6 hours of physical activity per day. The limits are important: calcium scoring cannot detect गैर-कैल्सीकृत पट्टिका, the design is cross-sectional, and outcome data are thin, with one possible myocardial infarction among 50 recent adult deaths ascertained by verbal autopsy. LDL-C has risen by about 0.16 mmol/L per year since 2011 as motorized river travel improved access to market food [35], a natural experiment whose coronary consequences are not yet known.
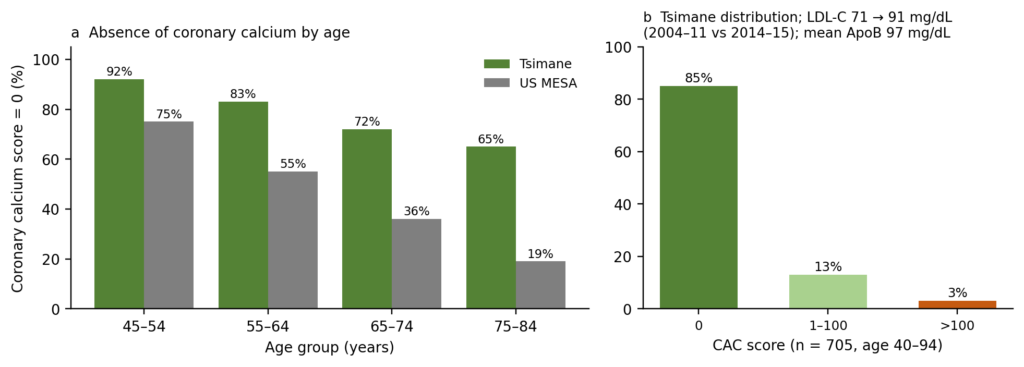
Figure 7. Coronary artery calcium in the Tsimane. (a) Proportion with a calcium score of zero by age group, Tsimane versus US MESA, as labeled in Figure 2 of Kaplan 2017. (b) Distribution of scores among 705 Tsimane adults. Calcium scoring does not detect noncalcified plaque.
Kitava. On Kitava in the Trobriand Islands, where tubers, fruit, fish, and coconut are dietary staples, semi-structured interviews with 213 adults identified no case corresponding to stroke, sudden death, or एनजाइना, and resting electrocardiograms showed few abnormalities [49]. Smoking was common: 76% of men and 80% of women over 20 smoked in the risk-factor survey [50]. The evidence rests on interviews and electrocardiograms rather than imaging or death registration.
What these populations add. None was vegan, and their fat intakes were not uniformly low in saturated fat. The Kitavan diet supplied about 21% of energy as fat and 17% as saturated fat, mostly lauric and myristic acid from coconut [51], a clear exception to the pattern. What rural China, traditional Okinawa, the Tsimane, and Kitava share is diets built from whole, minimally processed staples, leanness, and in most cases high physical activity. The pattern supports the cumulative-exposure argument and the whole-food lever; it provides no support for the claim that complete exclusion of animal foods is required. Fat intake ranged from very low in Okinawa to low among the Tsimane, and coconut was a Kitavan staple.
9. Prospective Cohort Evidence (Tier 3)
The most comprehensive cohort meta-analysis included 13 prospective cohorts with 844,175 participants. Compared with non-vegetarians, vegetarians had lower risk of cardiovascular disease (सापेक्ष जोखिम 0.85; 95% CI 0.79 to 0.92; 8 cohorts) and ischemic heart disease (0.79; 95% CI 0.71 to 0.88; 8 cohorts), but not of total stroke (0.90; 95% CI 0.77 to 1.05; 12 cohorts). For vegans the ischemic heart disease estimate was 0.82 (95% CI 0.68 to 1.00; 6 studies), and the cardiovascular disease estimate 0.92 (95% CI 0.79 to 1.06). Risk of bias was moderate in eight cohorts and serious in five [40]. Incidence estimates were used in preference to mortality where both were reported. The IHD association was weaker when early follow-up was excluded, about one-fifth of it appeared attributable to body mass index, and the E-value was 1.86 (lower confidence limit 1.49), meaning an unmeasured कन्फाउंडर (भ्रामक कारक) would need associations of that strength with both diet and disease to explain it away [40].
The “40% lower coronary risk” figure sometimes attached to vegetarian diets traces to a meta-analysis restricted to Seventh-day Adventist cohorts, which reported a relative risk of 0.60 (95% CI 0.43 to 0.80) for coronary events [2, 52]. That estimate is population-specific and should not be generalized. Several Adventist and Oxford cohorts recur across meta-analyses, so repeated citation is not independent corroboration. Cohort vegetarian and vegan categories are defined by exclusion of animal foods, not by total fat, so none of this evidence tests the very-low-fat component.
Endpoint-specific data matter. In EPIC-Oxford (48,188 participants followed for 18.1 years), vegetarians including vegans had a 22% lower rate of ischemic heart disease than meat eaters (hazard ratio 0.78; 95% CI 0.70 to 0.87), equivalent to about 10 fewer cases per 1,000 people over 10 years; adjustment for self-reported high cholesterol, high blood pressure, diabetes, and body mass index attenuated the estimate to 0.90 (95% CI 0.81 to 1.00). The same group had a 20% higher rate of total stroke (1.20; 95% CI 1.02 to 1.40), about three more cases per 1,000 over 10 years, mostly hemorrhagic, and this association did not attenuate with risk-factor adjustment [41]. Coronary benefit and stroke risk must therefore be reported separately, and the attenuation of the coronary association is consistent with benefit running largely through conventional risk factors.
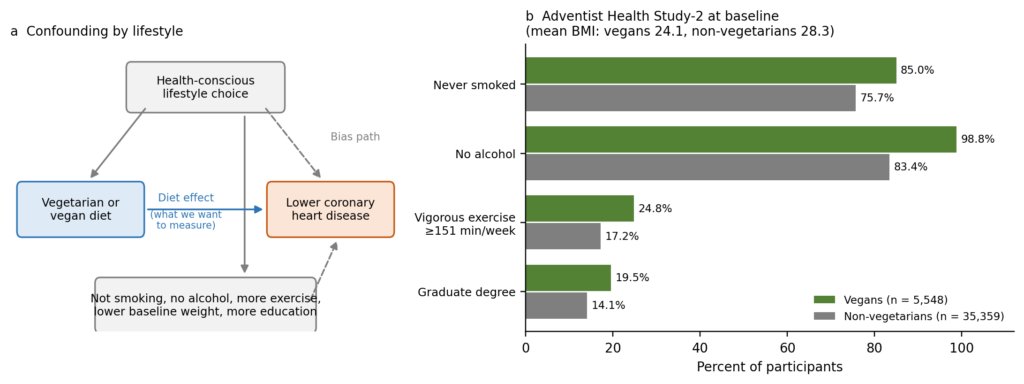
Figure 8. Prospective cohort estimates for vegetarian and vegan diets. The coronary association weakens after adjustment for conventional risk factors (EPIC-Oxford), and stroke risk is not lower. Estimates are shown side by side, not pooled; several cohorts overlap across meta-analyses. Sources: Dybvik 2023; Tong 2019; Orlich 2013; Kwok 2014.
9.1 Healthy-user bias: why associations are hard to read
कोहोर्ट अध्ययन उन लोगों की तुलना करते हैं जिन्होंने अलग-अलग आहार चुने हैं, और जो लोग शाकाहारी आहार चुनते हैं वे आमतौर पर अन्य स्वस्थ आदतें भी अपनाते हैं। इसे स्वस्थ-उपयोगकर्ता पूर्वाग्रह (healthy-user bias) कहा जाता है, जो कन्फाउंडिंग का एक रूप है: बीमारी में देखा गया पूरा या आंशिक अंतर आहार के बजाय अन्य आदतों के कारण हो सकता है। एडवेंटिस्ट डेटा इस समस्या को स्पष्ट रूप से दिखाता है। एडवेंटिस्ट हेल्थ स्टडी-2 में गैर-शाकाहारियों की तुलना में, वीगन लोगों द्वारा कभी धूम्रपान न करने की संभावना अधिक थी (75.7% के मुकाबले 85.0%), शराब बिल्कुल न पीने की संभावना कहीं अधिक थी (83.4% के मुकाबले 98.8%), सप्ताह में कम से कम 151 मिनट तक जोरदार व्यायाम करने की संभावना अधिक थी (17.2% के मुकाबले 24.8%), स्नातक की डिग्री होने की संभावना अधिक थी (14.1% के मुकाबले 19.5%), और वे अधिक दुबले थे (औसत बॉडी मास इंडेक्स 28.3 के मुकाबले 24.1) [53] (चित्र 9)। लेखक बताते हैं कि शाकाहारी आहार का सचेत जीवनशैली चुनाव स्वयं परिणामों को प्रभावित कर सकता है और अनियंत्रित कन्फाउंडिंग की संभावना बनी रहती है [53].
शोधकर्ता इस पूर्वाग्रह को कम करने के लिए कई उपकरणों का उपयोग करते हैं, और प्रत्येक की अपनी सीमाएं हैं। समान लोगों की तुलना करना: एडवेंटिस्ट हेल्थ स्टडी-2 और EPIC-ऑक्सफोर्ड दोनों में, गैर-शाकाहारी तुलना समूह स्वयं अपेक्षाकृत स्वास्थ्य के प्रति जागरूक है, और बहुत कम एडवेंटिस्ट धूम्रपान या शराब का सेवन करते हैं, जो अंतर को पूरी तरह खत्म किए बिना उसे कम कर देता है [53]. सांख्यिकीय समायोजन (Statistical adjustment): मॉडल धूम्रपान, व्यायाम, शिक्षा और इसी तरह के कारकों के लिए समायोजन करते हैं, लेकिन केवल उन कारकों के लिए जिन्हें मापा गया था, और केवल उतनी ही सटीकता के साथ जितनी सटीकता से उन्हें मापा गया था। समायोजन के प्रभाव को देखना: जब EPIC-ऑक्सफोर्ड ने अपने मॉडल में कोलेस्ट्रॉल, रक्तचाप, मधुमेह और बॉडी मास इंडेक्स को जोड़ा, तो शाकाहारी-इस्केमिक हृदय रोग का जोखिम अनुपात 0.78 से बदलकर 0.90 हो गया [41]; यह बताता है कि अधिकांश लाभ उन जोखिम कारकों के माध्यम से मिलता है, जिसकी अपेक्षा तब की जाती है जब आहार काम करता है, और यह यह भी दिखाता है कि अनुमान मॉडलिंग विकल्पों के प्रति कितना संवेदनशील है। मजबूती का परिमाण निर्धारण (Quantifying robustness): डाइबविक मेटा-विश्लेषण में, इस संबंध को पूरी तरह से समझाने के लिए एक बिना मापे गए कन्फाउंडर को आहार और हृदय रोग दोनों के साथ 1.86 के सापेक्ष जोखिम की आवश्यकता होगी [40]. अवधि और आयु: पांच कोहोर्ट्स के एक संयुक्त विश्लेषण में, शाकाहारियों में कम इस्केमिक हृदय रोग मृत्यु दर केवल उन लोगों तक सीमित थी जिन्होंने पांच साल से अधिक समय तक अपने आहार का पालन किया था, और यह कम उम्र में अधिक थी (65 वर्ष से कम आयु में 45% कम, 65-79 की आयु में 31% कम, और 80-89 की आयु में 8% कम, जो महत्वपूर्ण नहीं थी) [54]। आहार की अवधि के साथ संबंध वही है जो एक कारण प्रभाव (causal effect) उत्पन्न करेगा, हालांकि दीर्घकालिक शाकाहारी अन्य दीर्घकालिक आदतों में भी भिन्न हो सकते हैं।
दो और अवलोकन दोनों पहलुओं को दिखाते हैं। एक मेटा-विश्लेषण में गैर-एडवेंटिस्ट कोहोर्ट्स (0.84; 95% CI 0.74 से 0.96) की तुलना में एडवेंटिस्ट कोहोर्ट्स (सापेक्ष जोखिम 0.60) में एक बड़ा इस्केमिक हृदय रोग संबंध पाया गया [52]। वह अंतर एडवेंटिस्ट लोगों के बीच अधिक मजबूत स्वास्थ्य-उपयोगकर्ता प्रभाव को दर्शा सकता है, या यह दर्शा सकता है कि एडवेंटिस्ट शाकाहारी वास्तव में क्या खाते हैं: एडवेंटिस्ट वीगन ने एक दिन में लगभग 46–47 ग्राम फाइबर की सूचना दी, जबकि EPIC-ऑक्सफोर्ड वीगन में यह लगभग 26–28 ग्राम था [53]। और विपरीत कारणता—बीमारी के शुरुआती दौर के बाद आहार बदलने वाले लोग—नामांकन के समय पूर्व हृदय रोग वाले लोगों को बाहर करने से कम तो होता है लेकिन समाप्त नहीं होता है, जैसा कि दोनों कोहोर्ट्स ने किया था [41, 53].
इनमें से किसी का भी यह मतलब नहीं है कि कोहोर्ट साक्ष्यों को नजरअंदाज कर दिया जाना चाहिए। यह विशाल, दीर्घकालिक, विभिन्न देशों में सुसंगत है, और रैंडमाइज्ड लिपिड परीक्षणों और जीव विज्ञान के साथ संरेखित है। इसे टियर 3 साक्ष्य के रूप में देखा जाना चाहिए: संबंध के लिए मजबूत, कारण के लिए सहायक लेकिन निर्णायक नहीं, और अपने आप में एक स्वस्थ आहार की दूसरे के मुकाबले तुलना करने में असमर्थ।
चित्र 9. स्वस्थ-उपयोगकर्ता पूर्वाग्रह। (ए) कैसे एक जीवनशैली चुनाव आहार के अलावा अन्य माध्यमों से आहार को हृदय रोग के कम जोखिम से जोड़ सकता है। (बी) एडवेंटिस्ट हेल्थ स्टडी-2 में वीगन और गैर-शाकाहारियों की आधारभूत विशेषताएं, जैसा कि ओरलिच 2013 में रिपोर्ट किया गया है, आयु, लिंग और नस्ल द्वारा मानकीकृत।
9.2 क्या वीगन अन्य शाकाहारियों की तुलना में बेहतर करते हैं?
वीगन आहार में सभी पशु खाद्य पदार्थ वर्जित होते हैं; लैक्टो-ओवो शाकाहारी आहार में डेयरी और अंडे शामिल होते हैं; पेस्को-शाकाहारी आहार में मछली शामिल होती है। यदि पशु खाद्य पदार्थों के पूर्ण बहिष्कार से अतिरिक्त सुरक्षा मिलती, तो वीगन को अन्य समूहों की तुलना में बेहतर प्रदर्शन करना चाहिए था। कोहोर्ट डेटा ऐसा नहीं दिखाते हैं (चित्र 10)।
एडवेंटिस्ट हेल्थ स्टडी-2। माँसाहार न करने वालों की तुलना में, इस्केमिक हृदय रोग से मृत्यु का जोखिम अनुपात वीगन लोगों के लिए 0.90 (95% CI 0.60 से 1.33), लैक्टो-ओवो शाकाहारियों के लिए 0.82 (0.62 से 1.06), और पेस्को-शाकाहारियों के लिए 0.65 (0.43 से 0.97) था, जो एकमात्र सांख्यिकीय रूप से महत्वपूर्ण कमी थी [53]। पुरुषों में, वीगन लोगों के लिए इस्केमिक हृदय रोग से मृत्यु का जोखिम अनुपात 0.45 (0.21 से 0.94) और हृदय संबंधी मृत्यु के लिए 0.58 (0.38 से 0.89) था; महिलाओं में संबंधित अनुमान 1.39 (0.87 से 2.24) और 1.18 (0.88 से 1.60) थे [53]। पूरे समूह में औसतन 5.79 वर्षों में 372 इस्केमिक हृदय रोग से मौतें दर्ज की गईं, इसलिए ये उप-समूह अनुमान सटीक नहीं हैं, और शाकाहारी आहार का हृदय मृत्यु दर के साथ संबंध लिंग के अनुसार काफी भिन्न था [53]। 88,400 प्रतिभागियों के लंबे समय तक चले 2024 के फॉलो-अप में, शाकाहारियों में कुल मिलाकर इस्केमिक हृदय रोग मृत्यु दर कम थी, लेकिन वीगन आहार का संबंध कम होने से नहीं था सभी कारणों से होने वाली मृत्यु दर पुरुषों और महिलाओं दोनों में मिलाकर; वीगन पुरुषों में मृत्यु दर केवल कम उम्र में ही कम थी [55].
EPIC-Oxford और पूल्ड कोहोर्ट्स। माँसाहारियों की तुलना में, EPIC-Oxford में इस्केमिक हृदय रोग की घटना वीगन लोगों (67 मामले) में 0.82 (0.64 से 1.05), लैक्टो-ओवो शाकाहारियों में 0.77 (0.69 से 0.86), और मछली खाने वालों में 0.87 (0.77 से 0.99) थी [41]। पाँच कोहोर्ट्स के पूल्ड विश्लेषण में, इस्केमिक हृदय रोग मृत्यु दर नियमित माँसाहारियों की तुलना में वीगन लोगों में 26% कम और लैक्टो-ओवो शाकाहारियों और मछली खाने वालों दोनों में 34% कम थी [54]। वीगन आहार की एक व्यवस्थित समीक्षा में पाया गया कि कम से कम 7,380 वीगन लोगों को शामिल करने वाले तीन कोहोर्ट अध्ययनों में से किसी ने भी वीगन लोगों के लिए किसी भी प्राथमिक हृदय रोग परिणाम के काफी अधिक या कम जोखिम की सूचना नहीं दी [56].
यह क्या दिखाता है और क्या नहीं। वीगन लोगों की संख्या कम है, इसलिए उनके अनुमान शून्य होने के बजाय विस्तृत और अनिर्णायक हैं। इस समीक्षा के लिए अधिक महत्वपूर्ण बात यह है कि इन कोहोर्ट्स में वीगन लोग VLF-WFPB का पालन नहीं कर रहे थे: EPIC-Oxford के वीगन लोगों को वसा से 28.1% ऊर्जा मिली और वे दिन में लगभग 26 ग्राम फाइबर खाते थे [41], जो न तो वसा में बहुत कम है और न ही विशेष रूप से साबुत खाद्य पदार्थों में उच्च है। ये कोहोर्ट्स यह स्थापित नहीं करते हैं कि वीगन लोगों में लैक्टो-ओवो शाकाहारियों या मछली खाने वालों की तुलना में हृदय रोग का जोखिम कम होता है; वे समानता या हीनता भी स्थापित नहीं करते हैं, क्योंकि प्रत्येक समूह की तुलना अन्य के बजाय माँसाहारियों से की जाती है, और EPIC-Oxford में वीगन बिंदु अनुमान संख्यात्मक रूप से मछली खाने वालों की तुलना में कम था। एडवेंटिस्ट हेल्थ स्टडी-2 के भीतर, नट्स और बीजों से प्राप्त प्रोटीन हृदय मृत्यु दर में 40% की कमी से जुड़ा था, और माँस से प्राप्त प्रोटीन 61% अधिक मृत्यु दर से जुड़ा था, जिसमें उच्चतम और निम्नतम पंचमक की तुलना की गई थी; शाकाहारी आहार प्रकार के समायोजन के बाद भी ये संबंध बने रहे [57]। वह पैटर्न पौधे-आधारित प्रोटीन और नट्स का पक्ष लेता है। यह नट्स या सभी पशु खाद्य पदार्थों को बाहर करने का पक्ष नहीं लेता है।
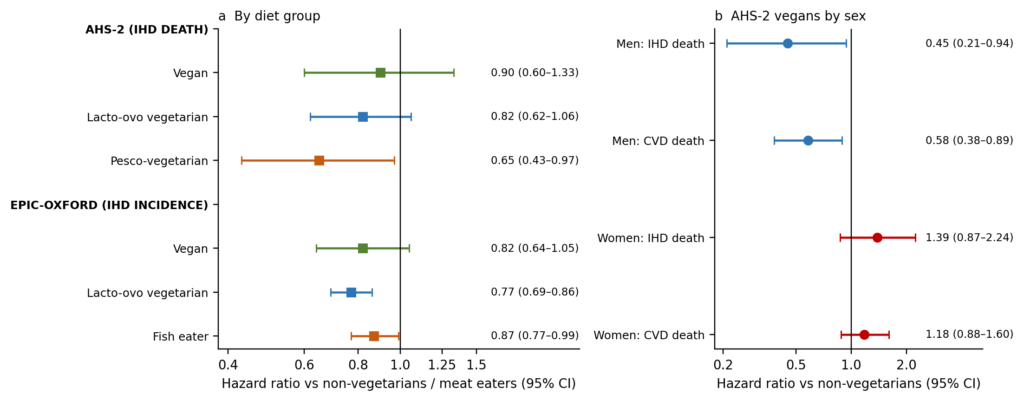
चित्र 10. अन्य शाकाहारी समूहों की तुलना में वीगन। (a) एडवेंटिस्ट हेल्थ स्टडी-2 (मौतें) और EPIC-Oxford (घटना मामले) में आहार समूह द्वारा इस्केमिक हृदय रोग, प्रत्येक की तुलना गैर-शाकाहारियों या माँसाहारियों से की गई है। (b) एडवेंटिस्ट हेल्थ स्टडी-2 वीगन लिंग के अनुसार। विस्तृत अंतराल वीगन लोगों की कम संख्या को दर्शाते हैं। स्रोत: Orlich 2013 (तालिका 4); Tong 2019 (पूरक तालिका 3)।
9.3 चीनी और ताइवानी शाकाहारी
इस समीक्षा की खोज में मुख्य भूमि चीन से वीगन लोगों और सर्वाहारी लोगों के बीच हृदय रोग परिणामों की तुलना करने वाला कोई भविष्योन्मुखी अध्ययन नहीं मिला। उपलब्ध चीनी और ताइवानी साक्ष्य शाकाहारियों से संबंधित हैं, जिनमें से अधिकांश डेयरी और अक्सर अंडे खाते हैं। ताइवान में, दो बौद्ध त्ज़ु ची कोहोर्ट्स (कुल 13,352 प्रतिभागी) में शाकाहारियों के बीच स्ट्रोक का जोखिम कम पाया गया: पहले कोहोर्ट में, इस्केमिक स्ट्रोक के लिए जोखिम अनुपात 0.26 (95% CI 0.08 से 0.88) था; दूसरे में, समग्र स्ट्रोक 0.52 (0.33 से 0.82), इस्केमिक स्ट्रोक 0.41 (0.19 से 0.88), और रक्तस्रावी स्ट्रोक 0.34 (0.12 से 1.00) था [58]। प्रतिभागी एक बौद्ध फाउंडेशन के सदस्य थे, जो अपनी विशिष्ट स्वस्थ-उपयोगकर्ता प्रोफ़ाइल वाली आबादी थी, और एक खोजपूर्ण विश्लेषण ने सुझाव दिया कि विटामिन बी12 के सेवन ने इस संबंध को संशोधित किया [58]। रक्तस्रावी स्ट्रोक का परिणाम EPIC-Oxford के परिणाम के विपरीत है [41], एक अनुस्मारक है कि स्ट्रोक के उपप्रकार अलग-अलग आबादी में अलग तरह से व्यवहार करते हैं।
एक में क्रॉस-सेक्शनल अध्ययन ज़ियामेन से, 169 स्वस्थ चीनी लैक्टो-शाकाहारी पुरुषों में निम्न रक्तचाप, LDL-C, ApoB, ट्राइग्लिसराइड्स और फास्टिंग ग्लूकोज, और पतली कैरोटिड इन्टीमा-मीडिया मोटाई, 126 सर्वाहारी पुरुषों की तुलना में [59]। यह इस पर टियर 4 साक्ष्य है प्रतिस्थापक मार्कर डेयरी खाने वाले शाकाहारियों में।
हांगकांग के आंकड़े एक चेतावनी जोड़ते हैं। हांगकांग के लगभग 80% वेगनों में विटामिन B12 की कमी की सूचना मिली थी, जो शायद ही कभी फोर्टिफाइड खाद्य पदार्थों या सप्लीमेंट्स का उपयोग करते थे; B12-कमी वाले शाकाहारी समूहों ने खराब धमनी एंडोथेलियल फ़ंक्शन और मोटी कैरोटिड दीवारें दिखाईं, और B12 सप्लीमेंटेशन ने हांगकांग के वेगनों में इन संवहनी उपायों में सुधार किया [60]। इसलिए सप्लीमेंट रहित वेगन आहार उन संवहनी लाभों को कम कर सकता है जो इसे प्रदान करने चाहिए, जो धारा 15 में पोषक तत्व मार्गदर्शन को पुष्ट करता है।
10. एसेल्स्टीन के अध्ययनों का पुनर्मूल्यांकन (टियर 4)
10.1 1985 क्लीवलैंड क्लिनिक कोहोर्ट
तीन रिपोर्टें इस कोहोर्ट का वर्णन करती हैं, और उनके विभाजक अलग-अलग हैं। पूर्ण 1995 की रिपोर्ट में 1985 और 1988 के बीच नामांकित गंभीर, एंजियोग्राफिक रूप से प्रलेखित कोरोनरी रोग वाले 22 रोगियों (21 पुरुष, 1 महिला) का वर्णन किया गया है; जिन 11 प्रतिभागियों के परिणाम रिपोर्ट किए गए हैं, उन सभी को ट्रिपल-वेसल रोग था और वे गैर-मधुमेह, गैर-हाइपरटेंसिव और धूम्रपान न करने वाले थे [42]। आहार ने वसा से ऊर्जा का 10% से भी कम हिस्सा प्राप्त किया और मलाई रहित दूध और गैर-वसा वाले दही को छोड़कर तेल, मांस, मछली, मुर्गे और डेयरी को बाहर रखा। प्रत्येक प्रतिभागी को व्यक्तिगत कोलेस्ट्रॉल कम करने वाली दवा भी मिली, जिसमें अक्सर दैनिक 40-60 मिलीग्राम लोवास्टेटिन के साथ दिन में दो बार 4 ग्राम कोलेस्टायरामाइन शामिल था; विश्राम और ध्यान प्रशिक्षण की पेशकश की गई थी लेकिन हफ्तों में ही छोड़ दी गई, और व्यायाम निर्धारित नहीं किया गया था [42]। इमेजिंग वाले 11 प्रतिभागियों में, औसत कुल कोलेस्ट्रॉल बेसलाइन पर 246 mg/dL से गिरकर उपचार के दौरान 132.4 mg/dL हो गया, जिसमें औसत LDL-C 71.6 mg/dL और HDL-C 36.3 mg/dL था [42].
उन 11 प्रतिभागियों में 20% से अधिक स्टेनोसिस वाले 38 घावों में से, तीन जिनका उपचार एंजियोप्लास्टी द्वारा किया गया और बाईपास ग्राफ्ट के समीपस्थ चार देशी-वाहिका घावों को पहले से ही बाहर रखा गया था—बाद वाले इसलिए क्योंकि, जैसा कि लेखकों ने नोट किया है, ऐसे घावों के बढ़ने की उम्मीद थी, और वे बढ़े—और फॉलो-अप में छह और का मिलान नहीं किया जा सका, जिससे 25 बचे [42]। दो तकनीशियन जिन्हें एंजियोग्राम क्रम के बारे में जानकारी नहीं थी, उन्होंने फिल्मों को पढ़ा। व्यास स्टेनोसिस प्रतिशत के आधार पर, 25 में से 11 घाव कम हुए और 14 स्थिर रहे, औसत स्टेनोसिस 53.4% से गिरकर 46.2% हो गया (अनुमानित कमी 7 प्रतिशत अंक; 95% CI 3.3 से 10.7), और 11 में से 8 प्रतिभागियों को प्रतिगामी (regressing) के रूप में वर्गीकृत किया गया। न्यूनतम ल्युमेन व्यास, जो कम संदर्भ-निर्भर माप है, उसके आधार पर 6 घाव कम हुए, 14 स्थिर रहे, और 5 बढ़े, और औसत वृद्धि 0.08 मिमी थी (95% CI −0.06 से 0.22; महत्वपूर्ण नहीं) [42].
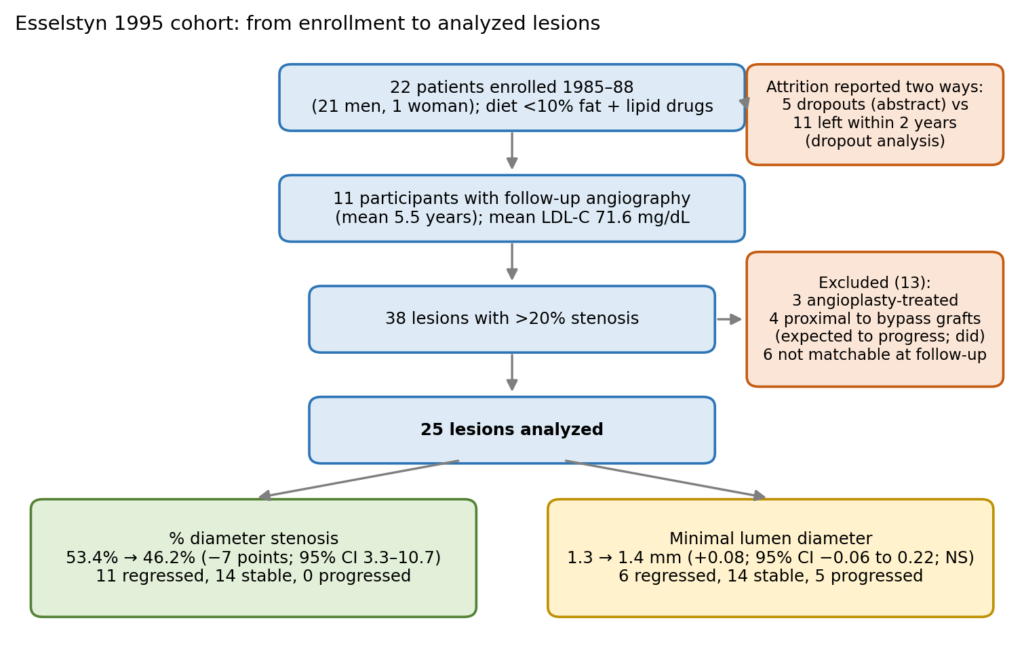
चित्र 11. एसेल्स्टीन 1995 कोहोर्ट: नामांकन, एट्रिशन, घावों का चयन, और रिपोर्ट की गई दो विधियों द्वारा एंजियोग्राफिक परिणाम। स्रोत: एसेल्स्टीन 1995 (पूर्ण पाठ)।
वही पेपर दो तरह से एट्रिशन की रिपोर्ट करता है। इसका सारांश बताता है कि 22 में से 5 प्रतिभागी दो साल के भीतर बाहर हो गए और 17 ने आहार बनाए रखा; इसका ड्रॉपआउट विश्लेषण बताता है कि 11 दो साल के भीतर चले गए (तीन चले गए, चार को कार्य संघर्ष था, तीन आहार नहीं रख सके, और एक ने चुना बायपास सर्जरी) [42]। पिछले आहार को फिर से शुरू करने वाले पांच ड्रॉपआउट्स ने 10 की सूचना दी हृदय संबंधी घटनाएं। इमेजिंग वाले 11 प्रतिभागियों ने नामांकन से आठ साल पहले 37 कार्डियोवैस्कुलर घटनाओं का अनुभव किया था। फॉलो-अप के दौरान किसी को भी नया रोधगलन (infarction) नहीं हुआ, हालांकि अध्ययन के दौरान दो को कोरोनरी प्रक्रियाओं की आवश्यकता हुई (एक में रिपीट एंजियोप्लास्टी, दूसरे में बाईपास सर्जरी) और जिस मरीज की बाईपास सर्जरी हुई थी, जिसकी इजेक्शन अंश 20% से कम थी, बाद में अतालता से उसकी मृत्यु हो गई [42].
1999 के अपडेट में समूह का वर्णन 24 रोगियों (23 पुरुष, 1 महिला) के रूप में किया गया है। छह गैर-अनुपालन करने वाले रोगियों को 12–18 महीनों के भीतर छोड़ दिया गया और वे मानक देखभाल में लौट आए; 18 ने पांच वर्षों तक पालन किया, और उनमें से 11 की पांच साल की एंजियोग्राफी हुई, जिसमें प्रतिशत स्टेनोसिस के आधार पर सभी 11 में ठहराव और 8 (73%) में प्रतिगमन दिखाई दिया। पांच वर्षों में औसत कोलेस्ट्रॉल 237 से गिरकर 137 mg/dL हो गया और 12 वर्षों में 145 mg/dL था। 18 अनुपालन करने वाले रोगियों के बारे में बताया गया कि नामांकन से पहले आठ वर्षों में उन्हें 49 कोरोनरी घटनाएं हुई थीं और फॉलो-अप के दौरान कोई नहीं, जबकि छोड़े गए छह रोगियों को 1998 तक 13 नई घटनाएं हुई थीं [5]। “कोई कोरोनरी घटना नहीं” रिपोर्ट के स्वयं के घटना वर्गीकरण को दर्शाता है: उसी समूह में पांच साल की एंजियोग्राफी के बाद बिना रोधगलन के एक वेंट्रिकुलर-अरिथमिक मृत्यु शामिल थी [42]। 2014 की रिपोर्ट एक और सारांश देती है, जिसमें कहा गया है कि 22 में से 17 रोगी अनुपालन करने वाले थे और यह कि उलटफेर 12 में से 4 में एंजियोग्राफिक रूप से पुष्टि की गई थी [4]। बेसलाइन कोलेस्ट्रॉल (246 बनाम 237 mg/dL), समूह का आकार (22 बनाम 24), और पूर्व-घटना गणना (1995 की चर्चा में 11 रोगियों में 37 घटनाएं बनाम 1999 में 18 रोगियों में 49) रिपोर्टों में भिन्न हैं। दो अलग-अलग 73% आंकड़े प्रसारित होते हैं: प्रतिशत स्टेनोसिस द्वारा प्रतिगमन वाले इमेज किए गए 11 रोगियों में से 8, और 1995 में अभी भी आहार का पालन कर रहे 22 मूल रोगियों में से 16 [5, 42].
नामांकन के बाद की घटनाओं की तुलना पिछले आठ वर्षों की घटनाओं से करना माध्य की ओर प्रतिगमन (रिग्रेशन टू द मीन) के प्रति संवेदनशील है, क्योंकि रोगी आमतौर पर घटनाओं के समूह के बाद ऐसे कार्यक्रमों में प्रवेश करते हैं। इस व्यवस्था में आहार को दवाओं के साथ जोड़ा गया था, इसलिए आहार के स्वतंत्र योगदान का अनुमान नहीं लगाया जा सकता है।
10.2 198 रोगियों का 2014 का समूह
डिजाइन और नामांकन। हृदय रोग वाले लगातार दो सौ स्व-संदर्भित स्वयंसेवकों को परामर्श दिया गया; दो फॉलो-अप में खो गए, जिससे 198 शेष रह गए (91% पुरुष; औसत आयु 62.9 वर्ष; औसत फॉलो-अप 44.2 ± 24.1 महीने)। 195 में कोरोनरी बीमारी का दस्तावेजीकरण किया गया था, 180 में एंजियोग्राफी या सीटी एंजियोग्राफी द्वारा; 44 को पहले मायोकार्डियल इन्फार्क्शन हुआ था। सभी धूम्रपान न करने वाले थे; 161 को हाइपरलिपिडिमिया, 60 को उच्च रक्तचाप और 23 को मधुमेह था। हस्तक्षेप एक एकल पांच घंटे का सेमिनार था जिसके बाद टेलीफोन या ईमेल द्वारा फॉलो-अप किया गया, और रोगियों ने अपनी सामान्य कार्डियक दवाएं जारी रखीं, जिन्हें रिकॉर्ड नहीं किया गया था। व्यायाम को प्रोत्साहित किया गया लेकिन आवश्यक नहीं था [4].
अनुपालन और डेटा संग्रह। जिन रोगियों ने सभी मांस, मछली और डेयरी, और जानबूझकर किसी भी अतिरिक्त तेल से परहेज किया, उन्हें अनुपालन करने वाले के रूप में वर्गीकृत किया गया। डेटा 2011–2012 में टेलीफोन द्वारा एकत्र किया गया था, जो मर चुके थे उनके रिश्तेदारों से। कोई लिपिड मान रिपोर्ट नहीं किया गया था [4].
परिणाम, हर के साथ। 177 अनुपालन करने वाले रोगियों में से, 112 ने बेसलाइन पर एनजाइना की सूचना दी, जिनमें से 104 (टेक्स्ट में 93%; तालिका 105, 94% देती है) में सुधार हुआ। रेडियोग्राफिक या स्ट्रेस टेस्टिंग द्वारा 177 में से 39 (22%) में “रिवर्सल” का दस्तावेजीकरण किया गया था। 177 में से अठारह (10%) को बदतर के रूप में वर्गीकृत किया गया: जांचकर्ताओं ने इनमें से नौ घटनाओं को आहार से असंबंधित माना (जिसमें उनके डॉक्टरों द्वारा राजी किए गए लक्षणविहीन रोगियों में दो कोरोनरी बाईपास ऑपरेशन शामिल थे, स्टेंट थ्रोम्बोसिस क्लोपिडोग्रेल बंद होने के बाद, और वारफेरिन से इनकार करने के बाद एक स्ट्रोक) और चार को बीमारी की प्रगति के रूप में (एक स्ट्रोक, दो बाईपास ऑपरेशन, एक रेस्टेंटिंग)। पांच गैर-कार्डियक मौतें हुईं और कोई कार्डियक मौत नहीं हुई। सुर्ख़ियों वाली 0.6% घटना दर केवल स्ट्रोक को प्रगति-संबंधित प्रमुख घटना के रूप में गिनती है; उसी लेख में एक पूरक तालिका इसके बजाय अनुपालन करने वाले रोगियों के लिए 2.2% घटना दर सूचीबद्ध करती है [4]। 21 गैर-अनुपालन करने वाले रोगियों में से, 13 (62%) को कम से कम एक घटना हुई: दो अचानक हृदय मृत्यु, एक हृदय प्रत्यारोपण, दो इस्केमिक स्ट्रोक, चार स्टेंटिंग प्रक्रियाएं, तीन बाईपास ऑपरेशन और एक एंडार्टेरेक्टॉमी [4].
विरोधाभास कारण-संबंधी क्यों नहीं है। समूहों को यादृच्छिक नहीं किया गया था; प्रतिभागियों ने स्वयं उस कार्यक्रम को चुना जिसे उन्होंने चाहा था; अनुपालन स्व-रिपोर्ट किया गया था और तथ्य के बाद वर्गीकृत किया गया था; जांचकर्ताओं ने टेलीफोन द्वारा घटनाओं का पता लगाया और उनका फैसला किया और निर्णय लिया कि कौन सी आहार-संबंधित थीं; इमेजिंग प्रोटोकॉल-संचालित के बजाय नैदानिक रूप से संचालित थी; दवा के उपयोग को रिकॉर्ड नहीं किया गया था; और गैर-अनुपालन समूह की सात घटनाएं थीं पुनर्संवहन procedures, which depend on symptoms and physician decisions. Adherent and nonadherent patients also differed at baseline, for example 93% versus 76% men [4]. The crude 62% versus 0.6% contrast can be divided, but the quotient is not a valid causal relative risk or इलाज के लिए आवश्यक संख्या: the groups were not randomized, and the event definitions applied to them are not comparable. Participants enrolled after 2007 received a copy of the senior author’s book as part of the program [4].
10.3 What Esselstyn’s work can and cannot carry
Esselstyn’s program deserves prominence for three reasons. It is the most intensive real-world expression of the whole-food lever: no oil, no animal foods in the 2014 cohort, no processed foods, and abundant leafy greens. It shows that some motivated patients with severe disease can sustain such a diet for years, with 16 of 22 original patients still following it in 1995 [42] and 89% self-reported adherence in the 2014 cohort [4]. And it generated specific, testable hypotheses—leafy-green nitrate and nitric oxide, endothelial protection, oil exclusion—that Section 5 evaluates against independent evidence.
What it cannot carry is causal weight for the beyond-ApoB claim or for the superiority claim. The 1995 cohort combined diet with cholestyramine and lovastatin and achieved mean LDL-C of 71.6 mg/dL, a level at which concomitant drug therapy is a plausible explanation for part of the angiographic result, though the uncontrolled design cannot establish that drugs alone account for it or that this LDL-C guarantees arrest of progression [42]; only 11 patients were imaged, 13 of 38 lesions were excluded, and the paper reports attrition two ways (Figure 11). The 2014 cohort had no lipid data, self-reported adherence, and investigator-adjudicated outcomes (Section 10.2). Considered alongside randomized lipid trials, two observations nonetheless become more plausible: sustained very low LDL-C achieved with a whole-food diet plus drugs is compatible with arrest of angiographic disease in most imaged patients [20, 21], and angina improved in most patients, consistent with the randomized Ornish and Heidelberg findings [6, 61, 62]. Unresolved are the diet’s independent contribution, whether excluding oil, nuts, and avocado adds anything, the true event rate in a representative population, and how the results would compare with an equally supported Mediterranean or higher-fat whole-food program.
11. Randomized and Controlled Lifestyle Trials (mainly Tier 2)
11.1 The Lifestyle Heart Trial
डिज़ाइन। Of 193 potentially eligible patients, 93 remained eligible after angiography and were randomized by an invitational design (53 experimental, 40 control); 28 and 20 respectively agreed to participate, giving the 48 trial participants. Thirty-five (20 experimental, 15 control) completed five-year मात्रात्मक कोरोनरी एंजियोग्राफी, read blind to allocation [6]. The intervention combined a 10%-fat whole-foods vegetarian diet with moderate एरोबिक व्यायाम, stress management (87 minutes per day at one year, 49 at five years), smoking cessation, and group psychosocial support. Experimental patients took no lipid-lowering drugs; 9 of 15 control patients (60%) started them between years one and five [6].
Angiography: which report, which cohort. Two reports describe this trial and are often quoted interchangeably, which makes them look inconsistent. The 1990 Lancet report covers the first year in all 48 participants, analyzing 195 lesions: mean percent diameter stenosis fell from 40.0% (SD 16.9) to 37.8% (16.5) in the experimental group and rose from 42.7% (15.5) to 46.1% (18.5) in controls; among lesions more than 50% stenosed the change was 61.1% to 55.8% versus 61.7% to 64.4%; and 18 of 22 experimental patients (82%) changed in the direction of regression [63]. The 1998 JAMA report covers the 35 participants who completed five-year angiography, a subset with slightly different baseline values (38.92% experimental, 42.50% control), and reports changes rather than start-and-end values [6]. The figures below are from the 1998 report unless stated; a 1990 value and a 1998 value should never be compared directly, because they describe different patients.
Percent diameter stenosis changed by −3.07 percentage points (95% CI −5.91 to −0.24) in the experimental group and +11.77 points (95% CI 3.40 to 20.14) in controls at five years (P = 0.001), corresponding to a 7.9% relative improvement and a 27.7% relative worsening [6]. These are changes in lumen narrowing, not a 7.9% removal of plaque volume. Minimum lumen diameter was unchanged in the experimental group (+0.001 mm) and fell 0.34 mm in controls (P = 0.05). The reference (“normal”) segment diameter decreased slightly in the experimental group (−0.13 mm) and widened slightly in controls (P = 0.01) [6]. Because percent stenosis is calculated relative to that reference segment, a stable minimum diameter with a narrowing reference segment will register as reduced stenosis; the authors interpreted the reference-segment change as flow streamlining [6]. Within the experimental group, stenosis change tracked adherence tertiles (−6.81, −3.02, and −0.37 points; n = 6, 7, and 6), an observational analysis within a randomized trial [6].
Lipids. LDL-C fell from 143.8 to 86.6 mg/dL (−40%) at one year and was 115.4 mg/dL (−20%) at five years; triglycerides rose (227.8 to 258.2 mg/dL at one year), HDL-C fell (40.1 to 34.8 mg/dL at five years), and ApoB returned to baseline by year five as described in Section 5.6. LDL-C did not differ between groups at five years, largely because most controls took lipid-lowering drugs [6].
Events and angina. Over five years there were 25 cardiac events among 28 experimental patients and 45 among 20 controls (rate ratio for controls 2.47; 95% CI 1.48 to 4.20) [6]. These are recurrent-event counts, not numbers of patients with an event, and they are dominated by procedures and hospitalizations: myocardial infarction 2 versus 4, angioplasty 8 versus 14, bypass surgery 2 versus 5, cardiac hospitalizations (which include those events) 23 versus 44, and deaths 2 versus 1 [6]. Hard events were too few for comparison. Reported angina frequency fell 91% within the experimental group at one year (with a 42% fall in duration and a 28% fall in severity) and 72% at five years [6, 63]; between-group differences were no longer significant at five years because the most symptomatic controls had undergone revascularization [6]. The control-group change in angina frequency at one year is given as a 186% increase in the 1998 paper but as 165% in the 1990 report [6, 63]; the difference has not been reconciled and both are stated here.
Attrition and bias. Seven patients lacked one-year angiograms, and four in each group lacked five-year angiograms; fourteen lesions were unavailable overall—four in the experimental group and ten in controls, including four control lesions excluded after revascularization—which would bias toward the null [6]. A correction notice added an omitted author [6].
व्याख्या. यादृच्छिकीकरण (Randomization) supports a causal reading of the comparison between the whole lifestyle package and usual care of the time, though post-allocation consent and attrition limit that confidence. The inability to isolate diet is a limitation of attribution, not an absence of randomization. Participation was selected after allocation: 93 patients were randomized by the invitational design and 48 then consented. Similar consent proportions in the two arms do not eliminate selection bias, and small size and attrition are further limitations.
11.2 PET perfusion (Gould 1995)
Gould and colleagues reported that, in the same 20 experimental and 15 control patients, the size and severity of perfusion abnormalities on rest–dipyridamole PET improved with the lifestyle intervention and worsened in controls, who received mainly antianginal therapy [61]. This is a functional outcome in the same patients, not an independent replication, and it is distinct from ventricular function and angiographic anatomy. Freeman and colleagues’ summary of a “400% increase in मायोकार्डियल पर्फ़्यूजन” could not be traced to this report and should not be reused [2].
11.3 The Multicenter Lifestyle Demonstration Project
This nonrandomized project followed 333 patients eligible for revascularization: 194 who chose the lifestyle program and 139 controls who underwent revascularization. At three years, 150 of 194 experimental patients (77%) had avoided revascularization, and rates of myocardial infarction, stroke, and death per patient-year were similar between groups [64]. The 77% describes procedure avoidance among self-selected patients; it is not a randomized 77% reduction in procedures or events. Freeman and colleagues’ statement that demonstration projects produced a “greater than 90% reduction in angina within weeks” cites this project and a 24-site program evaluation [2, 65]; the specific study, outcome, and time point could not be traced, and the verified one-year 91% figure from the Lifestyle Heart Trial cannot support a claim about weeks.
11.4 Lower-fat but non-vegan angiographic trials
In STARS, 90 men with coronary disease were randomized to usual care, a lipid-lowering diet (27% of energy from fat), or the diet plus cholestyramine, with angiography at 39 months. Mean absolute width of coronary segments narrowed 0.201 mm with usual care, was unchanged with diet alone (+0.003 mm), and widened 0.103 mm with diet plus cholestyramine; the proportion with progression was 46%, 15%, and 12% respectively [66]. In the Heidelberg trial, 113 men were randomized to usual care or intensive exercise plus a low-fat, low-cholesterol diet without lipid drugs; at one year, lesions progressed in 23% versus 48% and regressed in 32% versus 17% [62]. At six years, 90 patients were re-evaluated, and lipid differences between groups were no longer significant [67]. In डिस्को-सीटी, 92 patients with nonobstructive disease on optimal medical therapy were randomized to added intensive dietary counseling with a DASH-type pattern and activity checks, or to medical therapy alone; after about 67 weeks, noncalcified plaque volume fell more with the intervention (−51.3 versus −21.3 mm³; P = 0.045), although the change in total एथेरोमा volume did not differ significantly between groups [68]. At about six years, most of the weight lost during the intervention had been regained in both groups, and one गंभीर प्रतिकूल हृदय संबंधी घटना had occurred in the DASH group versus four (including one fatal myocardial infarction) among controls—too few events for inference [69]. These trials show that omnivorous or lower-fat regimens well above 10–15% fat also slowed progression.
12. The Strongest Competing Evidence (Tiers 1–2)
12.1 DASH and DASH-Sodium
In controlled feeding of 459 adults for eight weeks, the DASH combination diet lowered systolic and diastolic pressure by 5.5 and 3.0 mm Hg more than a typical American control diet, and by 11.4 and 5.5 mm Hg in the 133 participants with hypertension [11]. Combining DASH with low sodium lowered systolic pressure by 7.1 mm Hg in normotensive participants and 11.5 mm Hg in those with stage 1 hypertension, compared with the high-sodium control diet [16]. These benefits were achieved with low-fat dairy in the diet.
12.2 PREDIMED
The 2013 PREDIMED report was retracted because of randomization irregularities and republished in 2018 with reanalysis. Among 7,447 adults at high cardiovascular risk followed for a median of 4.8 years, major cardiovascular events occurred in 96 of 2,543 participants (3.8%) assigned a Mediterranean diet plus extra-virgin olive oil, 83 of 2,454 (3.4%) assigned a Mediterranean diet plus nuts, and 109 of 2,450 (4.4%) in the control group advised to reduce dietary fat (hazard ratios 0.69, 95% CI 0.53 to 0.91, and 0.72, 95% CI 0.54 to 0.95); results were similar after excluding 1,588 participants with known or suspected protocol departures [12]. The control arm received advice, not a very-low-fat plant-based diet.
12.3 The Lyon Diet Heart Study
In 605 survivors of a first myocardial infarction followed for a mean of 46 months, the Mediterranean-type diet reduced cardiac death plus nonfatal infarction (composite 1: 14 versus 44 events), composite 1 plus अस्थिर एनजाइनास्ट्रोक, हार्ट फेलियर, and embolism (composite 2: 27 versus 90), and composite 2 plus minor events requiring hospitalization (composite 3: 95 versus 180) [70]. The abstract reports adjusted risk ratios ranging from 0.28 to 0.53 across the three composites; the supplementary table of the 2014 Esselstyn article assigns 0.28 (95% CI 0.15 to 0.53) to composite 1 [4, 70]. Summaries of “up to 65%” or “70%” reductions do not match any single endpoint and should be avoided. The comparator was a prudent Western-type diet rather than a healthy active diet [10], and the intervention supplied an alpha-linolenic-acid-rich margarine in place of butter and cream [13]. Lyon shows that a plant-rich but not plant-exclusive diet with substantial unsaturated fat reduced recurrent events.
12.4 CORDIOPREV
CORDIOPREV randomized 1,002 patients with coronary heart disease to a Mediterranean diet (at least 35% fat; 40–60 g/day of extra-virgin olive oil) or a low-fat, high-complex-carbohydrate diet (less than 30% fat, less than 10% saturated fat, lean meat and low-fat dairy permitted), with equally intensive dietitian support and a median seven-year follow-up. Achieved fat was 40.5% of energy in the Mediterranean arm and 32.1% in the low-fat arm. The primary composite occurred in 87 (17.3%) versus 111 (22.2%) patients (unadjusted hazard ratio 0.745; 95% CI 0.563 to 0.986; adjusted models 0.719 to 0.753). Benefit was statistically demonstrable in men (hazard ratio 0.669; 95% CI 0.489 to 0.915), while the estimate in the smaller subgroup of 175 women was inconclusive rather than showing absence of benefit; no single component differed significantly; lipids and glucose did not change differently between diets; and 86.6% took statins at baseline. More low-fat participants abandoned their diet (17.2% versus 9.2%). The trial was funded principally by olive-oil foundations [10].
CORDIOPREV challenges the broad claim that less total fat is always better: within the 30–40% range, among omnivores on statins, the higher-fat Mediterranean diet did better. It does not test a 10–15% fat, animal-free, whole-food diet, which differs from its low-fat arm in fat level, animal-food content, and food processing.
12.5 Direct comparisons of plant-exclusive and Mediterranean diets
No trial has compared these diets on clinical events, and the three risk-factor trials below provide related but distinct comparisons rather than one comparison repeated. In a 16-week crossover trial in 62 overweight adults (52 completers), a low-fat vegan diet reduced body weight by 6.0 kg with no change on a PREDIMED-style Mediterranean diet (treatment effect −6.0 kg; 95% CI −7.5 to −4.5), and lowered LDL-C by 15.3 mg/dL with no significant change on the Mediterranean diet (treatment effect −14.8 mg/dL; 95% CI −23.5 to −6.2), whereas the Mediterranean diet lowered systolic pressure more (treatment effect +6.0 mm Hg favoring Mediterranean; 95% CI 1.0 to 10.9) [23]. लिपिड अनुमान उन 43 प्रतिभागियों को कवर करता है जिनमें लिपिड-कम करने वाली दवा में कोई बदलाव नहीं हुआ है और रक्तचाप अनुमान उन 41 प्रतिभागियों को जिनमें एंटीहाइपरटेंसिव दवा में कोई बदलाव नहीं हुआ है; सभी प्रतिभागियों के विश्लेषण में सिस्टोलिक प्रेशर के लिए एक महत्वपूर्ण कैरीओवर प्रभाव दिखाई दिया, जिनमें वे भी शामिल थे जिनकी दवा बदल गई थी, लेकिन स्थिर-दवा उपसमूह में नहीं [23]. वीगन चरण के अंत में रिपोर्ट किया गया फैट इंटेक ऊर्जा का 17% (95% CI 15 से 19) था, इसलिए परीक्षण में 10–15% फैट वाले आहार के बजाय कम फैट वाले वीगन आहार का परीक्षण किया गया, और रैंडमाइजेशन के बाद एक प्रतिभागी के क्रम असाइनमेंट को बदल दिया गया ताकि एक माँ और बेटी एक ही आहार का पालन करें [23]. यह परीक्षण एक ऐसे संगठन द्वारा आयोजित किया गया था जो पौधे-आधारित आहार का समर्थन करता है। CARDIVEG में, 107 कम जोखिम वाले अधिक वजन वाले वयस्कों में तीन महीने के क्रॉसओवर में, ऊर्जा-प्रतिबंधित लैक्टो-ओवो-शाकाहारी और भूमध्यसागरीय आहारों ने समान वजन और फैट की कमी उत्पन्न की; शाकाहारी आहार पर LDL-C अधिक गिरा, भूमध्यसागरीय आहार पर ट्राइग्लिसराइड्स अधिक गिरा, और शाकाहारी आहार पर विटामिन B12 कम हो गया [71]. EVADE CAD ने समान फैट सेवन (अनुभाग 5.3) पर एक वीगन आहार की तुलना AHA आहार से की [9]. केवल बरनार्ड ने एक वीगन आहार की तुलना भूमध्यसागरीय आहार से की; CARDIVEG ने लैक्टो-ओवो शाकाहारी आहार की तुलना भूमध्यसागरीय आहार से की, और EVADE ने वीगन आहार की तुलना AHA आहार से की। अलग से पढ़ने पर, प्रत्येक ने पाया कि पौधे-आधारित शाखा ने LDL-C को कम से कम उतना ही कम किया, जिसमें भूमध्यसागरीय तुलनित्र रक्तचाप (बरनार्ड) या ट्राइग्लिसराइड्स (CARDIVEG) पर बेहतर था; ये एक ही तुलना की तीन प्रतिकृतियां नहीं हैं।
12.6 कोक्रेन समीक्षा और घटना अंतराल
वीगन आहार की 2021 की कोक्रेन समीक्षा (फरवरी 2020 तक की खोज) में कम से कम 12 सप्ताह के फॉलो-अप वाले 13 रैंडमाइज्ड परीक्षण शामिल थे; किसी ने भी हृदय संबंधी नैदानिक अंतबिंदुओं की सूचना नहीं दी। 63 प्रतिभागियों के केवल एक परीक्षण ने संबोधित किया द्वितीयक रोकथाम दूसरे आहार हस्तक्षेप के विरुद्ध, और लिपिड या रक्तचाप पर कोई स्पष्ट प्रभाव नहीं दिखाया (निम्न- या बहुत-निम्न-निश्चितता प्रमाण) [72]. इसकी सख्त पात्रता—केवल वीगन, न्यूनतम 12 सप्ताह, सक्रिय या न्यूनतम-हस्तक्षेप तुलनित्र—बताती है कि इसके निष्कर्ष कोच और वांग मेटा-विश्लेषणों की तुलना में अधिक सतर्क क्यों हैं, जिन्होंने शाकाहारी आहार और विभिन्न तुलनित्रों को स्वीकार किया था [7, 22]. इस समीक्षा के लिए 10 सितंबर 2026 तक की गई एक अद्यतन खोज में, परिणाम के रूप में हृदय संबंधी घटनाओं के साथ बहुत कम फैट वाले वीगन आहार का कोई प्रकाशित रैंडमाइज्ड परीक्षण नहीं मिला। घटना साक्ष्य की अनुपस्थिति एक अंतराल है, न कि कोई लाभ न होने का प्रमाण। समूहीकृत विश्लेषणों को कोहोर्ट ओवरलैप के लिए जाँचने की भी आवश्यकता है: 1990 की एक वर्षीय और 1998 की पांच वर्षीय लाइफस्टाइल हार्ट ट्रायल रिपोर्ट एक ही रैंडमाइज्ड कोहोर्ट का वर्णन करती हैं, इसलिए एक विश्लेषण जो उन्हें अलग-अलग परीक्षणों के रूप में दर्ज करता है, वह एक कोहोर्ट की दोहरी गणना करता है और सटीकता को बढ़ा-चढ़ाकर दिखाता है।
जहाँ भी उपलब्ध हो, सीधी तुलना का उपयोग किया जाता है। असंबंधित परीक्षणों में प्रभाव के आकार की तुलना करके आहारों को रैंक नहीं किया जाता है, क्योंकि जनसंख्या, पृष्ठभूमि चिकित्सा, अनुपालन और अंतबिंदु भिन्न होते हैं।
चित्र 12 इस खंड में चर्चा किए गए नैदानिक परिणामों के साथ रैंडमाइज्ड परीक्षणों को लाइफस्टाइल हार्ट ट्रायल के आवर्तक-घटना अनुपात के साथ प्रदर्शित करता है।
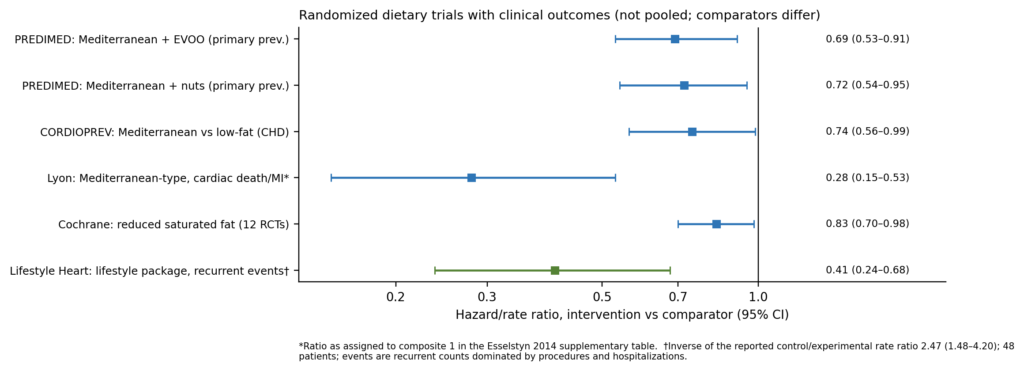
चित्र 12. नैदानिक परिणामों के साथ रैंडमाइज्ड आहार परीक्षण। अनुमान साथ-साथ दिखाए गए हैं, समूहीकृत नहीं; तुलनित्र, जनसंख्या और अंतबिंदु भिन्न हैं। बहुत कम फैट वाले वीगन आहार के किसी भी रैंडमाइज्ड परीक्षण ने नैदानिक घटनाओं की सूचना नहीं दी है।
12.7 तुलनित्र परीक्षणों पर समान मानक लागू करना
इस समीक्षा ने एसेलस्टीन और ओर्निश अध्ययनों की बारीकी से जांच की है, और जो परीक्षण भूमध्यसागरीय आहार के पक्ष में हैं वे भी उसी जांच के पात्र हैं। तालिका 2 प्रत्येक से वही प्रश्न पूछती है। उद्देश्य किसी भी परीक्षण को बेकार करार देना नहीं है बल्कि इस बारे में स्पष्ट होना है कि प्रत्येक किसका समर्थन कर सकता है।
PREDIMED. The 2018 republication documents the main problems itself. Sealed envelopes were used to conceal allocation only during part of the pilot phase; 425 household members were enrolled without randomization and given the same diet as their relative; at one site, 467 participants were assigned by clinic rather than individually; and randomization tables were used inconsistently at another site [12]. The authors reanalyzed the trial with statistical adjustment, and the results were similar when the 1,588 affected participants were excluded (hazard ratios 0.71 and 0.68 in the remaining 5,859) [12]. The control group received a yearly leaflet with low-fat advice until September 2006 and only afterward the same frequency of contact as the Mediterranean groups; its total fat intake changed little, so PREDIMED compared a supplemented Mediterranean diet with a lightly advised usual diet, not with a true low-fat diet [12]. Benefit was also present among participants recruited after control-group contact was increased—hazard ratio 0.49 (95% CI 0.26 to 0.92) versus 0.77 (0.59 to 1.00) before the October 2006 change (P = 0.21 for heterogeneity)—which argues against unequal support as the sole explanation, though a recruitment-period comparison cannot exclude some contribution from it [12]. Study discontinuation was 11.3% in the control group versus 4.9% in the Mediterranean groups. The olive oil and nuts were donated by producers and supplied free, participants knew their assignment, and only the endpoint committee was blinded [12]. The trial was stopped at its fourth interim analysis [12], and trials stopped early for benefit tend to overestimate effect size. Finally, the composite result was driven mainly by stroke (combined hazard ratio 0.58; 95% CI 0.42 to 0.82), whereas myocardial infarction (0.80; 0.53 to 1.21), cardiovascular death (0.80; 0.51 to 1.24), and death from any cause (0.98; 0.77 to 1.24) did not differ significantly; the authors attribute this to limited power [12] (Figure 13).
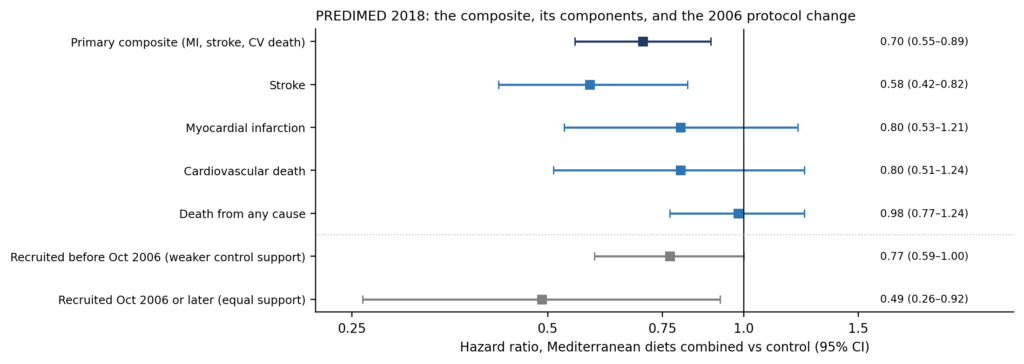
Figure 13. PREDIMED 2018: the composite result and its components (Mediterranean diets combined versus control), and the effect before and after the October 2006 increase in control-group support. Source: Estruch 2018, Table 3 and text.
Lyon Diet Heart Study. Lyon randomized 605 survivors of a first myocardial infarction in a single-blind design and was stopped early for benefit at a mean of 27 months, with follow-up later extended to 46 months [13, 14, 70]. Its comparator was a prudent Western-type diet rather than an intensively supported healthy diet [70]. The large reduction in events occurred while serum lipids, blood pressure, and body mass index remained similar between groups [14]. That is a genuine signal that a dietary pattern can reduce events through pathways other than lipid lowering (Section 5), but it comes from a small, early-stopped trial whose effect size is likely inflated.
CORDIOPREV. CORDIOPREV was a single-center trial funded principally by olive-oil foundations; benefit was statistically demonstrable only in men, with an inconclusive estimate in the smaller female subgroup; no single component of the composite was significant; and its low-fat arm reached 32.1% of energy from fat [10]. It has the strongest design of the three because both arms received equally intensive support, but it tests a moderate-fat omnivorous comparator, not a very-low-fat plant diet.
Problems shared across nutrition science. Several weaknesses apply to almost every study in this review, whichever diet it favors. Diet is usually measured by questionnaire; in Adventist Health Study-2, questionnaire validity correlations against repeated 24-hour recalls were 0.76 for लाल मांस but 0.53 for fish in white participants [53]. Participants in diet trials know what they are eating. Adherence fades, as shown by control-group discontinuation in PREDIMED, diet abandonment in CORDIOPREV, and declining adherence scores in the Lifestyle Heart Trial [6, 10, 12]. तुलनात्मक समूह (Comparators) अक्सर कमजोर होते हैं: PREDIMED का शुरुआती नियंत्रण समूह, ल्योन का विवेकपूर्ण आहार, और लाइफस्टाइल हार्ट ट्रायल की सामान्य देखभाल। परीक्षण अक्सर छोटे होते हैं या जल्दी रोक दिए जाते हैं। और हित हर दिशा में चलते हैं: जैतून के तेल और मेवे के उत्पादकों, कार्यक्रम विकसित करने वालों और वकालत करने वाले संगठनों ने यहाँ चर्चा किए गए अध्ययनों को वित्तपोषित या निर्देशित किया है [4, 10, 12, 23].
आलोचना क्या बदलती है। ये सीमाएं भूमध्यसागरीय (Mediterranean) लाभ के आकार और इस दावे पर कि भूमध्यसागरीय आहार श्रेष्ठ सिद्ध हुआ है, विश्वास को कम करती हैं। वे VLF-WFPB की स्थिति को नहीं बढ़ाती हैं, जिसका नैदानिक घटनाओं के साथ कोई भी रैंडमाइज्ड परीक्षण नहीं है। नैदानिक घटनाओं वाला एक रैंडमाइज्ड परीक्षण, भले ही वह त्रुटिपूर्ण हो, उस कारण संबंधी प्रश्न को संबोधित करता है जिसे एक अनियंत्रित केस सीरीज़ नहीं कर सकती, हालाँकि इसका महत्व अभी भी पक्षपात, सटीकता और यह प्रश्नगत आहार का कितनी सीधे तौर पर परीक्षण करता है, इस पर निर्भर करता है। दोनों पक्षों पर एक ही संदेह लागू करना ही इस समीक्षा के निष्कर्षों पर भरोसा करने की अनुमति देता है।
तालिका 2. बहस के प्रत्येक पक्ष के मुख्य परीक्षणों पर समान प्रश्न लागू करना।
| प्रश्न | PREDIMED | कार्डियोप्रेव | ल्योन डाइट हार्ट | लाइफ़स्टाइल हार्ट ट्रायल | एसेलस्टीन 2014 कोहोर्ट |
| प्रमाण का स्तर | 1 | 1 | 1 | 2 (घटनाओं की कम संख्या) | 4 |
| क्या रैंडमाइज्ड था? | हाँ, 7,447 में से 1,588 को प्रभावित करने वाले विचलनों के साथ; लिफाफे केवल पायलट के हिस्से में उपयोग किए गए [12] | हाँ [10] | हाँ [14] | हाँ, निमंत्रण आधारित; आधे पात्र लोगों ने मना कर दिया [6] | नहीं [4] |
| कौन ब्लाइंडेड (अविज्ञ) था? | केवल एंडपॉइंट कमेटी [12] | एंडपॉइंट (निष्कर्ष) न्यायनिर्णय मास्क्ड (नकाबपोश) के रूप में रिपोर्ट किया गया; प्रतिभागी और आहार विशेषज्ञ ब्लाइंडेड नहीं थे, जैसा कि किसी भी आहार परीक्षण में होता है | सिंगल-ब्लाइंड डिज़ाइन [14] | सिंगल-ब्लाइंड डिज़ाइन [14] | कोई नहीं; जांचकर्ताओं ने घटनाओं का निर्णय लिया [4] |
| तुलनात्मक समूह | वसा कम करने की सलाह; 2006 तक वार्षिक लीफलेट, फिर समान संपर्क; कुल वसा में थोड़ा बदलाव आया [12] | समान रूप से समर्थित कम वसा वाला आहार; 32.1% वसा प्राप्त की गई [10] | विवेकपूर्ण पश्चिमी-प्रकार का आहार [70] | सामान्य देखभाल; 60% ने लिपिड दवाएं शुरू कीं [6] | अनुपालन न करने वाले स्वयंसेवक [4] |
| जल्दी रोक दिया गया? | हाँ, चौथे अंतरिम विश्लेषण पर [12] | औसत 7-वर्षीय फॉलो-अप [10] | हाँ, 27 महीने पर; बाद में 46 महीने तक बढ़ाया गया [13, 14] | हाँ, 27 महीने पर; बाद में 46 महीने तक बढ़ाया गया [13, 14] | लागू नहीं |
| परिणाम का मुख्य कारण क्या था | स्ट्रोक 0.58; एमआई (MI) 0.80 और सीवी (CV) मृत्यु 0.80 महत्वपूर्ण नहीं [12] | पुरुषों में लाभ प्रमाणित करने योग्य; 175 महिलाओं में अनुमान अनिर्णायक; कोई भी एकल घटक महत्वपूर्ण नहीं [10] | समान सीरम लिपिड, बीपी और बीएमआई के साथ बड़ी गिरावट [14] | प्रक्रियाएं और अस्पताल में भर्ती (आवर्तक गणना) [6] | गैर-अनुपालन समूह में पुनर्वैस्कुलराइजेशन [4] |
| रुचि के क्षेत्र | उत्पादकों द्वारा दान किया गया जैतून का तेल और मेवे [12] | मुख्य रूप से जैतून के तेल के फाउंडेशन [10] | यहाँ मूल्यांकन नहीं किया गया | यहाँ मूल्यांकन नहीं किया गया | कार्यक्रम विकसित करने वाला; प्रतिभागियों को पुस्तक दी गई [4] |
| VLF-WFPB बनाम परीक्षण किया गया आहार | सप्लीमेंटेड भूमध्यसागरीय बनाम हल्की सलाह वाला सामान्य आहार | भूमध्यसागरीय 40.5% वसा बनाम सर्वाहारी कम वसा 32.1% | ALA-समृद्ध भूमध्यसागरीय-प्रकार | ALA-समृद्ध मार्जरीन और भूमध्यसागरीय-प्रकार की सलाह | तेल-मुक्त, पशु-मुक्त, कोई मेवे या एवोकैडो नहीं |
13. क्या बहुत कम कुल वसा अपने आप में बेहतर है?
वसा को अलग करें। संतृप्त वसा LDL-C को बढ़ाती है और इसकी कमी घटनाओं को कम करती है [26]; औद्योगिक ट्रांस फैट से बचना चाहिए [73]; असंतृप्त वसा LDL-C को कम करती है जब वे संतृप्त वसा की जगह लेती है और भूमध्यसागरीय परीक्षणों में घटनाओं में कमी के साथ जुड़ी होती है [10, 12]। 'कुल वसा' इन विपरीत प्रभावों को एक साथ मिला देती है।
वसा की जगह क्या आता है, यह मायने रखता है। VLF-WFPB में प्रतिस्थापन साबुत अनाज, फलियां, सब्जियां और फल हैं; अन्य कम वसा वाले आहारों में यह परिष्कृत स्टार्च या चीनी हो सकती है। किसी भी परीक्षण ने नैदानिक परिणामों पर पौधे-अनन्य (plant-exclusive) आहार के भीतर इन प्रतिस्थापनों की तुलना नहीं की है।
संपूर्ण-खाद्य पादप आहार के भीतर एकमात्र प्रत्यक्ष परीक्षण। एक रैंडमाइज्ड क्रॉसओवर परीक्षण में, कम से कम 5% अनुमानित हृदय जोखिम वाले 40 वयस्कों ने चार सप्ताह के लिए प्रतिदिन लगभग चार बड़े चम्मच या एक चम्मच से कम एक्स्ट्रा-वर्जिन जैतून के तेल के साथ संपूर्ण-खाद्य पादप-आधारित वीगन आहार का पालन किया; वसा ने क्रमशः 48% और 32% ऊर्जा की आपूर्ति की। दोनों चरणों ने बेसलाइन से LDL-C, कुल कोलेस्ट्रॉल, ApoB, HDL-C, ग्लूकोज और hs-CRP को कम किया। एक अनुक्रमिक अंतःक्रिया थी: उच्च से निम्न तेल की ओर जाने से LDL-C में 12.7 mg/dL (P = 0.04) की कमी आई, और निम्न से उच्च की ओर जाने से इसमें 15.8 mg/dL (P = 0.02) की वृद्धि हुई; पहली अवधि में, LDL-C 25.5 बनाम 16.7 mg/dL (P = 0.162) गिर गया [8]। किसी भी चरण में वसा 10-15% के करीब नहीं पहुंची, परीक्षण छोटा था, और कैरीओवर क्रॉसओवर विश्लेषण को जटिल बनाता है। यह बताता है कि तेल की बड़ी मात्रा जोड़ने से LDL-C की कमी कुंद हो सकती है; यह यह नहीं दर्शाता है कि 10-15% वसा लगभग 30% पर नट्स- और बीज-आधारित वनस्पति आहार से बेहतर है।
मेवे (नट्स), बीज और जैतून का तेल। एक्स्ट्रा-वर्जिन जैतून के तेल से भरपूर या नट्स के साथ पूरक भूमध्यसागरीय आहार ने तुलनात्मक समूहों के मुकाबले घटनाओं को कम किया [10, 12]। कोई भी परीक्षण यह नहीं दर्शाता है कि अन्यथा कम संतृप्त वसा वाले आहार से नट्स, बीज या जैतून के तेल को बाहर करने से नैदानिक परिणामों में सुधार होता है। एक बार के उच्च वसा वाले भोजन के बाद प्रवाह-मध्यस्थता फैलाव (flow-mediated dilation) की तीव्र हानि [30], जिसे तेल बहिष्कार के समर्थन में उद्धृत किया गया है [4], यह स्थापित नहीं कर सकता कि तेल एथेरोस्क्लेरोसिस का कारण बनते हैं।
ट्राइग्लिसराइड्स, एचडीएल, और ApoB–LDL-C मतभेद. बहुत कम वसा वाले, उच्च कार्बोहाइड्रेट वाले आहार ट्राइग्लिसराइड्स बढ़ा सकते हैं और HDL-C कम कर सकते हैं, जैसा कि लाइफस्टाइल हार्ट ट्रायल के पहले वर्ष में हुआ था [6]; कुल मिलाकर पादप-आधारित परीक्षणों में, ट्राइग्लिसराइड्स में कोई बदलाव नहीं हुआ [22], और CARDIVEG में भूमध्यसागरीय आहार ने शाकाहारी आहार की तुलना में ट्राइग्लिसराइड्स को अधिक कम किया [71जब ट्राइग्लिसराइड युक्त लिपोप्रोटीन बढ़ते हैं, तो LDL-C कम आँका जा सकता है एथेरोजेनिक कण संख्या। लाइफस्टाइल हार्ट ट्रायल इसे स्पष्ट करता है: पांच वर्षों में LDL-C आधार रेखा से 20% कम था जबकि ApoB नहीं था [6]। भविष्य के परीक्षणों में सीधे ApoB मापा जाना चाहिए।
आरोपण (Attribution)। जहाँ VLF-WFPB LDL-C पर तुलनात्मक आहार से बेहतर प्रदर्शन करता है, वहां यह लाभ वसा की मात्रा, वसा की गुणवत्ता (लगभग कोई संतृप्त वसा नहीं), भोजन की गुणवत्ता (फाइबर, पादप प्रोटीन), वजन घटाने या अनुपालन को प्रतिबिंबित कर सकता है। उदाहरण के लिए, बरनार्ड क्रॉसओवर ने वीगन आहार पर अधिक LDL-C कटौती और अधिक वजन घटाने दोनों का उत्पादन किया [23]। कोई भी उपलब्ध परीक्षण इन योगदानों को अलग नहीं करता है। वर्तमान साक्ष्यों के आधार पर, बहुत कम कुल वसा एक स्वतंत्र आवश्यकता के रूप में स्थापित नहीं है; संपूर्ण-खाद्य आहार के भीतर बहुत कम संतृप्त वसा वह घटक है जिसे सबसे मजबूत कारण समर्थन (causal support) प्राप्त है।
14. रोकथाम, उपचार और प्रत्यावर्तन
14.1 वे परिणाम जिन्हें आपस में मिलाया नहीं जाना चाहिए
हृदय संबंधी घटनाएं कम होना, धीमी प्रगति, पट्टिका स्थिरीकरण, सुधरा हुआ एनजाइना या छिड़काव (perfusion), कम एंजियोग्राफिक स्टेनोसिस, और मात्रात्मक रूप से मापा गया प्लाक वॉल्यूम का प्रतिगमन (regression) अलग-अलग परिणाम हैं। प्राथमिक और माध्यमिक रोकथाम भी अलग-अलग सेटिंग्स हैं।
14.2 इमेजिंग क्या दिखा सकती है और क्या नहीं
मात्रात्मक कोरोनरी एंजियोग्राफी लुमेन को मापती है, प्लाक को नहीं। प्रतिशत स्टेनोसिस संदर्भ खंड (reference segment) और वासमोटर टोनपर निर्भर करता है, और बाहरी (सकारात्मक) रिमॉडलिंग एक सामान्य लुमेन के पीछे पर्याप्त प्लाक छिपा सकती है। मायोकार्डियल परफ्यूजन और स्ट्रेस टेस्टिंग कार्य (function) को मापते हैं; जैसा कि हीडलबर्ग के जांचकर्ताओं ने उल्लेख किया है, सुधार शारीरिक प्रतिगमन के बिना भी हो सकता है [62]. इंट्रावैस्कुलर अल्ट्रासाउंड और कोरोनरी सीटी एंजियोग्राफी प्लाक की मात्रा और संरचना को मापते हैं; सीटी इसके अतिरिक्त गैर-कैल्सीकृत और कम-एटेन्युएशन प्लाकको चित्रित करता है। जब प्लाक स्थिर हो जाता है तो कोरोनरी कैल्शियम स्कोर बढ़ सकता है, क्योंकि स्टैटिन फाइब्रोफैटी और नेक्रोटिक-कोर घटकों को कम करते हुए कैल्सीकृत और रेशेदार प्लाक को बढ़ाते हैं, इसलिए केवल कैल्शियम-स्कोर परिवर्तन न तो सफलता का संकेत देता है और न ही विफलता का [74]। एंजियोग्राफी द्वारा संकुचन का पता लगाने से पहले प्लाक काफी बढ़ सकता है [74]; इसके विपरीत, एक स्पष्ट रूप से व्यापक लुमेन छोटे प्लाक के बजाय वासोमोटर टोन में बदलाव को प्रतिबिंबित कर सकता है। डॉसन और उनके सहयोगियों द्वारा संक्षेपित एक मेटा-प्रतिगमन में, प्रत्येक 1% की कमी एथेरोमा आयतन प्रतिशत प्रमुख प्रतिकूल घटनाओं की लगभग 20% कम संभावना से जुड़ी थी, लेकिन इसका कोई प्रत्यक्ष प्रमाण नहीं है कि प्रतिगमन स्वयं घटनाओं को कम करता है [74]। तालिका 3 सारांशित करती है कि प्रत्येक निष्कर्ष क्या स्थापित कर सकता है और क्या नहीं।
तालिका 3. लक्षण और इमेजिंग निष्कर्ष क्या स्थापित कर सकते हैं और क्या नहीं।
| निष्कर्ष | यह क्या स्थापित करता है | यह क्या स्थापित नहीं करता है |
| कम एनजाइना; बेहतर तनाव परीक्षण या PET परफ्यूजन [6, 61, 62] | बेहतर लक्षण या मायोकार्डियल रक्त आपूर्ति | प्लाक की मापी गई कमी |
| कम एंजियोग्राफिक प्रतिशत स्टेनोसिस | एक संदर्भ खंड के सापेक्ष कम संकुचित लुमेन | हटाए गए प्लाक का प्रतिशत; संदर्भ-खंड परिवर्तन परिणाम को बदल सकते हैं [6] |
| न्यूनतम लुमेन व्यास में परिवर्तन | घाव पर पूर्ण लुमेन परिवर्तन | प्लाक वॉल्यूम, जिसे बहिःमुखी पुनर्रूपण छिपा सकता है [74] |
| CCTA या IVUS प्लाक वॉल्यूम या संरचना परिवर्तन | Change in the measured plaque compartment, within acquisition and segmentation limits | Eradication of disease or a guaranteed event reduction |
| Rising coronary calcium score | A higher अगाटस्टन स्कोर, which reflects calcified area, density, or both | Greater total plaque burden or treatment failure; statins increase कैल्सीफाइड प्लाक while reducing fibrofatty and नेक्रोटिक कोर [74] |
14.3 The primate and pharmacologic benchmarks
Two bodies of evidence set the standard against which dietary regression claims should be read. Neither is a dietary trial in humans, and both are cited here as benchmarks rather than as support for any diet.
Controlled primate experiments (Tier 5). In rhesus monkeys given an atherogenic diet and then switched to a regression diet, atheromatous कोरोनरी धमनियां lost lipid [75], while arterial fibrous proteins behaved differently from the lipid compartment [76]. The achieved cholesterol level mattered: in animals whose plasma cholesterol was held near 300 mg/dL there was little or no increase in lumen area attributable to regression of intimal plaque, whereas at about 200 mg/dL a considerable share of the lumen gain was attributable to plaque regression, and the contribution depended on both plaque size and time [77]. This is the closest thing in the literature to a controlled demonstration that lowering atherogenic lipoproteins by dietary means depletes the lipid-rich compartment while denser tissue persists. It is also animal evidence, in a different species, with induced rather than spontaneous disease, and it cannot establish what a human diet achieves.
Pharmacologic imaging (Tiers 1–2). में GLAGOV, 968 statin-treated patients with angiographic coronary disease were randomized to monthly इवोलोक्यूमैब या प्लैसबो for 76 weeks, and 846 had evaluable serial intravascular ultrasound. Time-weighted LDL-C was 36.6 mg/dL versus 93.0 mg/dL, percent atheroma volume changed by −0.95% versus +0.05% (difference −1.0 percentage point; P < 0.001), and plaque regression occurred in 64.3% versus 47.3% of patients [78]. Notably, the trial’s virtual-histology substudy did not show a difference in dense calcium volume [78], so GLAGOV demonstrates volumetric regression rather than a compositional shift; trials designed to measure plaque composition are outside the scope of this review and no compositional figures are quoted. Two comparisons follow. No dietary trial has produced coronary regression of this magnitude under this level of rigor, and no dietary trial identified here used serial intravascular ultrasound at all, which is the modality that measures atheroma volume most precisely.
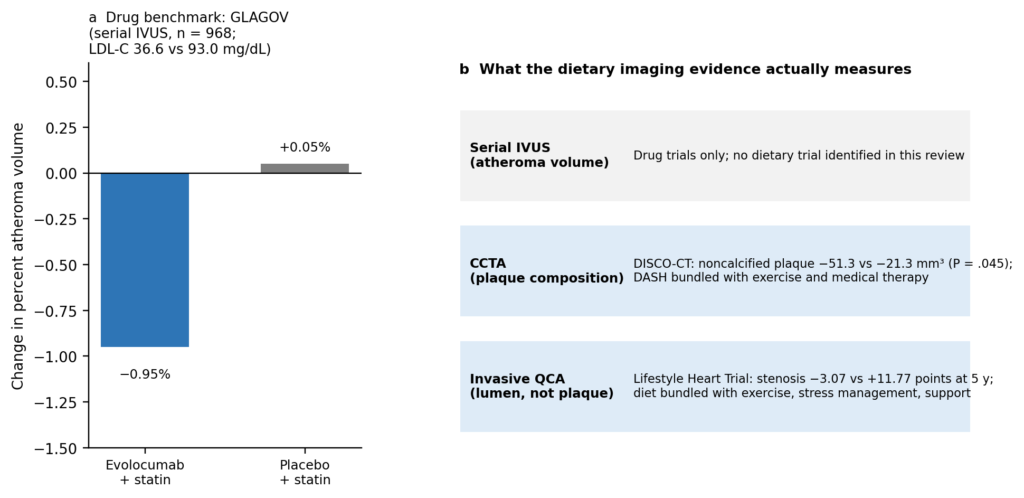
Figure 14. Benchmarks for coronary plaque change. Pharmacologic regression measured by serial intravascular ultrasound (GLAGOV) alongside the dietary imaging evidence available in this review, which uses different modalities and cannot be placed on the same axis. No dietary trial identified here used serial intravascular ultrasound. Sources: Nicholls 2016; Henzel 2021; Ornish 1998.
Exercise as a co-lever. Physical activity belongs alongside the three dietary levers rather than inside them. The populations with the least coronary calcium are also the most active: Tsimane men average six to seven hours and women four to six hours of physical activity a day [35]. In the two randomized imaging trials that showed benefit, exercise was part of the intervention rather than a controlled covariate—the Lifestyle Heart Trial bundled aerobic exercise with the diet [6], and DISCO-CT bundled activity counseling with DASH [68]—which is why neither can apportion credit. No quantitative estimate of the ApoB reduction attributable to aerobic training is given here; the point stands qualitatively that diet, activity, and lipid-lowering therapy act on overlapping pathways and are complementary rather than competing.
14.4 What the evidence supports in each domain
प्राथमिक रोकथाम. Evidence consists of cohort associations [40], population data (Sections 6–8), and randomized lipid trials [22]. No randomized event trial of VLF-WFPB exists.
Secondary prevention (treatment). The Lifestyle Heart Trial reduced angina and cardiac procedures and hospitalizations for a package that included a very-low-fat vegetarian diet [6]. Randomized event reductions with diet alone in secondary prevention come from Mediterranean-type trials [10, 70].
Slowed progression and partial regression. Intensive lifestyle programs incorporating very-low-fat vegetarian diets have demonstrated modest एंजियोग्राफिक प्रतिगमन in selected patients; the independent contribution of diet, and of total-fat restriction, remains uncertain [6, 42]. Lower-fat but non-vegan diets also slowed angiographic progression [62, 66], and a DASH-type program added to medical therapy reduced noncalcified plaque on CT [68]. Partial regression appears most likely when large, sustained reductions in atherogenic lipoproteins are achieved, often with drugs, and more regression was seen at five years than at one year in the Ornish program [6]. Regression does not mean eradication of disease or zero future risk.
The Dawson review. As summarized in the ACC’s published key points, the 2022 JACC state-of-the-art review judged the demonstrated effect of diet, exercise, and smoking cessation on coronary plaque volume and composition to be limited [74]. Claims sometimes attributed to that review in secondary summaries, including the assertion that most statin-treated dietary arms progressed, are not used here. Limited diet-only regression evidence does not mean dietary treatment has little clinical value: stabilizing plaque, improving perfusion, and preventing progression can be clinically meaningful even when anatomic change is small, although existing diet trials do not establish the mechanism of any event reduction.
15. Feasibility, Adequacy, and Safety
Adherence. Reported adherence has been high in selected volunteers: 89% by self-report in the 2014 Esselstyn cohort [4], and 94% versus 70% for vegan versus AHA diets at eight weeks in EVADE CAD, whose participants represented 14% of those meeting initial criteria [9]. In the Lifestyle Heart Trial, half of eligible invited patients declined, and the adherence score fell from 1.29 at one year to 1.06 at five years [6]. Over seven years in CORDIOPREV, more patients abandoned a conventional low-fat diet than a Mediterranean diet [10].
Nutrients. Vitamin B12 supplementation is essential; median intake in the EVADE vegan arm fell to 1.2 µg/day, and B12 levels fell during the vegetarian phase of CARDIVEG [9, 71]. Zinc and omega-3 fatty acid intakes were also lower on the vegan diet in EVADE [9]. Calcium, vitamin D, iodine, iron, and long-chain omega-3 status require planning, and fortified foods or supplements are appropriate where intake is inadequate [79]; “whole food” should not become a reason to reject them. Unfortified terrestrial plant foods supply alpha-linolenic acid but little or no preformed EPA or DHA, which algae-derived supplements and fortified products can provide within a vegan diet [79]; Esselstyn’s protocol added flaxseed as an alpha-linolenic acid source [4]. Aggressive fat restriction should not displace necessary energy or essential fats.
Energy and protein. Median protein intake on the EVADE vegan diet was 50 g/day (12.9% of energy) [9]. Energy-unrestricted vegetarian diets reduced energy intake by about 276 kcal/day relative to usual diets [7], and in the 2014 Esselstyn cohort the 135 patients with weight data lost an average of 18.7 lb [4]. Low energy density is an asset for weight loss but a potential hazard for older adults with poor appetite or सारकोपेनिया and for physically active people with high requirements; protein and energy adequacy should be planned individually.
Quality of life. In EVADE CAD, quality-of-life scores improved similarly on both diets [9].
Diet and drugs. Pooled randomized evidence puts the dietary ApoB reduction at about 14% [22]. A matched estimate of ApoB lowering under intensive statin or PCSK9 therapy is not presented here, so no numerical comparison is drawn; the clinical point stands on other grounds. In established ASCVD, diet is a complement to guideline-directed therapy, not a substitute for it, and indicated therapy should not be withheld or stopped in order to follow any diet.
This review is educational. Dietary change should be made alongside, not instead of, prescribed cardiovascular therapy, and medication adjustments belong with the treating physician.
16. Clinical Positioning
The 2023 AHA/ACC guideline for chronic coronary disease recommends a diet emphasizing vegetables, fruits, legumes, nuts, whole grains, and lean protein to reduce cardiovascular events (class 1, level B-R), and states that reducing saturated fat to less than 6% of energy and replacing it with monounsaturated and polyunsaturated fat, complex carbohydrate, and fiber can be beneficial (class 2a) [73]. Its nutrition figure lists मोनोअनसैचुरेटेड वसा such as olive oil and polyunsaturated fat among foods to choose [73]. 2026 ACC/AHA बहु-सोसाइटी डिस्लिपिडेमिया दिशा-निर्देश, which replaces the 2018 cholesterol guideline, describes preferred dietary patterns as predominantly plant-based—Mediterranean, DASH, and vegan or vegetarian [27].
The AHA’s 2026 dietary guidance lists features of a heart-healthy pattern that include choosing healthy sources of protein, choosing sources of unsaturated fat in place of saturated fat, choosing minimally processed foods, minimizing अतिरिक्त शर्करा, and reducing sodium [25].
These guidelines support plant-rich dietary treatment and accommodate a vegan pattern. They do not endorse a uniquely effective very-low-fat vegan reversal protocol, and they explicitly include nuts and unsaturated oils. A professional recommendation of a pattern is not evidence that every component or exclusion within a particular diet is necessary.
17. The Decisive Next Study
Primary design. A randomized, parallel-group trial with blinded endpoint assessment in medically treated adults with CT-documented coronary atherosclerosis, deliberately recruiting women, older adults, and patients outside specialist lifestyle programs. Arms: (A) VLF-WFPB, 10–15% of energy from fat, no animal foods, no added oil, limited nuts and avocado; (B) a higher-unsaturated-fat whole-food plant-based diet, about 30–40% fat from nuts, seeds, avocado, and extra-virgin olive oil, no animal foods; (C) a Mediterranean (PREDIMED/CORDIOPREV-style) or DASH diet. A versus B tests total-fat restriction within an animal-free diet; B versus C approximates the effect of animal-food exclusion, although replacement foods will differ. All arms receive identical contact time, cooking instruction, food support, and exercise advice.
Mechanistic substudy. Because the three-arm design cannot fully separate animal-food exclusion from total fat, a controlled-feeding 2 × 2 factorial substudy—animal-free versus limited specified animal foods, crossed with about 10–15% versus 30–35% of energy from fat, with saturated fat, sodium, fiber, protein, and energy matched as closely as feasible—would isolate each factor at stable weight. A third factor—whole versus ultra-processed plant foods at matched macronutrients—would test the processing lever directly, following the design of the inpatient processing trial [19]. Unavoidable differences in replacement foods must be measured and reported.
Two estimands. The pragmatic effect of assigning an ad libitum pattern, including its effects on weight and adherence, differs from the biological effect of dietary composition at stable weight. Adjusting away weight loss in the primary analysis would remove part of the assigned diet’s effect; the feeding substudy addresses composition.
Medication. प्रत्येक शाखा एक ही नैदानिक उपचार एल्गोरिदम का पालन करती है, और आहार संबंधी अंतर को बढ़ाने के लिए संकेतित उपचार को कभी नहीं रोका जाता है। चूँकि लिपिड लक्ष्यों की ओर अनुमापन (titration) आंशिक रूप से ApoB में आहार संबंधी अंतरों की भरपाई करेगा, इसलिए आवश्यक लिपिड-कम करने वाली थेरेपी की तीव्रता एक पूर्व-निर्दिष्ट माध्यमिक परिणाम बन जाती है, और ApoB का विश्लेषण दवा की तीव्रता के साथ किया जाता है। मुख्य परीक्षण एक सामान्य उपचार एल्गोरिदम के तहत तुलनात्मक प्रभावशीलता का अनुमान लगाता है; यह अपने आप में संचयी ApoB एक्सपोज़र को बराबर नहीं करता है, और ApoB से स्वतंत्र मार्गों के लिए किसी भी अवशिष्ट लाभ का श्रेय देने के लिए मध्यस्थों के बार-बार अनुदैर्ध्य माप और स्पष्ट कारण धारणाओं की आवश्यकता होगी।
परिणाम। चरण 1 प्राथमिक परिणाम: कोरोनरी सीटी एंजियोग्राफी पर प्रतिशत एथेरोमा आयतन (या गैर-कैल्सीफाइड प्लाक वॉल्यूम) में 24 महीने का परिवर्तन, जिसे लक्षणों के बजाय प्रोटोकॉल शेड्यूल पर एक ब्लाइंडेड कोर प्रयोगशाला में पढ़ा जाता है। माध्यमिक परिणाम: समय-औसत ApoB, गैर-HDL कोलेस्ट्रॉल, ट्राइग्लिसराइड्स, एम्बुलेटरी ब्लड प्रेशर, वजन और शरीर की संरचना, HbA1c, hs-CRP, TMAO, PET मायोकार्डियल रक्त प्रवाह, एनजाइना (सिएटल एनजाइना प्रश्नावली), कार्यप्रणाली, जीवन की गुणवत्ता, लागत, प्रतिधारण, और पोषक तत्व स्थिति (B12, आयरन, विटामिन D, आयोडीन, ओमेगा-3 इंडेक्स)। अनुपालन को वस्तुनिष्ठ रूप से (प्लाज्मा फैटी-एसिड प्रोफाइल, कैरोटीनॉयड, मूत्र नाइट्रोजन और पोटेशियम) और साथ ही बार-बार आहार रिकॉर्ड द्वारा मापा जाता है। चरण 2: हृदय संबंधी मृत्यु, मायोकार्डियल इन्फार्क्शन और इस्केमिक स्ट्रोक के एक कठिन समग्र के साथ एक घटना परीक्षण; प्रक्रियाओं का निर्णय गोपनीय तरीके से किया जाता है और अलग से रिपोर्ट किया जाता है, जिसमें पहले-घटना-तक-समय और आवर्ती-घटना दोनों विश्लेषण शामिल हैं।
विश्लेषण। मिसिंग डेटा और दवाओं के परिवर्तनों के पूर्व-निर्दिष्ट प्रबंधन के साथ इंटेंशन-टू-ट्रीट प्राथमिक विश्लेषण; कॉम्प्लायर-औसत कारण प्रभाव (complier-average causal effect) और प्रति-प्रोटोकॉल विश्लेषण माध्यमिक के रूप में; अनुपालन विश्लेषण अनुपालन करने वालों को नए यादृच्छिक समूहों के रूप में नहीं मानते हैं; ApoB, वजन और रक्तचाप का उपयोग करने वाले मध्यस्थता विश्लेषणों को खोजपूर्ण (exploratory) के रूप में लेबल किया गया है।
दृष्टांत नमूना आकार (धारणाएं बताई गई हैं)। चरण 1: प्रतिशत एथेरोमा आयतन में 24 महीने के परिवर्तन के लिए 3.0 प्रतिशत अंकों के मानक विचलन को मानते हुए, 1.0 अंक का न्यूनतम महत्वपूर्ण अंतर-शाखा अंतर, दो प्राथमिक युग्मवार तुलनाएं (A बनाम B; B बनाम C) प्रत्येक का परीक्षण द्वि-पक्षीय α = 0.025, और 90% पावर पर किया गया, प्रति शाखा लगभग 224 प्रतिभागियों की आवश्यकता है, या 20% एट्रिशन (attrition) की अनुमति देते हुए 280 प्रति शाखा (कुल 840) की आवश्यकता है। चरण 2: द्वि-पक्षीय α = 0.025 और 80% पावर पर प्रत्येक युग्मवार तुलना में 0.80 के जोखिम अनुपात का पता लगाने के लिए प्रति तुलना लगभग 764 घटनाओं की आवश्यकता होती है; संदर्भ शाखा में 15% के अनुमानित चार-वर्षीय प्रथम-घटना जोखिम के साथ, प्रति शाखा लगभग 2,800 प्रतिभागियों (कुल लगभग 8,400) की आवश्यकता होगी। ये आंकड़े दृष्टांत मात्र हैं; एक प्रोटोकॉल को अनुपालन, क्रॉसओवर और दवा अनुमापन के लिए धारणाओं की आवश्यकता होगी। वे यह भी बताते हैं कि घटना के साक्ष्य अभी तक मौजूद क्यों नहीं हैं।
18. डोमेन द्वारा निष्कर्ष
तालिका 4 (मुख्य पाठ के बाद) साक्ष्य आधार का सारांश प्रस्तुत करती है, और तालिका 5 दिखाती है कि क्या प्रत्येक प्रस्तावित लाभ तुलनित्र आहारों (comparator diets) के साथ साझा किया गया है या इसमें अतिरिक्त लाभ के साक्ष्य हैं।
लेबल: स्थापित—कथित परिणाम पर सुसंगत यादृच्छिक साक्ष्य। समर्थित लेकिन अनिश्चित—यादृच्छिक साक्ष्य जो छोटा, बहु-घटक, या मध्यवर्ती परिणामों पर है, या सुसंगत अवलोकनात्मक साक्ष्य। जैविक रूप से प्रशंसनीय—पर्याप्त परिणाम साक्ष्य के बिना यांत्रिक या अप्रत्यक्ष समर्थन। असमर्थित—कोई पर्याप्त साक्ष्य नहीं, या विरुद्ध साक्ष्य।
रोकथाम। यह कि सर्वाहारी आहार की तुलना में पौधे-आधारित आहार LDL-C और ApoB को कम करते हैं, वह है स्थापित (पूल किया हुआ LDL-C अंतर लगभग 11.6 mg/dL) [22]। यह कि VLF-WFPB एक विशिष्ट पश्चिमी आहार के सापेक्ष ASCVD घटना को कम करता है, वह हैसमर्थित लेकिन अनिश्चित40: कोहोर्ट एसोसिएशन (शाकाहारी IHD सापेक्ष जोखिम 0.79) लिपिड-मध्यस्थता वाली प्रशंसनीयता के अनुरूप हैं, लेकिन कोई यादृच्छिक घटना साक्ष्य नहीं है [ ]। यह कि यह मेडिटेरेनियन या DASH आहार की तुलना में ASCVD को बेहतर तरीके से रोकता है, वह असमर्थित है. कोरोनरी और स्ट्रोक के परिणामों की रिपोर्ट अलग-अलग की जानी चाहिए: EPIC-Oxford में, शाकाहारियों में IHD कम था लेकिन रक्तस्रावी और कुल स्ट्रोक दर अधिक थी [41].
उपचार। यह कि एक गहन जीवनशैली पैकेज, जिसमें बहुत कम वसा वाला शाकाहारी आहार शामिल है, सामान्य देखभाल की तुलना में एनजाइना और कार्डियक प्रक्रियाओं या अस्पताल में भर्ती होने को कम करता है, वह यह कि VLF-WFPB एक विशिष्ट पश्चिमी आहार के सापेक्ष ASCVD घटना को कम करता है, वह है, 1986–1992 के एक छोटे रैंडमाइज्ड ट्रायल पर आधारित है [6]. यह कि केवल आहार ही स्थापित बीमारी में घटनाओं को कम करता है, वह जैविक रूप से प्रशंसनीय है. यह कि यह भूमध्यसागरीय आहार की तुलना में घटनाओं को अधिक कम करता है, जिसके पास रैंडमाइज्ड माध्यमिक-निवारण साक्ष्य हैं [10, 70], वह ]। यह कि यह मेडिटेरेनियन या DASH आहार की तुलना में ASCVD को बेहतर तरीके से रोकता है, वह असमर्थित है.
रिग्रेशन (प्रतिगमन)। यह कि बहुत कम वसा वाले शाकाहारी आहार को शामिल करने वाले गहन जीवनशैली कार्यक्रम चयनित रोगियों में मामूली एंजियोग्राफिक रिग्रेशन पैदा करते हैं, वह यह कि VLF-WFPB एक विशिष्ट पश्चिमी आहार के सापेक्ष ASCVD घटना को कम करता है, वह है [6]. यह कि केवल VLF-WFPB इंट्रावास्कुलर अल्ट्रासाउंड या CT द्वारा मात्रात्मक प्लाक-वॉल्यूम रिग्रेशन पैदा करता है, वह ]। यह कि यह मेडिटेरेनियन या DASH आहार की तुलना में ASCVD को बेहतर तरीके से रोकता है, वह असमर्थित है क्योंकि इसका परीक्षण नहीं किया गया है। यह कि रिग्रेशन भविष्य के जोखिम को समाप्त कर देता है, वह ]। यह कि यह मेडिटेरेनियन या DASH आहार की तुलना में ASCVD को बेहतर तरीके से रोकता है, वह असमर्थित है.
श्रेष्ठता और आवश्यकता। यह कि बहुत कम कुल वसा स्वतंत्र रूप से आवश्यक है, वह ]। यह कि यह मेडिटेरेनियन या DASH आहार की तुलना में ASCVD को बेहतर तरीके से रोकता है, वह असमर्थित है; पादप आहारों के भीतर साक्ष्य अल्पकालिक और मिश्रित हैं, और रैंडमाइज्ड घटना साक्ष्य सर्वाहारी आहारों में असंतृप्त वसा को शामिल करने के पक्ष में हैं [8, 10, 12]. यह कि पशु खाद्य पदार्थों का पूर्ण बहिष्कार कम-संतृप्त-वसा वाले आहार से परे लाभ जोड़ता है, वह जैविक रूप से प्रशंसनीय है (शून्य आहार कोलेस्ट्रॉल, बहुत कम संतृप्त वसा, संभवतः कम TMAO) लेकिन परिणामों पर अपरीक्षित है।
होल फूड्स और प्रसंस्करण। यह कि न्यूनतम प्रसंस्कृत पादप खाद्य पदार्थ कम हृदय जोखिम से जुड़े हैं, और अति-प्रसंस्कृत पादप खाद्य पदार्थ उच्च जोखिम से, वह यह कि VLF-WFPB एक विशिष्ट पश्चिमी आहार के सापेक्ष ASCVD घटना को कम करता है, वह है: बड़े कोहोर्ट सुसंगत हैं, और ऊर्जा सेवन के लिए रैंडमाइज्ड साक्ष्य मौजूद हैं लेकिन एथेरोस्क्लेरोसिस के लिए नहीं [17–19]. यह कि आहार की गुणवत्ता और प्रसंस्करण पशु-खाद्य बहिष्कार जितना ही मायने रखते हैं, वह अपरीक्षित है: किसी भी अध्ययन ने सीधे इन दो पहलुओं की तुलना नहीं की है।
ApoB से परे। यह कि होल-फूड पादप आहार ApoB से परे मार्गों के माध्यम से धमनियों की रक्षा करते हैं, वह जैविक रूप से प्रशंसनीय है, आंशिक अवलोकन संबंधी समर्थन के साथ: तंत्र जानवरों में प्रदर्शित किए गए हैं, पत्तेदार-हरे नाइट्रेट हाइपरकोलेस्ट्रोलेमिया के समायोजन के बाद एक बड़े कोहोर्ट में कम जोखिम से जुड़े हैं, और लाइफस्टाइल हार्ट ट्रायल ने ApoB के बेसलाइन पर लौटने के बाद भी निरंतर एंजियोग्राफिक सुधार दिखाया [6, 28, 29]. यह स्थापित नहीं है, क्योंकि किसी भी ट्रायल ने मैच्ड ApoB पर आहार की तुलना नहीं की है।
अन्य शाकाहारियों की तुलना में वीगन। यह कि वीगन लोगों में लैक्टो-ओवो या पेस्को-शाकाहारियों की तुलना में हृदय रोग का जोखिम कम होता है, वह ]। यह कि यह मेडिटेरेनियन या DASH आहार की तुलना में ASCVD को बेहतर तरीके से रोकता है, वह असमर्थित है: एडवेंटिस्ट, ब्रिटिश और एकत्रित कोहोर्ट्स में, वीगन अनुमान दिशा में अनुकूल हैं लेकिन अनिर्णायक हैं, और कोई भी कोहोर्ट शाकाहारी उपसमूहों के बीच सीधा तुलना प्रदान नहीं करता है [41, 53, 54, 56]. एडवेंटिस्ट वीगन पुरुषों के बीच का संकेत परिकल्पना-उत्पन्न करने वाला है।
दवा थेरेपी के सापेक्ष भूमिका। स्थापित ASCVD में निर्दिष्ट लिपिड-लोअरिंग या अन्य दिशा-निर्देश-निर्देशित थेरेपी के स्थान पर आहार का उपयोग करना ]। यह कि यह मेडिटेरेनियन या DASH आहार की तुलना में ASCVD को बेहतर तरीके से रोकता है, वह असमर्थित है: यहाँ समीक्षा किए गए किसी भी ट्रायल ने निर्दिष्ट थेरेपी को बंद करने का परीक्षण नहीं किया, और लाभ दिखाने वाला प्रत्येक हस्तक्षेप ट्रायल इसके साथ ही दिया गया था [10, 12, 22].
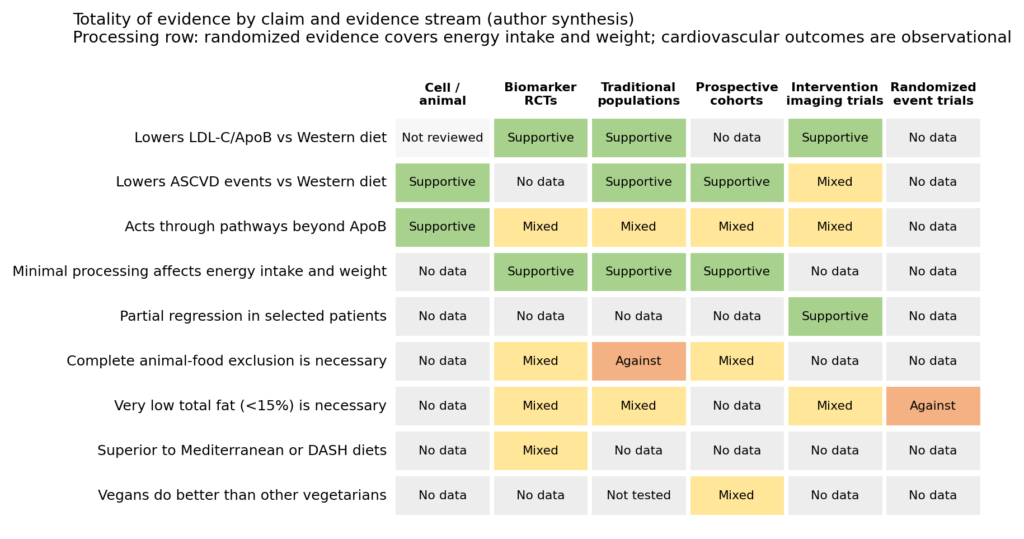
चित्र 15. दावे और साक्ष्य स्ट्रीम द्वारा साक्ष्य की समग्रता। अनुभाग 3–17 का लेखक संश्लेषण; “against” उन साक्ष्यों को चिह्नित करता है जो बताए गए दावे का खंडन करते हैं।
19. सबसे मजबूत दावा जिसे साक्ष्य आज पुष्ट करते हैं
एक संपूर्ण-खाद्य, पौधे-आधारित आहार सामान्य पश्चिमी आहार की तुलना में एथेरोजेनिक लिपोप्रोटीन को विश्वसनीय रूप से कम करता है, और जीवन भर कम पशु-खाद्य सेवन वाले समुदायों में कोलेस्ट्रॉल और दर्ज कोरोनरी मृत्यु दर कम पाई गई है। बहुत कम वसा वाले शाकाहारी आहारों पर आधारित गहन जीवनशैली कार्यक्रमों ने चुनिंदा रोगियों के छोटे अध्ययनों में सामान्य देखभाल की तुलना में मामूली एंजियोग्राफिक प्रतिगमन, बेहतर मायोकार्डियल छिड़काव, कम एनजाइना और कम कार्डियक प्रक्रियाओं का परिणाम दिया है। कुल मिलाकर, यह साक्ष्य इसे विश्वसनीय बनाता है कि ऐसा आहार कोरोनरी एथेरोस्क्लेरोसिस को रोकने, धीमा करने और कुछ रोगियों में आंशिक रूप से ठीक करने में मदद कर सकता है, मुख्य रूप से कम संचयी ApoB जोखिम के माध्यम से। इसका लाभ सबसे अधिक आहार के संपूर्ण-खाद्य स्वरूप—न्यूनतम प्रसंस्करण, उच्च फाइबर और प्रचुर सब्जियों—से जुड़ा है, न कि केवल पशु खाद्य पदार्थों के बहिष्कार से, और प्रशंसनीय लेकिन अप्रमाणित साक्ष्य बताते हैं कि इसका एक हिस्सा ApoB से परे अन्य मार्गों के माध्यम से कार्य करता है। साक्ष्य यह स्थापित नहीं करते हैं कि सभी पशु खाद्य पदार्थों और लगभग सभी अतिरिक्त वसा को बाहर करना, अच्छी तरह से लागू किए गए भूमध्यसागरीय, DASH, या उच्च-असंतृप्त-वसा वाले पौधे-आधारित आहार की तुलना में बेहतर सुरक्षा प्रदान करता है।
एक मजबूत दावे के लिए समान सहायता तीव्रता और समान चिकित्सा उपचार पर उन आहारों की एक यादृच्छिक तुलना की आवश्यकता होगी, जिसमें पूरे समय ApoB मापा गया हो, ब्लाइंडेड मात्रात्मक प्लैक इमेजिंग की गई हो, और अंततः नैदानिक परिणामों का निर्णय लिया गया हो। जब तक ऐसा डेटा मौजूद नहीं होता, VLF-WFPB को विशिष्ट रूप से प्रभावी रिवर्सल प्रोटोकॉल के बजाय, हृदय-स्वस्थ आहारों के परिवार के भीतर एक साक्ष्य-समर्थित विकल्प के रूप में प्रस्तुत करना सबसे अच्छा है, जो अपनी LDL-C-कम करने की क्षमता के लिए उल्लेखनीय है।
तालिका 4. साक्ष्य तालिका। टियर: 1 = नैदानिक परिणामों के साथ यादृच्छिक परीक्षण; 2 = मध्यवर्ती परिणामों का यादृच्छिक परीक्षण; 3 = संभावित समूह; 4 = जनसंख्या तुलना, क्रॉस-सेक्शनल अध्ययन, या केस सीरीज़ (अनुभाग 1.2)। CI = 95% विश्वास अंतराल।
| अध्ययन | टियर | डिज़ाइन, n, अवधि | आहार जैसा प्रदान किया गया / प्राप्त किया गया | पृष्ठभूमि चिकित्सा | परिणाम और प्रभाव अनुमान | प्रमुख सीमाएँ |
| कोच 2023 मेटा-विश्लेषण [22] | 2 | 30 RCTs; 6 परीक्षणों से ApoB | शाकाहारी या वीगन बनाम सर्वाहारी; वसा की मात्रा अलग-अलग थी | विविध; कुछ लिपिड दवाओं पर | TC −0.34 mmol/ L (CI −0.44 से −0.23); LDL-C −0.30 mmol/ L (−0.40 से −0.19) ≈ −11.6 mg/ dL; ApoB −12.92 mg/ dL (−22.63 से −3.20; I² = 71.7%, 6 परीक्षण); TG में कोई अंतर नहीं | विषम आहार और तुलनाकर्ता; छोटे परीक्षण; कोई परिणाम नहीं; वसा के स्तर को अलग नहीं करता है; ApoB अनुमान 6 परीक्षणों पर आधारित है जिनमें काफी विषमता है जिनकी स्वतंत्रता की पुष्टि यहाँ नहीं की जा सकी |
| वांग 2023 मेटा-विश्लेषण [7] | 2 | 20 RCTs, 1,878; औसत 25.4 सप्ताह | शाकाहारी, जिसमें ऑर्निश और कम वसा वाला वीगन शामिल है | अधिकांश कार्डियोमेटाबोलिक दवाओं पर | LDL-C −6.6 mg/ dL (−10.1 से −3.1); HbA1c −0.24% (−0.40 से −0.07); वजन −3.4 kg (−4.9 से −2.0); SBP −0.1 mm Hg (−2.8 से 2.6) | सक्रिय तुलनाकर्ताओं के बनाम LDL-C NS; अधिकांश में पूर्वाग्रह का उच्च जोखिम; मुख्य बिंदु पाठ परिणामों से भिन्न हैं |
| रीस 2021 कोक्रेन [72] | 2 | 13 RCTs; ≥12 सप्ताह; फरवरी 2020 तक की खोज | केवल वीगन | — | किसी भी परीक्षण ने नैदानिक परिणामों की सूचना नहीं दी; एक माध्यमिक-रोकथाम परीक्षण (n = 63): कोई स्पष्ट लिपिड या बीपी प्रभाव नहीं | छोटे परीक्षण; पुरानी खोज; कम निश्चितता |
| डाइबविक 2023 कोहोर्ट मेटा-विश्लेषण [40] | 3 | 13 कोहोर्ट्स, 844,175 | शाकाहारी या वीगन बनाम गैर-शाकाहारी (स्व-रिपोर्ट) | — | IHD RR 0.79 (0.71–0.88; 8 कोहोर्ट्स); CVD 0.85 (0.79–0.92); स्ट्रोक 0.90 (0.77–1.05); वीगन IHD 0.82 (0.68–1.00; 6) | शेष भ्रमित करने वाले कारक (Residual confounding) (E-मान 1.86); ~1/ 5 BMI-मध्यस्थता; शुरुआती फॉलो-अप को छोड़कर कमजोर; वसा का मूल्यांकन नहीं किया गया |
| EPIC-ऑक्सफोर्ड [41] | 3 | कोहोर्ट; 48,188; 18.1 वर्ष | वीगन सहित शाकाहारी बनाम मांस खाने वाले; वीगन ~28% वसा | — | IHD HR 0.78 (0.70–0.87), जोखिम-कारक समायोजन के बाद 0.90 (0.81–1.00); कुल स्ट्रोक HR 1.20 (1.02–1.40), ज्यादातर रक्तस्रावी; वीगन IHD 0.82 (0.64–1.05), लैक्टो-ओवो 0.77 (0.69–0.86), मछली खाने वाले 0.87 (0.77–0.99) | अवलोकनात्मक; स्व-रिपोर्ट किया गया आहार और जोखिम कारक |
| AHS-2 [53] | 3 | कोहोर्ट; 73,308 एडवेंटिस्ट; 5.79 वर्ष | वीगन, लैक्टो-ओवो, पेस्को-, अर्ध-शाकाहारी बनाम गैर-शाकाहारी | — | Vegetarians: IHD death 0.81 (0.64–1.02); men 0.71 (0.51–1.00). By group: vegan 0.90 (0.60–1.33), lacto-ovo 0.82 (0.62–1.06), pesco 0.65 (0.43–0.97); vegan men 0.45 (0.21–0.94), vegan women 1.39 (0.87–2.24) | Short follow-up; healthy-user profile (Figure 9); few vegan deaths |
| Plant diet indices [17] | 3 | 3 cohorts; ~209,000; 8,631 CHD | Healthful vs unhealthful plant-based indices | — | CHD HR (extreme deciles): PDI 0.92 (0.83–1.01); hPDI 0.75 (0.68–0.83); uPDI 1.32 (1.20–1.46) | FFQ-based; health professionals; hPDI rewards oils and nuts |
| UK Biobank processing [18] | 3 | Cohort; 126,842; median 9 y | Plant-sourced foods split by ultra-processing | — | Per 10% energy: plant non-UPF CVD 0.93 (0.91–0.95), CVD death 0.87 (0.80–0.94); plant UPF CVD 1.05 (1.03–1.07), death 1.12 (1.05–1.20) | Observational; 24-h recalls; NOVA classification |
| Danish nitrate cohort [29] | 3 | Cohort; 53,150; up to 23 y; 14,088 CVD | Vegetable nitrate quintiles (median 23 vs 59 mg/day) | Adjusted for hypercholesterolemia | CVD HR 0.85 (0.82–0.89); IHD 0.88 (0.82–0.94); ischemic stroke 0.83 (0.76–0.91); PAD 0.74 (0.67–0.83); 21.9% mediated by SBP | Observational; plateau ~60 mg/day; nitrate mainly lettuce and potato |
| Key 1999 pooled cohorts [54] | 3 | 5 cohorts; 76,172; mean 10.6 y | Vegan, lacto-ovo, fish eaters, occasional meat vs regular meat eaters | — | IHD mortality: vegetarians 0.76 (0.62–0.94); vegans 26% lower, lacto-ovo and fish eaters 34% lower; benefit limited to diet >5 y and larger at younger ages | Mortality only; older cohorts; adjusted for age, sex, smoking only |
| AHS-2 2024 [55] | 3 | Cohort; 88,400; ~11 y | Five diet groups | — | Vegetarians lower IHD mortality; vegan diet not associated with all-cause mortality overall; vegan men lower mortality at younger ages | Hazard ratios vary with age; stroke and dementia higher in older vegetarians |
| AHS-2 protein [57] | 3 | Cohort; 81,337; 9.4 y; 2,276 CVD deaths | Protein-source factors | — | CVD mortality: meat factor 1.61 (98.75% CI 1.12–2.32); nuts and seeds factor 0.60 (0.42–0.86) | Factor analysis; FFQ; observational |
| Vegan diets review [56] | 3 | Systematic review; 7 studies; ≥7,661 vegans | Vegan vs non-vegan | — | No cohort showed significantly higher or lower primary CVD risk in vegans | Few vegans; low power |
| Tzu Chi cohorts [58] | 3 | 2 cohorts; 13,352; Taiwan | Buddhist vegetarians (mostly lacto-ovo) vs non-vegetarians | — | Ischemic stroke 0.26 (0.08–0.88) and 0.41 (0.19–0.88); hemorrhagic 0.34 (0.12–1.00) | Stroke only; healthy-user setting; few events |
| Xiamen lacto-vegetarians [59] | 4 | Cross-sectional; 169 vs 126 men | Chinese lacto-vegetarian vs omnivore | — | Lower BP, LDL-C, ApoB, TG, glucose; thinner carotid IMT | Single measurement; surrogate markers; dairy-eating |
| Hong Kong vegans (review) [60] | 4 (review) | Review of cross-sectional and supplementation studies | Vegans and vegetarians with low B12 | — | ~80% B12 deficiency in Hong Kong vegans; impaired FMD and thicker IMT with deficiency; improved with B12 | Surrogate outcomes; caution for unsupplemented vegan diets |
| Tsimane [35] | 4 | Cross-sectional; 705 adults 40–94; CT calcium | 14% fat, 14% protein, 72% carbohydrate; game and fish; unprocessed | कोई नहीं | CAC 0 in 85%, 1–100 in 13%, >100 in 3%; >75 y: 65% zero; LDL-C 91 mg/dL; ApoB 97 mg/dL | CAC misses noncalcified plaque; cross-sectional; 6–7 h/day activity (men) |
| China Study I [43] | 4 | Ecological; 65 counties, 130 villages; diet 1983–84; mortality 1973–75 | 14% fat; animal protein ~1% of energy; not vegan | कोई नहीं | Mean TC 127 vs 203 mg/dL (US); CAD mortality ages 0–64: 4.0 (men) and 3.4 (women) vs 66.8 and 18.9 per 100,000 (US) | Ecological; decade gap; ages truncated; ascertainment; activity and competing mortality |
| Okinawa (Willcox) [45, 47] | 4 | Ecological; 1949 survey; vital statistics | ~1,785 kcal/day; sweet potato ~69% of energy; fat ~6%; some pork and fish | कोई नहीं | Older cohorts reported ~80% lower CHD mortality than US | Post-war scarcity; energy restriction; body size; transition; no individual linkage |
| Esselstyn 1995/1999 [5, 42] | 4 | Case series; 22–24 enrolled; 11 imaged at ~5 y | ≤10% fat; skim milk, nonfat yogurt allowed | Cholestyramine + lovastatin most often | TC 246 → 132.4 mg/dL (LDL-C 71.6); % stenosis 53.4 → 46.2% (−7 points, CI 3.3–10.7); MLD +0.08 mm (−0.06 to 0.22), NS; regression in 8/11 patients by % stenosis | No control; 13 of 38 lesions excluded (4 graft-proximal lesions that progressed); attrition reported as 5 and as 11; drugs; regression to the mean |
| Esselstyn 2014 [4] | 4 | Cohort; 198 (177 adherent, 21 nonadherent); mean 44.2 mo | No animal foods, oil, nuts, avocado; fat not measured | Usual medications, not recorded | Adherent: 1 progression-related stroke per investigators (0.6%); 18/177 “worse” (10%); 0 cardiac deaths. Nonadherent: 13/21 (62%) with ≥1 event, 7 of 13 events revascularizations | Self-selected; self-reported adherence; no lipids; investigator adjudication; not randomized; 2.2% in supplementary table |
| Lifestyle Heart Trial [6, 63] | 2 (events: counts) | RCT (invitational), 48; 35 with 5-y QCA; 5 y | 10% fat vegetarian (nonfat dairy, egg white); achieved 6.2% (1 y), 8.5% (5 y); plus exercise, stress management, support | No lipid drugs (exp.); 60% of controls started them | 5-y (1998 report, n = 35): % diameter stenosis −3.07 (−5.91 to −0.24) vs +11.77 (3.40 to 20.14), P = .001; minimum lumen diameter essentially unchanged (+0.001 mm) vs −0.34 mm (P = .05); 1-y (1990 report, n = 48): 40.0% → 37.8% vs 42.7% → 46.1%, 82% of experimental patients toward regression; events 25 vs 45, rate ratio 2.47 (1.48–4.20); angina −91% at 1 y (within group) | Multicomponent; small; half of eligible declined; attrition; events = recurrent counts, mostly procedures; stenosis and lumen diameter are not plaque volume |
| Gould 1995 PET [61] | 2 | Same trial; 20 vs 15 | उपरोक्त के अनुसार | उपरोक्त के अनुसार | Perfusion abnormalities smaller/less severe vs worsening in controls | Not independent; functional endpoint |
| Multicenter Lifestyle Demonstration [64] | 4 | Nonrandomized; 194 vs 139 revascularized; 3 y | ornish कार्यक्रम | Not reported | 150/194 (77%) avoided revascularization; similar MI, stroke, death rates per patient-year | Self-selection; comparator is revascularized patients |
| STARS [66] | 2 | RCT; 90 men; 39 mo | Lipid-lowering diet, 27% fat (not vegan) ± cholestyramine | Cholestyramine in one arm | MAWS −0.201 (usual care), +0.003 (diet), +0.103 mm (diet + resin); progression 46%, 15%, 12% | Small; men only; not plant-exclusive |
| Heidelberg [62] | 2 | RCT; 113 men; 12 mo | Low-fat, low-cholesterol diet + intensive exercise | No lipid drugs | Progression 23% vs 48%; regression 32% vs 17% | Exercise co-intervention; lipid differences gone at 6 y |
| DISCO-CT [68] | 2 | RCT; 92; ~67 wk; CCTA | DASH-based counseling + activity + OMT vs OMT | OMT in both arms | Noncalcified plaque −51.3 vs −21.3 mm³ (P = .045); total atheroma change not significantly different; ~6-y follow-up: MACE 1 vs 4 [69] | Single center; not plant-exclusive; weight largely regained; too few events |
| EVADE CAD [9] | 2 | RCT; 100; 8 wk | Vegan vs AHA diet; median fat 29.9% vs 30.2% of energy at 8 wk; unsaturated oils encouraged and olive oil in recipes for both; groceries provided | 94–96% statins | hs-CRP 32% lower (β 0.68, 0.49–0.94); LDL-C 13% lower (β 0.87, 0.78–0.97; NS at Bonferroni α) | Short; biomarker only; not very-low-fat; 14% of those meeting initial criteria enrolled |
| Barnard 2021 crossover [23] | 2 | Crossover RCT; 62 randomized, 52 completers; 16 wk per diet | Low-fat vegan (17% of energy from fat achieved; 95% CI 15–19) vs PREDIMED-style Mediterranean | Lipid estimate in 43 without lipid-drug changes; BP estimate in 41 without antihypertensive changes | Weight −6.0 kg (−7.5 to −4.5) and LDL-C −14.8 mg/dL (−23.5 to −6.2) favoring vegan; SBP +6.0 mm Hg (+1.0 to +10.9) favoring Mediterranean | Short; diet-induced weight loss may mediate the effects, so the direct effect of dietary composition is not isolated; advocacy sponsor; not a 10–15%-fat diet; significant SBP carryover in the all-participant analysis but not in the stable-medication subgroup; 1 participant reassigned after randomization to match a household member |
| CARDIVEG [71] | 2 | क्रॉसओवर RCT; 107 कम जोखिम वाले; प्रति आहार 3 महीने | कम कैलोरी वाला लैक्टो-ओवो शाकाहारी बनाम कम कैलोरी वाला भूमध्यसागरीय | कम जोखिम वाले वयस्क | वजन घटाने में समानता; शाकाहारी पर LDL-C कम; भूमध्यसागरीय पर TG कम; शाकाहारी पर B12 गिरा | कम जोखिम; वीगन या बहुत कम वसा वाला नहीं |
| हृदय स्वास्थ्य के लिए नुस्खा [8] | 2 | क्रॉसओवर RCT; 40; प्रति चरण 4 सप्ताह | उच्च EVOO (48% वसा) वाला WFPB वीगन बनाम कम EVOO (32% वसा) | निर्दिष्ट नहीं | दोनों ने LDL-C और ApoB को कम किया; अवधि 1 LDL-C −25.5 बनाम −16.7 mg/dL (P = .162); अनुक्रम अंतःक्रिया (sequence interaction) | छोटा; कैरीओवर; कोई भी चरण बहुत कम वसा वाला नहीं |
| पोर्टफोलियो मेटा-विश्लेषण [15] | 2 | नियंत्रित परीक्षण; 439 प्रतिभागी | NCEP स्टेप II आहार में नट्स, वनस्पति प्रोटीन, चिपचिपा फाइबर, स्टेरोल्स जोड़े गए; परीक्षणों में वसा की मात्रा अलग-अलग थी | विविध | LDL-C ~17% कम; ApoB और नॉन-HDL-C भी कम | केवल लिपिड एंडपॉइंट्स; इसमें नट्स शामिल हैं (कम वसा नहीं) |
| प्रसंस्करण RCT [19] | 2 | इनपेशेंट क्रॉसओवर; 20; प्रत्येक 2 सप्ताह | अल्ट्रा-प्रोसेस्ड बनाम अनप्रोसेस्ड, प्रस्तुत पोषक तत्वों के लिए मिलान किया गया | — | +508 ± 106 किलोकैलोरी/दिन अल्ट्रा-प्रोसेस्ड पर; +0.9 बनाम −0.9 किलोग्राम | छोटा; ऊर्जा संतुलन, एथेरोस्क्लेरोसिस नहीं |
| DASH [11] | 2 | फीडिंग RCT; 459; 8 सप्ताह | कम वसा वाले डेयरी सहित DASH संयोजन | — | BP −5.5/−3.0 mm Hg; उच्च रक्तचाप −11.4/−5.5 | केवल BP एंडपॉइंट |
| DASH-सोडियम [16] | 2 | फीडिंग RCT | DASH + कम सोडियम बनाम उच्च-सोडियम नियंत्रण | — | SBP −7.1 (सामान्य रक्तचाप), −11.5 mm Hg (चरण 1 उच्च रक्तचाप) | केवल BP एंडपॉइंट |
| PREDIMED 2018 [12] | 1 | RCT; 7,447 उच्च जोखिम; माध्यिका 4.8 वर्ष | भूमध्यसागरीय + EVOO या नट्स बनाम वसा कम करने की सलाह | — | 96/2,543 बनाम 83/2,454 बनाम 109/2,450; HR 0.69 (0.53–0.91) EVOO; 0.72 (0.54–0.95) नट्स | यादृच्छिकीकरण (randomization) अनियमितताओं के कारण 2013 की रिपोर्ट वापस ली गई; नियंत्रण सलाह पर आधारित था |
| ल्योन डाइट हार्ट [70] | 1 | RCT; 605 पोस्ट-MI; औसत 46 महीने | मक्खन और क्रीम के स्थान पर ALA-समृद्ध मार्जरीन की आपूर्ति, साथ ही भूमध्यसागरीय-प्रकार की सलाह, बनाम विवेकपूर्ण पश्चिमी आहार | — | हृदय मृत्यु/MI 14 बनाम 44; व्यापक समग्र 27 बनाम 90 और 95 बनाम 180; समग्रों में समायोजित RR 0.28–0.53 | कमजोर तुलनात्मक; पुराना उपचार युग |
| CORDIOPREV [10] | 1 | RCT; 1,002 CHD; माध्यिका 7 वर्ष | भूमध्यसागरीय (40.5% वसा) बनाम कम वसा वाला सर्वाहारी (32.1% वसा) | स्टैटिन 86.6% | 87 (17.3%) बनाम 111 (22.2%); HR 0.745 (0.563–0.986); पुरुष HR 0.669 (0.489–0.915); 175 महिलाओं में अनुमान अनिर्णायक | एकल केंद्र; जैतून के तेल फाउंडेशन का वित्तपोषण; कम वसा वाला हिस्सा VLF-WFPB नहीं था |
| हूपर 2020 कोक्रेन [26] | 1 | मुख्य घटना विश्लेषण में 12 RCT; 53,758 | संतृप्त वसा में कमी | — | संयुक्त CV घटनाएं RR 0.83 (0.70–0.98) | संतृप्त वसा का परीक्षण करता है, कुल वसा या VLF-WFPB का नहीं |
तालिका 5. VLF-WFPB के प्रस्तावित लाभ: तुलनात्मक आहार के साथ साझा, या अतिरिक्त लाभ का साक्ष्य?
| प्रस्तावित लाभ | प्रमुख साक्ष्य | भूमध्यसागरीय / DASH के साथ साझा? | VLF-WFPB के लिए अतिरिक्त लाभ का साक्ष्य | निर्णय |
| कम LDL-C और ApoB (बहुत कम संतृप्त वसा, कोई आहार कोलेस्ट्रॉल नहीं, फाइबर, वनस्पति प्रोटीन) | सर्वाहारी आहार के बनाम संयुक्त RCT [22]; वीगन बनाम भूमध्यसागरीय क्रॉसओवर [23]; CARDIVEG [71]; पोर्टफोलियो [15] | आंशिक रूप से: सभी में संतृप्त वसा कम होती है; पोर्टफोलियो नट्स के साथ ~17% LDL-C की कमी प्राप्त करता है; प्रत्यक्ष तुलना में भूमध्यसागरीय ने LDL-C को कम घटाया | कुछ पादप-आधारित हस्तक्षेप हफ्तों से महीनों में चयनित तुलनात्मक आहारों की तुलना में LDL-C और ApoB को अधिक कम करते हैं; विशिष्ट 10-15% वसा वाले प्रोटोकॉल की श्रेष्ठता स्थापित नहीं है | समर्थित (बायोमार्कर); विशिष्ट प्रोटोकॉल के लिए स्थापित नहीं |
| वजन घटाना / कम ऊर्जा घनत्व | वांग [7]; बर्नार्ड [23]; ओर्निश [6] | समान जब दोनों आहार ऊर्जा-प्रतिबंधित होते हैं [71] | छोटे परीक्षणों में अपनी इच्छानुसार (ad libitum) भोजन के साथ अधिक | संदर्भ-निर्भर |
| निम्न रक्तचाप | वांग (शून्य) [7]; DASH [11, 16]; बर्नार्ड [23] | हाँ; DASH और भूमध्यसागरीय समान या बेहतर | कोई भी नहीं दिखाया गया | कोई अतिरिक्त लाभ नहीं दिखाया गया |
| बेहतर ग्लाइसेमिक नियंत्रण | वांग, टाइप 2 मधुमेह उपसमूह [7] | आंशिक रूप से | पारंपरिक मधुमेह आहार के बनाम, भूमध्यसागरीय के बनाम नहीं | समर्थित लेकिन अनिश्चित |
| ट्राइग्लिसराइड्स और HDL-C | ओर्निश [6]; कोच [22]; CARDIVEG [71] | भूमध्यसागरीय TG को अधिक कम करता है | बहुत कम वसा वाले आहार ट्राइग्लिसराइड्स बढ़ा सकते हैं और HDL-C कम कर सकते हैं; केवल HDL-C में कमी हृदय संबंधी नुकसान प्रदर्शित नहीं करती है [80], और ट्राइग्लिसराइड्स को ApoB, नॉन-HDL-C और परिणामों के साथ पढ़ा जाना चाहिए | अनिश्चित; संभावित नुकसान |
| कम सूजन (hs-CRP) | EVADE CAD [9] | Mediterranean also lowered inflammatory markers in CARDIVEG [71] | vs AHA diet at ~30% fat; not tested at very low fat | जैविक रूप से प्रशंसनीय |
| Better endothelial function | Single-meal studies [30, 81]; olive-oil meta-analysis [32]; CORDIOPREV substudy [33]; EVADE EndoPAT [9] | Yes: sustained olive-oil and Mediterranean diets improved FMD | None sustained for VLF-WFPB | असमर्थित |
| Lower stroke risk | EPIC-ऑक्सफोर्ड [41]; Dybvik [40] | — | No: the higher stroke rate in EPIC-Oxford concerns its vegetarian grouping, not VLF-WFPB, which has not been tested for stroke | Not demonstrated either way |
| Clear food rules that aid adherence | Adherence data [4, 6, 9] | Any structured program | Behavioral hypothesis; strictness may help some and deter others | Hypothesis |
| Whole, minimally processed foods | Plant diet indices [17]; UK Biobank [18]; processing RCT [19] | Partly: DASH and Mediterranean are also minimally processed patterns | Strongest non-lipid lever; plant ultra-processed foods associated with higher risk | समर्थित लेकिन अनिश्चित |
| Leafy-green nitrate → nitric oxide | Danish cohort [29] | Yes: any vegetable-rich pattern | Association persists after lipid adjustment; not vegan-specific | Plausible, partly supported |
| Fiber → butyrate | Mouse models [28] | Yes: any high-fiber pattern | Cholesterol-independent in mice; no human outcome data | जैविक रूप से प्रशंसनीय |
| Lower TMAO / favorable microbiome | Cohort association [37]; Mendelian randomization null [38] | Partly (fiber-rich patterns) | No outcome evidence; genetic evidence against a causal TMAO effect | Weak hypothesis |
| Exclusion of added oil | हृदय स्वास्थ्य के लिए नुस्खा [8]; PREDIMED [12]; CORDIOPREV [10] | No: EVOO-rich diets reduced events vs comparators | Large oil additions may blunt LDL-C lowering; no event data | Unsupported as necessary |
| Exclusion of nuts and seeds | PREDIMED nut arm [12] | No: nut-supplemented diet reduced events | कोई नहीं | असमर्थित |
| Angiographic slowing or regression | Lifestyle Heart [6]; STARS [66]; Heidelberg [62]; DISCO-CT [68] | Yes: lower-fat non-vegan and DASH-based programs also slowed progression | Package effect only; diet share unknown | समर्थित लेकिन अनिश्चित |
| Complete exclusion of animal foods | AHS-2 [53]; EPIC-Oxford [41]; pooled cohorts [54]; vegan review [56]; AHS-2 protein [57] | लागू नहीं | None: vegans did not do better than lacto-ovo or pesco-vegetarians; nut and seed protein associated with lower CVD mortality | असमर्थित |
Abbreviations: ApoB, apolipoprotein B; BP, blood pressure; CCTA, coronary CT angiography; CHD, coronary heart disease; EVOO, extra-virgin olive oil; IHD, ischemic heart disease; MAWS, mean absolute width of coronary segments; MLD, minimal lumen diameter; NS, not significant; OMT, optimal medical therapy; QCA, quantitative coronary angiography; RCT, यादृच्छिक नियंत्रित परीक्षण; TC, total cholesterol; TG, triglycerides; VLF-WFPB, very-low-fat whole-food plant-based.
संदर्भ
- Wang T, Masedunskas A, Willett WC, Fontana L. Vegetarian and vegan diets: benefits and drawbacks. Eur Heart J. 2023;44(36):3423–3439. doi:10.1093/eurheartj/ehad436.
- Freeman AM, Morris PB, Barnard N, et al. Trending cardiovascular nutrition controversies. J Am Coll Cardiol. 2017;69(9):1172–1187. doi:10.1016/j.jacc.2016.10.086. PMID 28254181.
- Kahleova H, Levin S, Barnard ND. Vegetarian dietary patterns and cardiovascular disease. Prog Cardiovasc Dis. 2018;61(1):54–61. doi:10.1016/j.pcad.2018.05.002. PMID 29800598.
- Esselstyn CB Jr, Gendy G, Doyle J, Golubic M, Roizen MF. A way to reverse CAD? J Fam Pract. 2014;63(7):356–364b. PMID 25198208.
- Esselstyn CB Jr. Updating a 12-year experience with arrest and reversal therapy for coronary heart disease (an overdue requiem for palliative cardiology). Am J Cardiol. 1999;84(3):339–341, A8. doi:10.1016/S0002-9149(99)00290-8. PMID 10496449.
- Ornish D, Scherwitz LW, Billings JH, et al. Intensive lifestyle changes for reversal of coronary heart disease. JAMA. 1998;280(23):2001–2007. doi:10.1001/jama.280.23.2001. PMID 9863851. Correction (author list): JAMA. 1999;281(15):1380.
- Wang T, Kroeger CM, Cassidy S, et al. Vegetarian dietary patterns and cardiometabolic risk in people with or at high risk of cardiovascular disease: a systematic review and meta-analysis. JAMA Netw Open. 2023;6(7):e2325658. doi:10.1001/jamanetworkopen.2023.25658. PMID 37490288.
- Krenek AM, Mathews A, Guo J, et al. Recipe for Heart Health: a randomized crossover trial on cardiometabolic effects of extra virgin olive oil within a whole-food plant-based vegan diet. J Am Heart Assoc. 2024;13(15):e035034. doi:10.1161/JAHA.124.035034. PMID 39045758.
- Shah B, Newman JD, Woolf K, et al. Anti-inflammatory effects of a vegan diet versus the American Heart Association–recommended diet in coronary artery disease trial. J Am Heart Assoc. 2018;7(23):e011367. doi:10.1161/JAHA.118.011367. PMID 30571591.
- Delgado-Lista J, Alcala-Diaz JF, Torres-Peña JD, et al. Long-term secondary prevention of cardiovascular disease with a Mediterranean diet and a low-fat diet (CORDIOPREV): a randomised controlled trial. Lancet. 2022;399(10338):1876–1885. doi:10.1016/S0140-6736(22)00122-2. PMID 35525255.
- Appel LJ, Moore TJ, Obarzanek E, et al. A clinical trial of the effects of dietary patterns on blood pressure. DASH Collaborative Research Group. N Engl J Med. 1997;336(16):1117–1124. doi:10.1056/NEJM199704173361601. PMID 9099655.
- Estruch R, Ros E, Salas-Salvadó J, et al. Primary prevention of cardiovascular disease with a Mediterranean diet supplemented with extra-virgin olive oil or nuts. N Engl J Med. 2018;378(25):e34. doi:10.1056/NEJMoa1800389. PMID 29897866. (Replaces the retracted 2013 report.)
- Kris-Etherton P, Eckel RH, Howard BV, St Jeor S, Bazzarre TL. AHA science advisory: Lyon Diet Heart Study. Benefits of a Mediterranean-style, National Cholesterol Education Program/American Heart Association Step I dietary pattern on cardiovascular disease. Circulation. 2001;103(13):1823–1825. doi:10.1161/01.CIR.103.13.1823.
- de Lorgeril M, Renaud S, Mamelle N, et al. Mediterranean alpha-linolenic acid-rich diet in secondary prevention of coronary heart disease. Lancet. 1994;343(8911):1454–1459. doi:10.1016/S0140-6736(94)92580-1.
- Chiavaroli L, Nishi SK, Khan TA, et al. Portfolio dietary pattern and cardiovascular disease: a systematic review and meta-analysis of controlled trials. Prog Cardiovasc Dis. 2018;61(1):43–53. doi:10.1016/j.pcad.2018.05.004. PMID 29807048.
- Sacks FM, Svetkey LP, Vollmer WM, et al. Effects on blood pressure of reduced dietary sodium and the Dietary Approaches to Stop Hypertension (DASH) diet. N Engl J Med. 2001;344(1):3–10. doi:10.1056/NEJM200101043440101. PMID 11136953.
- Satija A, Bhupathiraju SN, Spiegelman D, et al. Healthful and unhealthful plant-based diets and the risk of coronary heart disease in U.S. adults. J Am Coll Cardiol. 2017;70(4):411–422. doi:10.1016/j.jacc.2017.05.047. PMID 28728684.
- Rauber F, Louzada MLC, Chang K, et al. Implications of food ultra-processing on cardiovascular risk considering plant origin foods: an analysis of the UK Biobank cohort. Lancet Reg Health Eur. 2024;43:100948. doi:10.1016/j.lanepe.2024.100948. PMID 39210945.
- Hall KD, Ayuketah A, Brychta R, et al. Ultra-processed diets cause excess calorie intake and weight gain: an inpatient randomized controlled trial of ad libitum food intake. Cell Metab. 2019;30(1):67–77.e3. doi:10.1016/j.cmet.2019.05.008.
- Ference BA, Ginsberg HN, Graham I, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease. 1. Evidence from genetic, epidemiologic, and clinical studies. A consensus statement from the European Atherosclerosis Society Consensus Panel. Eur Heart J. 2017;38(32):2459–2472. doi:10.1093/eurheartj/ehx144. PMID 28444290.
- Cholesterol Treatment Trialists’ (CTT) Collaboration. Efficacy and safety of more intensive lowering of LDL cholesterol: a meta-analysis of data from 170 000 participants in 26 randomised trials. Lancet. 2010;376(9753):1670–1681. doi:10.1016/S0140-6736(10)61350-5. PMID 21067804.
- Koch CA, Kjeldsen EW, Frikke-Schmidt R. Vegetarian or vegan diets and blood lipids: a meta-analysis of randomized trials. Eur Heart J. 2023;44(28):2609–2622. doi:10.1093/eurheartj/ehad211. PMID 37226630.
- Barnard ND, Alwarith J, Rembert E, et al. A Mediterranean diet and low-fat vegan diet to improve body weight and cardiometabolic risk factors: a randomized, cross-over trial. J Am Nutr Assoc. 2022;41(2):127–139. doi:10.1080/07315724.2020.1869625. PMID 33544066.
- McMurry MP, Connor WE, Cerqueira MT. Dietary cholesterol and the plasma lipids and lipoproteins in the Tarahumara Indians: a people habituated to a low cholesterol diet after weaning. Am J Clin Nutr. 1982;35(4):741–744. doi:10.1093/ajcn/35.4.741.
- Lichtenstein AH, Khera A, Anderson CAM, et al. 2026 dietary guidance to improve cardiovascular health: a scientific statement from the American Heart Association. Circulation. Published online 31 March 2026. doi:10.1161/CIR.0000000000001435.
- Hooper L, Martin N, Jimoh OF, Kirk C, Foster E, Abdelhamid AS. Reduction in saturated fat intake for cardiovascular disease. Cochrane Database Syst Rev. 2020;(8):CD011737. doi:10.1002/14651858.CD011737.pub3. (Version of record superseding the May 2020 issue, PMID 32428300.)
- Blumenthal RS, Morris PB, Gaudino M, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA guideline on the management of dyslipidemia: a report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2026. doi:10.1161/CIR.0000000000001423. Also J Am Coll Cardiol. doi:10.1016/j.jacc.2025.11.016.
- Kasahara K, Krautkramer KA, Org E, et al. Interactions between Roseburia intestinalis and diet modulate atherogenesis in a murine model. Nat Microbiol. 2018;3(12):1461–1471. doi:10.1038/s41564-018-0272-x.
- Bondonno CP, Dalgaard F, Blekkenhorst LC, et al. Vegetable nitrate intake, blood pressure and incident cardiovascular disease: Danish Diet, Cancer, and Health Study. Eur J Epidemiol. 2021;36(8):813–825. doi:10.1007/s10654-021-00747-3.
- Vogel RA, Corretti MC, Plotnick GD. Effect of a single high-fat meal on endothelial function in healthy subjects. Am J Cardiol. 1997;79(3):350–354. doi:10.1016/S0002-9149(96)00760-6. PMID 9036757.
- Vogel RA, Corretti MC, Plotnick GD. The postprandial effect of components of the Mediterranean diet on endothelial function. J Am Coll Cardiol. 2000;36(5):1455–1460. doi:10.1016/S0735-1097(00)00896-2. PMID 11079642.
- Schwingshackl L, Christoph M, Hoffmann G. Effects of olive oil on markers of inflammation and endothelial function—a systematic review and meta-analysis. Nutrients. 2015;7(9):7651–7675. doi:10.3390/nu7095356. PMID 26378571.
- Yubero-Serrano EM, Fernandez-Gandara C, Garcia-Rios A, et al. Mediterranean diet and endothelial function in patients with coronary heart disease: an analysis of the CORDIOPREV randomized controlled trial. PLoS Med. 2020;17(9):e1003282. doi:10.1371/journal.pmed.1003282. PMID 32903262.
- Christ A, Günther P, Lauterbach MAR, et al. Western diet triggers NLRP3-dependent innate immune reprogramming. Cell. 2018;172(1-2):162–175.e14. doi:10.1016/j.cell.2017.12.013. PMID 29328911.
- Kaplan H, Thompson RC, Trumble BC, et al. Coronary atherosclerosis in indigenous South American Tsimane: a cross-sectional cohort study. Lancet. 2017;389(10080):1730–1739. doi:10.1016/S0140-6736(17)30752-3. PMID 28320601.
- Koeth RA, Wang Z, Levison BS, et al. Intestinal microbiota metabolism of L-carnitine, a nutrient in red meat, promotes atherosclerosis. Nat Med. 2013;19(5):576–585. doi:10.1038/nm.3145. PMID 23563705.
- Tang WHW, Wang Z, Levison BS, et al. Intestinal microbial metabolism of phosphatidylcholine and cardiovascular risk. N Engl J Med. 2013;368(17):1575–1584. doi:10.1056/NEJMoa1109400. PMID 23614584.
- Jia J, Dou P, Gao M, et al. Assessment of causal direction between gut microbiota-dependent metabolites and cardiometabolic health: a bidirectional Mendelian randomization analysis. Diabetes. 2019;68(9):1747–1755. doi:10.2337/db19-0153.
- Watts GF, Jackson P, Mandalia S, et al. Nutrient intake and progression of coronary artery disease. Am J Cardiol. 1994;73(5):328–332. PMID 8109545.
- Dybvik JS, Svendsen M, Aune D. Vegetarian and vegan diets and the risk of cardiovascular disease, ischemic heart disease and stroke: a systematic review and meta-analysis of prospective cohort studies. Eur J Nutr. 2023;62(1):51–69. doi:10.1007/s00394-022-02942-8. PMID 36030329.
- Tong TYN, Appleby PN, Bradbury KE, et al. Risks of ischaemic heart disease and stroke in meat eaters, fish eaters, and vegetarians over 18 years of follow-up: results from the prospective EPIC-Oxford study. BMJ. 2019;366:l4897. doi:10.1136/bmj.l4897. PMID 31484644.
- Esselstyn CB Jr, Ellis SG, Medendorp SV, Crowe TD. A strategy to arrest and reverse coronary artery disease: a 5-year longitudinal study of a single physician’s practice. J Fam Pract. 1995;41(6):560–568. PMID 7500065.
- Campbell TC, Parpia B, Chen J. Diet, lifestyle, and the etiology of coronary artery disease: the Cornell China study. Am J Cardiol. 1998;82(10B):18T–21T. doi:10.1016/S0002-9149(98)00718-8. PMID 9860369.
- Connor WE, Cerqueira MT, Connor RW, Wallace RB, Malinow MR, Casdorph HR. The plasma lipids, lipoproteins, and diet of the Tarahumara Indians of Mexico. Am J Clin Nutr. 1978;31(7):1131–1142. doi:10.1093/ajcn/31.7.1131. PMID 665563.
- Willcox BJ, Willcox DC, Todoriki H, et al. Caloric restriction, the traditional Okinawan diet, and healthy aging: the diet of the world’s longest-lived people and its potential impact on morbidity and life span. Ann N Y Acad Sci. 2007;1114:434–455. doi:10.1196/annals.1396.037. PMID 17986602.
- Willcox DC, Willcox BJ, Todoriki H, Suzuki M. The Okinawan diet: health implications of a low-calorie, nutrient-dense, antioxidant-rich dietary pattern low in glycemic load. J Am Coll Nutr. 2009;28(Suppl):500S–516S. doi:10.1080/07315724.2009.10718117. PMID 20234038.
- Willcox BJ, Willcox DC. Caloric restriction, caloric restriction mimetics, and healthy aging in Okinawa: controversies and clinical implications. Curr Opin Clin Nutr Metab Care. 2014;17(1):51–58. doi:10.1097/MCO.0000000000000019. PMID 24316687.
- Gavrilova NS, Gavrilov LA. Comments on dietary restriction, Okinawa diet and longevity. Gerontology. 2012;58(3):221–223. doi:10.1159/000329894. PMID 21893946.
- Lindeberg S, Lundh B. Apparent absence of stroke and ischaemic heart disease in a traditional Melanesian island: a clinical study in Kitava. J Intern Med. 1993;233(3):269–275. doi:10.1111/j.1365-2796.1993.tb00986.x. PMID 8450295.
- Lindeberg S, Nilsson-Ehle P, Terént A, Vessby B, Scherstén B. Cardiovascular risk factors in a Melanesian population apparently free from stroke and ischaemic heart disease: the Kitava study. J Intern Med. 1994;236(3):331–340.
- Lindeberg S, Nilsson-Ehle P, Vessby B. Lipoprotein composition and serum cholesterol ester fatty acids in nonwesternized Melanesians. Lipids. 1996;31(2):153–158. doi:10.1007/BF02522614. PMID 8835402.
- Kwok CS, Umar S, Myint PK, Mamas MA, Loke YK. Vegetarian diet, Seventh Day Adventists and risk of cardiovascular mortality: a systematic review and meta-analysis. Int J Cardiol. 2014;176(3):680–686. doi:10.1016/j.ijcard.2014.07.080.
- Orlich MJ, Singh PN, Sabaté J, et al. Vegetarian dietary patterns and mortality in Adventist Health Study 2. JAMA Intern Med. 2013;173(13):1230–1238. doi:10.1001/jamainternmed.2013.6473. PMID 23836264.
- Key TJ, Fraser GE, Thorogood M, et al. Mortality in vegetarians and nonvegetarians: detailed findings from a collaborative analysis of 5 prospective studies. Am J Clin Nutr. 1999;70(3 Suppl):516S–524S. doi:10.1093/ajcn/70.3.516s. PMID 10479225.
- Abris GP, Shavlik DJ, Mathew RO, et al. Cause-specific and all-cause mortalities in vegetarian compared with those in nonvegetarian participants from the Adventist Health Study-2 cohort. Am J Clin Nutr. 2024;120(4):907–917. doi:10.1016/j.ajcnut.2024.07.028. PMID 39098708.
- Kaiser J, van Daalen KR, Thayyil A, Cocco MTARR, Caputo D, Oliver-Williams C. A systematic review of the association between vegan diets and risk of cardiovascular disease. J Nutr. 2021;151(6):1539–1552. doi:10.1093/jn/nxab037. PMID 33831953.
- Tharrey M, Mariotti F, Mashchak A, Barbillon P, Delattre M, Fraser GE. Patterns of plant and animal protein intake are strongly associated with cardiovascular mortality: the Adventist Health Study-2 cohort. Int J Epidemiol. 2018;47(5):1603–1612. doi:10.1093/ije/dyy030. PMID 29618018.
- Chiu THT, Chang HR, Wang LY, Chang CC, Lin MN, Lin CL. Vegetarian diet and incidence of total, ischemic, and hemorrhagic stroke in 2 cohorts in Taiwan. Neurology. 2020;94(11):e1112–e1121. doi:10.1212/WNL.0000000000009093. PMID 32102976.
- Yang SY, Li XJ, Zhang W, et al. Chinese lacto-vegetarian diet exerts favorable effects on metabolic parameters, intima-media thickness, and cardiovascular risks in healthy men. Nutr Clin Pract. 2012;27(3):392–398. doi:10.1177/0884533611436173. PMID 22412169.
- Woo KS, Kwok TCY, Celermajer DS. Vegan diet, subnormal vitamin B-12 status and cardiovascular health. Nutrients. 2014;6(8):3259–3273. doi:10.3390/nu6083259. PMID 25195560.
- Gould KL, Ornish D, Scherwitz L, et al. Changes in myocardial perfusion abnormalities by positron emission tomography after long-term, intense risk factor modification. JAMA. 1995;274(11):894–901. doi:10.1001/jama.1995.03530110056036. PMID 7674504.
- Schuler G, Hambrecht R, Schlierf G, et al. Regular physical exercise and low-fat diet: effects on progression of coronary artery disease. Circulation. 1992;86(1):1–11. doi:10.1161/01.cir.86.1.1. PMID 1617762.
- Ornish D, Brown SE, Scherwitz LW, et al. Can lifestyle changes reverse coronary heart disease? The Lifestyle Heart Trial. Lancet. 1990;336(8708):129–133. doi:10.1016/0140-6736(90)91656-U. PMID 1973470.
- Ornish D. Avoiding revascularization with lifestyle changes: the Multicenter Lifestyle Demonstration Project. Am J Cardiol. 1998;82(10B):72T–76T. doi:10.1016/S0002-9149(98)00744-9. PMID 9860380.
- Silberman A, Banthia R, Estay IS, et al. The effectiveness and efficacy of an intensive cardiac rehabilitation program in 24 sites. Am J Health Promot. 2010;24(4):260–266. (Cited only as the second source of an untraced statement in ref. 2.)
- Watts GF, Lewis B, Brunt JN, et al. Effects on coronary artery disease of lipid-lowering diet, or diet plus cholestyramine, in the St Thomas’ Atherosclerosis Regression Study (STARS). Lancet. 1992;339(8793):563–569. doi:10.1016/0140-6736(92)90863-X. PMID 1347091.
- Niebauer J, Hambrecht R, Velich T, et al. Attenuated progression of coronary artery disease after 6 years of multifactorial risk intervention: role of physical exercise. Circulation. 1997;96(8):2534–2541. PMID 9355890.
- Henzel J, Kępka C, Kruk M, et al. High-risk coronary plaque regression after intensive lifestyle intervention in nonobstructive coronary disease: a randomized study. JACC Cardiovasc Imaging. 2021;14(6):1192–1202. doi:10.1016/j.jcmg.2020.10.019. PMID 33341413.
- Makarewicz-Wujec M, Henzel J, Kępka C, et al. Long-term outcomes of the Dietary Approaches to Stop Hypertension (DASH) intervention in nonobstructive coronary artery disease: follow-up of the DISCO-CT study. Nutrients. 2025;17(15):2565. doi:10.3390/nu17152565.
- de Lorgeril M, Salen P, Martin JL, Monjaud I, Delaye J, Mamelle N. Mediterranean diet, traditional risk factors, and the rate of cardiovascular complications after myocardial infarction: final report of the Lyon Diet Heart Study. Circulation. 1999;99(6):779–785. doi:10.1161/01.CIR.99.6.779. PMID 9989963.
- Sofi F, Dinu M, Pagliai G, et al. Low-calorie vegetarian versus Mediterranean diets for reducing body weight and improving cardiovascular risk profile: CARDIVEG Study (Cardiovascular Prevention With Vegetarian Diet). Circulation. 2018;137(11):1103–1113. doi:10.1161/CIRCULATIONAHA.117.030088. PMID 29483085.
- Rees K, Al-Khudairy L, Takeda A, Stranges S. Vegan dietary pattern for the primary and secondary prevention of cardiovascular diseases. Cochrane Database Syst Rev. 2021;2(2):CD013501. doi:10.1002/14651858.CD013501.pub2. PMID 33629376.
- Virani SS, Newby LK, Arnold SV, et al. 2023 AHA/ACC/ACCP/ASPC/NLA/PCNA guideline for the management of patients with chronic coronary disease. Circulation. 2023;148(9):e9–e119. doi:10.1161/CIR.0000000000001168.
- Dawson LP, Lum M, Nerleker N, Nicholls SJ, Layland J. Coronary atherosclerotic plaque regression: JACC state-of-the-art review. J Am Coll Cardiol. 2022;79(1):66–82. doi:10.1016/j.jacc.2021.10.035. PMID 34991791.
- Armstrong ML, Megan MB. Lipid depletion in atheromatous coronary arteries in rhesus monkeys after regression diets. Circ Res. 1972;30(6):675–680. doi:10.1161/01.res.30.6.675.
- Armstrong ML, Megan MB. Arterial fibrous proteins in cynomolgus monkeys after atherogenic and regression diets. Circ Res. 1975;36(2):256–261. doi:10.1161/01.res.36.2.256.
- Clarkson TB, Bond MG, Bullock BC, Marzetta CA. A study of atherosclerosis regression in Macaca mulatta. IV. Changes in coronary arteries from animals with atherosclerosis induced for 19 months and then regressed for 24 or 48 months at plasma cholesterol concentrations of 300 or 200 mg/dl. Exp Mol Pathol. 1981;34(3):345–368. doi:10.1016/0014-4800(81)90052-6.
- Nicholls SJ, Puri R, Anderson T, et al. Effect of evolocumab on progression of coronary disease in statin-treated patients: the GLAGOV randomized clinical trial. JAMA. 2016;316(22):2373–2384. doi:10.1001/jama.2016.16951. PMID 27846344.
- Melina V, Craig W, Levin S. Position of the Academy of Nutrition and Dietetics: vegetarian diets. J Acad Nutr Diet. 2016;116(12):1970–1980. doi:10.1016/j.jand.2016.09.025. PMID 27886704.
- Voight BF, Peloso GM, Orho-Melander M, et al. Plasma HDL cholesterol and risk of myocardial infarction: a Mendelian randomisation study. Lancet. 2012;380(9841):572–580. doi:10.1016/S0140-6736(12)60312-2. PMID 22607825.
- Vogel RA. The Mediterranean diet and endothelial function: why some dietary fats may be healthy. Cleve Clin J Med. 2000;67(4):232–236. (Reports the Vogel group’s postprandial olive-oil, vitamin, and vinegar-salad experiments.)

