
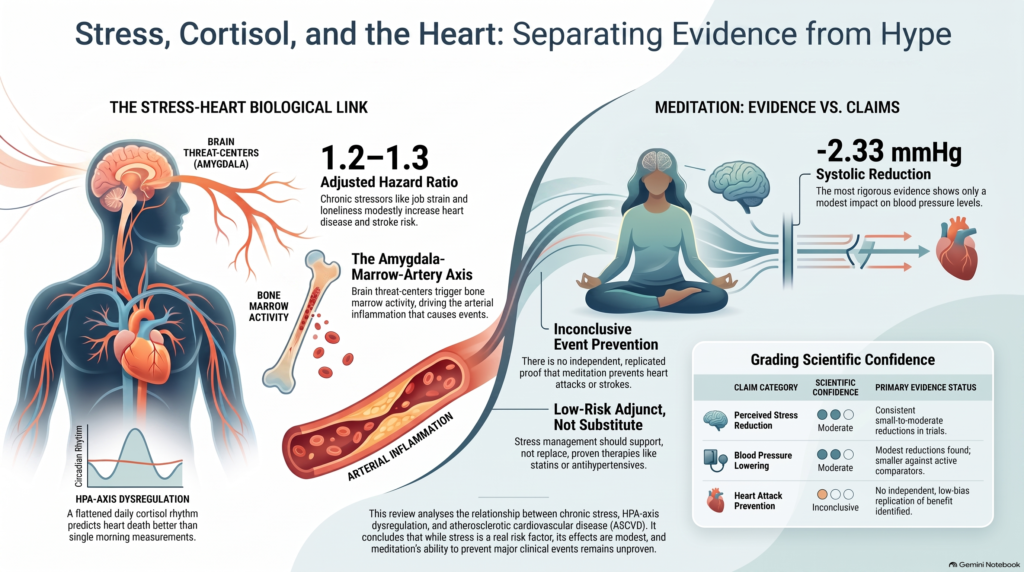
慢性心理的ストレス、視床下部-下垂体-副腎系(HPA軸)の調節障害、およびアテローム性動脈硬化性心血管疾患:メカニズム、影響の大きさ、および瞑想に基づく介入の証拠
構造化された批判 ナラティブレビューA narrative review is a type of scientific article that synthesizes existing research on a topic through expert selection and interpretation rather than through a pre-registered, exhaustive search with formal bias scoring; unlike a systematic review or meta-analysis, its conclusions can reflect the authors' editorial judgment in choosing which studies to emphasize. ヒトおよびトランスレーショナルエビデンスの
目次
- 抄録
- 範囲、情報源、およびエビデンス評価の枠組み
- 主な結論
- 確立されていること、確率が高いこと、わかっていないこと
- ストレス生理学:応答の構造
- コルチゾールの測定:検体マトリックス、動態、および解釈上のピットフォール
- ヒトの疫学エビデンス:ストレス曝露と動脈硬化性心血管疾患(ASCVD)
- コルチゾールとASCVD:原因、媒介因子、それともマーカー?
- メカニズムI:自律神経および血行動態
- メカニズムII: 炎症炎症は、怪我や侵入物とみなしたものに対する免疫システムの反応です。これにより腫れや熱、そして浄化細胞がもたらされます。. そして免疫
- メカニズムIII:内皮および血管
- メカニズムIV:代謝
- 機構V: 血栓症血栓症とは、血管内で血液が固まって血栓ができることです。. および急性誘発
- メカニズムVI:行動の媒介
- 機序的証拠マトリックス
- 介入の問い:分類法と主張のはしご
- ベンチマーク・シンセシス
- 主張A:知覚されたストレス
- 主張B:コルチゾールとHPA軸の生理学
- 主張C:確定 リスク要因危険因子とは、高コレステロール粒子、高血圧、喫煙、糖尿病、家族歴など、病気にかかる可能性を高めるものです。.
- 主張D: 動脈硬化症動脈硬化は、ほとんど的心筋梗塞と多くの脳卒中の背景にある病気です。コレステロールの粒子が動脈の壁に入り込み、体がそれを掃除するために免疫細胞を送り込み、何年もかけてその堆積物が硬化してプラークになります。.
- 主張E:重篤な臨床イベント
- エビデンスの質、バイアス、および有害事象
- リンクごとの証拠重み付き統合モデル
- 臨床および予防上のインプリケーション
- これらの結論を変える閾値
- 主要な未解決の研究上の問い
- 結論:主要な質問に対する直接的な回答
- このレビューの限界
- 参考文献
1. 抄録
背景. 慢性的な心理的ストレスは心疾患を引き起こすと広く主張されており、瞑想はそれを予防すると広く主張されている。どちらの主張も、検証されることよりも繰り返されることの方が多い。このレビューの目的は、査読済みの証拠が正確に何を支持しているのか、ヒトにおいては生物学的に妥当であるが未証明であることは何か、そして真の不確実性がどこに残っているのかを明確に述べることである。.
方法. 2026年8月20日までに検索されたMEDLINE/PubMed、Scopus、Embase、およびコクランライブラリー(CENTRALおよびCDSR)を通じて特定された査読済み文献の構造化された批判的ナラティブレビュー。参考文献および引用チェイニングを用いている。定量的主張は、一次情報源または固有名詞に遡る システマティックレビューシステマティックレビューは、事前に宣言された方法を用いてある問いに関するすべての研究を検索し、一貫した基準によってそれらを評価する。. 可能な限り、IEEEスタイルの番号付き引用を全体に散りばめてください。これは ではない 系統的レビュー:プロトコルは登録されず、重複除外前のレコード数は保持されておらず、研究レベルのバイアスリスク評価ツールは正式に適用されていない。エビデンスには、明示的な基準に照らして著者評価によるナラティブな確信度カテゴリ(強い、中等度、限定的、または結論が出ない)が割り当てられており、それぞれに格下げの明確な根拠が示されている。また、瞑想に関する5つの分離可能な主張が一貫して区別されている:(A)知覚されたストレスを軽減する;(B)コルチゾールまたは視床下部-下垂体-副腎(HPA)系生理機能を変化させる;(C)既establishedなリスク因子を改善する;(D)測定可能な動脈硬化の進行を遅らせる;(E)重大な臨床イベントを減少させる。.
調査結果. 前向きに研究されたいくつかの心理社会的ストレスの構成概念について、発症に対する調整済みの相対的な関連性は 冠動脈疾患冠状動脈疾患は、アスケロスクレロティック・プラーク(動脈硬化性プラーク)の蓄積によって心筋に血液を供給する動脈が狭窄または閉塞する疾患であり、世界中で心筋梗塞および心臓死の主要な原因となっています。. そして虚血性の 脳卒中脳卒中は、脳の一部への血流が詰まりまたは出血によって止まるときに起こります。. 曝露の定義やアウトカムによって推定値は異なるものの、一般的には1.2〜1.3の範囲に収まることが多い。これらは控えめな関連ではあるが、集団レベルでは決して無視できない規模のものである。これらは、以下に報告される相対的効果とは直接的に比較できるものではない。 喫煙喫煙は血管の内壁を傷つけ、血圧を上げ、血液を凝固しやすくし、プラークの成長を早めます。., 血圧血圧とは、血液が動脈の壁を押す力ののことです。120/80のように2つの数字で表されます。上の数字は心臓が収縮するときの圧力で、下の数字は弛緩するときの圧力です。. または累積 アポリポ蛋白アポリポ蛋白とは、血液中の脂肪を運ぶ粒子に結合しているタンパク質です。脂肪と水は混ざらないため、これらのタンパク質は脂肪が血流の中を安全に移動できるようにする包みのような役割を果たします。. BアポBアポBは、動脈の壁に詰まってプラークを引き起こす可能性のあるコレステロール粒子のすべての外側に存在するタンパク質です。それらの粒子はそれぞれ、正確に1個のアポBを運んでいます。.)の曝露であり、異なる曝露スケールで測定され、異なる設計によって確立されているため、それらを互いに順位付けするには、本レビューが試みていない較正された絶対リスク比較が必要となる。症例対照推定値は大幅に大きい(INTERHEARTINTERHEART was a large international case-control study that compared risk factors in people who had had a first heart attack against matched controls across 52 countries. The article cites its finding that permanent general stress carried an odds ratio of 2.17 for myocardial infarction, with psychosocial factors together accounting for a population-attributable risk of roughly 32.5%.恒常的な総合ストレスに対するオッズ比 2.17( 集団寄与危険度Population-attributable risk (PAR) is the proportion of cases of a disease in a population that could theoretically be prevented if a given risk factor were eliminated, taking into account both how risky the factor is and how common it is. The article cites INTERHEART's estimate that the combined psychosocial factor had a PAR of roughly 32.5% for myocardial infarction. (心理社会的要因の合計で≈32.5%)、さらにケース・クロスオーバー法による推定値はこれよりもさらに大きく(オッズ比 2.44、 心筋梗塞詳しい項目については心臓発作をご覧ください。. (激しい怒りから1時間以内)が、これらのデザインは異なるものを測定しており、将来のリスクと互換性はありません。因果関係の証拠は中等度です。これは時間的順序、生物学的妥当性、再現性のある実験的ヒト生理学、および1つの画期的な脳画像化コホートに基づいているためですが、次のような理由に基づくものではありません。 ランダム化無作為化とは、臨床試験の参加者を偶然によって治療群または対照群に割り当てるプロセスであり、既知および未知の交絡因子が均等に分散されることを保証するものです。しかし、PREDIMEDの研究で監査人が発見したように、無作為化が失敗した場合、両群間には治療効果の見かけを歪めるような違いが生じる可能性があります。., 、および residual confoundingThe bias that remains in an observational study even after statistical adjustment, because some shared risk factors — such as poverty, smoking, or diabetes — cannot be fully measured or removed; with a modest relative risk like 1.20, residual confounding alone could plausibly explain the entire observed association. 社会経済的地位および行動による影響は排除できない。. 遺伝子組換え技術はこのリストには属さない。. 利用可能な メンデルランダム化Mendelian randomization is a clever research method that uses the genes people were born with as a natural experiment. 機器測定による早朝血漿コルチゾール、下流の バイオマーカーバイオマーカーとは、健康や病気の状態について教えてくれる、体内で測定可能なもののことであり、例えば、検査値、スキャン画像の結果、血圧の数値などが挙げられます。., 、心理的ストレスではなく、セクション8.4のコルチゾール因果関係の中で議論されているものであり、ストレス自体の因果的地位には何ら影響を与えない。.
コルチゾールは、HPA系およびグルココルチコイド生理学の非特異的バイオマーカーとして、また生物学的に妥当なメディエーターとして最もよく理解されている。前向き研究および遺伝学的データは、心血管系リスクへのわずかな因果的寄与と矛盾しないが、通常の生理学的範囲内での因果関係は依然として不確実であり、コルチゾールが心理的ストレスの唯一の伝達物質でないことは確かである。 制御異常の枠組み 持続的な血中コルチゾール値の上昇モデルよりも防御可能である。日内変動曲線の平坦化、夕方のコルチゾール値の上昇、反応性の変化、, 糖質コルチコイド受容体抵抗性Glucocorticoid receptor resistance is a state in which cells become less responsive to cortisol's signalling, so the body's ability to regulate inflammation and other stress responses is impaired even when cortisol levels appear normal. The article lists it as one of the HPA dysregulation patterns associated with adverse cardiovascular phenotypes., 、および組織におけるグルココルチコイド代謝の変化のそれぞれが、有害な表現型に関連付けられているが、単一のHPA表現型が決定的な心血管異常として確立されているわけではない―― メタ分析メタアナリシスは、多数の個別研究の結果を統計的に統合して1つの全体的な推定値を算出します。. 80件の研究のうち、より緩やかな傾斜は全体的な健康状態の悪さと関連していることが示された(r = 0.147)一方、変量効果による心血管系サブグループは統計的に有意ではなかった [78]. Whitehall II研究では、平坦な日内変動の傾きが心血管死亡率を予測した(ハザード比ハザード比は、2つのグループでイベントが起こる速さを比較するものです。比率が0.75の場合、治療群でのイベント発生率が4分の一減少し、対照群の4分の3であったことを意味します。. 1.87、95% CI 1.32–2.64)である一方、朝のコルチゾールおよび コルチゾール覚醒反応The cortisol awakening response (CAR) is the sharp rise in cortisol that normally occurs in the 30–45 minutes after waking, and is used as a measure of how well the HPA axis is functioning. The article notes that in Whitehall II the CAR did not predict cardiovascular mortality, whereas a flatter diurnal cortisol slope did. しなかった。LURICにおいて、早朝血清コルチゾールと心血管死亡率との間の単純な関連性(ハザード比1.32)は、従来の危険因子による調整によって消失した(0.97)。.
瞑想は、主観的なストレスを確実に軽減し、血圧をわずかに低下させます。しかし、心筋梗塞、脳卒中、または心血管死を予防するという点については、説得力のある独立した無作為化試験による証拠はありません。 2024年のコクラン・レビュー(無作為化試験81件、参加者6,971名、2021年11月時点の検索結果)によると、心血管系の臨床事象に関するデータを提供した比較は2件のみであった。すなわち、マインドフルネスに基づく介入と非介入対照群との比較(1件の試験、参加者110名; RR 0.94、95%信頼区間 0.37–2.42;確実性が極めて低い)および 超越瞑想Transcendental Meditation (TM) is a specific meditation technique involving the silent repetition of a personally assigned mantra for around 20 minutes twice daily. The article notes that TM is the technique behind the most-cited trial claiming a large reduction in cardiovascular events — a result that weakened substantially under independent reanalysis. 能動的対照群との比較(1件の試験、参加者201名;RR 0.91、95%信頼区間 0.56–1.49;確実性は低い)。 いずれも検出可能な効果は認められなかった。この分析における唯一の中程度の確実性を持つ収縮期血圧の推定値——超越瞑想とアクティブ対照群の比較——は、−2.33 mmHgという最も小さい値であった。.
解釈. 瞑想を含むストレス管理は、主に血圧、心理的幸福、および行動的自己調節の観点から、ガイドラインに基づく心血管予防に対する合理的で低リスクな補助療法である。これは以下の代わりになるものではない 脂質低下脂質低下とは、食事、薬、あるいはその両方によって、血中のアポBを運ぶ有害な粒子を減らすことを意味します。., 、血圧治療、禁煙、血糖コントロール、あるいは身体活動 心臓発作心臓発作は、心筋の一部への血流が遮断され、その筋肉が壊死し始めることで起こります。.,、動脈硬化を逆転させたり、コルチゾールを正常化して 心血管疾患心血管疾患とは、心臓発作、脳卒中、下肢の動脈閉塞など、心臓や血管に関する問題の総称です。.”証拠を超える.
2. 適用範囲、情報源、およびエビデンス評価フレームワーク
2.1 取り組む課題
このレビューでは、8つの疑問を取り上げます。
- 慢性の心理的ストレスは動脈硬化性心血管疾患(ASCVD)のリスクを増加させるか、またどの程度増加させるか?
- その関係が交絡によるものではなく因果関係であるという証拠は、どの程度強力ですか?
- 最も強力な生物学的メカニズムは何ですか 人間 最強の動物実験やin-vitro(試験管内)の証拠とは異なるエビデンスですか?
- コルチゾールは、原因(シソー)、媒介物質(メディエーター)、マーカーのいずれとしての役割を果たしているのか、それともそれらの組み合わせなのか?どのような特定の役割を果たしているのだろうか?
- コルチゾールの上昇自体が病原性を持つのか、それともHPA系(視床下部-下垂体-副腎系)の調節障害の方がより正確なモデルなのか?
- ストレスとASCVD(動脈硬化性心疾患)の関連のうち、どれくらいの割合が血圧や炎症によって仲介されているのか, インスリン抵抗性インスリン抵抗性とは、細胞がインスリンに対して十分に応答しなくなる状態のことであり、そのため膵臓は同じ働きをするためにますます多くのインスリンを分泌し続けなければならなくなります。., 、肥満、睡眠、および行動?
- 瞑想はこれらの中のいずれかを変化させるのでしょうか——そしてエビデンス階層のどのレベルにおいてでしょうか?
- 今日、科学的に正当化できると言えるのは何であり、何が越権行為にあたるのか。
2.2 検索戦略、情報源、および適格基準
デザイン. これは 構造化批判的ナラティブレビュー, 、システマティックレビューではありません。この区別は、レビューが主張できる内容を制限するため、明確に述べられています。つまり、レビューは評価することができます。, 等級GRADE (Grading of Recommendations, Assessment, Development and Evaluations) is a widely used framework for rating the certainty of evidence behind a clinical finding, classifying it as high, moderate, low, or very low based on factors such as study design, risk of bias, consistency, directness, and precision of results., 、およびそれが特定した証拠を解釈することはできるが、文献が網羅的に列挙されていると主張することはできない。.
データベースと日付. MEDLINE/PubMed、Scopus、Embase、およびコクラン・ライブラリー(CENTRALおよびコクラン・システマティック・レビュー・データベース)を検索した。最終検索日は 2026年8月20日. 全文を取得するためにPubMed Centralを使用し、それは ではない treated as an independent bibliographic database. Reference lists and forward citation chaining (Google Scholar) were used to identify additional peer-reviewed studies, particularly for post-2021 meditation trials not covered by the Cochrane search, which closed on 14 November 2021.
Table 1. Search domains, concept strings, and eligibility.
| Review question | Core concept string (adapted per database syntax) | Eligible designs | Principal exclusions |
| Stress → ASCVD outcomes | (“psychological stress” OR “job strainJob strain is a research construct that combines high psychological demands at work with low control over how that work is done, and is one of the most studied occupational stress exposures in cardiovascular epidemiology. The article reports that high job strain is associated with roughly a 20–30% higher risk of coronary heart disease or stroke.” OR “work stress” OR “perceived stress” OR loneliness OR “social isolation” OR “caregiver burden”) AND (myocardial infarction OR “coronary heart disease” OR stroke OR “cardiovascular mortality” OR atherosclerosis) | Prospective cohort前向きコホート研究は、健康な人々を登録し、その特徴を記録し、その後何が起こるかを待って観察する。., IPD meta-analysis, case-control, case-crossover, systematic review | Cross-sectional-only exposure–outcome designs; animal-only |
| Cortisol / HPA → ASCVD outcomes | (cortisol OR “hypothalamic-pituitary-adrenal” OR glucocorticoid OR “cortisol awakening response” OR “diurnal slope” OR “hair cortisol”) AND (cardiovascular OR coronary OR stroke OR mortality OR “coronary 動脈動脈は、心臓から全身へ血液を送り出す血管です。. calcium”) | Prospective cohort, Mendelian randomization, systematic review, natural-experiment (Cushing) | Case reports; exogenous-steroid pharmacology |
| Mechanistic pathways | (stress OR cortisol OR catecholamine) AND (inflammation OR “flow-mediated dilation” OR endothelial OR haematopoiesis OR NLRP3NLRP3 is an alarm system inside immune cells. When it detects something it treats as a threat, it triggers a burst of inflammatory signaling. OR coagulation OR “インスリンInsulin is a hormone made by your pancreas. Its main job is letting sugar move out of your blood and into your cells for fuel. resistance”) | Human experimental, prospective mechanistic cohort, translational studies with human component | Animal-only studies, except where explicitly labelled as such |
| Meditation → outcomes | (meditation OR mindfulness OR MBSR OR “transcendental meditation” OR “stress reduction”) AND (“blood pressure” OR cortisol OR “heart rate variabilityHeart rate variability (HRV) is the natural beat-to-beat variation in the time between heartbeats, and is used as a non-invasive measure of autonomic nervous system balance — higher variability generally reflecting greater parasympathetic (rest-and-digest) activity. It is listed in the article as one of the outcomes measured in meditation trials.” OR inflammation OR “intima-media” OR “cardiovascular events”) | ランダム化比較試験ランダム化比較試験では、人々を完全な偶然によって治療群または比較群に割り付け、その後両群を追跡調査します。.; systematic reviews and meta-analyses of RCTs | Uncontrolled/single-arm studies; non-peer-reviewed material |
Eligibility. Peer-reviewed human studies in any language, any geography, any date. Society scientific statements are cited as consensus positions, explicitly labelled, and never as primary evidence. Non-peer-reviewed material — institutional news releases, magazine coverage, and organizational commentary — was excluded from the evidence base. Where full texts were paywalled, quantitative values were taken from published abstracts and cross-checked across indexing sources; such instances are flagged in Section 29.
What this review does not have. No protocol was prospectively registered. Screening was performed by a single reviewer without duplicate independent screening. Deduplicated record counts and a study-selection flow diagram were not retained, and are therefore not reported here rather than reconstructed retrospectively. Formal instruments (RoB 2, ROBINS-IA standardized tool (Risk Of Bias In Non-randomized Studies of Interventions) used in systematic reviews to rate how susceptible each observational study is to bias; in the Larvin meta-analysis, 21 of 32 included studies were rated at critical risk and the rest at serious risk, with none rated low., AMSTAR-2) were not applied at study level; risk of bias is assessed narratively against named domains. These are material limitations, and Section 2.5 states how they constrain the review’s permissible claims.
2.3 Author-assessed narrative confidence categories
Four categories are used, applied to individual claims rather than to whole literatures. These are author-assessed narrative confidence categories, not GRADE ratings, and they are not interchangeable with GRADE certainty levels even where the words coincide.
| カテゴリー | Criteria |
| Strong | Consistent findings across multiple designs including experimental human data or very large prospective cohorts; effect direction stable under adjustment; plausible mechanism demonstrated in humans |
| 中程度 | Consistent prospective association or reproducible human experimental physiology, but limited by residual 交絡Confounding is when a hidden third factor makes two unrelated things look connected., few events, single-study dependence, or reliance on surrogate endpoints代替評価項目とは、LDLコレステロール、CIMT、冠動脈カルシウムなどの測定可能な生体マーカーであり、治験において心発作などの臨床的転帰の代用として使用されるものである。代替評価項目における好ましい変化はベネフィットの妥当性を裏付けるものではあるが、それ単体では、ある治療法が心発作や死亡を防ぐことを証明するものではない。. |
| Limited | Small, heterogeneous, or conflicting human studies; mechanism established chiefly in animals or cell systems; effect present only in subgroups |
| Inconclusive | No adequately powered, low-bias study addresses the question; existing data are compatible with a range of conclusions including no effect |
To make these assessments auditable rather than impressionistic, every graded claim in Table 9 carries an explicit basis for downgrade, drawn from six named domains: risk of bias, indirectness, imprecision, inconsistency, confounding, そして 出版バイアスPublication bias is the tendency for studies with striking positive results to get published while studies finding nothing quietly disappear..
2.4 Two distinctions that structure the entire review
First: the exposure–outcome tier. Evidence connecting perceived stress へ バイオマーカー is not evidence connecting biomarkers to 危険因子, which is not evidence connecting risk factors to 動脈硬化, which is not evidence connecting atherosclerosis to hard outcomes. Each link must be established separately. The literature routinely borrows credibility across these tiers.
Second: the timescale. Chronic exposure operating over decades and acute triggering operating over minutes are distinct phenomena with distinct evidence bases (Figure 4). An odds ratio of 2.44 for myocardial infarction in the hour after acute anger is a statement about 不安定プラーク破裂するリスクが高いプラークが脆弱性プラークであり、その特徴は、薄い線維性皮膜、大きな脂質コア、活発な炎症、そしてしばしば動脈の外側への突出です。. crossing a clinical threshold; it is not a statement about how the 歯垢プラークとは、動脈の壁の内側にコレステロール、免疫細胞、瘢痕組織、カルシウムが蓄積したものです。. formed. Conflating them inflates the apparent atherogenic effect of stress severalfold.
2.5 What this review may and may not claim
Because the search is structured but not systematic, this review adopts the following self-imposed constraints, and Sections 22 through 28 are written to obey them:
- No unqualified absence claims. Statements that no trial or study exists are rendered as “we identified no…” with the search date attached.
- No claim of exhaustive coverage. The word comprehensive is not used to describe the search.
- Symmetry of scepticism. The evidentiary standard applied to meditation claims is applied equally to stress-causality and cortisol-causality claims. Where the review declines to infer event reduction from a biomarker change in an intervention trial, it likewise declines to infer plaque progression from a biomarker change in an observational cohort.
- Grades are author judgments. They are offered as structured reasoning, with downgrade reasons stated, not as formal certainty ratings.
3. Key Conclusions
- Prospective association is real but modest. Adjusted prospective estimates for several commonly studied psychosocial constructs — job strain, perceived stress, loneliness, social isolation — often fall in the approximate 2–1.3 range for incident coronary heart disease and ischaemic stroke, although individual estimates lie outside this interval in both directions. Estimates around 1.4–1.6 are more common in published-only syntheses, less fully adjusted analyses, and case-control literatures, and should not be presented as the prospective estimate.
- Case-control and case-crossover estimates are larger and mean something different. INTERHEART reported an odds ratio of 17 (99% CI 1.84–2.55) for permanent general stress and a population-attributable risk of approximately 32.5% for the combined psychosocial factor — not for permanent stress alone [1]; the INTERHEART case-crossover analysis reported OR 2.44 (99% CI 2.06–2.89) for myocardial infarction within one hour of anger or emotional upset [9]. Both are informative; neither is a prospective incidence estimate.
- Publication bias is documented, not hypothetical. In the IPD-Work consortium, job strain carried a hazard ratio of 43 (1.15–1.77) in published cohorts versus 1.16 (1.02–1.32) in unpublished ones — unusually direct evidence that publication status was associated with larger reported effects, and a reason to weight the lower figure [3].
- Cortisol is not the whole story and may not be the main story. Circulating cortisol relates to cardiovascular outcomes inconsistently across studies, and the pattern of results tracks the measurement window more closely than it tracks the biology (Figures 2 and 5).
- HPA-axis dysregulation is a more defensible framework than persistent hypercortisolaemia — but “dysregulation” should not be collapsed into one mandatory phenotype. Flattened diurnal slope, elevated late-night cortisol, altered reactivity, and glucocorticoid receptor resistance have each been reported in adverse contexts, but their cardiovascular prognostic meaning is not uniform and rests on cohorts with few cardiovascular events. What the evidence does not support is a general model in which chronic psychological stress reliably produces continuously elevated circulating cortisol.
- Inflammatory and haematopoietic signalling is among the most coherent human mechanistic pathways — more so than cortisol. The amygdala → bone marrow → arterial inflammation → events pathway, demonstrated in a single imaging cohort with 22 events, is in this review’s judgment one of the most integrated brain-to-artery human datasets available — with bone-marrow activity mediating 46% of the amygdala–arterial inflammation relationship and arterial inflammation mediating 39% of the amygdala–event relationship [11].
- Behaviour is part of the causal system, not a nuisance variable. Because chronic distress can contribute to smoking, inactivity, poor sleep, and non-adherence, statistically adjusting these away can understate the total effect of stress — though it does not thereby isolate a direct biological effect, which requires formal mediation analysis.
- Meditation’s evidence weakens sharply from claim A to claim E (Figure 8). Perceived stress: moderate. Cortisol: limited-to-moderate, and confined largely to at-risk samples. Blood pressure: moderate, and smaller than commonly reported once active comparators are used. Atherosclerosis: limited and inconclusive — an early positive cIMT trial had substantial attrition, and a later randomized trial in a different population did not demonstrate a between-group cIMT benefit. Hard events: inconclusive.
- Comparator choice materially influences the answer. In the Cochrane synthesis, every large blood-pressure estimate carries either I² ≥ 87% or fewer than 150 participants; the one moderate-certainty systolic estimate is −2.33 mmHg (Figure 7).
- Researcher allegiance is an important potential source of bias in this literature, particularly in Transcendental Meditation research, where the only trials reporting hard-endpoint benefit originate from a single institutionally affiliated investigator network. This is a reason to require independent replication, not in itself evidence that allegiance produced the reported effects.
4. What Is Established, What Is Probable, and What Is Not Known
Established (strong evidence). Several psychosocial stress constructs are associated with cardiovascular events in prospective and case-control studies, while human imaging and mechanistic studies provide supporting evidence for selected intermediate pathways. Acute mental stress produces reproducible, transient impairment of 血管内皮機能血管の内側を覆う内膜が血管の緊張、炎症、血液凝固を調節する能力。健康な内視細胞は一酸化窒素を放出し、動脈をリラックスさせ、プラーク形成に対する抵抗力を保ちます。. in both healthy adults and patients with coronary disease. Acute emotional stress can trigger 心臓発作心血管系を対象とした臨床試験において、心筋梗塞、不安定狭心症、心臓死などの臨床的に重要な心血管関連事象を評価項目として使用する。. in people who already have disease. Pathological hypercortisolism — Cushing’s syndrome — causes 高血圧Hypertension is the medical term for high blood pressure., dysglycaemia, visceral adiposity, dyslipidaemia, and premature cardiovascular death. Meditation lowers perceived stress and modestly lowers blood pressure. Chronic stress is associated with altered leukocyte biology in humans.
Probable (moderate evidence). A causal contribution of ordinary chronic stress to cardiovascular risk. (Direct human evidence for stress-induced plaque initiation or progression is materially weaker than the evidence for clinical events, blood-pressure pathways, endothelial responses and acute triggering, and is graded Limited–Moderate.) The amygdala–marrow–artery axis. Inflammation as a mediator. Diurnal cortisol dysregulation as a predictor of cardiovascular mortality. Cortisol as a possible causal contributor — genetic evidence is compatible with a small effect but is statistically inconclusive. Behavioural mediation is probably important, but the fraction of the total association attributable to behavioural pathways is not established.
Limited or uncertain. Whether meditation meaningfully changes cortisol outside at-risk populations. Whether meditation slows atherosclerosis. The independent clinical value of any circulating cortisol measure for cardiovascular risk stratification. Whether the specific NLRP3/IL-1β axis mediates psychological-stress effects in humans, as distinct from mediating atherosclerosis generally. The proportional contribution of direct neuroendocrine injury versus indirect behavioural pathways.
Inconclusive. Whether any stress-reduction intervention reduces hard cardiovascular events. We identified no adequately powered, low-bias, independently conducted trial in our search to 20 August 2026. This is the central gap in the field.
5. Stress Physiology: The Architecture of the Response
5.1 Central appraisal
Psychological stress depends not simply on an external input but on the brain’s appraisal of threat, demand, predictability, and coping resources. Threat cues are processed in distributed cortico-limbic circuitry — prefrontal cortex, amygdala, hippocampus, insula — in which prefrontal, limbic, insular and hypothalamic networks jointly regulate threat appraisal and response, with prefrontal regulation able to modulate amygdalar output and contribute to terminating the response once a threat resolves. Chronic psychological adversity is associated with a shift in this balance toward sustained amygdalar activity relative to prefrontal regulation [11,37]. From the amygdala and the hypothalamic paraventricular nucleus, two effector arms descend.
5.2 The sympathetic-adrenal-medullary arm
The SAM axis responds within seconds. Sympathetic outflow and adrenal medullary secretion raise circulating epinephrine and norepinephrine, increasing 心拍数心拍数とは、心臓が1分間に鼓動する回数のことです。., contractility, and peripheral vascular resistance while parasympathetic (vagal) tone is withdrawn. This is often reflected in changes in vagally mediated heart-rate variability, though HRV is also influenced by respiration, posture and recording conditions and is not a one-to-one readout of 迷走神経トーンThe level of activity of the parasympathetic (vagus nerve) branch of the autonomic nervous system acting on the heart; high vagal tone slows the resting heart rate and is generally cardioprotective, but in extreme endurance athletes it has been proposed to contribute to atrial fibrillation risk.. Beyond haemodynamics, catecholamine signalling acts directly on immune and haematopoietic compartments — a point developed in Section 10.
5.3 The hypothalamic-pituitary-adrenal arm
The HPA axis operates over minutes to hours. Paraventricular neurons release corticotropin-releasing hormone and アルギニンArginine is an amino acid found in whole foods such as walnuts that serves as the biochemical precursor the body uses to synthesize nitric oxide, thereby supporting endothelial relaxation and healthy blood vessel dilation. vasopressin into the hypophyseal portal circulation; CRH stimulates pituitary corticotropes to secrete adrenocorticotropic hormone; ACTH binds melanocortin-2 receptors in the adrenal zona fasciculata, driving conversion of コレステロールコレステロールは、体が必要とするロウ状の物質です。細胞壁、ホルモン、ビタミンD、そして食べ物を消化する胆汁の材料となります。コレステロールがなければ私たちは生きていけません。. to cortisol. Cortisol then exerts negative feedback at both hypothalamic and pituitary levels.
Acutely, this is adaptive. Cortisol mobilizes energy substrates, enhances vascular reactivity to catecholamines, and restrains the immune response. The pathological question is never whether these systems activate — they must — but whether repeated activation, failed recovery, altered circadian timing, or altered receptor responsiveness generates sustained allostatic burden.
5.4 Receptor biology: two receptors, not one
Cortisol binds two intracellular nuclear receptors with markedly different affinities:
- その mineralocorticoid receptor (MR, Type I) has high affinity and is substantially occupied at basal cortisol concentrations.
- その glucocorticoid receptor (GR, Type II) has lower affinity and is engaged principally during stress-induced peaks and the morning surge.
This two-receptor architecture matters clinically. Under sustained glucocorticoid excess, renal MR occupancy by cortisol — normally limited by pre-receptor metabolism, below — has been proposed to promote sodium retention, volume expansion and hypertension [30]. This is one described route by which glucocorticoid excess may become a haemodynamic problem.
5.5 Pre-receptor metabolism: the tissue-level amplifier
Circulating cortisol is a poor proxy for the cortisol a given tissue actually experiences, because two enzymes modulate local exposure independently of plasma concentration:
- 11β-HSD1, abundant in liver and visceral adipose tissue, regenerates active cortisol from inactive cortisone. It amplifies intracellular glucocorticoid signalling, gluconeogenesis, and 内臓脂肪See Belly Fat for the full entry. deposition even when plasma cortisol is normal [30].
- 11β-HSD2, expressed in aldosterone-sensitive distal nephron, inactivates cortisol to cortisone, protecting the renal MR from occupancy by cortisol [30].
The practical implication is that a normal serum cortisol does not exclude tissue-level glucocorticoid excess. This is a real limitation on any clinical strategy built around measuring circulating cortisol.
5.6 The circadian architecture
Under unstressed conditions cortisol follows a pronounced circadian rhythm driven by the suprachiasmatic nucleus: a sharp rise peaking roughly 30–45 minutes after waking (the コルチゾール覚醒反応, CAR), a steep decline across the day, and a nadir near midnight (Figure 1A). The rhythm — its amplitude, its slope, and the timing of its nadir — carries information that a single value cannot.
5.7 Why “chronic stress produces high cortisol” is wrong
This is the single most important correction in this review. Chronic stress does ではない reliably produce persistently elevated cortisol. Depending on chronicity, timing, developmental history, and receptor sensitivity, it can produce hypercortisolism, hypocortisolism, a blunted CAR, an exaggerated CAR, or a flatter diurnal slope with elevated late-day or nadir cortisol — phenotypes associated with adverse health outcomes in several cohorts, but without uniformly consistent cardiovascular associations in meta-analysis [78].
Three further observations complete the picture:
Blunted reactivity is not necessarily resilience. Meta-analysis of adverse childhood experiences finds blunted rather than exaggerated cortisol and cardiovascular stress reactivity [40]. Low reactivity in that context reflects dysregulation, not robustness. In MESAMESA, the Multi-Ethnic Study of Atherosclerosis, followed thousands of adults with no known heart disease, scanning their arteries and tracking outcomes., blunted diastolic blood-pressure reactivity to acute stress predicted premature 全因死亡率全死因死亡とは、心疾患に限らず、あらゆる原因による死亡を意味し、研究が測定できる最も広範で、ごまかしが最も効かない結果です。. [42]. Blunted reactivity is therefore not evidence of resilience; but the prognostic implications vary by physiological measure and population, and these data do not establish a general U-shaped rule across HPA and cardiovascular responses.
Glucocorticoid receptor resistance decouples cortisol from its effect. In chronically stressed caregivers, salivary cortisol profiles can resemble those of controls while monocytes show diminished glucocorticoid-responsive transcription, enhanced NF-κB-related transcription, and higher inflammatory markers [14,15]. Multiple molecular mechanisms have been proposed to alter GR sensitivity, including changes in receptor expression, impaired ligand binding and nuclear translocation, co-chaperone regulation of receptor turnover, and epigenetic modification at loci such as FKBP5. Several of these details derive primarily from mechanistic and translational work rather than from direct human cardiovascular experiments [30], and they are listed here as candidate mechanisms rather than as demonstrated steps in a human pathway.
This resolves the central paradox. Cortisol is anti-inflammatory, yet chronic stress is pro-inflammatory. One mechanism that may partly reconcile this is reduced glucocorticoid sensitivity in selected immune-cell populations — the target tissue listening less well. It is a candidate resolution, not a demonstrated universal property of chronic stress. On this account inflammation proceeds not despite adequate cortisol but because adequate cortisol is less effectively transduced — while catecholamine- and sympathetically-driven pro-inflammatory haematopoiesis pushes in the same direction. Chronic inflammation in stressed populations is, however, multifactorial: sleep, adiposity, metabolic state, infection and behaviour all contribute, and glucocorticoid resistance is one contributor among several.
The accurate formulation is therefore stress → HPA-axis dysregulation, not stress → high cortisol.
図1. Diurnal cortisol pattern may be more informative than a single morning level for cardiovascular prognosis. Panel A is a schematic of characteristic phenotypes, not measured data. Panel B reports observed hazard ratios; in Whitehall II, morning cortisol and the cortisol awakening response did not predict mortality.
6. Measuring Cortisol: Matrices, Kinetics, and Interpretive Traps
Part of the apparent inconsistency in the cortisol–ASCVD literature reflects differences in sampling window and matrix rather than biological disagreement — though confounding, disease state, medication, population heterogeneity and analytic choices also contribute [41] (Figure 2).
図2. Cortisol biomarkers measure different things over different timescales. A single morning serum cortisol captures one time point in a system with a pronounced circadian rhythm; part of the inconsistency in this literature reflects that mismatch, alongside genuine biological heterogeneity.
Table 2. Cortisol measurement matrices.
| Matrix | Window captured | 測定するもの | Principal strengths | Principal limitations |
| Serum / plasma, single draw | Single time point | Total cortisol (bound + free) | Widely available; standardized assays | Acutely sensitive to venepuncture stress and sampling time; influenced by corticosteroid-binding globulin; a poor index of chronic exposure |
| Salivary, multi-sample | Hours to a day | Free, biologically active cortisol | Non-invasive; enables CAR and diurnal slope; repeatable | Adherence-dependent; sensitive to waking-time accuracy, food, and smoking |
| 24-hour urinary free cortisol | 1 day | Integrated daily free-cortisol output | Integrates across the day; unaffected by single-timepoint noise | Collection errors common; affected by renal function; one day may not represent chronic state |
| Hair cortisol / cortisone | Weeks to months (conventionally ≈1 cm of proximal scalp hair ≈ 1 month, with substantial biological and assay variability) | Cumulative systemic exposure | A useful longer-term integrated glucocorticoid biomarker, although standardization and clinical interpretation remain incomplete | Affected by hair biology, colour, washing and cosmetic treatment; assay heterogeneity; clinical scaling not established |
Three interpretive consequences follow.
First, a single morning serum cortisol is a weak marker of chronic stress [41], and studies using it should not be treated as testing the same hypothesis as studies using diurnal salivary profiles or hair glucocorticoids. One well-conducted 横断研究A cross-sectional study takes a single snapshot of a population at one moment. found no association between circulating plasma cortisol and coronary or peripheral arterial disease [29] — a finding that constrains the clinical utility of spot cortisol rather than refuting the broader stress hypothesis.
Second, the shape of the reported effect tracks the matrix. In Figure 5, the largest point estimates come from integrated-exposure measures in small cohorts with few events; the most precise estimates come from pooled single-timepoint measures with modest effects. This pattern is compatible with measurement differences and small-study imprecision, including potential small-study inflation or winner’s-curse effects, but does not by itself identify the true causal effect size.
第三に、, cortisone may outperform cortisol in hair. In the Lifelines cohort, hair cortisone — but not hair cortisol — was independently associated with incident cardiovascular disease, most strongly in participants under 60 (odds ratio 4.21, 95% CI 1.91–9.07 per log₁₀ unit) [20]. The finding is biologically interesting and requires replication before any clinical inference.
7. Human Epidemiologic Evidence: Stress Exposures and ASCVD
Figure 3 displays the principal estimates. This section explains what each contributes and where each is weak.
図3. Psychosocial exposures and atherosclerotic cardiovascular outcomes. Study design determines interpretation. Many adjusted prospective estimates for CHD and ischaemic-stroke outcomes fall in the approximate 1.2–1.4 range, although individual prospective estimates lie outside that interval. INTERHEART and INTERSTROKE intervals are 99% CI as reported.
7.1 Case-control evidence: INTERHEART and INTERSTROKE
INTERHEART enrolled 11,119 cases of first myocardial infarction and 13,648 controls across 52 countries. Permanent general stress carried an odds ratio of 2.17 (99% CI 1.84–2.55); several periods of stress, 1.45; financial stress, 1.33; stressful life events, 1.48; depression, 1.55. A high internal locus of control was protective (0.68). Separately, the combined psychosocial factor — not permanent general stress alone — carried a population-attributable risk of approximately 32.5% for myocardial infarction, and the pattern was consistent across regions, sexes, and ethnic groups. The association persisted after adjustment for income and education [1].
INTERSTROKE, using the same architecture for acute stroke, found psychosocial stress at odds ratio 1.30 (99% CI 1.06–1.60) and depression at 1.35 (99% CI 1.10–1.66) [2]. Note that both studies report 99% rather than 95% 信頼区間信頼区間とは、ある研究の結果と統計的に整合する値の範囲のことです。. by design; the intervals are therefore wider than they would otherwise appear.
The limitation is structural and unavoidable. In a case-control studyA case-control study starts with people who already have a disease, finds similar people who do not, and looks backward for differences. of myocardial infarction, stress exposure is ascertained after the event, from people who have just had a heart attack and are searching for an explanation. Post-event ascertainment creates potential for differential recall that could inflate associations, although its direction and magnitude cannot simply be assumed. INTERHEART’s consistency across 52 countries strengthens generalizability, but cross-regional consistency does not eliminate differential recall. A well-designed case-control study can validly estimate an exposure odds ratio, and with incidence-density sampling that odds ratio estimates an incidence-rate ratio. What the design does not do is directly measure population incidence, and it remains vulnerable to differential retrospective exposure ascertainment. This is why the 2.17 figure, though frequently quoted, should not anchor the reader’s sense of magnitude.
7.2 Occupational strain
その IPD-Work consortium pooled individual participant data from 13 European cohorts: 197,473 initially disease-free workers, 2,358 incident coronary events, mean 7.5 years of follow-up. Job strain — high psychological demand combined with low decision latitude — carried a hazard ratio of 1.23 (95% CI 1.10–1.37), with a population-attributable risk of roughly 3.4% [3].
Two features of this analysis are more instructive than the headline number.
First, a point of precision usually lost in secondary citation: the headline hazard ratio of 1.23 is adjusted for sex and age only. The consortium reported separately that the association was also present after adjustment for socioeconomic status and for lifestyle and conventional risk factors, and in analyses excluding events occurring in the first three years (HR 1.31, 1.15–1.48) and five years (HR 1.30, 1.13–1.50) of follow-up to address 逆因果関係Reverse causation is when the arrow points the other way — the illness caused the exposure rather than the exposure causing the illness.. The effect is robust across specifications, but the widely quoted 1.23 should not be described as fully risk-factor-adjusted.
Second, and more valuable, the consortium compared previously published with previously unpublished cohorts. The hazard ratio in previously published cohorts was 1.43 (1.15–1.77); in previously unpublished cohorts it was 1.16 (1.02–1.32). This provides unusually direct evidence that publication status was associated with effect-size differences within a single consortium — though the contrast may also reflect factors correlated with publication status rather than publication bias alone. It is also specific to the job-strain corpus and should not be assumed to hold at the same magnitude in other stress literatures. It may nonetheless help explain part of the discrepancy between reviews reporting 1.2–1.4 and those reporting 1.4–1.6 — the latter are, in substantial part, reading the published literature at face value.
The opposite criticism has also been made, and should be recorded. Published correspondence argued that the constituent cohorts carry unacknowledged biases toward the null — single-occasion exposure measurement, healthy-worker selection, and loss of exposure contrast across follow-up — such that both 1.23 and the 3.4% population-attributable risk may themselves be underestimates [71,72]. The consortium replied defending its estimates [73]. This review does not adjudicate between the two critiques. It notes that the point estimate is bracketed by credible arguments in both directions, which is a further reason to treat 1.2–1.4 as a range rather than a measurement.
For stroke, the meta-analytic estimate was RR 1.22 (1.01–1.47) overall and 1.58 (1.12–2.23) for ischaemic stroke, while the more conservative individual-participant analysis gave HR 1.09 (0.94–1.26) for total stroke and 1.24 (1.05–1.47) for ischaemic stroke [4,5]. The ischaemic-specific signal is the more consistent of the two.
7.3 Perceived stress
Pooling six prospective cohorts and 118,696 participants, high perceived stress carried a risk ratio of 1.27 (95% CI 1.12–1.45) for incident coronary heart disease [6]. The exposure instruments varied across studies, which limits precision but also means the finding is not an artefact of one questionnaire.
7.4 Loneliness and social isolation
Across 16 longitudinal datasets and more than 181,000 adults, loneliness and social isolation carried RR 1.29 (1.04–1.59) for coronary heart disease and RR 1.32 (1.04–1.68) for stroke [7]. These estimates sit within the same band as job strain and perceived stress despite measuring a conceptually distinct exposure. That supports a broader psychosocial-risk association, but similarity between distinct constructs does not by itself constitute causal replication or imply a shared mechanism.
7.5 Caregiver strain
In the Caregiver Health Effects Study, 392 spousal caregivers aged 66–96 were followed alongside 420 non-caregiving controls. Caregivers reporting mental or physical strain had a 63% higher four-year all-cause mortality (RR 1.63, 95% CI 1.00–2.65) after adjustment for age, sex, health status, and subclinical disease [8]. The lower confidence bound touches 1.00, and the outcome is all-cause rather than cardiovascular mortality; the study is best read as corroborating rather than as independently establishing.
7.6 Acute triggering
その INTERHEART case-crossover analysis of 12,461 first myocardial infarctions found that anger or emotional upset in the preceding hour was associated with OR 2.44 (99% CI 2.06–2.89), with a population-attributable risk of 8.5% [9]. The within-person design controls for time-invariant 交絡因子A confounder is a variable that is associated with both the exposure being studied (such as TMAO) and the outcome (such as heart disease), making it appear as though one causes the other when a third factor is actually responsible. The article lists renal function, insulin resistance, systemic inflammation, and age as major confounders that inflate the apparent cardiovascular risk of high TMAO in… — 遺伝学Genetics is the study of what you inherit from your parents., socioeconomic position, chronic behaviour — which is a substantial methodological advantage over cohort designs. It does not control time-varying confounders, nor differential recall of what occurred during the hazard period.
But it answers a different question. The comparison is between one hour and another hour in the same person, whose coronary anatomy is identical in both. It establishes that a transient physiological state can precipitate an event in existing disease. It says nothing about アテローム発生アテローム性動脈硬化形成は、プラークが形成される段階的なプロセスです。.. Related evidence — takotsubo 心筋症Cardiomyopathy is disease of the heart muscle itself, rather than of the arteries feeding it., population spikes in cardiac events after earthquakes and during emotionally charged sporting events, case-crossover data on anger and heavy exertion — belongs to this same category (Figure 4).
Figure 4. Two distinct timescales that are routinely conflated. Acute triggering is evidence that a transient physiological state can push pre-existing disease across the clinical threshold; it is not evidence that stress builds plaque.
7.7 Synthesis
Table 3. Human epidemiologic evidence linking stress exposures to ASCVD outcomes.
| 勉強 | Design / N | Exposure | Outcome / follow-up | Effect (95% CI unless noted) | Key limitation | Grade |
| INTERHEART, 2004 | Case-control; 24,767; 52 countries | Self-reported permanent stress, financial stress, life events | Acute MI | OR 2.17 (99% CI 1.84–2.55) permanent stress; combined psychosocial PAR ≈32.5% | Recall bias inherent to design | 中程度 |
| INTERSTROKE, 2010 | Case-control; 22 countries | Psychosocial stress; depression | Acute stroke | OR 1.30 (99% CI 1.06–1.60); depression 1.35 (1.10–1.66) | Same design limitation | 中程度 |
| IPD-Work, 2012 | IPD meta-analysis, 13 cohorts; 197,473; 2,358 events | Job strain (demand–control) | Incident CHD; mean 7.5 y | HR 1.23 (1.10–1.37); PAR ≈3.4% | Published cohorts 1.43 vs unpublished 1.16 | 中程度 |
| Huang et al., 2015 | Meta-analysis, 6 cohorts; 138,782 | Job strain | Incident stroke | RR 1.22 (1.01–1.47) total; 1.58 (1.12–2.23) ischaemic | Fewer cohorts; heterogeneous ascertainment | 中程度 |
| Fransson et al., 2015 | IPD meta-analysis | Job strain | Incident stroke | HR 1.09 (0.94–1.26) total; 1.24 (1.05–1.47) ischaemic | Null for total stroke | 中程度 |
| Richardson et al., 2012 | Meta-analysis, 6 cohorts; 118,696 | Perceived stress scales | Incident CHD | RR 1.27 (1.12–1.45) | Instrument heterogeneity | 中程度 |
| Valtorta et al., 2016 | Meta-analysis, 16 datasets; >181,000 | Loneliness / social isolation | CHD and stroke | RR 1.29 (1.04–1.59) CHD; 1.32 (1.04–1.68) stroke | Exposure definition varies | 中程度 |
| Schulz & Beach, 1999 | Prospective cohort; 812 | Caregiver strain | 4-y all-cause mortality | RR 1.63 (1.00–2.65) | All-cause outcome; CI touches null; no biomarkers | 中程度 |
| INTERHEART trigger, 2016 | Case-crossover; 12,461 MI cases | Anger / upset in prior hour | MI onset | OR 2.44 (99% CI 2.06–2.89); PAR 8.5% | Post-MI recall; triggering ≠ atherogenesis | Moderate–Strong for triggering |
The synthesis is straightforward, with its scope stated. For several prospectively studied psychosocial constructs and CHD or ischaemic-stroke outcomes, adjusted estimates commonly fall in the approximate 1.2–1.4 range. That statement does not extend to every prospective entry in Table 3 — total stroke in the IPD analysis was 1.09, and the caregiver estimate of 1.63 is for all-cause mortality. They are directionally robust, replicated across exposures and populations, and consistent enough that sampling variation alone is unlikely to explain the pattern. They are also modest, vulnerable to residual confounding by socioeconomic position and behaviour, and, in the occupational literature, published cohorts produced materially larger estimates than unpublished cohorts.
A caution on calibration: it is tempting to rank this magnitude against smoking, established hypertension, or cumulative apoB exposure, but relative effects estimated on different exposure scales, over different induction periods, and by different designs are not directly commensurable. What can be said is that job strain’s population-attributable risk in IPD-Work was approximately 3.4%, which the investigators themselves described as substantially smaller than that of standard risk factors [3] — a comparison made within a single analysis rather than across literatures.
8. Cortisol and ASCVD: Cause, Mediator, or Marker?
Figure 5 arrays the principal estimates. What follows is the case for each interpretation and the resolution.
Figure 5. Cortisol measures and cardiovascular outcomes. Because exposure scales, cortisol matrices and outcomes differ, point estimates should not be compared quantitatively across rows. Estimates in grey cross the null. The largest point estimates come from the studies with the fewest events and the widest confidence intervals.
8.1 Diurnal rhythm
Whitehall II followed 4,047 civil servants for a mean of 6.1 years (139 deaths, 32 cardiovascular). A flatter diurnal cortisol slopeThe diurnal cortisol slope is the rate at which cortisol falls from its morning peak to its evening low over the course of a day. A flatter slope — meaning cortisol stays too high into the evening — has been associated in some studies with worse cardiovascular outcomes, including cardiovascular mortality in the Whitehall II cohort. predicted all-cause mortality (HR 1.30 per 1 SD reduction in slope steepness, 95% CI 1.09–1.55) and, more strongly, cardiovascular death (HR 1.87, 95% CI 1.32–2.64), independent of covariates. Morning cortisol and the CAR did ではない predict mortality [16]. This is an influential prospective observation: within a single well-characterized cohort, the rhythm predicted and the level did not. It rests on 32 cardiovascular deaths and requires replication.
KORA-F3 followed 1,090 participants for approximately 11 years (31 cardiovascular deaths) and found the same pattern from the other direction. A more pronounced CAR was associated with 下げる cardiovascular mortality (HR 0.59, 95% CI 0.36–0.96), as was a greater peak-to-bedtime ratio (HR 0.50, 0.34–0.73), while high late-night cortisol was associated with もっと高く cardiovascular mortality (HR 1.49, 1.13–1.97). Preserved diurnal variability appeared protective [17].
イン coronary artery bypass patients, a steeper pre-surgical diurnal slope was protective for MACE and death (HR 0.73, 95% CI 0.56–0.96 per unit steeper) [18].
A broader synthesis provides an important qualification. A 2017 systematic review and meta-analysis of 179 associations from 80 studies found flatter diurnal cortisol slopes associated with poorer health overall (average r = 0.147), with significant associations in 10 of 12 outcome subtypes — including mortality, and largest for immune and inflammatory outcomes (r = 0.288). The cardiovascular-disease symptoms and diagnoses subgroup was not statistically significant in the random-effects model (r = 0.098, 95% CI −0.034 to 0.226) [78]. The cardiovascular-specific evidence is therefore suggestive rather than uniformly consistent, and this qualifies — rather than contradicts — the positive cardiovascular-mortality findings above.
Across the three cohorts, more preserved diurnal organization was generally associated with better outcomes, whereas amplitude at any single point was not. The measures and estimands nonetheless differ between studies, and the caveat is shared and serious: all three had few cardiovascular deaths — 32, 31, and a modest event count respectively — with correspondingly wide confidence intervals. Taken together, these data favour studying diurnal organization rather than relying on a single morning value, but they do not establish one prognostically validated cardiovascular HPA phenotype.
8.2 Integrated output
イン InCHIANTI, 861 adults aged 65 and over were followed for a mean 5.7 years. Twenty-four-hour urinary cortisol in the highest tertile carried HR 5.00 (95% CI 2.02–12.37) for cardiovascular mortality — but on only 41 cardiovascular deaths, with a confidence interval spanning a sixfold range, in an elderly cohort, from a single baseline collection [19]. Two features argue against the most obvious alternative explanations: the association was specific to cardiovascular rather than non-cardiovascular mortality, and it was consistent in participants with and without cardiovascular disease at baseline (p for interaction = 0.78), which constrains reverse 因果関係Causation means one thing actually makes another thing happen. It is different from correlation, which only means two things tend to show up together. [19]. The imprecision nonetheless remains severe, and the point estimate should never be quoted without its interval.
の Lifelines cohort (6,341 hair samples; cortisone in 4,701), hair cortisone independently predicted incident cardiovascular disease, with the association concentrated in participants under 60 (OR 4.21, 95% CI 1.91–9.07 per log₁₀ unit). The scaling is difficult to translate clinically, and elevated hair glucocorticoids are not proof that psychological stress produced them [20].
Against this, a cross-sectional path analysis found that path coefficients through standard modifiable risk factors — hypertension, dyslipidaemia, 糖尿病糖尿病は、体が十分なインスリンを作らないか、あるいは作られたインスリンに反応しなくなることで、血糖値が常に高すぎる状態になる疾患です。. — accounted for much of the statistical association between hair cortisol and 冠動脈疾患冠状動脈疾患は、心筋に栄養を送る動脈にプラークが蓄積する病気です。. [21]. Temporal mediation cannot be inferred from a cross-sectional design: exposure, putative mediator and outcome were measured at a single time point, so the ordering that the word mediation implies is assumed rather than observed. The result is consistent with cortisol acting through conventional risk factors, but it is equally consistent with reverse ordering or with shared upstream determinants.
8.3 Reactivity and subclinical atherosclerosis
Whitehall II also tested whether acute cortisol reactivity to standardized laboratory stressors predicted structural disease. Among 466 civil servants without known coronary disease, coronary artery 石灰化石灰化とは、カルシウムがプラークに沈着し、その一部が硬く骨状になることです。. progression (Agatston increase >10) occurred in 38.2% over three years, and heightened cortisol stress reactivity independently predicted it (OR 1.27, 95% CI 1.02–1.60 per SD) after adjustment for age, sex, baseline CAC, employment grade, smoking, blood pressure, BMI, fibrinogen, and スタチンスタチンは、肝臓がコレステロールを作るのに使う酵素の働きを遅らせます。肝臓は血液中からより多くのコレステロールを取り除くことでこれに反応し、そこに真の利益があります。. use [22]. This is one of the few studies in the field connecting a stress-physiology measure to a structural endpoint with adequate adjustment, and it is graded accordingly.
その MESA Stress Study produced a more mixed picture. Among 464 participants in the coronary calcium analysis and 610 in the ankle-brachial index analysis, salivary diurnal cortisol parameters showed weak or inconsistent associations with both, and the investigators described their own findings as providing only weak support for a link between cortisol and 無症候性動脈硬化症Subclinical atherosclerosis means plaque is present but has not yet caused any symptoms or events.. In a later MESA analysis of 918 participants, 12-hour urinary cortisol was not associated with cardiovascular events overall. Higher cortisol was associated with greater coronary calcium progression in women but not men, and event associations varied by waist-to-hip ratio, with significant effect modification in women [23,24]. The inconsistency across matrices within a single cohort is itself informative and reinforces Section 6.
8.4 Genetic evidence
Two-sample Mendelian randomization using single-nucleotide polymorphisms at the SERPINA6/SERPINA1 locus on chromosome 14 — which govern corticosteroid-binding globulin and thereby morning plasma cortisol — provides an additional genetic causal-inference test.
The observational meta-analysis in the same investigation gave OR 1.18 (1.06–1.31) per SD of morning plasma cortisol for incident cardiovascular disease. The MR estimate across 122,737 coronary heart disease cases and 547,261 controls gave OR 1.06 (95% CI 0.98–1.15) per SD [25].
How to read this honestly. The genetic point estimate is directionally concordant with the observational estimate, but its confidence interval includes no effect and therefore does not distinguish a small causal effect from the null. Related work at the same locus, examining hepatic CBG expression and tissue gene expression, provides additional support for a causal contribution to ischaemic heart disease [26]. Two caveats are decisive. First, the instruments explain only about 0.5% of morning cortisol variance, which limits 統計的検出力Statistical power is a study's ability to detect a real effect if one exists. It depends mostly on how many events occur. and the precision of the causal estimate; this is a matter of power rather than of instrument strength statistics, and the analysis should be described that way rather than as a “weak-instrument” result per se. Second, instrument validity is complicated by the biology of the SERPINA6/SERPINA1 locus itself: variants governing corticosteroid-binding globulin have been associated with other cardiometabolic traits, raising the possibility of horizontal pleiotropy [26]. The correct conclusion is that genetic data are compatible with a small causal contribution, and equally compatible with none.
8.5 The experiment of nature
Endogenous Cushing’s syndrome provides strong natural-experiment evidence for the cardiovascular toxicity of sustained pathological glucocorticoid excess: central 肥満肥満とは、健康に影響を及ぼすほど過剰な体脂肪を蓄えている状態を意味します。., diabetes, hypertension, dyslipidaemia, and premature death, with a standardized mortality ratio of 3.0 (95% CI 2.3–3.9; I² = 80.5%) and atherosclerotic disease with thromboembolism the leading cause of death (43.4%), ahead of infection (12.7%) and malignancy (10.6%). Notably, excess risk persists after biochemical remission — the standardized mortality ratio is 5.7 in active Cushing disease but remains elevated at 2.3 in remission — implicating cumulative prior exposure rather than concurrent hormone level — an idea structurally analogous to cumulative apoB exposure [28].
The generalization must be resisted. Cushing’s syndrome involves cortisol concentrations far outside the range produced by chronic psychological stress. It establishes that the hormone 缶 cause cardiovascular disease at sufficient dose. It does not establish that ordinary chronic stress reaches that dose, and the evidence in Sections 5.7 and 8.1 suggests it usually does not.
8.6 The null and attenuated studies
Any honest account must weight the negative results equally.
LURIC followed 3,052 patients undergoing coronary angiography for a median 9.9 years. Baseline morning serum cortisol in the highest versus lowest quartileOne of four equal groups into which a population is divided when ranked by a measured variable; the article reports that individuals in the lowest fitness quartile had dramatically higher mortality than those in higher quartiles. initially predicted cardiovascular mortality (HR 1.32, 95% CI 1.04–1.67). After multivariable adjustment for age, sex, BMI, smoking, hypertension, diabetes, lipids, and coronary disease severity, the association was completely abolished (HR 0.97, 95% CI 0.76–1.25) [27].
This result admits two readings, and they are not equivalent. The mediation reading holds that cortisol acts through those risk factors, so adjusting for them is over-adjustment that removes real effect. The confounding reading holds that the crude association was never independent. LURIC alone cannot distinguish them. But the practical clinical implication is similar under either reading: morning serum cortisol was not independently associated with cardiovascular mortality after multivariable adjustment in established coronary disease. Note that the study did not perform formal incremental discrimination or 再分類心血管リスク評価において、「再分類」とは、CACスキャンやApoB測定などの追加検査により、患者があるリスクカテゴリーから別のリスクカテゴリーへと移行し、標準的なリスク計算ツールだけでは引き起こされなかった治療方針の変更につながるプロセスを指します。. analyses, so “adds no predictive value” is a stronger statement than the data support; what they support is the absence of an independent association.
Separately, a cross-sectional study found no association between circulating plasma cortisol and coronary or peripheral arterial disease [29], reinforcing that a single-timepoint measure is a weak marker.
8.7 Verdict
Table 4. Cortisol and cardiovascular outcomes.
| 勉強 | Design / N | Cortisol measure | 成果 | Effect (95% CI) | Grade |
| Whitehall II, 2011 | Prospective; 4,047; 32 CV deaths | Multi-sample salivary diurnal slope | CV mortality; 6.1 y | HR 1.87 (1.32–2.64) per SD flatter; morning cortisol and CAR null | 中程度 |
| KORA-F3, 2022 | Prospective; 1,090; 31 CV deaths | Salivary CAR, peak:bedtime, late-night | CV mortality; ≈11 y | CAR 0.59 (0.36–0.96); peak:bedtime 0.50 (0.34–0.73); late-night 1.49 (1.13–1.97) | 中程度 |
| Ronaldson et al., 2015 | Prospective, CABG patients | Pre-surgical diurnal slope | MACE and death | HR 0.73 (0.56–0.96) per unit steeper | 中程度 |
| InCHIANTI, 2010 | Prospective; 861; 41 CV deaths | 24-h urinary cortisol | CV mortality; 5.7 y | Highest tertile HR 5.00 (2.02–12.37) | Moderate, imprecise |
| Lifelines, 2024 | Prospective; 6,341 hair samples | Hair cortisol / cortisone | Incident CVD; 5–7 y | Age <60: OR 4.21 (1.91–9.07) per log₁₀ cortisone | 中程度 |
| Stomby et al., 2022 | Cross-sectional path model | Hair cortisol | Coronary artery disease | Path coefficients through standard risk factors account for much of the association; temporal ordering not observed | Limited for mediation |
| Hamer et al. (Whitehall II), 2012 | Prospective; 466 | Salivary cortisol reactivity to lab stress | CAC progression; 3 y | OR 1.27 (1.02–1.60) per SD | Moderate–Strong |
| Hajat et al., 2013 (MESA) | Prospective; 464 (CAC), 610 (ABI) | Salivary diurnal cortisol | CAC, ABI | Weak and inconsistent associations | 中程度 |
| Flynn et al., 2023 (MESA) | Prospective; 918 | 12-h overnight urinary cortisol | CVD events; CAC progression | No overall CVD-event association; greater CAC progression in women; waist-to-hip-ratio interaction for events | 中程度 |
| Crawford et al., 2019 | Nested cohorts + meta-analysis | Morning plasma cortisol | Incident CVD | Pooled OR 1.18 (1.06–1.31) per SD | 中程度 |
| Crawford et al., MR | Two-sample MR; 122,737 cases | Genetically predicted morning cortisol | CHD | OR 1.06 (0.98–1.15) per SD | Limited–Moderate; low variance explained (≈0.5%), imprecise estimate, potential locus pleiotropy |
| LURIC, 2021 | Prospective; 3,052; median 9.9 y | Morning serum cortisol, quartiles | CV mortality | Crude HR 1.32 (1.04–1.67); adjusted 0.97 (0.76–1.25) | 中程度 |
| Limumpornpetch et al., 2022 | Meta-analysis of cohorts | Endogenous Cushing’s syndrome | All-cause mortality | SMR 3.0 (2.3–3.9), I² = 80.5%; atherosclerotic disease and thromboembolism 43.4% of deaths; SMR 2.3 in remission vs 5.7 active | Strong for extreme exposure; not generalizable |
| Reynolds et al., 2009 | Cross-sectional | Circulating plasma cortisol | CAD, PVD | No association | Moderate (null) |
The resolution. Cortisol is a biomarker and a plausible mediator; a small causal contribution remains possible but unproven. Its role differs by exposure, population, and measure. It is a biomarker of HPA and glucocorticoid physiology — albeit a nonspecific one, influenced by circadian phase, binding タンパク質タンパク質は、体内の筋肉や組織の構築と修復に使用される栄養素です。., illness, medication, sleep, assay and matrix, and therefore not specific to psychological stress. It is plausibly a mediator, though the supporting path analysis is cross-sectional and cannot establish temporal ordering [21]. A small causal contribution remains possible on genetic evidence that is directionally concordant but statistically inconclusive, and on the Cushing’s literature, which establishes causality only at an exposure range that ordinary chronic stress does not reach.
What cortisol is ではない is the unique causal transmitter of psychological stress to the artery. The simultaneous activation of sympathetic and immune systems, the decoupling introduced by glucocorticoid receptor resistance, the tissue-level amplification by 11β-HSD1, and prospective evidence suggesting that diurnal pattern may be more informative than isolated levels together make a cortisol-centric model untenable.
Clinically, this has one clear implication, developed in Section 25: do not order cortisol testing for cardiovascular risk stratification. It remains a research tool outside of suspected Cushing’s syndrome.
9. Mechanism I: Autonomic and Haemodynamic
Chronic sympathetic overactivity with reduced vagal tone raises resting heart rate, exaggerates blood-pressure reactivity, and promotes hypertension, vasoconstriction, and arterial stiffnessArterial stiffness is a measure of how much an artery's wall resists expansion with each pulse of blood; it increases with age as elastin is lost and collagen accumulates, and manifests clinically as a rising systolic blood pressure alongside a falling or stable diastolic blood pressure after about age 60.. Each of these is an established atherogenic input, and hypertension in particular is a proven causal risk factor with an unambiguous randomized-trial evidence base of its own.
This is the pathway with the best combination of plausibility and human support, for a reason that is easy to overlook: the terminal step is already proven. One does not need to demonstrate that hypertension causes atherosclerosis; that is known. What remains to be demonstrated is that stress meaningfully contributes to blood-pressure burden. Prospective work linking cortisol responses to mental stress with incident hypertension supports the first half of that chain [74]. The argument is not complete on those terms alone: establishing a stress → hypertension → ASCVD causal pathway additionally requires evidence that stress alters sustained blood-pressure burden and that this pathway mediates a specifiable share of subsequent disease. Neither has been quantified.
Repeated pressor and flow changes also increase mechanical loading of the arterial wall and may alter local haemodynamic stresses at atherosclerosis-prone sites such as bifurcations, where local shear patterns are determined substantially by arterial geometry. Higher circulating norepinephrine and epinephrine concentrations are associated with higher cardiovascular risk in pooled observational data (norepinephrine RR 1.68, 1.37–2.06; epinephrine RR 1.58, 1.10–2.26), though circulating catecholamine concentration is an imperfect proxy for regional sympathetic nerve activity [10].
Grade: Moderate–Strong.
10. Mechanism II: Inflammation and Immunity
This is the mechanistically richest pathway in the human literature, and the one where translational evidence is strongest.
10.1 Acute stress produces measurable immune signalling
In a systematic review and meta-analysis of laboratory psychological stress, acute stressors increased IL-1β (d ≈ 0.66), IL-6Interleukin-6, or IL-6, is a signaling molecule the immune system uses to spread an inflammatory message through the body. (d ≈ 0.35), IL-10 (d ≈ 0.69), and TNF-α (d ≈ 0.28), with IL-6 responses growing larger at later sampling points consistent with the known kinetics of cytokine production [13].
This matters more than its effect sizes suggest. Controlled laboratory paradigms use within-person pre–post contrasts, which removes many stable between-person confounders and shows that acute psychological stress can induce measurable inflammatory change in humans [13]. It therefore argues against explaining stress–inflammation associations entirely by lifestyle differences between people — though it does not abolish confounding, since baseline characteristics can still modify both the resting state and the magnitude of response, and the included studies are not uniformly randomized.
10.2 Glucocorticoid receptor resistance
As developed in Section 5.7, chronically stressed humans can show reduced glucocorticoid-responsive transcription and enhanced NF-κB-related transcription in monocytes without any obvious excess of daily cortisol secretion. This provides one plausible human mechanistic explanation for the anti-inflammatory-hormone paradox [14,15].
Grade: Moderate for the mechanism; Limited for its quantified contribution to ASCVD outcomes. No study has shown how much plaque is attributable to glucocorticoid resistance.
10.3 The amygdala–marrow–artery axis
A particularly influential integrative human study imaged 293 patients with ¹⁸F-FDG PET/CT and followed them for a median of 3.7 years, during which 22 had a cardiovascular event.
Resting amygdalar metabolic activity was associated with bone-marrow activity (r = 0.47, p < 0.0001), arterial inflammation (r = 0.49, p < 0.0001), and cardiovascular events (standardized HR 1.59, 95% CI 1.27–1.98, p < 0.0001), and remained significant after multivariable adjustment. Serial mediation analysis was consistent with an amygdala → bone marrow → arterial inflammation → event pathway: bone-marrow activity accounted for a reported 46% of the amygdala–arterial inflammation relationship and arterial inflammation for 39% of the amygdala–event relationship. These are observational mediation estimates derived from 22 events and should be read as hypothesis-generating rather than as a precise causal decomposition.
A separate cross-sectional psychometric substudy found perceived stress associated with amygdalar activity (r = 0.56, p = 0.049), arterial inflammation (r = 0.59, p = 0.035), and CRP (r = 0.83, p = 0.021) [11].
Three caveats are essential, and they are frequently omitted. First, the psychometric substudy had n = 13; correlations of 0.83 in a sample of thirteen are not stable estimates. Second, the longitudinal cohort had 22 events — enough for a hazard ratio, not enough for confident mediation decomposition. Third, the study is observational; stress was never manipulated. It is a single, well-conducted, blinded-adjudication study establishing an important mechanistic association, and it requires replication.
The translational complement comes from work showing monocytosis and neutrophilia in chronically stressed medical residents, coupled with murine experiments in which chronic stress activated β3-adrenergic signalling in the bone-marrow niche, reduced CXCL12, stimulated haematopoietic progenitor proliferation, and accelerated inflammatory plaque features. The detailed β3/CXCL12 causal chain is animal evidence. The human contribution is the upstream observation of stress-related leukocytosis. These should not be reported as a single seamless finding [12].
Grade: Moderate.
10.4 The NLRP3 qualification
NLRP3/IL-1β biology is clearly relevant to atherosclerosis, and higher NLRP3 expression in subcutaneous adipose tissue correlates with angiographic coronary atherosclerosis severity in humans, in a study that did not assess psychological stress [44]. However, the specific chain psychological stress → NLRP3 activation → human coronary events has not been demonstrated with anything like the strength of stress → IL-6/CRP or stress → 内皮機能障害血管内皮機能障害とは、その薄い内側の裏打ちが十分に機能しなくなる状態です。血管が適切に拡張せず、バリア機能がより漏れやすくなります。.. Direct stress–NLRP3 experiments remain disproportionately animal or cellular.
Calling NLRP3 an established human mediator of stress-induced ASCVD would exceed the evidence. Grade: Limited for stress-specific mediation.
10.5 Is inflammation itself a modifiable causal node?
This question can be answered with randomized evidence, which is unusual in this review. A 2025 systematic review and meta-analysis pooling 37,056 individuals across 32 randomized trials found that anti-inflammatory therapies targeting the NLRP3/IL-1β/IL-6/CRP pathway reduced myocardial infarction (RR 0.85, 95% CI 0.78–0.93) and coronary 血行再建術血行再建術とは、閉塞または狭窄した冠動脈の血流を回復させるために行われる医療または外科的処置(冠動脈バイパス術や経皮的冠動脈インターベンションなど)であり、根底にあるアテローム性動脈硬化のプロセスではなく、物理的な閉塞に対処するものである。. (RR 0.80, 0.74–0.86), but did ではない significantly reduce overall 主要心血管イベント主要心血管イベント、またはMACEとは、心血管死、心筋梗塞、脳卒中など、研究においてまとめて集計される有害な転帰のグループのことである。., stroke, or mortality [43].
The interpretation is precise: these randomized data support selected inflammatory pathways as modifiable causal contributors to some coronary outcomes. Pharmacologic interruption of this pathway reduces some outcomes and not others, which supports the causal relevance of inflammation to selected coronary endpoints. It does ではない, however, quantify how much stress-related risk is mediated by inflammation, and it should not be read as a ceiling on what an upstream behavioural intervention could achieve: such an intervention could act simultaneously through blood pressure, autonomic regulation, sleep, behaviour, metabolism and endothelial function, and differs from a targeted drug in specificity, 固守服薬遵守とは、処方されたとおりに日々、実際に薬を服用することを意味します。. and off-target profile.
11. Mechanism III: Endothelial and Vascular
11.1 Acute mental stress impairs endothelial function
In landmark human experimental work, acute mental stress tasks — competitive mental arithmetic, public speaking — induced transient endothelial dysfunction in healthy individuals, with brachial artery flow-mediated dilation falling significantly from baseline at 30 and 90 minutes post-stress and requiring up to four hours to recover [31]. This has been demonstrated experimentally in more than one human laboratory, using different stressors and vascular beds [31,76], and constitutes strong experimental human physiology.
11.2 It has prognostic value
The more important finding is that this response predicts outcomes. In 569 patients with coronary artery disease, mean FMD fell from 4.8% before a public-speaking stress task to 3.9% afterward; 63.3% developed stress-induced endothelial dysfunction. Over a median 3.0 years, 74 major adverse cardiovascular events occurred, and stress-induced endothelial dysfunction was associated with subdistribution HR 1.78 (95% CI 1.15–2.76). Each one-percentage-point stress-related decrease in FMD carried sHR 1.15 (1.03–1.27) [32].
A separate ischaemic heart disease cohort found that each SD worse stress-induced endothelial response predicted MACE with HR 1.35 (1.07–1.71), with impaired microvascular stress responses appearing especially prognostic in women — suggesting the cardiovascular consequences of stress may differ by sex and vascular compartment [33].
Grade: Moderate–Strong. This is a reproducible human experimental effect with demonstrated prognostic value in the population of clinical interest.
11.3 Molecular mechanism: what is human and what is not
A largely translational molecular model proposes the following: sympathetic activation stimulates the renin–angiotensin–aldosterone system and upregulates angiotensin II type 1 receptor (AT₁R) signalling in 内皮細胞すべての血管の内面を覆う薄い細胞層であり、血管緊張の調節、血液凝固の防止、および動脈壁への物質の通過の制御を行います。また、その機能障害はアテローム性動脈硬化における初期の極めて重要な段階です。.; AT₁R activation stimulates NADPH oxidase, generating superoxide; superoxide reacts with 一酸化窒素一酸化窒素は、血管の内壁が血管に弛緩して広がるよう伝えるために産生するガスです。. to form peroxynitriteA reactive nitrogen species formed when nitric oxide is neutralized by superoxide radicals; its production during postprandial oxidative stress sharply reduces the bioavailable nitric oxide needed for arterial dilation and anti-atherogenic vascular function.; peroxynitrite oxidizes the eNOS cofactor tetrahydrobiopterin, causing eNOS uncouplingA dysfunctional state of endothelial nitric oxide synthase in which the enzyme produces superoxide rather than nitric oxide, amplifying oxidative stress and reducing vasodilatory capacity; it is reversed as tetrahydrobiopterin availability is restored during plaque regression., whereupon the enzyme produces superoxide rather than nitric oxide in a self-sustaining cycle. Reduced NO bioavailability then permits NF-κB-driven expression of VCAM-1VCAM-1 is a sticky molecule that appears on an inflamed vessel lining and grabs passing white blood cells so they can burrow into the wall., ICAM-1ICAM-1 is a molecule that appears on the surface of the blood vessel lining and acts like Velcro, catching passing immune cells., and E-selectin, which capture circulating monocytes for transmigration into the 内皮下腔内皮下腔は、動脈の内膜のすぐ下、1層の細胞とその下の筋肉の間にある狭い隙間である。..
Downstream of this, a further set of mechanisms — disruption of endothelial tight-junction proteins (ZO-1, claudin-5, occludin), MMP-9 upregulation with TIMP-1 suppression, VEGF- and angiogenin-driven intra-plaque 新生血管形成Neovascularization is the growth of new blood vessels. Inside a plaque, they sprout from the vessels feeding the artery's own wall., and TNF-α-mediated impairment of 内皮前駆細胞Bone-marrow-derived precursor cells that circulate in the bloodstream and home to sites of endothelial injury, where they participate in re-endothelialization and microvascular repair; their mobilization is enhanced by statins, aerobic exercise, and whole-food plant-based nutrition. — has been proposed. Each of these steps derives from animal or cell-system work rather than from human plaque, and none is individually sourced to a human study here. They are listed as candidate mechanisms, not as findings.
A necessary demarcation, and it matters more than it may appear. Two components of this account do have direct human experimental support. Selective endothelin-A receptor antagonism with intra-arterial BQ-123 prevented the prolonged endothelial dysfunction that followed a mental stress task in healthy subjects, implicating endothelin-A signalling causally in the human response [76]. And in a three-way randomized crossover study of 15 overweight or obese men, AT₁R blockade with olmesartan and ascorbic acid infusion each altered the stress-induced fall in flow-mediated dilation and the accompanying redox profile, implicating AT₁R-mediated redox imbalance [77]. Both are small studies, and the second is confined to one sex and body-composition stratum.
The remainder of the cascade — the NADPH-oxidase/peroxynitrite/tetrahydrobiopterin/eNOS-uncoupling sequence and the downstream adhesion-molecule and plaque steps — remains substantially translational. It should not be cited to the demonstration that endothelial glucocorticoid receptor signalling suppresses atherogenesis, which is an ApoE-deficient mouse experiment [45] and speaks to endothelial GR biology rather than to this pathway. The tight-junction, MMP-9/TIMP-1, VEGF/angiogenin, and endothelial progenitor components derive predominantly from animal models, cell systems, and mechanistic reviews. They are biologically coherent and worth stating — but they are hypotheses about human plaque, not observations of it, and this review declines to present them at the same evidentiary level as the FMD data in Section 11.2. Related work showing that acute mental stress rapidly redistributes leukocytes in humans, with locally derived norepinephrine increasing endothelial adhesion signalling and plaque leukocyte recruitment in mice, illustrates the same split precisely [34].
Grade: Moderate for stress-induced endothelial dysfunction in humans; Limited for the detailed downstream molecular cascade in human plaque.
12. Mechanism IV: Metabolic
Glucocorticoids increase hepatic グルコースブドウ糖は、細胞にエネルギーを供給するために血液が運ぶ糖です。. production, antagonize peripheral insulin action, and contribute to visceral adiposity through tissue-specific glucocorticoid signalling [30]. These are established features of glucocorticoid physiology; none has been demonstrated to mediate a quantified share of stress-related ASCVD.
In community populations, altered diurnal cortisol — flatter slopes, higher bedtime cortisol — is associated with type 2 diabetes, and long-term hair glucocorticoid measures correlate with cardiometabolic traits [38].
12.1 The lipid pathway requires particular caution
It is sometimes asserted that stress raises LDLコレステロールLDLコレステロール(LDL-C)は、LDL粒子内に存在するコレステロールの量です。これは、ほとんどすべての標準的な検査報告書に記載されている数値です。. and thereby causes atherosclerosis. This is too simple, and the evidence does not support it.
ApoB-containing リポタンパク質リポタンパク質とは、脂肪とコレステロールを血流に乗せて運ぶ小さなカプセルのことです。脂肪は水に溶けないため、移動するにはタンパク質の包みが必要です。. remain the substrate that atherosclerotic plaque formation requires, a position supported by convergent genetic, epidemiologic and interventional evidence [75]. Psychological stress may alter diet, adiposity, インスリン感受性インスリン感受性とは、細胞がインスリンに対してどれだけよく反応するかということです。それはインスリン抵抗性の反対です。., and hepatic metabolism, and hypercortisolaemia with elevated free fatty acid flux can plausibly increase hepatic VLDLVLDL(超低密度リポ蛋白)は、肝臓が中性脂肪を体内の他の部位へと送り出すために作り出す粒子です。. and apoB secretion while lowering HDLHDL、すなわち高密度リポタンパク質は、しばしば「善玉コレステロール」と呼ばれる粒子です。組織からコレステロールを回収し、肝臓へ運び戻します。. cholesterol. But studies of job strain have not consistently found large adverse changes in 総コレステロール総コレステロールは、悪玉も善玉も含め、すべての粒子に含まれるコレステロールの合計です。., LDLLDL(低密度リポ蛋白)は、コレステロールを血液中に運ぶ主要な粒子であり、動脈壁に詰まる主原因となるものです。. cholesterol, or fibrinogen [39].
The defensible model is that stress interacts with pre-existing lipoprotein exposure rather than creating it. A person with low lifetime apoB exposure and high chronic stress is in a materially different position from a person with high lifetime apoB exposure and high chronic stress, and the literature gives no reason to think stress substitutes for the lipoprotein term.
12.2 Separating hormone from behaviour
The deeper problem with the metabolic literature is that in everyday chronic stress, behavioural pathways — diet, inactivity, アルコールアルコールは、ビール、ワイン、蒸留酒を酔わせる成分です。., and sleep loss — may contribute importantly to the metabolic effects observed. Distinguishing direct glucocorticoid effects from behavioural ones in observational human data is extremely difficult, and few studies have attempted it rigorously.
Grade: Moderate overall; Limited for a stress → cortisol → dyslipidaemia → atherosclerosis pathway specifically.
13. Mechanism V: Thrombosis and Acute Triggering
These mechanisms are distinct from long-term atherogenesis and should be reported separately (Figure 4).
Acute psychological stress produces measurable haemostatic change. A systematic review found relatively consistent stress-related alterations in coagulation, 線溶The physiological process by which the body dissolves blood clots through the enzyme plasmin; Lp(a) impairs this process by competing with plasminogen for fibrin-binding sites, reducing clot clearance and increasing the risk of an occlusive cardiac event., haemorheology, and platelet measures, though with considerable methodological weakness. Controlled norepinephrine infusion increases factor VIII activity, fibrinogen, and D-dimer, providing direct evidence that adrenergic signalling alters coagulation [35].
The proposed components are: epinephrine binding platelet α₂-adrenergic receptors, lowering cyclic AMP and the aggregation threshold, with P-selectin and activated glycoprotein IIb/IIIa rising within minutes; elevated factor VIII, von Willebrand factor, and fibrinogen; increased tissue factor expression; and elevated プラスミノーゲン血栓を溶解する酵素であるプラスミンへと変換される血清タンパク質。Lp(a)中のアポ(a)はプラスミン原と強い構造的相同性を共有しており、これによりLp(a)は血栓の分解を競合的に阻害する。. activator inhibitor-1 impairing endogenous fibrinolysis [35].
An important nuance is usually lost. In healthy subjects, coagulation and fibrinolysis often rise together, preserving haemostatic balance. It is in people with vascular disease or other vulnerabilities that a relative prothrombotic imbalance becomes consequential. The acute-stress prothrombotic state is therefore best understood as a modifier of existing risk, not a universal hazard.
Mental stress-induced myocardial ischaemia (MSIMI) roughly doubles the risk of adverse cardiac events and mortality in patients with coronary artery disease. The supporting meta-analysis rested on only five small studies with fewer than 50 events each — a thin base for a widely cited conclusion [36]. Mechanistically, in diseased 冠動脈冠動脈とは、心臓の外側を囲むように走っている細い血管で、心筋そのものに血液を供給するものです。. with endothelial dysfunction, catecholamine release fails to produce normal flow-mediated vasodilation; direct α-adrenergic stimulation of vascular smooth muscle instead produces paradoxical vasoconstriction.
Grade: Moderate–Strong for acute triggering; Moderate for the specific haemostatic mechanisms.
14. Mechanism VI: Behavioural Mediation
Multiple behavioural pathways plausibly contribute to the stress–ASCVD relationship: smoking, alcohol, diet quality, physical inactivity, sleep disruption, medication non-adherence, obesity, and co-occurring depression or anxiety. The share attributable to them is not established.
The standard analytic response is to adjust for these. Many prospective studies do so and find attenuated but still significant associations. This is often described as showing a “partly independent” effect, but the accurate statement is narrower: associations persist after adjustment for measured covariates. Statistical adjustment does not establish biological independence.
But adjustment cuts both ways, and this is under-appreciated. Chronic distress can contribute to smoking, inactivity, sleep disturbance and non-adherence, while these factors can also share upstream determinants with distress and can feed back on it. Depending on the causal structure, a given behaviour may act as a mediator, a confounder, a consequence of a common cause, or some combination. So:
- A minimally adjusted estimate retains pathways operating through behaviour, but also retains more confounding.
- A covariate-adjusted estimate conditions on measured variables and attenuates behaviourally mediated pathways — but conditioning on post-exposure variables can also induce collider bias, and it does ではない by itself identify a controlled or natural direct effect.
- Neither is “the” answer, and reporting only one is misleading.
This is a point of formal causal inference, not a stylistic preference. Estimating how much of the stress–ASCVD relationship is transmitted biologically rather than behaviourally requires a specified causal estimand and mediation analysis under explicit identification assumptions — no-unmeasured-confounding of exposure–outcome, mediator–outcome, and exposure–mediator relationships, and correct measurement and temporal ordering. Ordinary multivariable covariate adjustment alone does not establish these identification assumptions and does not by itself identify a controlled or natural direct effect.
This resolves an apparent conflict in the literature. The cross-sectional path analysis showing that standard risk factors mediate most of the hair-cortisol–CAD association and the INTERHEART finding that the psychosocial–MI association persists after adjustment for income and education are not contradictory. They are estimating different quantities.
There is no defensible single percentage for how much of stress-related ASCVD is behavioural versus direct. The answer varies by stressor, population, life stage, baseline disease, and mediator definition. Any review that supplies a specific figure is over-claiming.
The 2025 AHA scientific statement on post-myocardial-infarction psychological distress explicitly identifies these behavioural routes as credible pathways by which distress worsens prognosis [48] — which is also, usefully, where the clinical leverage lies (Section 21).
Grade: Moderate–Strong.
15. Mechanistic Evidence Matrix
Table 5. Mechanisms linking psychological stress to ASCVD, graded by human evidence.
| メカニズム | Proposed pathway | Human evidence | Consistency | Grade |
| HPA-axis dysregulation | Threat circuitry → CRH/ACTH → altered cortisol level, timing, recovery | Prospective links to diurnal slope, late-night cortisol, urinary and hair glucocorticoids | Direction depends on metric; several cohorts associate flatter or less differentiated rhythms with adverse outcomes, but cardiovascular findings are not uniformly consistent in meta-analysis | 中程度 |
| Glucocorticoid receptor resistance | Repeated stress → reduced immune-cell GR signalling → failure to suppress NF-κB | Human monocyte transcriptional data in chronically stressed caregivers | Biologically coherent; few outcome-linked studies | 中程度 mechanism; Limited outcome mediation |
| SAM / catecholamine activation | Stress → sympathetic output → heart rate, blood pressure, vasoconstriction, immune effects | Strong acute physiology; hormone–CVD meta-analysis; controlled norepinephrine infusion | Generally consistent | Moderate–Strong |
| Hypertension / haemodynamic load | Recurrent pressor and flow changes → mechanical wall stress and sustained BP burden; possible alteration of local haemodynamic forces | Cortisol responses to mental stress predict incident hypertension [74]; terminal step independently proven causal | Consistent in direction | Moderate–Strong |
| Cytokine inflammation | Stress → adrenergic/HPA/immune signalling → IL-6, IL-1β, TNF-α, CRP | Experimental acute-stress meta-analysis; chronic-stress genomic studies | Strongest for IL-6; magnitude varies | Strong for acute activation; 中程度 for ASCVD mediation |
| Amygdala–marrow–artery axis | Central threat response → sympathetic marrow signalling → leukopoiesis → arterial inflammation | One PET/CT cohort (n = 293, 22 events) with serial mediation; animal β3/CXCL12 chain | Highly coherent translationally; single human study | 中程度 |
| NLRP3 / IL-1β | Stress → inflammasome → IL-1β, IL-18 | NLRP3 linked to human atherosclerosis; stress-specific chain mostly animal/cellular | Stress-specific human evidence sparse | Limited for stress-specific mediation |
| Endothelial dysfunction | Stress → neurohumoral and redox signalling → impaired endothelial NO-dependent function / FMD | Reproducible experimental FMD impairment; prognostic for MACE in CAD | Reproduced clinically | Moderate–Strong |
| Downstream endothelial molecular cascade | Tight-junction loss, MMP-9/TIMP-1 imbalance, VEGF/angiogenin neovascularization, EPC suppression | Predominantly animal and cell-system; mechanistic reviews | Coherent but unverified in human plaque | Limited |
| Insulin resistance / visceral adiposity | Cortisol + behaviour + sleep loss → insulin resistance, central adiposity, diabetes | Strong endocrine plausibility; diurnal cortisol–type 2 diabetes association | Relation plausible; mediator-specific estimates lacking | 中程度 |
| ApoB / lipoprotein pathway | Stress-related metabolic change → altered atherogenic lipoproteins | Inconsistent direct stress–lipid association in occupational cohorts | Not consistently adverse | Limited |
| Coagulation / 血小板Platelets are small, anucleate cell fragments in the blood whose primary role is to clump together at sites of vascular injury to form a clot and stop bleeding; because they cannot synthesize new protein, aspirin's irreversible inhibition of their clotting enzyme lasts for the platelet's entire 7–10 day lifespan. | Acute stress → factor VIII, fibrinogen, vWF, platelet activity, impaired fibrinolysis | Laboratory studies and systematic review; NE infusion experiments | Broadly procoagulant but heterogeneous | 中程度 |
| Acute event triggering | Stress surge → demand, vasoconstriction, endothelial and thrombotic shift → ischaemia | Large international case-crossover data; MSIMI cohorts | Strong temporal signal | Moderate–Strong |
| Behavioural mediation | Stress → smoking, diet, inactivity, sleep, alcohol, non-adherence → CVD | Large observational base; consensus statements | Repeatedly observed | Moderate–Strong |
Figure 6 renders this matrix as a pathway diagram with per-link weighting. The shape of the evidence is worth noting explicitly: the chain is strongest at its two ends and weakest in the middle. That stress acutely activates these systems is well established in human laboratory physiology; that stress predicts events is well established epidemiologically. The quantitative contribution of each intermediate step to プラーク負荷プラーク負荷とは、単に最も状態の悪い一箇所だけでなく、動脈全体に存在するプラークの総量のことです。. in humans is not.
Figure 6. Integrated pathway from psychological stress to atherosclerotic events, with per-link human evidence weight. Labels grade the strength of human evidence for each arrow, not the size of the effect.
16. The Intervention Question: Taxonomy and the Claim Ladder
16.1 Meditation is not one treatment
Analysing “meditation” as a single intervention treats a clinically and methodologically heterogeneous class as though it were one treatment.
- Mindfulness-based interventions (MBIs), including MBSR, combine attentional training, acceptance and non-reactivity, body awareness, and frequently movement, yoga, and explicit behavioural instruction. MBSR is conventionally an eight-week instructor-led programme with substantial home practice.
- Mindfulness-based cognitive therapy (MBCT) adds cognitive-behavioural technique.
- Transcendental Meditation (TM) is a standardized mantra-based practice, typically 15–20 minutes twice daily, taught through an organized certification structure.
- Focused-attention and paced-breathing practices concentrate on a physiological anchor, such as breathing at approximately six breaths per minute.
The heterogeneity is not cosmetic. The Mindfulness-Based Blood Pressure Reduction (MB-BP) programme explicitly teaches DASH-pattern diet, physical activity, medication adherence, and alcohol reduction alongside meditation. A trial of MB-BP is a trial of a multicomponent behavioural intervention, and attributing its results to meditation specifically is unwarranted [60].
Focused-attention meditation deserves separate mention: cardiovascular trials generally bundle attentional practices into broader mindfulness programmes rather than testing a standardized focused-attention intervention in isolation. There is therefore insufficient evidence to rank focused-attention meditation against MBSR or TM for ASCVD endpoints.
16.2 The comparator problem
An inactive control — waitlist, no treatment, usual care — does not isolate meditation. It bundles instructor attention, expectancy, social contact, time spent sitting quietly, repeated measurement, and the structure of a programme. A waitlist-controlled trial therefore does not isolate the practice-specific effect; it estimates the effect of the whole package and its expectancy context, and inactive comparators tend to yield larger estimates in this literature.
Figure 7 shows what this does to the numbers. Comparator choice materially influences the estimated effect — though intervention type, trial size, adherence, population, background therapy, measurement method and heterogeneity all contribute as well.
Figure 7. In meditation trials, the choice of comparator materially influences the answer. The only moderate-certainty systolic blood-pressure estimate in the Cochrane review — Transcendental Meditation against an active comparator — is also the smallest.
16.3 Five separable claims
Because these are routinely conflated, they are separated throughout (Figure 8):
- Claim A: meditation reduces perceived stress.
- Claim B: meditation changes stress physiology (cortisol, HPA function).
- Claim C: meditation improves established risk factors (blood pressure, HRV, inflammation, metabolic markers).
- 主張D: meditation slows measurable atherosclerosis.
- Claim E: meditation reduces hard events — myocardial infarction, stroke, cardiovascular death.
Evidence weakens sharply from A to E, and E cannot be inferred from A through D.
Figure 8. Five separable claims about meditation, and the evidence for each. An intervention can reliably reduce how stressed a person feels, modestly lower their blood pressure, and still have no demonstrated effect on whether they have a heart attack.
17. The Benchmark Synthesis
その 2024 Cochrane review is the reference standard for this question. It included 81 randomized trials and 6,971 participants, requiring interventions of at least 12 weeks in adults at high cardiovascular risk or with established cardiovascular disease, and examined four prespecified comparisons. Most trials were at unclear risk of bias, many were small, and heterogeneity was substantial across most outcomes.
Table 6. Cochrane 2024 — findings by comparison.
| Comparison | 血圧 | Psychological outcomes | Clinical events | Certainty |
| MBIs vs active comparators (29 RCTs, 2,883 participants) | SBP MD −6.08 mmHg (−12.79 to 0.63), I² = 88%; DBP −5.18 (−10.65 to 0.29), I² = 91%; 6 trials, 388 participants | Perceived stress SMD −0.24 (−0.45 to −0.03), I² = 0%, 6 trials, 357 participants; anxiety SMD −0.06 (−0.25 to 0.13), I² = 0%; depression ≈ null; wellbeing little or no effect | None reported. Smoking cessation RR 1.45 (0.78–2.68), I² = 79% | Low for BP; moderate for perceived stress, anxiety, depression |
| MBIs vs non-active comparators (38 RCTs, 2,905 participants) | SBP MD −6.62 mmHg (−13.15 to −0.10), I² = 87%; DBP −3.35 (−5.86 to −0.85), I² = 61%; 9 trials, 379 participants | Larger effects than against active controls | One trial (110 participants): RR 0.94 (0.37–2.42) | Low for BP; very low for events |
| TM vs active comparators (8 RCTs, 830 participants; SBP analysis 8 RCTs, 774 participants) | SBP MD −2.33 mmHg (−3.99 to −0.68), I² = 2% — TM probably reduces SBP; DBP less certain | — | One trial (201 participants): RR 0.91 (0.56–1.49) | Moderate for SBP; 低い for events |
| TM vs non-active comparators (2 RCTs, 186 participants) | SBP MD −6.34 mmHg (−9.86 to −2.81), I² = 0%; DBP −5.13 (−9.07 to −1.19), I² = 18%; 2 trials, 139 participants | One trial (112 participants): anxiety SMD −0.71 (−1.09 to −0.32); depression −0.48 (−0.86 to −0.11) | None reported. No adverse events or smoking data | Low for SBP; very low for DBP |
Two observations dominate. First, of 81 randomized trials, exactly two contributed cardiovascular clinical-event data — one at very low certainty (MBIs vs inactive, RR 0.94, 0.37–2.42) and one at low certainty (TM vs active, RR 0.91, 0.56–1.49) — and neither showed a detectable effect. Because the Cochrane search closed in November 2021, this characterises the trials it included rather than the entire literature to the present day. Second, the only moderate-certainty blood-pressure estimate in the entire review is also the smallest: −2.33 mmHg for TM against an active comparator, with essentially no heterogeneity (I² = 2%) and the largest participant total — 774 of the 830 participants in that comparison contributed systolic data. Every estimate near −6 mmHg carries either I² ≥ 87% or fewer than 150 participants.
The Cochrane authors’ own summary is that they found very little information on clinical endpoints, limited information on blood pressure and psychological outcomes, substantial between-study heterogeneity, and a body of evidence generally of low certainty [50].
A note on a common citation error. The −2.33 mmHg figure is frequently attributed to mindfulness-based interventions, or to a non-active comparison. It belongs to TM versus active comparators. The distinction matters: the figure is often deployed to argue that mindfulness produces meaningful blood-pressure reduction, when it in fact represents the most rigorously controlled — and smallest — estimate in the review.
18. Claim A: Perceived Stress
Mindfulness-based interventions probably produce a small reduction in perceived stress against active comparators, in the cardiovascular-risk populations Cochrane included. Against active comparators, the Cochrane pooled estimate was SMD −0.24 (−0.45 to −0.03; I² = 0%; 6 trials, 357 participants; moderate certainty) — a small effect with no detected statistical heterogeneity (I² = 0%), across six trials. Against inactive comparators, effects are larger.
Two qualifications. First, pooled effects on anxiety and depression against active comparators were approximately null (anxiety SMD −0.06, I² = 0%, moderate certainty). Reducing perceived stress is not the same as treating an anxiety or depressive disorder, and this literature does not support the latter claim in cardiovascular populations [50]. Second, the difference between active-controlled and waitlist-controlled effects is itself the finding: the smaller effect against active comparators suggests that non-specific intervention and context effects contribute meaningfully to estimates obtained in uncontrolled or waitlist designs.
Grade: Moderate.
19. Claim B: Cortisol and HPA Physiology
The strongest aggregate evidence comes from a systematic review and meta-analysis of 58 randomized trials with 3,508 participants (Figure 9A). Across blood, salivary, and hair matrices, psychological stress-management interventions changed cortisol with a pooled Hedges’ g of 0.282. That pooled figure covers stress-management interventions generally, not meditation specifically; the mindfulness/meditation subgroup estimate was g = 0.345. Effects were larger for CAR measures (g = 0.644) than diurnal cortisol measures (g = 0.255). By modality, mindfulness and meditation (g = 0.345) and relaxation (g = 0.347) were most effective, while mind–body (g = 0.129) and talking therapies (g = 0.107) were non-significant [51].
Figure 9. Meditation alters stress biology modestly and inconsistently. ‘Modulation’ is a more accurate description than ‘cortisol lowering’; no study has shown that a meditation-induced cortisol change mediates a reduction in cardiovascular events.
Complementary evidence: across 10 randomized trials using blood sampling, meditation had a medium effect on cortisol (g = 0.62, 95% CI 0.22–1.02, p = 0.003) — but only in at-risk or somatically ill samples, not in healthy participants without risk factors [52]. A meta-analysis of MBIs on salivary cortisol in healthy adults (5 RCTs, n = 190) found smaller and less consistent effects [53].
Three interpretive points.
First, “modulation” is safer than either “lowering” or “normalisation.” Depending on baseline phenotype, a favourable change could mean a stronger CAR, a steeper diurnal decline, lower evening cortisol, or altered reactivity — potentially in opposite directions in different people. Reporting a pooled standardized effect as “meditation lowers cortisol” misdescribes what was measured; but neither do these pooled effects demonstrate movement toward a validated healthy physiological reference, which is what “normalisation” would assert.
Second, the observation that active-controlled trials in that meta-analysis did ではない show weaker cortisol effects than passive-controlled trials argues against explaining the entire effect by no-treatment expectancy. It does not identify a meditation-specific mechanism, since active controls differ widely in credibility and intensity.
Third, and decisively: no study has demonstrated that a meditation-induced cortisol change mediates any cardiovascular benefit. Observing a cortisol decrease and a blood-pressure decrease in the same trial does not establish that the former caused the latter, let alone that either prevented atherosclerosis.
Grade: Limited–Moderate. Some evidence suggests larger effects in at-risk or somatically ill samples, with the clearest signal in pooled blood-cortisol studies and weaker salivary findings.
20. Claim C: Established Risk Factors
20.1 Blood pressure — the best-supported surrogate
The Cochrane estimates are in Table 6. Older TM-specific meta-analyses estimated larger reductions of approximately −4.7/−3.2 mmHg, and a separate TM meta-analysis of 12 studies and 996 participants reported −4.26 mmHg systolic and −2.33 mmHg diastolic [62,63]. The AHA statement on alternative approaches to blood-pressure lowering rated TM only Class IIb, Level of Evidence B, explicitly citing study-quality concerns [49], and the same statement noted that effect estimates in this literature vary with study quality.
Individual trials illustrate why pooling is contentious:
- MBSR versus progressive muscle relaxation in 56 adults with prehypertension: clinic SBP fell 4.8 mmHg versus 0.7 mmHg (p = 0.016) and DBP fell 1.9 mmHg versus a 1.2 mmHg rise (p = 0.008) — but ambulatory blood pressure did not differ. [58]
- HARMONY: 101 adults with untreated stage-1 hypertension showed essentially no between-group difference in 24-hour ambulatory blood pressure at 12 weeks (+0.4/0.0 versus +0.4/−0.4 mmHg) [59].
- MB-BP, a mindfulness-based multicomponent blood-pressure programme rather than a meditation-only trial: 201 participants with elevated office blood pressure showed a prespecified between-group difference in office systolic pressure of −4.5 mmHg (95% CI −9.0 to −0.1) at six months versus enhanced usual care. But the intervention also targeted diet, physical activity, medication adherence, alcohol, and stress; sedentary time fell by 350.8 minutes per week. Improved health behaviour is one plausible contributor, but the multicomponent design prevents attributing the blood-pressure effect to meditation alone, and co-occurrence of behavioural and blood-pressure change does not by itself establish mediation. A 2026 secondary analysis found a small improvement in composite cardiovascular health (SMD 0.144, 0.023–0.266) while individual component confidence intervals generally crossed the null. The lead investigator disclosed ownership of a company providing mindfulness training, with preregistration, restricted data access, and independent statistical analysis as declared safeguards [60,61].
In several of these trials, clinic blood pressure moved while ambulatory blood pressure did not. This discrepancy warrants caution, though it is drawn from a small number of trials and should not be generalized to the whole literature. Ambulatory measurement is less susceptible to office and white-coat effects and is generally more prognostically informative.
Grade: Moderate. A realistic expectation differs by modality and comparator rather than resolving to one number: approximately −2.3 mmHg systolic for TM against an active comparator (moderate certainty); larger but imprecise and highly heterogeneous estimates for MBIs (low certainty, confidence intervals crossing or near the null against active comparators); and approximately −4.5 mmHg office systolic for the multicomponent MB-BP programme, which cannot be attributed to meditation alone.
20.2 Heart-rate variability
Popular accounts assert that meditation “restores vagal tone.” The randomized evidence does not support this as a consistent chronic effect. A meta-analysis of 19 RCTs 見つかりました Hedges’ g 0.38 (95% CI −0.014 to 0.77; I² = 89.1%) for resting vagally mediated HRV — not statistically convincing, and extraordinarily heterogeneous. Removing a single extreme outlier reduced the estimate to 0.19 (−0.02 to 0.39) [57].
Grade: Inconclusive.
20.3 Inflammation
The picture is mixed and, importantly, level-dependent (Figure 9B).
Pooled across 48 randomized trials with 4,683 participants, MBIs produced small reductions in CRP at post-treatment (standardized mean change difference −0.14, −0.26 to −0.01) and IL-6 (−0.35, −0.67 to −0.03). At follow-up, CRP remained reduced (−0.39, −0.68 to −0.10) while the IL-6 interval included no effect (−0.13, −0.29 to 0.03) [54].
But a relatively large, matched-active-control randomized trial complicates this. In 190 lonely older adults, MBSR versus an active health-enhancement programme reduced pro-inflammatory NF-κB-related gene expression (d = 0.17, p = 0.028) but did ではない reduce circulating IL-6 or CRP, nor alter CREB, IRF, or glucocorticoid-receptor transcriptional activity. An earlier positive gene-expression trial had only n = 40 [55,56].
The lesson is specific and generalizable: transcriptional signalling and systemic protein biomarkers do not necessarily move together. Demonstrating a change at one level of the inflammatory cascade is not evidence of change at another, and neither is evidence of change in plaque.
Grade: Limited–Moderate.
20.4 Metabolic outcomes
Small improvements in glucose, lipids, and metabolic-syndrome components appear in some trials but are underpowered and inconsistent. A meta-analysis in diabetes found psychological benefits from MBSR but no detectable pooled HbA1c improvement at post-intervention or follow-up [64]. Cochrane found no significant lipid or glycaemic changes for MBIs against active controls.
Behavioural change driven by these programmes may still be cardiovascularly useful — but that is a behavioural mechanism, not a demonstration of a cortisol → insulin-sensitivity pathway.
Grade: Limited.
21. Claim D: Atherosclerosis
Direct randomized evidence is sparse and inconsistent.
The most-cited trial randomized 138 hypertensive African American adults to TM versus health education. Only about 60 of the 138 randomized participants contributed paired carotid 中内膜厚Intima-media thickness, or IMT, is a measurement of how thick the inner layers of an artery have become, usually taken in the neck with ultrasound. data (roughly 43.5% retention), and among those completers cIMT regressed in the TM group (−0.098 mm) while progressing in controls (+0.054 mm; p = 0.038) [65]. Attrition of this magnitude creates a high risk of attrition bias, and the finding is best regarded as preliminary.
A randomized trial conducted from 2000 to 2014 and published in 2025, in a different population and with a different follow-up structure, did not demonstrate a between-group cIMT benefit. Of 197 randomized participants, 136 completed post-test cIMT. After one year, cIMT changed by −0.0004 mm in the TM group and −0.0003 mm in health education — no significant difference. There were also no differences in lipids or blood pressure at one year. The authors noted that both groups progressed less than historical non-randomized controls, but that comparison is not randomized and cannot support a causal inference about either arm [67].
Beyond these, small mind-body studies have evaluated flow-mediated dilation or endothelial biomarkers, but none establishes that meditation changes coronary プラーク体積プラーク体積とは、動脈の一区間におけるプラークの総物理量であり、立方ミリメートル単位で測定されます。., carotid plaque, coronary artery calcium progression, or plaque composition.
The hierarchy matters here more than anywhere. Improving FMD is not slowing plaque. Slowing a surrogate is not preventing myocardial infarction.
Grade: Limited / Inconclusive — with the later trial’s failure to demonstrate a between-group cIMT benefit carrying substantial weight. Because populations, designs and follow-up differ, this is a failure to demonstrate benefit in a related trial rather than a strict replication attempt.
22. Claim E: Hard Clinical Events
Two small randomized trials, both from the same TM-affiliated research group at institutions linked to the organization that teaches and licenses the technique, report hard-endpoint benefit.
- 201 Black patients with coronary heart disease randomized to TM versus health education. Over a mean 5.4 years, TM was associated with a 48% reduction in the composite primary endpoint of all-cause mortality, myocardial infarction, and stroke: HR 0.52 (95% CI 0.29–0.92; p = 0.025), alongside a systolic blood-pressure reduction of approximately 4.9 mmHg [66].
- The trial published in 2025 had a null primary endpoint. This trial was conducted from 2000 to 2014 and published in 2025 after delayed analysis; it is not a newly recruited contemporary trial, and its registration (NCT05642936) post-dates data collection by many years. Its primary endpoint, carotid intima-media thickness, showed no between-group difference. The secondary event analysis reported a 65% relative MACE reduction at five years (HR 0.346, 95% CI 0.134–0.893; p = 0.017), with the 14-year analysis null (HR 0.68, 0.35–1.31) [67].
- Three features require explicit flagging. First, events were analysed across multiple maximum-follow-up windows (1, 5, 10 and 14 years) without a stated multiplicity adjustment; the five-year window is best treated as the main secondary analysis and the others as exploratory. Second, event counts are small throughout. Third, the reported ten-year result is internally inconsistent as published: the paper gives HR 0.485 with a 95% confidence interval of 0.226–1.044 alongside p = 0.0435. An interval that includes 1.0 cannot accompany a p-valueA p-value estimates how likely you would be to see a result at least this striking if the treatment did nothing at all. below 0.05. Until that discrepancy is resolved by the authors, the ten-year result should not be described as statistically significant, and this review does not do so.
These findings must be weighed carefully rather than dismissed or accepted.
In their favour: both are randomized, both used an active comparator (health education rather than waitlist), and the direction is consistent.
Against them: both are small; both come from a single research group; the confidence intervals are wide (the 2025 upper bound of 0.893 sits close to unity); the 2025 trial’s own primary endpoint — cIMT — was null, so the event finding is a secondary outcome in a trial that failed its primary; multiple maximum-follow-up windows were analysed and significance was lost at 14 years; trial registration post-dated the original data collection; and both carry researcher-allegiance and institutional-affiliation concerns of a degree that would attract close scrutiny in any pharmaceutical context. The distinction matters and this review observes it: the 2025 trial explicitly declared no commercial or financial conflict of interest, while several authors hold institutional affiliations with organizations involved in teaching and researching the intervention. That is an allegiance concern, not a documented undeclared financial conflict, and should be described as such. A 2025 commentary in a major cardiology review journal advocating TM within cardiovascular prevention frameworks originates from the same investigator group and should be read with the same awareness [69].
A separate 2025 multicentre trial of meditation and health education for cardiometabolic disease prevention in 201 Black women reported no between-group difference in carotid intima-media thickness, with some metabolic signals on secondary outcomes [68]. It is a separate trial but arises from the same investigator network, and therefore does not constitute independent replication.
The Cochrane review, applying prespecified methods to trials published to November 2021, found very sparse clinical-event evidence — two comparisons, one low and one very low certainty, neither showing a detectable effect [50]. Because its search closed in 2021, Cochrane cannot by itself adjudicate the 2025 and 2026 publications discussed above; our own structured search to 20 August 2026 identified no independent replication among them.
The correct statement is therefore precise, and scoped to what we searched: in the literature identified through our search to 20 August 2026, we found no independent, replicated, low-bias randomized evidence that meditation prevents cardiovascular events or death. This is not the same as evidence of no effect. It is the absence of the evidence that would be required to make the claim — and, given a structured rather than systematic search, it is a review finding rather than a proof of non-existence.
Grade: Inconclusive.
Table 7. Meditation and stress-reduction trials and syntheses.
| 勉強 | Intervention vs comparator | N / duration | Principal outcomes | Effect | Principal methodological concerns |
| Cochrane review, 2024 | MBI or TM vs active or non-active | 81 RCTs; 6,971 | BP, psychological outcomes, lipids; CVD events sought | See Table 6; only 2 trials reported events | Mostly unclear; low to moderate certainty |
| Rogerson et al., 2024 | Stress-management vs pooled controls | 58 RCTs; 3,508 | Cortisol (CAR, diurnal, single-sample) | g = 0.282 overall; CAR 0.644; meditation 0.345 | Moderate; heterogeneous comparators |
| Koncz et al., 2021 | Meditation vs control | 10 RCTs (blood samples) | Blood cortisol | g = 0.62 (0.22–1.02); at-risk samples only | Moderate; small trials |
| Sanada et al., 2016 | MBI vs control, healthy adults | 5 RCTs; 190 | Salivary cortisol | Smaller, inconsistent | 中程度 |
| Dunn & Dimolareva, 2022 | MBI vs randomized controls | 48 RCTs; 4,683 | CRP, IL-6 | CRP −0.14 (−0.26 to −0.01); IL-6 −0.35 (−0.67 to −0.03) | Population and dose heterogeneity |
| MBSR gene-expression RCT, 2023 | MBSR vs active health-enhancement, older adults | 190; 8 weeks | NF-κB gene expression; IL-6; CRP | Gene expression d = 0.17 (p = 0.028); IL-6 and CRP unchanged | Low–moderate; best-designed inflammation trial |
| Brown et al., 2021 | Mindfulness / meditation vs control | 19 RCTs | Vagally mediated HRV | g = 0.38 (−0.014 to 0.77), I² = 89%; 0.19 without outlier | Extreme heterogeneity |
| Hughes et al., 2013 | MBSR vs progressive muscle relaxation | 56; 8 weeks | Clinic and ambulatory BP | Clinic SBP −4.8 vs −0.7 mmHg (p = 0.016); ambulatory null | Small, short |
| Blom et al. (HARMONY), 2014 | MBSR vs waitlist | 101; 12 weeks | 24-h ambulatory BP | +0.4/0.0 vs +0.4/−0.4 mmHg — no effect | Pilot; waitlist |
| Loucks et al. (MB-BP), 2023 | 8-wk adapted mindfulness + CV behaviour education vs enhanced usual care | 201; 6-mo follow-up | Office SBP; behaviour | SBP −4.5 mmHg (−9.0 to −0.1); sedentary time −350.8 min/wk | 17.4% loss to follow-up; multicomponent; investigator commercial interest |
| MB-BP secondary analysis, 2026 | Same programme | 201; 6 mo | Composite CV health | SMD 0.144 (0.023–0.266); component CIs cross null | Secondary analysis |
| Anderson et al., 2008 | TM vs control | メタアナリシス | SBP, DBP | −4.7 mmHg SBP; −3.2 DBP | Older meta-analysis; study-quality and investigator-allegiance concerns; AHA rated TM Class IIb, LOE B |
| Castillo-Richmond et al., 2000 | TM vs health education | 138 randomized; ≈60 paired cIMT (43.5% retention) | Carotid IMT | −0.098 vs +0.054 mm (p = 0.038) | Severe attrition; small analysed sample; preliminary |
| Schneider et al., 2012 | TM vs health education, CHD patients | 201; mean 5.4 y | Composite mortality, MI, stroke | HR 0.52 (0.29–0.92), p = 0.025 | Small trial; single investigator network; allegiance concern |
| Norris et al., 2025 | TM vs health education | 197 randomized; 136 cIMT | cIMT at 12 months (primary); MACE to 14 y | cIMT null (−0.0004 vs −0.0003 mm); MACE HR 0.346 (0.134–0.893) at 5 y, null at 14 y | Primary endpoint null; secondary events across multiple windows; retrospective registration; allegiance concern |
23. Evidence Quality, Bias, and Adverse Effects
Table 8. Author-assessed narrative confidence by claim, with explicit basis for downgrade.
Downgrade domains: RoB = risk of bias · IND = indirectness · IMP = imprecision · INC = inconsistency · CONF = confounding · PB = publication bias.
| Claim | 自信 | Downgrade domains | Basis |
| Stress → ASCVD association (several psychosocial constructs, CHD/CVD) | Strong | CONF | Consistent associations across case-control and prospective cohort studies for several psychosocial constructs; imaging and mechanistic studies provide supporting evidence for selected intermediate pathways; residual socioeconomic and behavioural confounding remains |
| Stress → ASCVD causation (clinical events) | 中程度 | CONF, IND | Temporality and experimental physiology support it; no randomized test; residual confounding cannot be excluded |
| Stress → plaque initiation / progression | Limited–Moderate | IND, IMP | Direct human serial-imaging evidence is sparse; most support inferred from event and surrogate endpoints |
| Amygdala–marrow–artery pathway | 中程度 | IMP, RoB | One longitudinal imaging study; 22 events; observational mediation; psychometric substudy n = 13 |
| Cortisol diurnal dysregulation → CV mortality | 中程度 | IMP, INC | Several prospective cohorts report adverse associations with flatter or less differentiated rhythms, but cardiovascular event counts are small (31–32 deaths), measures differ, and a broader meta-analysis found no significant random-effects association for the cardiovascular-disease subgroup [78] |
| Cortisol Mendelian randomization → CHD | Limited–Moderate | IMP, IND | CI includes null; instruments explain ≈0.5% of variance, limiting power; SERPINA6/SERPINA1 pleiotropy unresolved; instruments cortisol, not stress |
| Spot cortisol → CV outcomes | Limited | CONF, INC | Attenuated to null on adjustment (LURIC); null cross-sectional study; matrix mismatch with chronic exposure |
| Hypertension / autonomic pathway | Moderate–Strong | IND | Terminal step independently proven causal; exposure–mediator link and mediated fraction unquantified |
| Inflammation — acute stress-induced activation | Strong | — | Experimental human meta-analysis with consistent direction |
| Inflammation — mediation of stress-related ASCVD risk | 中程度 | IND | Anti-inflammatory RCTs establish causal relevance of inflammation to selected coronary outcomes, not the mediated fraction of stress risk |
| Endothelial dysfunction — acute human response | Moderate–Strong | IMP | Reproducible experimental effect; prognostic in CAD; small experimental samples |
| Endothelial molecular cascade (downstream steps) | Limited | IND | Predominantly animal and cell-system evidence; endothelin-A and AT₁R components have small human support |
| Metabolic pathway | 中程度 | IND | Endocrine plausibility strong; stress-specific mediated fraction unquantified |
| Lipid / apoB pathway | Limited | INC | Occupational-cohort stress–lipid associations inconsistent |
| Thrombotic and acute-triggering pathways | Moderate–Strong | RoB | Large case-crossover data; mechanism studies methodologically heterogeneous |
| Behavioural mediation | Moderate–Strong | IND | Repeatedly observed; no defensible single quantification of mediated fraction |
| A. Meditation → reduced perceived stress | 中程度 | IMP | SMD −0.24 against active comparators, I² = 0%; small effect, modest sample |
| B. Meditation → cortisol / HPA change | Limited–Moderate | INC, IND | Effects mainly in at-risk samples; heterogeneous matrices; pooled estimate not meditation-specific; mediation unproven |
| C. Meditation → blood pressure | 中程度 | INC, IMP | Only moderate-certainty systolic estimate is −2.33 mmHg (TM vs active); MBI estimates heterogeneous (I² ≥ 87%) |
| C. Meditation → HRV | Inconclusive | INC, IMP | Pooled effect crosses null; I² = 89%; outlier-sensitive |
| C. Meditation → inflammation | Limited–Moderate | INC, IND | Small pooled biomarker effects; best-controlled trial found gene-expression change without CRP or IL-6 change |
| D. Meditation → reduced atherosclerosis | Limited / Inconclusive | RoB, IMP | Original cIMT finding had 43.5% retention; later trial showed no between-group difference |
| E. Meditation → reduced hard events | Inconclusive | RoB, IMP, PB | Two small allegiance-linked trials; sparse low-/very-low-certainty Cochrane event data; no independent replication identified |
23.1 Systematic problems
Comparator selection. Waitlist and no-treatment controls tend to yield larger estimated effects than active comparators in this literature. Cochrane found consistently larger effects against inactive comparators.
Publication bias and related reporting concerns. Publication status was directly associated with effect size in the occupational-stress literature (1.43 published versus 1.16 unpublished). In the TM literature, small samples, selective-reporting possibilities, retrospective registration in some studies, and researcher allegiance create related but separately defined concerns, without an equivalent empirical quantification of publication bias.
Researcher allegiance and institutional affiliation. Particularly pronounced in TM research, where the trials reporting hard-endpoint benefit originate from investigators institutionally affiliated with organizations that teach and research the technique. Where financial interests are separately disclosed — as in the MB-BP programme and the 2026 commentary — this review says so explicitly; where trials declare no financial conflict, the concern is allegiance and affiliation rather than undeclared financial interest. The AHA statement explicitly called for adequately powered randomized trials with under 20% dropout conducted by investigators without inherent bias in outcome. That call has not been answered [46].
Underpowering and attrition. Studies are frequently underpowered per arm; attrition ranges from 17% to more than 50% among the key trials reviewed here.
Surrogate reliance and short follow-up. Trial durations in the Cochrane corpus were required to be at least 12 weeks, and most were short relative to what would be needed to assess structural plaque remodelling or event rates.
Reverse causality in cortisol cohorts. In cohorts with existing cardiovascular disease, hormone measurements may reflect disease severity, medications, acute illness, sleep, or renal function rather than psychological stress.
23.2 Adverse effects
Mind-body interventions are generally safe but not free of adverse effects. A 2020 systematic review pooling heterogeneous designs estimated an overall adverse-event prevalence of approximately 8% among people practising mindfulness or meditation — chiefly heightened anxiety, panic, depressive symptoms, or depersonalization — broadly comparable to rates reported for standard psychological therapies, though estimates varied widely by study design and reporting was substantially incomplete [70]. Notably, the Cochrane review found that most included trials did not report adverse events at all, which is itself a reporting failure [50].
24. Integrated Model with Per-Link Evidence Weight
Disease pathway (Figure 6). Grades below apply to each individual link and distinguish acute physiological certainty from chronic disease mediation. Chronic stress → cortico-limbic threat circuitry [Moderate–Strong] → acute HPA and sympathetic activation [Strong for acute physiology; chronic phenotype variable] → catecholamine response [Strong for acute physiology; Moderate for chronic CVD association], cortisol dysregulation [Moderate], reduced chronic vagal tone [Limited–Moderate], glucocorticoid receptor resistance [Moderate as mechanism; Limited as ASCVD mediator] → inflammation via marrow haematopoiesis, IL-6/CRP, NF-κB [Moderate–Strong in humans], endothelial dysfunction [Moderate–Strong], stress → sustained blood-pressure burden [Moderate]; blood pressure → ASCVD [Strong], insulin resistance and visceral adiposity [Moderate, partly behavioural], platelet and coagulation activation [Moderate, mainly acute] → atherosclerosis initiation and progression [Limited–Moderate: direct human serial-imaging evidence is sparse] → plaque instability and thrombosis [Moderate] → myocardial infarction, stroke, cardiovascular death [association Strong; mechanism-specific causal weight Moderate].
Intervention pathway. Meditation → reduced perceived stress [Moderate] → possible improvement in HPA and autonomic regulation [Limited–Moderate] → reduced blood pressure [Moderate], some reduction in inflammatory gene expression [Limited], small metabolic change [Limited] → possible reduction in atherosclerosis [Inconclusive; early positive cIMT trial followed by a later related null trial] → possible reduction in events [Inconclusive].
24.1 The two competing narratives, stated precisely
The strongest available interpretation of the mechanistic evidence is ではない:
stress → continuously elevated cortisol → plaque.
A model more consistent with the available evidence — offered as a conceptual scheme, not a demonstrated serial mediation chain — is:
repeated psychological threat → altered central threat processing → repeated and dysregulated HPA and sympathetic activity → abnormal cortisol timing and reactivity, sometimes with glucocorticoid resistance and tissue-level amplification, together with catecholamine and haemodynamic activation → inflammatory, vascular, metabolic and behavioural change → increased susceptibility to atherosclerosis, and, in people who already have disease, increased vulnerability to acute triggering.
The second model accommodates what the first cannot: that some chronically stressed populations show high cortisol, others blunted reactivity, and others relatively normal circulating profiles with impaired glucocorticoid signalling.
24.2 Where stress sits relative to apoB
A point of framing that this review considers important. Atherosclerosis requires the retention of apoB-containing lipoproteins in the arterial 内膜内膜は動脈壁の一番内側の層であり、平滑な内壁のすぐ下に位置しています。. and a chronic inflammatory response to them. Psychological stress does not replace that process; current atherosclerosis biology provides no basis for treating psychological stress as an alternative to apoB-containing lipoprotein retention in plaque initiation [75].
Stress is more plausibly a modifier of atherogenic lipoprotein exposure and its vascular consequences than an alternative to apoB-driven plaque biology. What it can plausibly do is modify the rate at which that process runs, and modify the probability that established plaque converts to a clinical event. The magnitude of that modification will depend heavily on baseline apoB burden, smoking, blood pressure, diabetes, sleep, age, genetics, existing plaque burden, and behaviour. This is why the same 相対リスク相対リスクは2つのグループを比較するもので、このグループの心臓発作の発生率は、あのグループよりも30パーセント低かった。. means very different absolute things in different people — and why stress management is properly framed as a modifier of risk, not as a foundation of prevention.
25. Clinical and Prevention Implications
Stress management, including meditation, is a reasonable, low-risk adjunct for interested patients — particularly for blood pressure, psychological wellbeing, and behavioural self-regulation. It should ではない replace statins or other apoB-lowering therapy, 降圧薬An antihypertensive is any drug used to lower high blood pressure. The article distinguishes antihypertensives — which became widely used from the 1970s onward — from statins, noting that blood-pressure drugs contributed to coronary mortality decline well before statin therapy was available., smoking cessation, diabetes treatment, physical activity, 心臓リハビリテーション心臓発作などの心疾患の発症後に処方される、運動、教育、生活習慣の改善を組み合わせた医学的管理下で行われるプログラムであり、心血管機能を改善し、将来の発作のリスクを軽減することを目的としている。., or any other guideline-directed intervention. This is also the position of the American Heart Association, which concluded that meditation “may be considered as an adjunct” while noting that benefits remain to be better established [46,47].
Staged, actionable recommendations:
- Assess psychosocial stressors, depression, anxiety, and social isolation as risk markers — particularly in patients with unexplained risk, poor control, or after myocardial infarction. The value of screening lies in identifying people who need behavioural support, not in generating a risk score.
- Address established behavioural risk factors and psychosocial barriers alongside guideline-directed prevention. Smoking, physical activity, sleep, alcohol use and medication adherence are clinically important behavioural factors that can accompany psychological distress and should be addressed according to established prevention guidance. This is where the practical leverage is likely to lie, though the ordering is a clinical judgment rather than a directly tested comparison.
- Optimize guideline-directed prevention regardless of stress status — blood pressure, LDL cholesterol and apoB, glucose, smoking. Stress status does not change these targets.
- Offer meditation or structured stress reduction to patients who want it, framing the expected benefit honestly: modest blood-pressure and perceived-stress reduction, unproven event reduction. Where stress contributes to hypertension, poor sleep, inactivity, unhealthy eating, or difficulty adhering to treatment, the case for intervention is stronger — although the relative contribution of behavioural versus direct physiological mediation is not established.
- Do not order cortisol testing for cardiovascular risk stratification. It remains a research tool except where Cushing’s syndrome is clinically suspected. In LURIC, morning serum cortisol showed no independent association with cardiovascular mortality after adjustment for conventional risk factors [27], and no cortisol measure has been shown in a formal incremental-prediction analysis to improve risk estimation or to identify treatment responders.
- Do not present meditation as an alternative to pharmacotherapy. The most consequential harm in this area is not the intervention — it is the substitution.
- Counsel patients with established coronary disease about acute triggering where clinically appropriate. This is a distinct and better-supported phenomenon than chronic atherogenesis. Note, however, that evidence establishing acute triggering does not establish that counselling about it prevents events; no trial has tested that.
26. Thresholds That Would Change These Conclusions
Stating in advance what evidence would change one’s mind is a discipline this literature would benefit from.
- アン independently conducted, actively controlled, event-driven randomized trial, powered a priori for a clinically plausible MACE reduction given the expected baseline event rate, follow-up duration, non-adherence and competing risk, showing that meditation reduces MACE would justify elevating it from adjunct to recommended therapy. Independent replication by investigators without intervention-specific allegiance would materially increase confidence.
- Replication of the amygdala–marrow–artery finding in a larger cohort with adequate event numbers would move that pathway from Moderate to Strong.
- Demonstration that experimentally modifying an adverse diurnal cortisol pattern in a prespecified direction reduces events — not merely correlates with them — would justify cortisol-rhythm monitoring and would establish cortisol as a modifiable target rather than a readout.
- Serial 冠動脈画像診断冠動脈内のプラークの大きや性質を可視化するために用いられる、定量冠動脈造影や血管内超音波法などの非侵襲的または侵襲的な手法。オーニッシュやエッセルスティンの研究は、症状やイベントのデータのみに頼るのではなく、客観的な冠動脈イメージングを用いている点で特筆すべきである。. in a randomized stress-reduction trial showing changed plaque burden or phenotype would fill the Claim D gap directly.
- Stronger genetic instruments for cortisol, explaining substantially more than 0.5% of variance, would sharpen the causal estimate in either direction.
We identified none of these in our search to 20 August 2026.
27. Major Unanswered Research Questions
- Does reducing stress, by any means, reduce hard cardiovascular events in an adequately powered, low-bias, independent randomized trial?
- Does stress reduction alter serial coronary plaque burden or inflammatory プラーク表現型Plaque phenotype refers to the biological and structural characteristics of an atherosclerotic lesion — including the size of its lipid-rich necrotic core, fibrous cap thickness, degree of calcification, and inflammatory cell content — which together determine whether a plaque is stable or at high risk of rupturing.?
- Is modification of an adverse diurnal cortisol pattern itself cardioprotective, or is the pattern merely a marker of underlying health?
- Which meditation type, dose, frequency, and duration — if any — is most effective, via which mechanism, against an active control?
- How much of the stress–ASCVD link is genuinely causal versus confounded by socioeconomic position and behaviour?
- Can hair cortisol or cortisone add incremental predictive value over standard risk factors?
- Do baseline neuroimaging or cortisol phenotypes identify subgroups deriving disproportionate benefit from mind-body intervention?
- Do effects differ by sex, race, socioeconomic stress burden, PTSD or depression status, or baseline HPA phenotype?
- Do stress-reduction practices reproducibly modify immune gene expression, and if so, through what epigenetic mechanisms — including FKBP5-related regulation and GR signalling?
The field needs better mediation designs: an ideal study would randomize a standardized intervention, repeatedly measure perceived stress, sleep, behaviour, ambulatory blood pressure, catecholamines, multi-timepoint salivary cortisol, hair glucocorticoids, inflammatory signalling, endothelial function, and validated arterial imaging, then follow adjudicated cardiovascular events. Without that temporal mediator structure, an observed cortisol decrease and an observed blood-pressure decrease cannot establish that the former caused the latter.
28. Conclusions: Direct Answers to the Core Questions
Table 9. Summary answers.
| 質問 | Answer | Grade |
| Do chronic psychosocial stressors increase ASCVD risk? | Several distinct constructs — job strain, perceived stress, loneliness and social isolation — are each associated with modestly higher risk. Adjusted prospective estimates commonly ~1.2–1.3 for several psychosocial constructs; case-control and trigger estimates larger and answering different questions | Association Strong |
| How strong is the causal evidence? | Moderate. Supported by temporality, consistency and human experimental physiology, but materially weaker than the causal evidence for apoB exposure, smoking and blood pressure; residual confounding remains possible | 中程度 |
| Which mechanisms have the strongest human evidence? | Autonomic and haemodynamic activation; inflammation; endothelial dysfunction; behavioural mediation; acute triggering. Brain–marrow–artery signalling is compelling but rests on one study | Moderate–Strong |
| What role does cortisol play? | A nonspecific biomarker of HPA/glucocorticoid physiology and a plausible mediator; a small causal contribution is possible but unproven. Not the unique transmitter of stress | Limited–Moderate for causation |
| Is elevated cortisol pathogenic, or is dysregulation the better model? | Dysregulation is the better framework, without one mandatory phenotype. Frank hypercortisolism is unequivocally pathogenic but is not the usual chronic-stress state | Strong evidence against the simple model; 中程度 for any specific dysregulated phenotype |
| How much is mediated by BP, inflammation, insulin resistance, adiposity, sleep, and behaviour? | Unknown, and probably heterogeneous across populations and stressors. No single percentage is defensible; minimally adjusted and covariate-adjusted estimates answer different questions, and neither identifies a direct biological effect | — |
| Does meditation reduce perceived stress? | Yes, modestly; effect shrinks against credible active controls | 中程度 |
| Does meditation alter cortisol or HPA physiology? | Small-to-moderate pooled effects, mainly in at-risk samples. “Modulation” is more accurate than either blanket “lowering” or “normalisation”; favourable direction depends on baseline HPA phenotype and cortisol metric. Mediation of benefit unproven | Limited–Moderate |
| Does meditation improve established risk factors? | Blood pressure modestly — approximately −2.3 mmHg systolic for TM versus active comparators in the moderate-certainty Cochrane estimate, with larger but less certain estimates in other comparisons; HRV not convincingly; inflammation inconsistently; metabolic markers not reliably | 中程度 for BP |
| Does meditation slow atherosclerosis? | Not demonstrated consistently. An early small trial reported cIMT benefit with substantial attrition; a later randomized trial in a different population did not demonstrate a between-group benefit | Limited / Inconclusive |
| Does meditation prevent MI, stroke, or CV death? | Not established. Two small allegiance-linked trials suggest benefit; no independent replication; Cochrane found sparse low-/very-low-certainty event evidence | Inconclusive |
28.1 What is justified, and what is overreach
Justified. Several forms of chronic psychosocial stress and distress are prospectively associated with modestly higher ASCVD risk after adjustment for measured covariates, and probably contribute causally to some degree. HPA-axis dysregulation — not simple hypercortisolism — is a more defensible physiological framework, though no single dysregulated phenotype is established. Acute emotional stress can trigger events in people with existing disease. Meditation lowers perceived stress, modestly lowers blood pressure, is generally low risk, and is a reasonable adjunct within a complete prevention strategy — though adverse psychological experiences do occur and cardiovascular trials have reported harms incompletely.
Overreach. That stress is a major independent driver of atherosclerosis comparable to lipids or smoking. That cortisol testing is clinically useful for cardiovascular risk. That meditation “prevents heart attacks or strokes.” That meditation “reverses atherosclerosis.” That meditation “normalizes cortisol to prevent cardiovascular disease.” That any of this justifies deferring or substituting for guideline-directed therapy.
The gap between these two lists is where most public communication on this topic goes wrong — and, because cumulative apoB exposure drives atherosclerotic risk over time [75], the substitution error is not a harmless one.
29. Limitations of This Review
This is a narrative evidence review, not a systematic review with a registered protocol, prespecified search strategy, or formal risk-of-bias instrument applied to each included study. Study selection reflects the judgement of the author, informed by four independently prepared source syntheses, and may not be exhaustive.
The grading scheme in Section 2.3 is explicit but is not GRADE, and the grades are the author’s assessments rather than formal consensus ratings. Where full texts were paywalled, quantitative values were taken from published abstracts. Effect estimates drawn from meta-analyses inherit the limitations of those analyses, including heterogeneity and the publication bias documented in Section 7.2.
The review is weighted toward literature published in English and toward cohorts in high-income countries, with the notable exceptions of INTERHEART and INTERSTROKE. Finally, this is a rapidly moving area — the Cochrane authors themselves noted a large number of ongoing eligible studies — and conclusions about Claims D and E in particular should be expected to change.
30. References
- Rosengren A, Hawken S, Ôunpuu S, Sliwa K, Zubaid M, Almahmeed WA, et al. Association of psychosocial risk factors with risk of acute myocardial infarction in 11 119 cases and 13 648 controls from 52 countries (the INTERHEART study): case-control study. Lancet. 2004;364(9438):953–62. doi:10.1016/S0140-6736(04)17019-0. PMID: 15364186.
- O’Donnell MJ, Xavier D, Liu L, Zhang H, Chin SL, Rao-Melacini P, et al. Risk factors for ischaemic and intracerebral haemorrhagic stroke in 22 countries (the INTERSTROKE study): a case-control study. Lancet. 2010;376(9735):112–23. doi:10.1016/S0140-6736(10)60834-3. PMID: 20561675.
- Kivimäki M, Nyberg ST, Batty GD, Fransson EI, Heikkilä K, Alfredsson L, et al. Job strain as a risk factor for coronary heart disease: a collaborative meta-analysis of individual participant data. Lancet. 2012;380(9852):1491–7. doi:10.1016/S0140-6736(12)60994-5. PMID: 22981903.
- Huang Y, Xu S, Hua J, Zhu D, Liu C, Hu Y, et al. Association between job strain and risk of incident stroke: a meta-analysis. Neurology. 2015;85(19):1648–54. doi:10.1212/WNL.0000000000002098. PMID: 26468409.
- Fransson EI, Nyberg ST, Heikkilä K, Alfredsson L, Bjorner JB, Borritz M, et al. Job strain and the risk of stroke: an individual-participant data meta-analysis. Stroke. 2015;46(2):557–9. doi:10.1161/STROKEAHA.114.008019. PMID: 25563644.
- Richardson S, Shaffer JA, Falzon L, Krupka D, Davidson KW, Edmondson D. Meta-analysis of perceived stress and its association with incident coronary heart disease. Am J Cardiol. 2012;110(12):1711–6. doi:10.1016/j.amjcard.2012.08.004. PMID: 22975465.
- Valtorta NK, Kanaan M, Gilbody S, Ronzi S, Hanratty B. Loneliness and social isolation as risk factors for coronary heart disease and stroke: systematic review and meta-analysis of longitudinal observational studies. Heart. 2016;102(13):1009–16. doi:10.1136/heartjnl-2015-308790. PMID: 27091846. PMCID: PMC4941172.
- Schulz R, Beach SR. Caregiving as a risk factor for mortality: the Caregiver Health Effects Study. JAMA. 1999;282(23):2215–9. doi:10.1001/jama.282.23.2215. PMID: 10605972.
- Smyth A, O’Donnell M, Lamelas P, Teo K, Rangarajan S, Yusuf S; INTERHEART Investigators. Physical activity and anger or emotional upset as triggers of acute myocardial infarction: the INTERHEART study. Circulation. 2016;134(15):1059–67. doi:10.1161/CIRCULATIONAHA.116.023142. PMID: 27753614.
- Tsai S-Y, Chi N-F, Wang Y-C, et al. Association of stress hormones and the risk of cardiovascular diseases: a systematic review and meta-analysis. Int J Cardiol Cardiovasc Risk Prev. 2024;23:200305. doi:10.1016/j.ijcrp.2024.200305. PMID: 39319239. PMCID: PMC11420448. Outcome is broad cardiovascular disease, not ASCVD specifically.
- Tawakol A, Ishai A, Takx RAP, Figueroa AL, Ali A, Kaiser Y, et al. Relation between resting amygdalar activity and cardiovascular events: a longitudinal and cohort study. Lancet. 2017;389(10071):834–45. doi:10.1016/S0140-6736(16)31714-7. PMID: 28088338.
- Heidt T, Sager HB, Courties G, Dutta P, Iwamoto Y, Zaltsman A, et al. Chronic variable stress activates hematopoietic stem cells. Nat Med. 2014;20(7):754–8. doi:10.1038/nm.3589. PMID: 24952646.
- Marsland AL, Walsh C, Lockwood K, John-Henderson NA. The effects of acute psychological stress on circulating and stimulated inflammatory markers: a systematic review and meta-analysis. Brain Behav Immun. 2017;64:208–19. doi:10.1016/j.bbi.2017.01.011. PMID: 28089638.
- Miller GE, Chen E, Sze J, Marin T, Arevalo JMG, Doll R, et al. A functional genomic fingerprint of chronic stress in humans: blunted glucocorticoid and increased NF-κB signaling. Biol Psychiatry. 2008;64(4):266–72. doi:10.1016/j.biopsych.2008.03.017. PMID: 18440494.
- Cohen S, Janicki-Deverts D, Doyle WJ, Miller GE, Frank E, Rabin BS, et al. Chronic stress, glucocorticoid receptor resistance, inflammation, and disease risk. Proc Natl Acad Sci U S A. 2012;109(16):5995–9. doi:10.1073/pnas.1118355109. PMID: 22474371.
- Kumari M, Shipley M, Stafford M, Kivimäki M. Association of diurnal patterns in salivary cortisol with all-cause and cardiovascular mortality: findings from the Whitehall II study. J Clin Endocrinol Metab. 2011;96(5):1478–85. doi:10.1210/jc.2010-2137. PMID: 21346074.
- Karl S, Johar H, Ladwig KH, Peters A, Lederbogen F. Dysregulated diurnal cortisol patterns are associated with cardiovascular mortality: findings from the KORA-F3 study. Psychoneuroendocrinology. 2022;141:105753. doi:10.1016/j.psyneuen.2022.105753. PMID: 35395560.
- Ronaldson A, Kidd T, Poole L, Leigh E, Jahangiri M, Steptoe A. Diurnal cortisol rhythm is associated with adverse cardiac events and mortality in coronary artery bypass patients. J Clin Endocrinol Metab. 2015;100(10):3676–82. doi:10.1210/jc.2015-2617. PMID: 26305622. PMCID: PMC4889728.
- Vogelzangs N, Beekman ATF, Milaneschi Y, Bandinelli S, Ferrucci L, Penninx BWJH. Urinary cortisol and six-year risk of all-cause and cardiovascular mortality. J Clin Endocrinol Metab. 2010;95(11):4959–64. doi:10.1210/jc.2010-0192. PMID: 20739384.
- van der Valk ES, Mohseni M, Iyer AM, et al. Long-term glucocorticoid exposure and incident cardiovascular diseases — the Lifelines cohort. J Clin Endocrinol Metab. 2024;109(10):2520–9. doi:10.1210/clinem/dgae081. PMID: 38500477. PMCID: PMC11403319. Outcome is broad CVD.
- Stomby A, Strömberg S, Theodorsson E, Faresjö ÅO, Jones M, Faresjö T. Standard modifiable cardiovascular risk factors mediate the association between elevated hair cortisol concentrations and coronary artery disease. Front Cardiovasc Med. 2022;8:765000. doi:10.3389/fcvm.2021.765000. PMID: 35146006. PMCID: PMC8821522. Cross-sectional mediation analysis; not a SCAPIS analysis.
- Hamer M, Endrighi R, Venuraju SM, Lahiri A, Steptoe A. Cortisol responses to mental stress and the progression of coronary artery calcification in healthy men and women. PLoS One. 2012;7(2):e31356. doi:10.1371/journal.pone.0031356. PMID: 22328931. PMCID: PMC3273460.
- Hajat A, Diez-Roux AV, Sanchez BN, Holvoet P, Bild D, Seeman T, et al. Examining the association between salivary cortisol levels and subclinical measures of atherosclerosis: the Multi-Ethnic Study of Atherosclerosis. Psychoneuroendocrinology. 2013;38(7):1036–46. doi:10.1016/j.psyneuen.2012.10.007. PMID: 23146655. PMCID: PMC4020284.
- Flynn S, Srikanthan P, Ravellette K, Inoue K, Watson K, Horwich T. Urinary cortisol and cardiovascular events in women vs. men: the Multi-Ethnic Study of Atherosclerosis. Am Heart J Plus. 2023;36:100344. doi:10.1016/j.ahjo.2023.100344. PMID: 37982128. PMCID: PMC10655947.
- Crawford AA, Soderberg S, Kirschbaum C, Murphy L, Eliasson M, Ebrahim S, et al. Morning plasma cortisol as a cardiovascular risk factor: findings from prospective cohort and Mendelian randomization studies. Eur J Endocrinol. 2019;181(4):429–38. doi:10.1530/EJE-19-0161. PMID: 31325907. PMCID: PMC6733337.
- Crawford AA, Bankier S, Altmaier E, Barnes CLK, Clark DW, Ermel R, et al. Variation in the SERPINA6/SERPINA1 locus alters morning plasma cortisol, hepatic corticosteroid binding globulin expression, gene expression in peripheral tissues, and risk of cardiovascular disease. J Hum Genet. 2021;66(6):625–36. doi:10.1038/s10038-020-00895-6. PMID: 33469137.
- Pilz S, Theiler-Schwetz V, Trummer C, et al. Associations of serum cortisol with cardiovascular risk and mortality in patients referred to coronary angiography (LURIC). J Endocr Soc. 2021;5(5):bvab017. doi:10.1210/jendso/bvab017. PMID: 33869979. PMCID: PMC8041336.
- Limumpornpetch P, Morgan AW, Tiganescu A, Baxter PD, Nyawira Nyaga V, Pujades-Rodriguez M, et al. The effect of endogenous Cushing syndrome on all-cause and cause-specific mortality. J Clin Endocrinol Metab. 2022;107(8):2377–88. doi:10.1210/clinem/dgac265. PMID: 35486378. PMCID: PMC9282270.
- Reynolds RM, Ilyas B, Price JF, Fowkes FGR, Newby DE, Webb DJ, Walker BR. Circulating plasma cortisol concentrations are not associated with coronary artery disease or peripheral vascular disease. QJM. 2009;102(7):469–75. doi:10.1093/qjmed/hcp057. PMID: 19458201.
- Ortiz R, Kluwe B, Lazarus S, Teruel MN, Joseph JJ. Cortisol and cardiometabolic disease: a target for advancing health equity. Trends Endocrinol Metab. 2022;33(11):786–97. doi:10.1016/j.tem.2022.08.002. PMID: 36266164. PMCID: PMC9676046. Narrative review; cited as a secondary synthesis for glucocorticoid receptor, pre-receptor metabolism and cardiometabolic framework, not as primary evidence for any individual molecular step.
- Ghiadoni L, Donald AE, Cropley M, et al. Mental stress induces transient endothelial dysfunction in humans. Circulation. 2000;102(20):2473–8. doi:10.1161/01.CIR.102.20.2473. PMID: 11076819. Small experimental sample.
- Lima BB, Hammadah M, Kim JH, et al. Association of transient endothelial dysfunction induced by mental stress with major adverse cardiovascular events in men and women with coronary artery disease. JAMA Cardiol. 2019;4(10):988–96. doi:10.1001/jamacardio.2019.3252. PMID: 31509180. PMCID: PMC6739728.
- Sullivan S, Young A, Garcia M, et al. Sex differences in vascular response to mental stress and adverse cardiovascular events among patients with ischemic heart disease. Arterioscler Thromb Vasc Biol. 2023;43(5):e112–e120. doi:10.1161/ATVBAHA.122.318576. PMID: 36857628. PMCID: PMC10164352.
- Hinterdobler J, Schott S, Jin H, et al. Acute mental stress drives vascular inflammation and promotes plaque destabilization in mouse atherosclerosis. Eur Heart J. 2021;42(39):4077–88. doi:10.1093/eurheartj/ehab371. PMID: 34279021. PMCID: PMC8516477. Human data concern leukocyte redistribution; plaque destabilization is mouse evidence.
- Thrall G, Lane D, Carroll D, Lip GYH. A systematic review of the effects of acute psychological stress and physical activity on haemorheology, coagulation, fibrinolysis and platelet reactivity: implications for the pathogenesis of acute coronary syndromes. Thromb Res. 2007;120(6):819–47. doi:10.1016/j.thromres.2007.01.004. PMID: 17321571.
- Wei J, Rooks C, Ramadan R, Shah AJ, Bremner JD, Quyyumi AA, et al. Meta-analysis of mental stress-induced myocardial ischemia and subsequent cardiac events in patients with coronary artery disease. Am J Cardiol. 2014;114(2):187–92. doi:10.1016/j.amjcard.2014.04.022. PMID: 24856319.
- Kivimäki M, Steptoe A. Effects of stress on the development and progression of cardiovascular disease. Nat Rev Cardiol. 2018;15(4):215–29. doi:10.1038/nrcardio.2017.189. PMID: 29213140.
- Hackett RA, Steptoe A, Kumari M. Association of diurnal patterns in salivary cortisol with type 2 diabetes in the Whitehall II study. J Clin Endocrinol Metab. 2014;99(12):4625–31. doi:10.1210/jc.2014-2459. PMID: 25215558.
- Alfredsson L, Hammar N, Fransson E, et al. Job strain and major risk factors for coronary heart disease among employed males and females in a Swedish study on work, lipids and fibrinogen. Scand J Work Environ Health. 2002;28(4):238–48. doi:10.5271/sjweh.671. PMID: 12199425.
- Brindle RC, Pearson A, Ginty AT. Adverse childhood experiences (ACEs) relate to blunted cardiovascular and cortisol reactivity to acute laboratory stress: a systematic review and meta-analysis. Neurosci Biobehav Rev. 2022;134:104530. doi:10.1016/j.neubiorev.2022.104530. PMID: 35031343.
- Salomon RE, Tan KR, Vaughan A, Adynski H, Muscatell KA. Minimally-invasive methods for examining biological changes in response to chronic stress: a scoping review. Int J Nurs Stud. 2020;103:103419. doi:10.1016/j.ijnurstu.2019.103419. PMID: 31945603. PMCID: PMC7067628.
- Chauntry AJ, Diaz KM, Sloan RP, et al. Psychobiological reactivity to acute psychological stress as a predictor of cardiovascular disease and mortality: the Multi-Ethnic Study of Atherosclerosis. Psychoneuroendocrinology. 2026;183:107657. doi:10.1016/j.psyneuen.2025.107657. PMID: 41135261.
- Pan Y, Fan F, Jiang J, Zhang Y. Clinical outcomes of anti-inflammatory therapies inhibiting the NLRP3/IL-1β/IL-6/CRP pathway in coronary artery disease patients: a systematic review and meta-analysis. Inflamm Res. 2025;74:99. doi:10.1007/s00011-025-02058-9. PMID: 40583093. PMCID: PMC12206679.
- Bando S, Fukuda D, Soeki T, et al. Expression of NLRP3 in subcutaneous adipose tissue is associated with coronary atherosclerosis. Atherosclerosis. 2015;242(2):407–14. doi:10.1016/j.atherosclerosis.2015.07.043. PMID: 26282945. NLRP3 measured in subcutaneous adipose tissue; psychological stress not assessed.
- Goodwin JE, Feng Y, Velazquez H, Zhou H, Sessa WC. Endothelial glucocorticoid receptor suppresses atherogenesis — brief report. Arterioscler Thromb Vasc Biol. 2015;35(4):779–82. doi:10.1161/ATVBAHA.114.304525. PMID: 25810297. PMCID: PMC4375730. ApoE-deficient mouse model; not human evidence.
- Levine GN, Lange RA, Bairey-Merz CN, Davidson RJ, Jamerson K, Mehta PK, et al. Meditation and cardiovascular risk reduction: a scientific statement from the American Heart Association. J Am Heart Assoc. 2017;6(10):e002218. doi:10.1161/JAHA.117.002218. PMID: 28963100.
- Levine GN, Cohen BE, Commodore-Mensah Y, Fleury J, Huffman JC, Khalid U, et al. Psychological health, well-being, and the mind-heart-body connection: a scientific statement from the American Heart Association. Circulation. 2021;143(10):e763–83. doi:10.1161/CIR.0000000000000947. PMID: 33486973.
- Levine GN, Carney RM, Cohen BE, et al. Post-myocardial infarction psychological distress: a scientific statement from the American Heart Association. Circulation. 2025;152:e298–e310. doi:10.1161/CIR.0000000000001381. PMID: 40977387. PMCID: PMC12919889.
- Brook RD, Appel LJ, Rubenfire M, Ogedegbe G, Bisognano JD, Elliott WJ, et al. Beyond medications and diet: alternative approaches to lowering blood pressure — a scientific statement from the American Heart Association. Hypertension. 2013;61(6):1360–83. doi:10.1161/HYP.0b013e318293645f. PMID: 23608661.
- Rees K, Takeda A, Court R, Kudrna L, Hartley L, Ernst E. Meditation for the primary and secondary prevention of cardiovascular disease. Cochrane Database Syst Rev. 2024;2(2):CD013358. doi:10.1002/14651858.CD013358.pub2. PMID: 38358047. PMCID: PMC10867897.
- Rogerson O, Wilding S, Prudenzi A, O’Connor DB. Effectiveness of stress management interventions to change cortisol levels: a systematic review and meta-analysis. Psychoneuroendocrinology. 2024;159:106415. doi:10.1016/j.psyneuen.2023.106415. PMID: 37879237.
- Koncz A, Demetrovics Z, Takacs ZK. Meditation interventions efficiently reduce cortisol levels of at-risk samples: a meta-analysis. Health Psychol Rev. 2021;15(1):56–84. doi:10.1080/17437199.2020.1760727. PMID: 32635830.
- Sanada K, Montero-Marin J, Alda Díez M, Salas-Valero M, Pérez-Yus MC, Morillo H, et al. Effects of mindfulness-based interventions on salivary cortisol in healthy adults: a meta-analytical review. Front Physiol. 2016;7:471. doi:10.3389/fphys.2016.00471. PMID: 27807420. PMCID: PMC5069287.
- Dunn TJ, Dimolareva M. The effect of mindfulness-based interventions on immunity-related biomarkers: a comprehensive meta-analysis of randomised controlled trials. Clin Psychol Rev. 2022;92:102124. doi:10.1016/j.cpr.2022.102124. PMID: 35078038.
- Lindsay EK, Marsland AL, Cole SW, et al. Mindfulness-based stress reduction reduces proinflammatory gene regulation but not systemic inflammation among older adults: a randomized controlled trial. Psychosom Med. 2024;86(5):463–72. doi:10.1097/PSY.0000000000001264. PMID: 37982547. PMCID: PMC11098967. Published online 2023.
- Creswell JD, Irwin MR, Burklund LJ, Lieberman MD, Arevalo JMG, Ma J, Breen EC, Cole SW. Mindfulness-Based Stress Reduction training reduces loneliness and pro-inflammatory gene expression in older adults: a small randomized controlled trial. Brain Behav Immun. 2012;26(7):1095–101. doi:10.1016/j.bbi.2012.07.006. PMID: 22820409. PMCID: PMC3635809.
- Brown L, Rando AA, Eichel K, Van Dam NT, Celano CM, Huffman JC, et al. The effects of mindfulness and meditation on vagally mediated heart rate variability: a meta-analysis. Psychosom Med. 2021;83(6):631–40. doi:10.1097/PSY.0000000000000900. PMID: 33395216.
- Hughes JW, Fresco DM, Myerscough R, van Dulmen MHM, Carlson LE, Josephson R. Randomized controlled trial of mindfulness-based stress reduction for prehypertension. Psychosom Med. 2013;75(8):721–8. doi:10.1097/PSY.0b013e3182a3e4e5. PMID: 24127622.
- Blom K, Baker B, How M, Dai M, Irvine J, Abbey S, et al. Hypertension analysis of stress reduction using mindfulness meditation and yoga: results from the HARMONY randomized controlled trial. Am J Hypertens. 2014;27(1):122–9. doi:10.1093/ajh/hpt134. PMID: 24038797.
- Loucks EB, Schuman-Olivier Z, Saadeh FB, et al. Effect of adapted mindfulness training in participants with elevated office blood pressure: the MB-BP study — a randomized clinical trial. J Am Heart Assoc. 2023;12(11):e028712. doi:10.1161/JAHA.122.028712. PMID: 37218591. PMCID: PMC10381983. Multicomponent intervention; investigator commercial interest disclosed.
- Wu F, Brewer LC, Neves VV, Scarpaci MM, Saadeh FB, Proulx JA, Loucks EB. Impact of the mindfulness-based blood pressure reduction (MB-BP) program on cardiovascular health: a randomized clinical trial. Am J Prev Cardiol. 2026;27:101584. doi:10.1016/j.ajpc.2026.101584. PMID: 42291030. PMCID: PMC13261222.
- Anderson JW, Liu C, Kryscio RJ. Blood pressure response to Transcendental Meditation: a meta-analysis. Am J Hypertens. 2008;21(3):310–6. doi:10.1038/ajh.2007.65. PMID: 18311126.
- Bai Z, Chang J, Chen C, Li P, Yang K, Chi I. Investigating the effect of transcendental meditation on blood pressure: a systematic review and meta-analysis. J Hum Hypertens. 2015;29(11):653–62. doi:10.1038/jhh.2015.6. PMID: 25673114.
- Fisher V, Li WW, Malabu U. The effectiveness of mindfulness-based stress reduction (MBSR) on the mental health, HbA1c, and mindfulness of diabetes patients: a systematic review and meta-analysis of randomised controlled trials. Appl Psychol Health Well Being. 2023;15(4):1733–49. doi:10.1111/aphw.12441. PMID: 36855248.
- Castillo-Richmond A, Schneider RH, Alexander CN, Cook R, Myers H, Nidich S, et al. Effects of stress reduction on carotid atherosclerosis in hypertensive African Americans. Stroke. 2000;31(3):568–73. doi:10.1161/01.STR.31.3.568. PMID: 10700487.
- Schneider RH, Grim CE, Rainforth MV, Kotchen T, Nidich SI, Gaylord-King C, et al. Stress reduction in the secondary prevention of cardiovascular disease: randomized, controlled trial of Transcendental Meditation and health education in Blacks. Circ Cardiovasc Qual Outcomes. 2012;5(6):750–8. doi:10.1161/CIRCOUTCOMES.112.967406. PMID: 23149426.
- Norris KC, Salerno J, Bairey Merz CN, Kaushik V, Gelleta S, Castillo A, Nidich S, Gaylord-King C, Schneider RH. A randomized controlled trial of meditation and health education on carotid intima-media thickness and major adverse cardiovascular events in Black men and women. Front Med (Lausanne). 2025;12:1513699. doi:10.3389/fmed.2025.1513699. PMID: 40177279. PMCID: PMC11962031. Trial conducted 2000–2014; registered retrospectively (NCT05642936). Declares no commercial or financial conflict of interest; author institutional affiliations constitute an allegiance concern.
- Gaylord-King C, Harris CL, Xu S, Salerno JW, Walton KG, Bairey-Merz CN, Nidich S, Schneider RH. A multicenter randomized controlled trial of meditation and health education in the prevention of cardiometabolic disease in Black women. J Womens Health. 2025;34(10):1247–56. doi:10.1177/15409996251364663. PMID: 40759176.
- Schneider RH, Norris KC, Brook RD. Transcendental Meditation to combat psychosocial stress, hypertension and cardiovascular disease. Nat Rev Cardiol. 2026;23(1):4–5. doi:10.1038/s41569-025-01235-x. PMID: 41266880. Commentary, not primary outcome evidence; cited to document investigator allegiance. Disclosed conflicts include an author commercial interest.
- Farias M, Maraldi E, Wallenkampf KC, Lucchetti G. Adverse events in meditation practices and meditation-based therapies: a systematic review. Acta Psychiatr Scand. 2020;142(5):374–93. doi:10.1111/acps.13225. PMID: 32820538.
- Landsbergis P, Schnall P. Job strain and coronary heart disease [correspondence]. Lancet. 2013;381(9865):448. doi:10.1016/S0140-6736(13)60242-1. PMID: 23399068.
- Choi B, Schnall P, Ko S, Dobson M, Baker D. Job strain and coronary heart disease [correspondence]. Lancet. 2013;381(9865):448. doi:10.1016/S0140-6736(13)60243-3. PMID: 23399069.
- Kivimäki M, Singh-Manoux A, Nyberg S, Batty GD. Job strain and coronary heart disease — authors’ reply. Lancet. 2013;381(9865):448–9. doi:10.1016/S0140-6736(13)60244-5. PMID: 23399067.
- Hamer M, Steptoe A. Cortisol responses to mental stress and incident hypertension in healthy men and women. J Clin Endocrinol Metab. 2012;97(1):E29–34. doi:10.1210/jc.2011-2132. PMID: 22031509.
- Borén J, Chapman MJ, Krauss RM, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease: pathophysiological, genetic, and therapeutic insights — a consensus statement from the European Atherosclerosis Society Consensus Panel. Eur Heart J. 2020;41(24):2313–30. doi:10.1093/eurheartj/ehz962. PMID: 32052833. PMCID: PMC7308544.
- Spieker LE, Hürlimann D, Ruschitzka F, Corti R, Enseleit F, Shaw S, Hayoz D, Deanfield JE, Lüscher TF, Noll G. Mental stress induces prolonged endothelial dysfunction via endothelin-A receptors. Circulation. 2002;105(24):2817–20. doi:10.1161/01.CIR.0000021598.15895.34. PMID: 12070106.
- Rocha HNM, Batista GMS, Storch AS, Garcia VP, Teixeira GF, Mentzinger J, Gomes EAC, Campos MO, Nóbrega ACL, Rocha NG. Mental stress induces endothelial dysfunction by AT1R-mediated redox imbalance in overweight/obese men. Braz J Med Biol Res. 2023;56:e12547. doi:10.1590/1414-431X2023e12547. PMID: 36995873. PMCID: PMC10041671. Three-way randomized crossover, n = 15; single sex and body-composition stratum.
- Adam EK, Quinn ME, Tavernier R, McQuillan MT, Dahlke KA, Gilbert KE. Diurnal cortisol slopes and mental and physical health outcomes: a systematic review and meta-analysis. Psychoneuroendocrinology. 2017;83:25–41. doi:10.1016/j.psyneuen.2017.05.018. PMID: 28578301. PMCID: PMC5568897. 179 associations from 80 studies to January 2015; overall r = 0.147; cardiovascular-disease subgroup not significant in random-effects analysis.
Verification Note
Quantitative estimates were cross-checked against the primary publication or the cited systematic review wherever available. INTERHEART and INTERSTROKE figures are reported with 99% confidence intervals per the original study designs; all other intervals are 95% unless stated.
Three points of interpretation are flagged for the reader. First, the Tawakol psychometric substudy comprised n = 13 participants, and correlations from that substudy should be treated as exploratory. Second, the trial published in 2025 reports a ten-year hazard ratio of 0.485 with a 95% confidence interval of 0.226–1.044 alongside p = 0.0435; these are internally inconsistent as published, and this review therefore does not describe that result as statistically significant. Third, the Transcendental Meditation hard-endpoint literature (references 65–69) should be read with explicit awareness of researcher allegiance and institutional affiliation; where a financial interest is separately disclosed — as for the MB-BP programme (reference 60) and the 2026 commentary (reference 69) — this is stated, and where trials declare no financial conflict the concern is allegiance rather than undeclared financial interest.
Figures 1A and 6 are schematic representations, not plots of measured data. All other figures plot values reported in the cited primary sources.

