
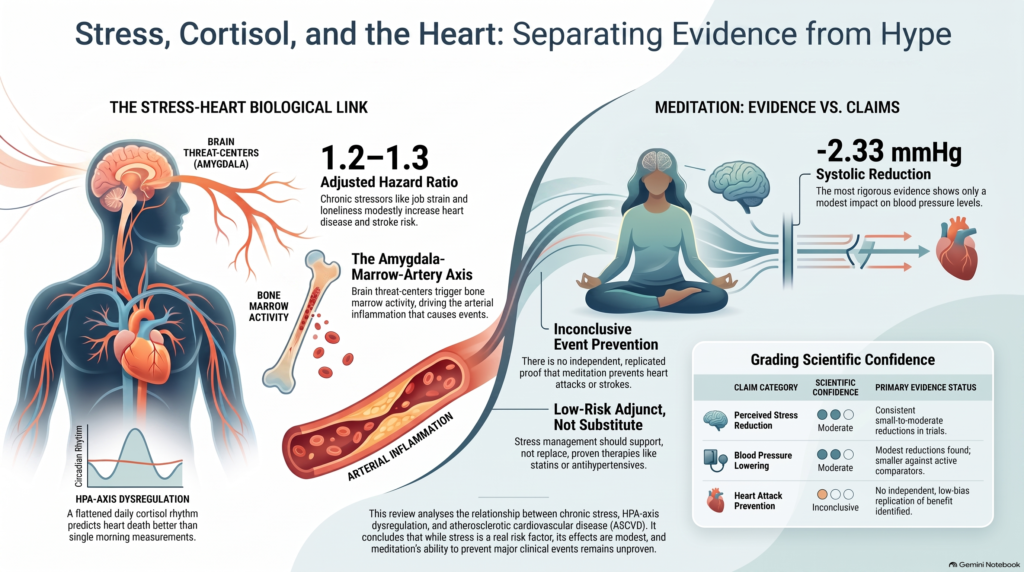
Chronische psychologische stress, HPA-as-dysregulatie en atherosclerotische hart- en vaatziekten: mechanismen, effectgrootte en het bewijs voor op meditatie gebaseerde interventie
Een gestructureerde kritische verhalend overzicht van menselijk en translationeel bewijs
Inhoud
- Abstract
- Kader voor reikwijdte, bronnen en bewijsgradering
- Belangrijkste conclusies
- Wat Vaststaat, Wat Waarschijnlijk Is, en Wat Niet Bekend Is
- Stressfysiologie: De architectuur van de respons
- Cortisol meten: matrices, kinetiek en interpretatievalkuilen
- Epidemiologische bewijzen bij de mens: stressexposities en ASCVD
- Cortisol en ASCVD: Oorzaak, mediator of merker?
- Mechanisme I: Autonoom en hemodynamisch
- Mechanisme II: Ontsteking en Immuniteit
- Mechanisme III: Endotheel en Vasculair
- Mechanisme IV: Metabool
- Mechanisme V: Trombose en Acute Triggering
- Mechanisme VI: Gedragsmediatie
- Mechanistische bewijzenmatrix
- De interventievraag: Taxonomie en de claimladder
- De Benchmark Synthese
- Bewering A: Ervaren stress
- Claim B: Cortisol en HPA-fysiologie
- Claim C: Vastgesteld Risicofactoren
- Claim D: Aderverkalking
- Claim E: Harde klinische gebeurtenissen
- Bewijskwaliteit, vertekening en bijwerkingen
- Geïntegreerd model met bewichtingsfactor per link
- Klinische en preventieve implicaties
- Drempels die deze conclusies zouden veranderen
- Belangrijke onbeantwoorde onderzoeksvragen
- Conclusies: Directe antwoorden op de kernvragen
- Beperkingen van deze beoordeling
- Referenties
1. Samenvatting
Achtergrond. Er wordt vaak beweerd dat chronische psychologische stress hart- en vaatziekten veroorzaakt, en mediteren zou dit juist voorkomen. Beide beweringen worden vaker herhaald dan onderzocht. Het doel van dit overzicht is om nauwkeurig uiteen te zetten wat wordt ondersteund door collegiaal getoetst bewijs, wat biologisch plausibel maar onbewezen is bij mensen, en waar echte onzekerheid blijft bestaan.
Methoden. Gestructureerd kritisch literatuuroverzicht van aan peer-review onderworpen literatuur, geïdentificeerd via MEDLINE/PubMed, Scopus, Embase en de Cochrane Library (CENTRAL en CDSR), doorzocht tot 20 augustus 2026, met referentie- en citatieketening. Kwantitatieve claims zijn getraceerd naar een primaire bron of een benoemde systematische literatuurstudie waar mogelijk, voorzien van genummerde verwijzingen in IEEE-stijl. Dit is niet een systematisch literatuuroverzicht: er werd geen protocol geregistreerd, het aantal ontdubbelde records werd niet bewaard en er werden geen formele instrumenten voor risico op vertekening op studieniveau toegepast. Bewijs krijgt door de auteur beoordeelde narratieve betrouwbaarheidscategorieën toegewezen — sterk, matig, beperkt of onbeslist — op basis van expliciete criteria, elk met een opgegeven reden voor een lagere waardering, en er worden doorgaans vijf te onderscheiden beweringen over meditatie gemaakt: (A) vermindert ervaren stress; (B) verandert cortisol of de HPA-fysiologie; (C) verbetert gevestigde risicofactoren; (D) vertraagt meetbare atherosclerose; (E) vermindert harde klinische gebeurtenissen.
Bevindingen. Voor verschillende prospectief bestudeerde psychosociale stressconstructen, gecorrigeerde relatieve associaties met incidentie kransslagaderziekte en ischemisch beroerte liggen doorgaans in de orde van 1,2–1,3, hoewel schattingen variëren na gelang van de definitie van blootstelling en de uitkomst. Dit zijn bescheiden associaties die op schaal van de bevolking niettemin niet-triviaal zijn. Ze zijn niet direct vergelijkbaar met relatieve effecten die worden gerapporteerd voor roken, bloeddruk of cumulatief apolipoproteïne B (apoB) blootstelling, die worden gemeten op verschillende blootstellingsschalen en zijn vastgesteld aan de hand van verschillende ontwerpen; het rangschikken van deze ten opzichte van elkaar vereist een gekalibreerde vergelijking van het absolute risico waaraan dit overzicht zich niet waagt. Patiënt-controle-schattingen zijn aanzienlijk groter (INTERHEART: odds-ratio van 2,17 voor permanente algehele stress, met een populatie-attributabel risico van ≈32,5% voor de gecombineerde psychosociale factor), en de schattingen op basis van de case-crossover-analyse waren nog hoger (oddsratio 2,44 voor myocardinfarct binnen één uur na acute woede), maar deze ontwerpen meten verschillende dingen en zijn niet uitwisselbaar met prospectief risico. Causaal bewijs is matig: het berust op temporaliteit, biologische plausibiliteit, reproducerende experimentele menselijke fysiologie en één baanbrekend hersenbeeldvormingscohort — maar niet op randomisatie, en residuele confounding door sociaaleconomische positie en gedrag kan niet worden uitgesloten. Genetische instrumentatie behoort niet tot deze lijst. De beschikbare Mendeliana randomisatie instrumenten ochtend plasmacortisol, een stroomafwaartse biomarker, geen psychologische stress; dit wordt besproken onder cortisol-causaliteit in Sectie 8.4 en heeft geen gewicht voor de causale status van stress zelf.
Cortisol kan het best worden begrepen als een niet-specifieke biomarker van de HPA- en glucocorticosteroïdfysiologie en een biologisch plausibele mediator. Prospectieve en genetische data zijn verenigbaar met een kleine causale bijdrage aan het cardiovasculaire risico, maar causaliteit binnen het gebruikelijke fysiologische bereik blijft onzeker, en cortisol is zeker niet de enige overbrenger van psychologische stress. dysregulatiekader is beter te verdedigen dan een model van aanhoudend verhoogd circulerend cortisol. Afgevlakte dagcurve, verhoogd avondcortisol, veranderde reactiviteit, glucocorticoïdreceptorresistentie, en een veranderd weefselglucocorticoïdemetabolisme zijn elk geassocieerd met ongunstige fenotypes, hoewel geen enkel HPA-fenotype is vastgesteld als de bepalende cardiovasculaire afwijking — a meta-analyse van de 80 studies vonden vlakkere hellingen die geassocieerd waren met een slechtere gezondheid in het algemeen (r = 0,147), terwijl de subgroep voor cardiovasculaire aandoeningen met willekeurige effecten niet statistisch significant was [78]. In Whitehall II voorspelde een vlakker dagritme cardiovasculaire mortaliteit (hazardratio 1,87, 95% CI 1,32–2,64) terwijl het ochtendcortisolgehalte en de cortisolontwaakingsrespons Niet waar. In LURIC werd een ruwe associatie tussen ochtendserumcortisol en cardiovasculaire mortaliteit (hazard ratio 1,32) tenietgedaan door correctie voor conventionele risicofactoren (0,97).
Meditatie vermindert aantoonbaar de ervaren stress en verlaagt de bloeddruk in beperkte mate. Er is geen overtuigend, onafhankelijk en gerandomiseerd bewijs dat meditatie een hartinfarct, een beroerte of cardiovasculaire sterfte voorkomt. Uit de Cochrane-review uit 2024 (81 gerandomiseerde studies, 6.971 deelnemers, zoekopdracht tot en met november 2021) bleek dat slechts twee vergelijkingen gegevens over cardiovasculaire klinische voorvallen opleverden: op mindfulness gebaseerde interventies versus een inactieve vergelijkingsgroep (één studie, 110 deelnemers; RR 0,94, 95%-betrouwbaarheidsinterval 0,37–2,42; zeer lage zekerheid) en Transcendentaal Meditatie vergeleken met een actieve vergelijkingsgroep (één onderzoek, 201 deelnemers; RR 0,91, 95%-betrouwbaarheidsinterval 0,56–1,49; lage zekerheid). Geen van beide vertoonde een waarneembaar effect. De enige schatting van de systolische bloeddruk met matige zekerheid — Transcendente Meditatie vergeleken met een actieve vergelijkingsgroep — is tevens de kleinste: −2,33 mmHg systolisch.
Interpretatie. Stressmanagement, inclusief meditatie, is een redelijk, risicoarm additief bij richtlijngetrouwe cardiovasculaire preventie, voornamelijk voor de bloeddruk, psychologisch welzijn en gedragsmatige zelfregulatie. Het is geen vervanging voor lipidenverlagend, bloeddrukbehandeling, rookstop, glycemische controle of fysieke activiteit. Beweringen dat meditatie “voorkomt hartaanvallen,” “keert aderverkalking om,” of “normaliseert cortisol om hart- en vaatziekten”de bewijzen overschrijden.
2. Bereik, bronnen en bewijsgraderingskader
2.1 Beantwoorde vragen
Deze review behandelt acht vragen:
- Verhoogt chronische psychologische stress het risico op atherosclerotische hart- en vaatziekten (ASCVD), en zo ja, in welke mate?
- Hoe sterk is het bewijs dat het verband causaal is in plaats van verstoord?
- Welke biologische mechanismen hebben de sterkste mens bewijs, onderscheiden van het sterkste dierlijke of in-vitro bewijs?
- Welke specifieke rol speelt cortisol — oorzaak, mediator, merker of een combinatie hiervan?
- Is verhoogd cortisol op zich pathogeen, of is dysregulatie van de HPA-as een nauwkeuriger model?
- Hoeveel van de associatie tussen stress en ASCVD wordt gemedieerd door bloeddruk, ontsteking, insulineresistentie, adipositas, slaap en gedrag?
- Modificeert meditatie een van deze — en op welk niveau van de bewijshiërarchie?
- Wat is er vandaag de dag wetenschappelijk te rechtvaardigen om te zeggen, en wat vormt een overschrijding?
2.2 Zoekstrategie, bronnen en geschiktheid
Ontwerp. Dit is een gestructureerde kritische narratieve literatuurstudie, geen systematisch literatuuronderzoek. Het onderscheid wordt duidelijk vermeld omdat dit beperkt wat de recensie kan beweren: het kan afwegen, cijfer, en de bewijzen die het heeft geïdentificeerd interpreteren, maar het mag niet beweren dat de literatuur uitputtend is geïnventariseerd.
Databases en datum. MEDLINE/PubMed, Scopus, Embase en de Cochrane Library (CENTRAL en de Cochrane Database of Systematic Reviews) werden doorzocht tot een einddatum van 20 augustus 2026. PubMed Central werd gebruikt om de volledige tekst te verkrijgen en is niet behandeld als een onafhankelijke bibliografische database. Referentielijsten en voorwaartse citatieketening (Google Scholar) werden gebruikt om aanvullende door vakgenoten getoetste onderzoeken te identificeren, met name voor meditatiestudies van na 2021 die niet werden gedekt door de Cochrane-zoekopdracht, die werd afgesloten op 14 november 2021.
Tabel 1. Zoekdomeinen, conceptreeksen en geschiktheid.
| Beoordelingsvraag | Kernconceptreeks (aangepast aan databasesyntaxis) | In aanmerking komende ontwerpen | Belangrijkste uitsluitingen |
| Stress → ASCVD-resultaten | (“psychologische stress” OR “werkbelasting” OR “werkstress” OR “ervaren stress” OR eenzaamheid OR “sociale isolatie” OR “mantelzorgbelasting”) EN (myocardinfarct OF “coronair hartlijden” OF beroerte OF “cardiovasculaire mortaliteit” OF atherosclerose) | Prospectieve cohortstudie, IPD-meta-analyse, patiënt-controleonderzoek, case-crossover, systematische review | Alleen cross-sectionele blootstellings-uitkomstontwerpen; uitsluitend dierlijk |
| Cortisol / HPA → ASCVD-uitkomsten | (cortisol OF “hypothalamus-hypofyse-bijnieras” OF glucocorticoïd OF “cortisol ontwakingsrespons” OF “dagelijks verloop” OF “haarcortisol”) AND (cardiovasculair OF coronair OF beroerte OF mortaliteit OF “coronair slagader calcium | Prospectief cohortonderzoek, Mendeliaanse randomisatie, systematische review, natuurlijke-experiment (Cushing) | Casusbeschrijvingen; farmacologie van exogene steroïden |
| Mechanistische routes | (stress OF cortisol OF catecholamine) EN (ontsteking OF “flow-mediated dilation” OF endotheliale OF hematopoïese OF NLRP3 OF stolling OF “insuline verzet” | Humaan experimentele, prospectieve mechanistische cohort-, translationele studies met menselijke component | Uitsluitend dierproeven, tenzij uitdrukkelijk anders vermeld |
| Meditatie → resultaten | (meditatie OF mindfulness OF MBSR OF “transcendentale meditatie” OF “stressreductie”) AND (“bloeddruk” OF cortisol OF “hartslagvariabiliteit” OF ontsteking OF “intima-media” OF “cardiovasculaire gebeurtenissen”) | Gerandomiseerde gecontroleerde onderzoeken; systematische reviews en meta-analyses van RCT's | Niet-gecontroleerde/eengroepsstudies; niet-ge реценseerd materiaal |
Geschiktheid. Door peer-review getoetste menselijke studies in elke taal, op elke geografische locatie, van elke datum. Wetenschappelijke standpunten van verenigingen worden aangehaald als consensusposities, expliciet gelabeld en nooit als primair bewijs. Niet-gepeer-reviewd materiaal — institutioneel nieuws, tijdschriftenberichten en commentaar van organisaties — werd uitgesloten van de bewijsbasis. Waar volledige teksten achter een betaalmuur stonden, werden kwantitatieve waarden overgenomen uit gepubliceerd samenvattingen en gekruist met indexeringsbronnen; dergelijke gevallen worden vermeld in Sectie 29.
Wat deze recensie niet heeft. Er is vooraf geen protocol geregistreerd. De screening is uitgevoerd door één enkele beoordelaar zonder dubbele onafhankelijke screening. Ontdubbelde aantamallen en een stroomdiagram voor studieselectie zijn niet bewaard gebleven en worden hier om die reden niet gerapporteerd in plaats van retrospectief gereconstrueerd. Formele instrumenten (RoB 2, ROBINS-I, AMSTAR-2) werden niet op studieniveau toegepast; het risico op bias wordt narratief beoordeeld aan de hand van genoemde domeinen. Dit zijn wezenlijke beperkingen, en Sectie 2.5 vermeldt hoe deze de toelaatbare beweringen van het onderzoek inperken.
2.3 Door de auteur beoordeelde categorieën van verhalend vertrouwen
Er worden vier categorieën gebruikt, die worden toegepast op afzonderlijke claims in plaats van op hele literaturen. Dit zijn door de auteur beoordeelde categorieën van narratief zelfvertrouwen, geen GRADE-beoordelingen, en ze zijn niet uitwisselbaar met GRADE-zekerheidsniveaus, zelfs niet waar de woorden overeenkomen.
| Categorie | Criterium |
| Sterk | Consistente bevindingen over meerdere designs, waaronder experimentele humane data of zeer grote prospectieve cohorten; effectrichting stabiel na correctie; aannemelijk mechanisme aangetoond bij mensen |
| Gematigd | Consistente prospectieve associatie of reproduceerbare humane experimentele fysiologie, maar beperkt door residuele verwarrend, weinig incidenten, afhankelijkheid van een enkele studie, of vertrouwen op surrogatenormen |
| Beperkt | Kleine, heterogene of tegenstrijdige humane studies; mechanisme hoofdzakelijk vastgesteld in dier- of celsystemen; effect alleen aanwezig in subgroepen |
| Onbeslist | Geen enkele voldoende ondersvermogen hebbende studie met een laag risico op vertekening beantwoordt de vraag; bestaande gegevens zijn verenigbaar met een reeks conclusies, waaronder geen effect. |
Om deze beoordelingen controleerbaar in plaats van impressionistisch te maken, draagt elke beoordeelde bewering in Tabel 9 een expliciete grond voor degradatie, geput uit zes genoemde domeinen: risico op vertekening, indirectheid, onnauwkeurigheid, inconsistentie, confounding, en publicatiebias.
2.4 Twee onderscheidingen die de hele bespreking structureren
Eerst: de blootstelling-uitkomst-tier. Bewijs dat verbindt ervaren stress naar biomarkers is geen bewijs dat biomarkers verbindt aan risicofactoren, wat geen bewijs is dat risicofactoren verbindt met aderverkalking, wat geen bewijs is dat aderverkalking verbindt met harde resultaten. Elke link moet afzonderlijk worden gelegd. De literatuur ontleent routinematig geloofwaardigheid aan deze niveaus.
Ten tweede: de tijdschaal. Chronische blootstelling die over tientallen jaren werkt en acute triggers die over minuten werken zijn verschillende fenomeningen met verschillende bewijsbasissen (Figuur 4). Een odds ratio van 2,44 voor een myocardinfarct in het uur na acute woede is een uitspraak over kwetsbare plaque het overschrijden van een klinische drempel; het is geen uitspraak over hoe de tandplak gevormd. Het door elkaar halen daarvan vergroot het schijnbare atherogene effect van stress vele malen.
2.5 Wat deze beoordeling wel en niet mag beweren
Omdat het zoeken gestructureerd maar niet systematisch is, hanteert dit overzicht de volgende zelf opgelegde beperkingen, en zijn de secties 22 tot en met 28 zo geschreven dat deze daaraan voldoen:
- Geen ongekwalificeerde afwezigheidsclaims. Beweringen dat er geen trial of studie bestaat, worden geformuleerd als “wij identificeerden geen...” met de zoekdatum eraan toegevoegd.
- Geen claim van volledige dekking. Het woord uitgebreid wordt niet gebruikt om de zoekopdracht te beschrijven.
- Symmetrie van het scepticisme. De bewijsnorm die wordt toegepast op claims over meditatie wordt eveneens toegepast op claims over stress-causaliteit en cortisol-causaliteit. Waar de beoordeling weigert om een afname van gebeurtenissen af te leiden uit een verandering in een biomarker in een interventiestudie, weigert deze eveneens om plaque-progressie af te leiden uit een verandering in een biomarker in een observationeel cohort.
- Cijfers zijn oordelen van de auteur. Ze worden aangeboden als gestructureerde redenering, met vermelding van de redenen voor afwaardering, niet als formele zekerheidsbeoordelingen.
3. Belangrijkste conclusies
- Prospectieve associatie is reëel maar bescheiden. Aangepaste prospectieve schattingen voor verschillende veel bestudeerde psychosociale constructen — taakspanning, ervaren stress, eenzaamheid, sociale isolatie — vallen vaak binnen het geschatte 2–1.3 bereik voor coronaire hartziekte en ischemische beroerte, hoewel individuele schattingen in beide richtingen buiten dit interval vallen. Schattingen rond 1,4–1,6 komen vaker voor in syntheses op basis van alleen gepubliceerde literatuur, minder volledig gecorrigeerde analyses en patiënt-controleonderzoeken, en moeten niet worden gepresenteerd als de prospectieve schatting.
- Patiënt-controle- en patiënt-crossover-schattingen zijn groter en betekenen iets anders. INTERHEART rapporteerde een odds ratio van 17 (99% CI 1,84–2,55) voor permanente algemene stress en een populatie-attributiefracht van ongeveer 32.5% voor de gecombineerde psychosociale factor — niet voor aanhoudende stress alleen [1]; de INTERHEART case-crossover-analyse rapporteerde OR 2,44 (99%, betrouwbaarheidsinterval 2,06–2,89) voor een hartinfarct binnen een uur na boosheid of emotionele ontreddering9]. Beide zijn informatief; geen van beide is een prospectieve incidentieschatting.
- Publicatiebias is gedocumenteerd, niet hypothetisch. Binnen het IPD-Work-consortium had jeostress een hazardratio van 43 (1.15–1.77) in gepubliceerde cohorten versus 1.16 (1.02–1.32) in ongepubliceerde onderzoeken — ongewoon direct bewijs dat de publicatiestatus samenhing met groter gerapporteerde effecten, en een reden om aan het lagere cijfer meer gewicht te hechten [3].
- Cortisol is niet het hele verhaal en is mogelijk niet het belangrijkste verhaal. Circulerend cortisol is in onderzoeken inconsistent gerelateerd aan cardiovasculaire uitkomsten, en het patroon van de resultaten volgt de meetvenster nauwkeuriger volgt dan de biologie (Figuren 2 en 5).
- Ontregeling van de HPA-as is een beter verdedigbaar kader dan aanhoudende hypercortisolemie — maar “dysregulatie” mag niet worden gereduceerd tot één verplicht fenotype. Een afgevlakt dagritme, verhoogd cortisol late avond, veranderde reactiviteit en glucocorticoïde receptorresistentie zijn elk gerapporteerd in ongunstige contexten, maar hun cardiovasculaire prognostische betekenis is niet uniform en berust op cohorten met weinig cardiovasculaire gebeurtenissen. Wat het bewijs niet ondersteunt, is een algemeen model waarin chronische psychologische stress betrouwbaar continu verhoogd circulerend cortisol produceert.
- Ontsteking en hematopoëtische signaaloverdracht behoren tot de meest coherente menselijke mechanistische trajecten — meer nog dan cortisol. Het traject amygdala → beenmerg → arteriële ontsteking → gebeurtenissen, dat is aangetoond in één beeldvormingscohort met 22 gebeurtenissen, is naar het oordeel van dit overzicht een van de meest geïntegreerde beschikbare datasets bij mensen die de verbinding tussen hersenen en slagaders weergeven — waarbij de beenmergactiviteit 46% van de relatie tussen de amygdala–arteriële ontsteking bemiddelt, en waarbij arteriële ontsteking 39% van de relatie tussen de amygdala en de gebeurtenis bemiddelt [11].
- Gedrag maakt deel uit van het causale systeem, geen storende variabele. Omdat chronische stress kan bijdragen aan roken, inactiviteit, slecht slapen en therapieontrouw, kan het statistisch corrigeren hiervoor het totale effect van stress onderschatten — hoewel het daarmee geen direct biologisch effect isoleert, waarvoor formele mediatieanalyse.
- Het bewijs voor meditatie zwakt sterk af van bewering A tot bewering E (Figuur 8). Ervaren stress: matig. Cortisol: beperkt tot matig, en grotendeels beperkt tot risicogroepen. Bloeddruk: matig, en kleiner dan vaak wordt gerapporteerd zodra actieve vergelijkers worden gebruikt. Atherosclerose: beperkt en niet-conclusief — een vroege positieve cIMT-studie kende aanzienlijke uitval, en een latere gerandomiseerde studie in een andere populatie liet geen cIMT-voordeel tussen de groepen zien. Harde eindpunten: niet-conclusief.
- De keuze van de vergelijker is van wezenlijke invloed op het antwoord. In de Cochrane-synthese gaat elke grote schatting van de bloeddruk gepaard met ofwel een I² ≥ 87%, ofwel minder dan 150 deelnemers; de enige schatting van de systolische bloeddruk met matige zekerheid bedraagt −2,33 mmHg (figuur 7).
- Loyaliteit van de onderzoeker is een belangrijke potentiële bron van vertekening in deze literatuur, in het bijzonder bij Transcendentaal Meditatie-onderzoek, waar de enige onderzoeken die voordelen op het gebied van harde eindpunten rapporteren afkomstig zijn van één enkele institutioneel gelieerde onderzoeksnetwerk. Dit is een reden om onafhankelijke replicatie te eisen, niet op zich bewijs dat partijdigheid de gerapporteerde effecten heeft veroorzaakt.
4. Wat vaststaat, wat waarschijnlijk is en wat niet bekend is
Vastgesteld (sterk bewijs). Verschillende psychosociale stressconstructen worden geassocieerd met cardiovasculaire events in prospectieve en case-control-studies, terwijl beeldvormend onderzoek bij de mens en mechanistische studies ondersteunend bewijs leveren voor geselecteerde intermediaire pathways. Acute mentale stress produceert een reproduceerbare, voorbijgaande stoornis van endotheelfunctie zowel bij gezonde volwassenen als bij patiënten met een oogaandoening. Acute emotionele stress kan leiden tot cardiaque voorvallen bij mensen die al ziek zijn. Pathologisch hypercortisolisme — het syndroom van Cushing — veroorzaakt hypertensie, dysglykemie, visceraale adipositas, dyslipidemie en premature cardiovasculaire sterfte. Meditatie verlaagt de ervaren stress en verlaagt de bloeddruk in bescheiden mate. Chronische stress wordt bij mensen geassocieerd met een veranderde leukocytenbiologie.
Waarschijnlijk (matig bewijs). Een causale bijdrage van gewone chronische stress aan cardiovasculair risico. (Direct menselijk bewijs voor door stress geïnduceerde plaque initiatie of progressie is materieel zwakker dan het bewijs voor klinische events, bloeddrukroutes, endotheliale responsen en acute uitlokking, en is beoordeeld als Beperkt–Matig.) De amygdala-beenmerg-slagader-as. Ontsteking als mediator. Dagritme-cortisoldysregulatie als voorspeller van cardiovasculaire mortaliteit. Cortisol als een mogelijk causale bijdrage — genetisch bewijs is verenigbaar met een klein effect, maar is statistisch niet conclusief. Gedragsmatige mediatie is waarschijnlijk belangrijk, maar het aandeel van de totale associatie dat toe te schrijven is aan gedragsmatige trajecten is niet vastgesteld.
Beperkt of onzeker. Of meditatie cortisol aanzienlijk verandert buiten risicopopulaties. Of meditatie atherosclerose vertraagt. De onafhankelijke klinische waarde van elke circulerende cortisolmeting voor risicostratificatie van cardiovasculaire aandoeningen. Of de specifieke NLRP3/IL-1β-as effecten van psychologische stress bij mensen bemiddelt, onderscheiden van het algemeen bemiddelen van atherosclerose. De proportionele bijdrage van directe neuroendocriene schade versus indirecte gedragsmatige trajecten.
Onbeslist. Of elke stressreducerende interventie vermindert harde cardiovasculaire events. We vonden geen adequaat gepowerde, laag-bias, onafhankelijk uitgevoerde trial in onze zoektocht tot 20 augustus 2026. Dit is de centrale hiaten in het veld.
5. Stressfysiologie: De Architectuur van de Respons
5.1 Centrale beoordeling
Psychologische stress hangt niet simpelweg af van een externe prikkel, maar van de beoordeling door de hersenen van dreiging, belasting, voorspelbaarheid en copingsbronnen. Dreigingssignalen worden verwerkt in gedistribueerde cortico-limbische circuits — prefrontale cortex, amygdala, hippocampus, insula — waarin prefrontale, limbische, insulaire en hypothalamische netwerken gezamenlijk de beoordeling van en reactie op dreiging reguleren, waarbij prefrontale regulatie in staat is de output van de amygdala te moduleren en bij te dragen aan het beëindigen van de reactie zodra een dreiging is geweken. Chronische psychologische tegenslag wordt geassocieerd met een verschuiving in dit evenwicht naar aanhoudende amygdala-activiteit ten opzichte van prefrontale regulatie [11,37Vanaf de amygdala en de hypothalamische paraventriculaire kern dalen twee effectortakken af.
5.2 De sympathisch-adrenomedullaire as
De SAM-as reageert binnen enkele seconden. Sympathische outflow en afscheiding door het bijniermerg verhogen circulerend epinephrine en norepinephrine, waardoor hartslag, contractiliteit en perifeer vaatweerstand, terwijl de parasympathische (vagale) toon wordt afgebouwd. Dit wordt vaak weerspiegeld in veranderingen in vagale gemedieerde hartslagvariabiliteit, hoewel HRV ook wordt beïnvloed door ademhaling, houding en opnameomstandigheden en geen een-op-een weergave is van nervus vagus-tonus. Naast de hemodynamiek werkt catecholaminesignalering direct in op immuun- en hematopoëtische compartimenten — een punt dat in paragraaf 10 wordt uitgewerkt.
5.3 De hypothalamus-hypofyse-bijnieras-as
De HPA-as werkt in minuten tot uren. Paraventriculaire neuronen scheiden corticotropine-vrijmakend hormoon en af arginine vasopressine in de hypofysaire portale circulatie; CRH stimuleert hypofysecorticotrofen om adrenocorticotroop hormoon te scheiden; ACTH bindt aan melanocortine-2-receptoren in de zona fasciculata van de bijnier, wat de omzetting stimuleert van cholesterol tot cortisol. Cortisol oefent vervolgens een negatieve terugkoppeling uit op zowel hypofyse- als hypothalamusniveau.
Op de korte termijn is dit adaptief. Cortisol mobiliseert energiasubstraten, versterkt de vasculaire reactiviteit op catecholaminen en remt de immuunrespons. De pathologische vraag is nooit of deze systemen activeren — dat moeten ze — maar of herhaalde activatie, mislukt herstel, een veranderd circadiaan ritme of een veranderde receptorresponsiviteit een aanhoudende allostatische belasting genereert.
5.4 Recepturbiologie: twee receptoren, niet één
Cortisol bindt aan twee intracellulaire nucleaire receptoren met aanzienlijk verschillende affiniteiten:
- De mineralocorticoïdreceptor (MR, type I) heeft een hoge affiniteit en is bij basale cortisolconcentraties aanzienlijk bezet.
- De glucocorticoïdreceptor (GR, type II) heeft een lagere affiniteit en is voornamelijk betrokken tijdens door stress geïnduceerde pieken en de ochtendpiek.
Deze architectuur met twee receptoren is klinisch van belang. Onder aanhoudend glucocorticoïdoverschot wordt verondersteld dat de renale MR-bezetting door cortisol — die normaal gesproken wordt beperkt door prereceptor-metabolisme, zie hieronder — natriumretentie, volumetoename en hypertensie bevordert [30Dit is één beschreven route waarlangs een overmaat aan glucocorticoïden een hemodynamisch probleem kan worden.
5.5 Pre-receptormetabolisme: de weefselniveau-versterker
Circulerend cortisol is een slechte maatstaf voor het cortisol dat een bepaalde weefsel daadwerkelijk ervaart, omdat twee enzymen de lokale blootstelling onafhankelijk van de plasmaconcentratie moduleren:
- 11β-HSD1, overvloedig aanwezig in lever- en visceraal vetweefsel, regenereert actief cortisol uit inactief cortison. Het versterkt intracellulaire glucocorticosteroïdsignalering, gluconeogenese en visceraal vet afzetting zelfs wanneer het plasmacortisol normaal is [30].
- 11β-HSD2, tot uitdrukking gebracht in het aldosterongevoelige distale nefron, inactiveert cortisol tot cortison, waardoor de renale MR wordt beschermd tegen binding door cortisol [30].
De praktische implicatie is dat een normaal serumcortisol een glucocorticoidoverschot op weefselniveau niet uitsluit. Dit is een wezenlijke beperking van elke klinische strategie die is gebaseerd op het meten van circulerend cortisol.
5.6 De circadiaanse architectuur
Onder niet-gestresste omstandigheden volgt cortisol een uitgesproken circadiaan ritme dat wordt aangestuurd door de suprachiasmaticus: een scherpe stijging die ongeveer 30-45 minuten na het ontwaken een piek bereikt (de cortisolontwaakingsrespons, CAR), een steile daling gedurende de dag, en een dieptepunt rond middernacht (Figuur 1A). Het ritme — de amplitude, de helling en het tijdstip van het dieptepunt — bevat informatie die een enkele waarde niet kan bevatten.
5.7 Waarom “chronische stress produceert veel cortisol” onjuist is
Dit is de allerbelangrijkste correctie in deze beoordeling. Chronische stress doet niet betrouwbaar aanhoudend verhoogde cortisol produceren. Afhankelijk van de chroniciteit, timing, ontwikkelingsgeschiedenis en receptorgevoeligheid kan dit hypercortisolisme, hypocortisolisme, een afgevlakte CAR, een overdreven CAR of een vlakker dagelijks verloop met verhoogde cortisolwaarden aan het einde van de dag of op het laagste punt — fenotypes die geassocieerd worden met ongunstige gezondheidsuitkomsten in verschillende cohorten, maar zonder uniform consistente cardiovasculaire associaties in meta-analyse [78].
Drie verdere waarnemingen completeren het beeld:
Afgestompte reactiviteit is niet per se veerkracht. Meta-analyse van negatieve jeugdervaringen vindt afgestompt in plaats van overmatige cortisol- en cardiovasculaire stressreactiviteit40]. Lage reactiviteit in die context weerspiegelt ontregeling, geen robuustheid. In MESA, een afgevlakte reactiviteit van de diastolische bloeddruk op acute stress voorspelde vroegtijdige sterfte door alle oorzaken [42]. Een afgevlakte reactiviteit is daarom geen bewijs van veerkracht; maar de prognostische implicaties variëren per fysiologische maatstaf en populatie, en deze gegevens vormen geen bewijs voor een algemene U-vormige regel voor HPA- en cardiovasculaire reacties.
Glucocorticoïdreceptorresistentie ontkoppelt cortisol van zijn effect. Bij chronisch gestreste mantelzorgers kunnen de speekselcortisolprofielen vergelijkbaar zijn met die van controles, terwijl monocyten een verminderde glucocorticoïd-responsieve transcriptie, een verhoogde NF-κB-gerelateerde transcriptie en hogere ontstekingsmarkers vertonen [14,15]. Er zijn verschillende moleculaire mechanismen voorgesteld die de GR-gevoeligheid veranderen, waaronder veranderingen in receptorexpressie, verminderde ligandbinding en nucleaire translocatie, co-chaperonregulatie van receptoromzet en epigenetische modificatie op loci zoals FKBP5. Verschillende van deze details zijn primair afkomstig van mechanistisch en translationeel onderzoek in plaats van van directe cardiovasculaire experimenten bij de mens [30], en ze worden hier vermeld als kandidaat-mechanismen in plaats van als aangetoonde stappen in een menselijke route.
Dit lost de centrale paradox op. Cortisol is ontstekingsremmend, maar chronische stress is pro-inflammatoir. Een mechanisme dat dit deels kan verklaren is een verminderde glucocorticosteroïdgevoeligheid in geselecteerde immuuncelpopulaties — het doelweefsel luistert minder goed. Het is a kandidaatoplossing, geen aangetoonde universele eigenschap van chronische stress. Volgens deze opvatting verloopt ontsteking niet ondanks adequaat cortisol, maar omdat adequaat cortisol minder effectief wordt getransduceerd — terwijl door catecholamines en het sympatisch zenuwstelsel aangedreven pro-inflammatoire hematopoëse in dezelfde richting duwt. Chronische ontstekingen bij gestreste populaties zijn echter multifactorieel: slaap, adipositas, metabole status, infectie en gedrag dragen allemaal bij, en glucocorticoïdresistentie is één bijdrager tussen verscheidene.
De exacte formulering is daarom stress → HPA-asdysregulatie, geen stress → hoog cortisol.
Figuur 1. Het dagelijkse cortisoly പാttern kan informatiever zijn dan een enkel ochtendniveau voor de cardiovasculaire prognose. Paneel A is een schema van karakteristieke fenotypes, geen gemeten gegevens. Paneel B rapporteert waargenomen hazard ratios; in Whitehall II voorspelden ochtendcortisol en de cortisolontwaakreactie de mortaliteit niet.
6. Het meten van cortisol: matrices, kinetiek en interpretatieve valkuilen
Een deel van de kennelijke tegenstrijdigheid in de literatuur over cortisol en ASCVD weerspiegelt verschillen in afnametijdvenster en matrix in plaats van biologische meningsverschillen — hoewel confounding, ziektetoestand, medicatie, populatieheterogeniteit en analytische keuzes hier ook aan bijdragen [41] (Figuur 2).
Figuur 2. Cortisolbiomarkers meten verschillende dingen over verschillende tijdsbestekken. Een enkel ochtendserumcortisol legt één tijdstip vast in een systeem met een uitgesproken circadiaans ritme; een deel van de inconsistentie in deze literatuur weerspiegelt die mismatch, naast echte biologische heterogeniteit.
Tabel 2. Cortisolmeetmatrices.
| Matrix | Venster vastgelegd | Wat het meet | Belangrijkste sterke punten | Belangrijkste beperkingen |
| Serum / plasma, enkele trekking | Enkel meetmoment | Totaal cortisol (gebonden + vrij) | Alom verkrijgbaar; gestandaardiseerde bepalingen | Acutesinds zeer gevoelig voor stress door venapunctie en afnametijd; beïnvloed door corticosteroïd-bindend globuline; een slechte index van chronische blootstelling |
| Speeksel-, multisample | Uren tot een dag | Vrij, biologisch actief cortisol | Niet-invasief; maakt CAR en diurnale helling mogelijk; herhaalbaar | Afhankelijk van therapietrouw; gevoelig voor nauwkeurigheid van het ontwaaktijdstip, voeding en roken |
| 24-uurs urinair vrij cortisol | 1 dag | Geïntegreerde dagelijkse uitscheiding van vrij cortisol | Integreert over de dag; niet beïnvloed door ruis van een enkel tijdstip | Verzamelfouten komen vaak voor; beïnvloed door nierfunctie; één dag is mogelijk niet representatief voor de chronische toestand |
| Haarcortisol / cortison | Weken tot maanden (conventioneel ≈1 cm proximaal hoofdhaar ≈ 1 maand, met aanzienlijke biologische en assay-variabiliteit) | Cumulatieve systemische blootstelling | Een nuttige geïntegreerde glucocorticoïde biomarker voor de langere termijn, hoewel standaardisatie en klinische interpretatie onvolledig blijven | Beïnvloed door haarbiologie, kleur, wassen en cosmetische behandeling; assay-heterogeniteit; klinische schaling niet vastgesteld |
Hieruit volgen drie interpretatieve consequenties.
Ten eerste, een enkel ochtendserumcortisol is een zwakke marker voor chronische stress [41], en studies die dit gebruiken, mogen niet worden behandeld als het testen van dezelfde hypothese als studies die diurnale speekselprofielen of haarglucocorticoïden gebruiken. Eén goed uitgevoerde cross-sectionele studie vond geen associatie tussen circulerend plasmacortisol en coronaire of perifere hart- en vaatziekten [29] — een bevinding die de klinische bruikbaarheid van een eenmalige cortisolmeting beperkt, in plaats van de bredere stresshypothese te weerleggen.
Ten tweede, de vorm van het gerapporteerde effect volgt de matrix. In Figuur 5 zijn de grootste puntschattingen afkomstig van geïntegreerde blootstellingsmaten in kleine cohorten met weinig incidenten; de meest precieze schattingen zijn afkomstig van gepoolde metingen op een enkel tijdstip met bescheiden effecten. Dit patroon is verenigbaar met meetverschillen en onnauwkeurigheid van kleine studies, inclusief potentiële inflatie door kleine studies of winner’s-curse-effecten, maar identificeert op zichzelf niet de werkelijke causale effectgrootte.
Ten derde, cortison presteert mogelijk beter dan cortisol in het haar. In het Lifelines-cohort was haarcortison — maar niet haarcortisol — onafhankelijk geassocieerd met incidentele hart- en vaatziekten, het sterkst bij deelnemers onder de 60 (odds ratio 4,21, 95% BI 1,91–9,07 per log₁₀-eenheid) [20]. De bevinding is biologisch interessant en vereist replicatie voordat er klinische conclusies kunnen worden getrokken.
7. Menselijk epidemiologisch bewijs: stressexposities en ASCVD
Figuur 3 toont de belangrijkste schattingen. Deze sectie legt uit wat elke schatting bijdraagt en waar de zwakke punten liggen.
Figuur 3. Psychosociale blootstellingen en atherosclerotische cardiovasculaire uitkomsten. Het onderzoeksontwerp bepaalt de interpretatie. Veel gecorrigeerde prospectieve schattingen voor CHD en ischemische beroerte vallen in het bereik van ongeveer 1,2–1,4, hoewel individuele prospectieve schattingen buiten dat interval liggen. INTERHEART- en INTERSTROKE-intervallen zijn 99% BI zoals gerapporteerd.
7.1 Case-control bewijs: INTERHEART en INTERSTROKE
INTERHEART omvatte 11.119 gevallen van een eerste myocardinfarct en 13.648 controles in 52 landen. Permanente algemene stress vertoonde een odds ratio van 2,17 (99% BI 1,84–2,55); meerdere perioden van stress, 1,45; financiële stress, 1,33; stressvolle levensgebeurtenissen, 1,48; depressie, 1,55. Een hoge interne locus of control werkte beschermend (0,68). Los daarvan was de gecombineerde psychosociale factor — niet permanente algemene stress alleen — verantwoordelijk voor een populatie-attributief risico van ongeveer 32.5% voor het myocardinfarct, en het patroon was consistent in verschillende regio's, geslachten en etnische groepen. De associatie bleef bestaan na correctie voor inkomen en opleiding [1].
INTERSTROKE, die dezelfde architectuur gebruikte voor acute beroerte, vond psychosociale stress met een odds ratio van 1,30 (99% BI 1,06–1,60) en depressie met 1,35 (99% BI 1,10–1,66) [2]. Merk op dat beide studies 99% rapporteren in plaats van 95% betrouwbaarheidsintervallen volgens ontwerp; de intervallen zijn daarom breder dan ze anders zouden lijken.
De beperking is structureel en onvermijdbaar. In een case-control studie van het myocardinfarct wordt de stressexpositie vastgesteld na het voorval, bij mensen die net een hartaanval hebben gehad en op zoek zijn naar een verklaring. Vaststelling na het voorval creëert een risico op differentiële herinnering die associaties zou kunnen opblazen, hoewel de richting en omvang ervan niet zomaar kunnen worden aangenomen. De consistentie van INTERHEART in 52 landen versterkt de generaliseerbaarheid, maar consistentie over regio's heen sluit differentiële herinnering niet uit. Een goed opgezette case-control studie kan valide een odds ratio voor blootstelling schatten, en bij een incidentie-dichtheidssteekproef schat die odds ratio een incidentie-ratio. Wat het ontwerp niet doet, is de populatie-incidentie direct meten, en het blijft kwetsbaar voor differentiële retrospectieve vaststelling van blootstelling. Dit is de reden waarom het getal van 2,17, hoewel veel geciteerd, niet als ankerpunt voor het gevoel van omvang van de lezer zou moeten dienen.
7.2 Werkgerelateerde belasting
De IPD-Work consortium voegde individuele deelnemersgegevens van 13 Europese cohorten samen: 197.473 aanvankelijk ziektevrije werknemers, 2.358 incidentele coronaire voorvallen, gemiddeld 7,5 jaar follow-up. Werkbelasting — hoge psychologische belasting gecombineerd met lage beslissingsruimte — vertoonde een hazard ratio van 1,23 (95% BI 1,10–1,37), met een populatie-attributief risico van ongeveer 3,4% [3].
Twee kenmerken van deze analyse zijn leerzamer dan het headline-getal.
Ten eerste, een punt van precisie dat meestal verloren gaat in secundaire citaten: de headline hazard ratio van 1,23 is gecorrigeerd voor alleen geslacht en leeftijd. Het consortium rapporteerde afzonderlijk dat de associatie ook aanwezig was na correctie voor sociaaleconomische status en voor levensstijl en conventionele risicofactoren, en in analyses waarin voorvallen in de eerste drie jaar (HR 1,31; 1,15–1,48) en vijf jaar (HR 1,30; 1,13–1,50) van de follow-up werden uitgesloten om omgekeerde causaliteit. Het effect is robuust over de verschillende specificaties heen, maar de veel geciteerde 1,23 mag niet worden omschreven als volledig gecorrigeerd voor risicofactoren.
Ten tweede, en waardevoller, het consortium vergeleek eerder gepubliceerde met eerder niet-gepubliceerde cohorten. De hazard ratio in eerder gepubliceerde cohorten was 1.43 (1.15–1.77); in eerder niet-gepubliceerde cohorten was dit 1.16 (1.02–1.32). This provides unusually direct evidence that publication status was associated with effect-size differences within a single consortium — though the contrast may also reflect factors correlated with publication status rather than publication bias alone. It is also specific to the job-strain corpus and should not be assumed to hold at the same magnitude in other stress literatures. It may nonetheless help explain part of the discrepancy between reviews reporting 1.2–1.4 and those reporting 1.4–1.6 — the latter are, in substantial part, reading the published literature at face value.
The opposite criticism has also been made, and should be recorded. Published correspondence argued that the constituent cohorts carry unacknowledged biases toward the null — single-occasion exposure measurement, healthy-worker selection, and loss of exposure contrast across follow-up — such that both 1.23 and the 3.4% population-attributable risk may themselves be underestimates [71,72]. The consortium replied defending its estimates [73]. This review does not adjudicate between the two critiques. It notes that the point estimate is bracketed by credible arguments in both directions, which is a further reason to treat 1.2–1.4 as a range rather than a measurement.
For stroke, the meta-analytic estimate was RR 1.22 (1.01–1.47) overall and 1.58 (1.12–2.23) for ischaemic stroke, while the more conservative individual-participant analysis gave HR 1.09 (0.94–1.26) for total stroke and 1.24 (1.05–1.47) for ischaemic stroke [4,5]. The ischaemic-specific signal is the more consistent of the two.
7.3 Perceived stress
Pooling six prospective cohorts and 118,696 participants, high perceived stress carried a risk ratio of 1.27 (95% CI 1.12–1.45) for incident coronary heart disease [6]. The exposure instruments varied across studies, which limits precision but also means the finding is not an artefact of one questionnaire.
7.4 Loneliness and social isolation
Across 16 longitudinal datasets and more than 181,000 adults, loneliness and social isolation carried RR 1.29 (1.04–1.59) for coronary heart disease and RR 1.32 (1.04–1.68) for stroke [7]. These estimates sit within the same band as job strain and perceived stress despite measuring a conceptually distinct exposure. That supports a broader psychosocial-risk association, but similarity between distinct constructs does not by itself constitute causal replication or imply a shared mechanism.
7.5 Caregiver strain
In the Caregiver Health Effects Study, 392 spousal caregivers aged 66–96 were followed alongside 420 non-caregiving controls. Caregivers reporting mental or physical strain had a 63% higher four-year all-cause mortality (RR 1.63, 95% CI 1.00–2.65) after adjustment for age, sex, health status, and subclinical disease [8]. The lower confidence bound touches 1.00, and the outcome is all-cause rather than cardiovascular mortality; the study is best read as corroborating rather than as independently establishing.
7.6 Acute triggering
De INTERHEART case-crossover analysis of 12,461 first myocardial infarctions found that anger or emotional upset in the preceding hour was associated with OR 2,44 (99%, betrouwbaarheidsinterval 2,06–2,89), with a population-attributable risk of 8.5% [9]. The within-person design controls for time-invariant confounders — genetica, socioeconomic position, chronic behaviour — which is a substantial methodological advantage over cohort designs. It does not control time-varying confounders, nor differential recall of what occurred during the hazard period.
But it answers a different question. The comparison is between one hour and another hour in the same person, whose coronary anatomy is identical in both. It establishes that a transient physiological state can precipitate an event in existing disease. It says nothing about atherogenese. Related evidence — takotsubo cardiomyopathie, population spikes in cardiac events after earthquakes and during emotionally charged sporting events, case-crossover data on anger and heavy exertion — belongs to this same category (Figure 4).
Figure 4. Two distinct timescales that are routinely conflated. Acute triggering is evidence that a transient physiological state can push pre-existing disease across the clinical threshold; it is not evidence that stress builds plaque.
7.7 Synthesis
Table 3. Human epidemiologic evidence linking stress exposures to ASCVD outcomes.
| Studie | Design / N | Exposure | Outcome / follow-up | Effect (95% CI unless noted) | Key limitation | Cijfer |
| INTERHEART, 2004 | Case-control; 24,767; 52 countries | Self-reported permanent stress, financial stress, life events | Acute MI | OR 2.17 (99% CI 1.84–2.55) permanent stress; combined psychosocial PAR ≈32.5% | Recall bias inherent to design | Gematigd |
| INTERSTROKE, 2010 | Case-control; 22 countries | Psychosocial stress; depression | Acute stroke | OR 1.30 (99% CI 1.06–1.60); depression 1.35 (1.10–1.66) | Same design limitation | Gematigd |
| IPD-Work, 2012 | IPD meta-analysis, 13 cohorts; 197,473; 2,358 events | Job strain (demand–control) | Incident CHD; mean 7.5 y | HR 1.23 (1.10–1.37); PAR ≈3.4% | Published cohorts 1.43 vs unpublished 1.16 | Gematigd |
| Huang et al., 2015 | Meta-analysis, 6 cohorts; 138,782 | Job strain | Incident stroke | RR 1.22 (1.01–1.47) total; 1.58 (1.12–2.23) ischaemic | Fewer cohorts; heterogeneous ascertainment | Gematigd |
| Fransson et al., 2015 | IPD meta-analysis | Job strain | Incident stroke | HR 1.09 (0.94–1.26) total; 1.24 (1.05–1.47) ischaemic | Null for total stroke | Gematigd |
| Richardson et al., 2012 | Meta-analysis, 6 cohorts; 118,696 | Perceived stress scales | Incident CHD | RR 1.27 (1.12–1.45) | Instrument heterogeneity | Gematigd |
| Valtorta et al., 2016 | Meta-analysis, 16 datasets; >181,000 | Loneliness / social isolation | CHD and stroke | RR 1.29 (1.04–1.59) CHD; 1.32 (1.04–1.68) stroke | Exposure definition varies | Gematigd |
| Schulz & Beach, 1999 | Prospective cohort; 812 | Caregiver strain | 4-y all-cause mortality | RR 1.63 (1.00–2.65) | All-cause outcome; CI touches null; no biomarkers | Gematigd |
| INTERHEART trigger, 2016 | Case-crossover; 12,461 MI cases | Anger / upset in prior hour | MI onset | OR 2.44 (99% CI 2.06–2.89); PAR 8.5% | Post-MI recall; triggering ≠ atherogenesis | Moderate–Strong for triggering |
The synthesis is straightforward, with its scope stated. For several prospectively studied psychosocial constructs and CHD or ischaemic-stroke outcomes, adjusted estimates commonly fall in the approximate 1.2–1.4 range. That statement does not extend to every prospective entry in Table 3 — total stroke in the IPD analysis was 1.09, and the caregiver estimate of 1.63 is for all-cause mortality. They are directionally robust, replicated across exposures and populations, and consistent enough that sampling variation alone is unlikely to explain the pattern. They are also modest, vulnerable to residual confounding by socioeconomic position and behaviour, and, in the occupational literature, published cohorts produced materially larger estimates than unpublished cohorts.
A caution on calibration: it is tempting to rank this magnitude against smoking, established hypertension, or cumulative apoB exposure, but relative effects estimated on different exposure scales, over different induction periods, and by different designs are not directly commensurable. What can be said is that job strain’s population-attributable risk in IPD-Work was approximately 3.4%, which the investigators themselves described as substantially smaller than that of standard risk factors [3] — a comparison made within a single analysis rather than across literatures.
8. Cortisol and ASCVD: Cause, Mediator, or Marker?
Figure 5 arrays the principal estimates. What follows is the case for each interpretation and the resolution.
Figure 5. Cortisol measures and cardiovascular outcomes. Because exposure scales, cortisol matrices and outcomes differ, point estimates should not be compared quantitatively across rows. Estimates in grey cross the null. The largest point estimates come from the studies with the fewest events and the widest confidence intervals.
8.1 Diurnal rhythm
Whitehall II followed 4,047 civil servants for a mean of 6.1 years (139 deaths, 32 cardiovascular). A flatter diurnal cortisol slope predicted all-cause mortality (HR 1.30 per 1 SD reduction in slope steepness, 95% CI 1.09–1.55) and, more strongly, cardiovascular death (HR 1.87, 95% CI 1.32–2.64), independent of covariates. Morning cortisol and the CAR did niet predict mortality [16]. This is an influential prospective observation: within a single well-characterized cohort, the rhythm predicted and the level did not. It rests on 32 cardiovascular deaths and requires replication.
KORA-F3 followed 1,090 participants for approximately 11 years (31 cardiovascular deaths) and found the same pattern from the other direction. A more pronounced CAR was associated with lager cardiovascular mortality (HR 0.59, 95% CI 0.36–0.96), as was a greater peak-to-bedtime ratio (HR 0.50, 0.34–0.73), while high late-night cortisol was associated with hoger cardiovascular mortality (HR 1.49, 1.13–1.97). Preserved diurnal variability appeared protective [17].
In coronary artery bypass patients, a steeper pre-surgical diurnal slope was protective for MACE and death (HR 0.73, 95% CI 0.56–0.96 per unit steeper) [18].
A broader synthesis provides an important qualification. A 2017 systematic review and meta-analysis of 179 associations from 80 studies found flatter diurnal cortisol slopes associated with poorer health overall (average r = 0.147), with significant associations in 10 of 12 outcome subtypes — including mortality, and largest for immune and inflammatory outcomes (r = 0.288). The cardiovascular-disease symptoms and diagnoses subgroup was not statistically significant in the random-effects model (r = 0.098, 95% CI −0.034 to 0.226) [78]. The cardiovascular-specific evidence is therefore suggestive rather than uniformly consistent, and this qualifies — rather than contradicts — the positive cardiovascular-mortality findings above.
Across the three cohorts, more preserved diurnal organization was generally associated with better outcomes, whereas amplitude at any single point was not. The measures and estimands nonetheless differ between studies, and the caveat is shared and serious: all three had few cardiovascular deaths — 32, 31, and a modest event count respectively — with correspondingly wide confidence intervals. Taken together, these data favour studying diurnal organization rather than relying on a single morning value, but they do not establish one prognostically validated cardiovascular HPA phenotype.
8.2 Integrated output
In InCHIANTI, 861 adults aged 65 and over were followed for a mean 5.7 years. Twenty-four-hour urinary cortisol in the highest tertile carried HR 5.00 (95% CI 2.02–12.37) for cardiovascular mortality — but on only 41 cardiovascular deaths, with a confidence interval spanning a sixfold range, in an elderly cohort, from a single baseline collection [19]. Two features argue against the most obvious alternative explanations: the association was specific to cardiovascular rather than non-cardiovascular mortality, and it was consistent in participants with and without cardiovascular disease at baseline (p for interaction = 0.78), which constrains reverse causaliteit [19]. The imprecision nonetheless remains severe, and the point estimate should never be quoted without its interval.
In de Lifelines cohort (6,341 hair samples; cortisone in 4,701), hair cortisone independently predicted incident cardiovascular disease, with the association concentrated in participants under 60 (OR 4.21, 95% CI 1.91–9.07 per log₁₀ unit). The scaling is difficult to translate clinically, and elevated hair glucocorticoids are not proof that psychological stress produced them [20].
Against this, a cross-sectional path analysis found that path coefficients through standard modifiable risk factors — hypertension, dyslipidaemia, diabetes — accounted for much of the statistical association between hair cortisol and kransslagaderziekte [21]. Temporal mediation cannot be inferred from a cross-sectional design: exposure, putative mediator and outcome were measured at a single time point, so the ordering that the word mediation implies is assumed rather than observed. The result is consistent with cortisol acting through conventional risk factors, but it is equally consistent with reverse ordering or with shared upstream determinants.
8.3 Reactivity and subclinical atherosclerosis
Whitehall II also tested whether acute cortisol reactivity to standardized laboratory stressors predicted structural disease. Among 466 civil servants without known coronary disease, coronary artery verkalking progression (Agatston increase >10) occurred in 38.2% over three years, and heightened cortisol stress reactivity independently predicted it (OR 1.27, 95% CI 1.02–1.60 per SD) after adjustment for age, sex, baseline CAC, employment grade, smoking, blood pressure, BMI, fibrinogen, and statine use [22]. This is one of the few studies in the field connecting a stress-physiology measure to a structural endpoint with adequate adjustment, and it is graded accordingly.
De MESA Stress Study produced a more mixed picture. Among 464 participants in the coronary calcium analysis and 610 in the ankle-brachial index analysis, salivary diurnal cortisol parameters showed weak or inconsistent associations with both, and the investigators described their own findings as providing only weak support for a link between cortisol and subklinische atherosclerose. In a later MESA analysis of 918 participants, 12-hour urinary cortisol was not associated with cardiovascular events overall. Higher cortisol was associated with greater coronary calcium progression in women but not men, and event associations varied by waist-to-hip ratio, with significant effect modification in women [23,24]. The inconsistency across matrices within a single cohort is itself informative and reinforces Section 6.
8.4 Genetic evidence
Two-sample Mendelian randomization using single-nucleotide polymorphisms at the SERPINA6/SERPINA1 locus on chromosome 14 — which govern corticosteroid-binding globulin and thereby morning plasma cortisol — provides an additional genetic causal-inference test.
The observational meta-analysis in the same investigation gave OR 1.18 (1.06–1.31) per SD of morning plasma cortisol for incident cardiovascular disease. The MR estimate across 122,737 coronary heart disease cases and 547,261 controls gave OR 1.06 (95% CI 0.98–1.15) per SD [25].
How to read this honestly. The genetic point estimate is directionally concordant with the observational estimate, but its confidence interval includes no effect and therefore does not distinguish a small causal effect from the null. Related work at the same locus, examining hepatic CBG expression and tissue gene expression, provides additional support for a causal contribution to ischaemic heart disease [26]. Two caveats are decisive. First, the instruments explain only about 0.5% of morning cortisol variance, which limits statistische onderscheidingsvermogen and the precision of the causal estimate; this is a matter of power rather than of instrument strength statistics, and the analysis should be described that way rather than as a “weak-instrument” result per se. Second, instrument validity is complicated by the biology of the SERPINA6/SERPINA1 locus itself: variants governing corticosteroid-binding globulin have been associated with other cardiometabolic traits, raising the possibility of horizontal pleiotropy [26]. The correct conclusion is that genetic data are compatible with a small causal contribution, and equally compatible with none.
8.5 The experiment of nature
Endogenous Cushing’s syndrome provides strong natural-experiment evidence for the cardiovascular toxicity of sustained pathological glucocorticoid excess: central obesitas, diabetes, hypertension, dyslipidaemia, and premature death, with a standardized mortality ratio of 3.0 (95% CI 2.3–3.9; I² = 80.5%) and atherosclerotic disease with thromboembolism the leading cause of death (43.4%), ahead of infection (12.7%) and malignancy (10.6%). Notably, excess risk persists after biochemical remission — the standardized mortality ratio is 5.7 in active Cushing disease but remains elevated at 2.3 in remission — implicating cumulative prior exposure rather than concurrent hormone level — an idea structurally analogous to cumulative apoB exposure [28].
The generalization must be resisted. Cushing’s syndrome involves cortisol concentrations far outside the range produced by chronic psychological stress. It establishes that the hormone kunnen cause cardiovascular disease at sufficient dose. It does not establish that ordinary chronic stress reaches that dose, and the evidence in Sections 5.7 and 8.1 suggests it usually does not.
8.6 The null and attenuated studies
Any honest account must weight the negative results equally.
LURIC followed 3,052 patients undergoing coronary angiography for a median 9.9 years. Baseline morning serum cortisol in the highest versus lowest kwartiel initially predicted cardiovascular mortality (HR 1.32, 95% CI 1.04–1.67). After multivariable adjustment for age, sex, BMI, smoking, hypertension, diabetes, lipids, and coronary disease severity, the association was completely abolished (HR 0.97, 95% CI 0.76–1.25) [27].
This result admits two readings, and they are not equivalent. The mediation reading holds that cortisol acts through those risk factors, so adjusting for them is over-adjustment that removes real effect. The confounding reading holds that the crude association was never independent. LURIC alone cannot distinguish them. But the practical clinical implication is similar under either reading: morning serum cortisol was not independently associated with cardiovascular mortality after multivariable adjustment in established coronary disease. Note that the study did not perform formal incremental discrimination or herclassificatie analyses, so “adds no predictive value” is a stronger statement than the data support; what they support is the absence of an independent association.
Separately, a cross-sectional study found no association between circulating plasma cortisol and coronary or peripheral arterial disease [29], reinforcing that a single-timepoint measure is a weak marker.
8.7 Verdict
Table 4. Cortisol and cardiovascular outcomes.
| Studie | Design / N | Cortisol measure | Resultaat | Effect (95% CI) | Cijfer |
| Whitehall II, 2011 | Prospective; 4,047; 32 CV deaths | Multi-sample salivary diurnal slope | CV mortality; 6.1 y | HR 1.87 (1.32–2.64) per SD flatter; morning cortisol and CAR null | Gematigd |
| KORA-F3, 2022 | Prospective; 1,090; 31 CV deaths | Salivary CAR, peak:bedtime, late-night | CV mortality; ≈11 y | CAR 0.59 (0.36–0.96); peak:bedtime 0.50 (0.34–0.73); late-night 1.49 (1.13–1.97) | Gematigd |
| Ronaldson et al., 2015 | Prospectief, CABG-patiënten | Pre-chirurgische diurnale curve | MACE en sterfte | HR 0,73 (0,56–0,96) per eenheid steiler | Gematigd |
| InCHIANTI, 2010 | Prospectief; 861; 41 CV-sterfgevallen | 24-uurs urinecortisol | CV-mortaliteit; 5,7 j | Hoogste tertiel HR 5,00 (2,02–12,37) | Matig, onnauwkeurig |
| Lifelines, 2024 | Prospectief; 6.341 haarmonsters | Haarcortisol / cortison | Incidentele CVD; 5–7 j | Leeftijd <60: OR 4,21 (1,91–9,07) per log₁₀ cortison | Gematigd |
| Stomby et al., 2022 | Cross-sectioneel padmodel | Haarcortisol | Coronaire hartziekte | Padcoëfficiënten via standaard risicofactoren verklaren een groot deel van de associatie; temporele ordening niet waargenomen | Beperkt voor mediatie |
| Hamer et al. (Whitehall II), 2012 | Prospectief; 466 | Speekselcortisolreactiviteit op laboratoriumstress | CAC-progressie; 3 j | OR 1,27 (1,02–1,60) per SD | Matig–Sterk |
| Hajat et al., 2013 (MESA) | Prospectief; 464 (CAC), 610 (ABI) | Diurnale speekselcortisol | CAC, ABI | Zwakke en inconsistente associaties | Gematigd |
| Flynn et al., 2023 (MESA) | Prospectief; 918 | 12-uurs nachtelijke urinecortisol | CVD-voorvallen; CAC-progressie | Geen algemene associatie met CVD-voorvallen; grotere CAC-progressie bij vrouwen; interactie van middel-heupverhouding voor voorvallen | Gematigd |
| Crawford et al., 2019 | Geneste cohorten + meta-analyse | Ochtendplasmacortisol | Incidentele CVD | Gepoolde OR 1,18 (1,06–1,31) per SD | Gematigd |
| Crawford et al., MR | Two-sample MR; 122.737 gevallen | Genetisch voorspeld ochtendcortisol | CHD | OR 1,06 (0,98–1,15) per SD | Beperkt–Matig; lage verklaarde variantie (≈0,5%), onnauwkeurige schatting, potentiële locuspleiotropie |
| LURIC, 2021 | Prospectief; 3.052; mediaan 9,9 j | Ochtendserumcortisol, kwartielen | CV-mortaliteit | Ruwe HR 1,32 (1,04–1,67); gecorrigeerd 0,97 (0,76–1,25) | Gematigd |
| Limumpornpetch et al., 2022 | Meta-analyse van cohorten | Endogeen syndroom van Cushing | Sterfte door alle oorzaken | SMR 3,0 (2,3–3,9), I² = 80,5%; atherosclerotische ziekte en trombo-embolie 43,4% van de sterfgevallen; SMR 2,3 in remissie vs 5,7 actief | Sterk voor extreme blootstelling; niet generaliseerbaar |
| Reynolds et al., 2009 | Cross-sectioneel | Circulerend plasmacortisol | CAD, PVD | Geen associatie | Matig (nul) |
De resolutie. Cortisol is een biomarker en een plausibele mediator; een kleine causale bijdrage blijft mogelijk maar onbewezen. De rol ervan verschilt per blootstelling, populatie en maatstaf. Het is een biomarker voor de HPA-as en glucocorticoïdenfysiologie — zij het een aspecifieke, beïnvloed door de circadiane fase, binding eiwitten, ziekte, medicatie, slaap, assay en matrix, en daarom niet specifiek voor psychologische stress. Het is aannemelijk een mediator, hoewel de ondersteunende padanalyse cross-sectioneel is en geen temporele ordening kan vaststellen [21]. Een kleine causale bijdrage blijft mogelijk op basis van genetisch bewijs dat directioneel concordant maar statistisch niet overtuigend is, en op basis van de literatuur over Cushing, die causaliteit alleen vaststelt bij een bereik van blootstelling dat gewone chronische stress niet bereikt.
Wat cortisol is niet is de unieke causale overdrager van psychologische stress naar de slagader. De gelijktijdige activering van sympathische en immuunsystemen, de ontkoppeling door glucocorticoïdreceptorresistentie, de versterking op weefselniveau door 11β-HSD1 en prospectief bewijs dat suggereert dat het diurnale patroon informatiever kan zijn dan geïsoleerde spiegels, maken een cortisol-centrisch model onhoudbaar.
Klinisch heeft dit één duidelijke implicatie, die wordt uitgewerkt in Sectie 25: vraag geen cortisolonderzoek aan voor cardiovasculaire risicostratificatie. Het blijft een onderzoeksinstrument buiten het vermoeden van het syndroom van Cushing.
9. Mechanisme I: Autonoom en hemodynamisch
Chronische sympathische overactiviteit met verminderde vagale tonus verhoogt de rusthartslag, versterkt de bloeddrukreactiviteit en bevordert hypertensie, vasoconstrictie en arteriële stijfheid. Elk hiervan is een vastgestelde atherogene input, en met name hypertensie is een bewezen causale risicofactor met een eigen ondubbelzinnige bewijsbasis uit gerandomiseerd onderzoek.
Dit is het traject met de beste combinatie van plausibiliteit en ondersteuning bij mensen, om een reden die gemakkelijk over het hoofd wordt gezien: de laatste stap is al bewezen. Men hoeft niet aan te tonen dat hypertensie atherosclerose veroorzaakt; dat is bekend. Wat nog moet worden aangetoond, is dat stress op een betekenisvolle manier bijdraagt aan de bloeddruklast. Prospectief werk dat cortisolresponsen op mentale stress koppelt aan incidentele hypertensie ondersteunt de eerste helft van die keten [74]. Het argument is op basis van die termen alleen niet volledig: het vaststellen van een causale route van stress → hypertensie → ASCVD vereist aanvullend bewijs dat stress de aanhoudende bloeddruklast verandert en dat deze route een specifiek aandeel van de daaropvolgende ziekte medieert. Geen van beide is gekwantificeerd.
Herhaalde veranderingen in druk en stroming verhogen ook de mechanische belasting van de vaatwand en kunnen lokale hemodynamische stress veranderen op plekken die gevoelig zijn voor atherosclerose, zoals bifurcaties, waar lokale shear-patronen grotendeels worden bepaald door de arteriële geometrie. Hogere circulerende concentraties noradrenaline en adrenaline worden geassocieerd met een hoger cardiovasculair risico in gepoolde observationele gegevens (noradrenaline RR 1,68, 1,37–2,06; adrenaline RR 1,58, 1,10–2,26), hoewel de circulerende catecholamineconcentratie een imperfecte proxy is voor regionale sympathische zenuwactiviteit [10].
Graad: Matig–Sterk.
10. Mechanisme II: Ontsteking en immuniteit
Dit is de mechanistisch rijkste route in de menselijke literatuur, en degene waarvoor het translationele bewijs het sterkst is.
10.1 Acute stress produceert meetbare immuun-signaalstoffen
In een systematische review en meta-analyse van laboratorium-psychologische stress verhoogden acute stressoren IL-1β (d ≈ 0,66), IL-6 (d ≈ 0,35), IL-10 (d ≈ 0,69) en TNF-α (d ≈ 0,28), waarbij de IL-6-respons groter werd bij latere meetmomenten, consistent met de bekende kinetiek van cytokineproductie [13].
Dit is belangrijker dan de effectgroottes doen vermoeden. Gecontroleerde laboratoriumparadigma's maken gebruik van binnen-persoonlijke pre-post contrasten, waardoor veel stabiele tussen-persoonlijke confounders worden geëlimineerd, en tonen aan dat acute psychologische stress meetbare inflammatoire veranderingen bij mensen kan induceren [13]. Het pleit daarom tegen het volledig verklaren van de associaties tussen stress en ontsteking door leefstijlverschillen tussen mensen — hoewel het confounding niet uitsluit, aangezien baselinekenmerken nog steeds zowel de rusttoestand als de omvang van de respons kunnen modificeren, en de geïncludeerde studies niet uniform gerandomiseerd zijn.
10.2 Glucocorticoïdreceptorresistentie
Zoals uitgewerkt in Sectie 5.7 kunnen chronisch gestresste mensen verminderde glucocorticoïd-responsieve transcriptie en verhoogde NF-κB-gerelateerde transcriptie in monocyten vertonen, zonder een duidelijke overmaat aan dagelijkse cortisolsecretie. Dit biedt een plausibele menselijke mechanistische verklaring voor de paradox van het ontstekingsremmende hormoon [14,15].
Graad: Matig voor het mechanisme; Beperkt voor de gekwantificeerde bijdrage aan ASCVD-uitkomsten. Geen enkele studie heeft aangetoond hoeveel plaque toe te schrijven is aan glucocorticoïdressistentie.
10.3 De amygdala–merg–slagader-as
Een bijzonder invloedrijke integratieve studie bij mensen bracht 293 patiënten in beeld met ¹⁸F-FDG PET/CT en volgde hen gedurende een mediaan van 3,7 jaar, waarin 22 een cardiovasculair incident plaatsvond.
Metabole activiteit van de amygdala in rust was geassocieerd met beenmergactiviteit (r = 0,47, p < 0,0001), arteriële ontsteking (r = 0,49, p < 0,0001) en cardiovasculaire incidenten (gestandaardiseerde HR 1,59, 95% BI 1,27–1,98, p < 0,0001), en bleef significant na multivariabele aanpassing. Seriële mediatie-analyse was consistent met een route van amygdala → beenmerg → arteriële ontsteking → incident: beenmergactiviteit verklaarde een gerapporteerde 46% van de relatie tussen amygdala en arteriële ontsteking, en arteriële ontsteking verklaarde 39% van de relatie tussen amygdala en incidenten. Dit zijn observationele mediatie-schattingen afgeleid van 22 incidenten en moeten worden gelezen als hypothesegenererend in plaats van als een nauwkeurige causale ontleding.
A separate cross-sectional psychometric substudy found perceived stress associated with amygdalar activity (r = 0.56, p = 0.049), arterial inflammation (r = 0.59, p = 0.035), and CRP (r = 0.83, p = 0.021) [11].
Three caveats are essential, and they are frequently omitted. First, the psychometric substudy had n = 13; correlations of 0.83 in a sample of thirteen are not stable estimates. Second, the longitudinal cohort had 22 events — enough for a hazard ratio, not enough for confident mediation decomposition. Third, the study is observational; stress was never manipulated. It is a single, well-conducted, blinded-adjudication study establishing an important mechanistic association, and it requires replication.
The translational complement comes from work showing monocytosis and neutrophilia in chronically stressed medical residents, coupled with murine experiments in which chronic stress activated β3-adrenergic signalling in the bone-marrow niche, reduced CXCL12, stimulated haematopoietic progenitor proliferation, and accelerated inflammatory plaque features. The detailed β3/CXCL12 causal chain is animal evidence. The human contribution is the upstream observation of stress-related leukocytosis. These should not be reported as a single seamless finding [12].
Grade: Moderate.
10.4 The NLRP3 qualification
NLRP3/IL-1β biology is clearly relevant to atherosclerosis, and higher NLRP3 expression in subcutaneous adipose tissue correlates with angiographic coronary atherosclerosis severity in humans, in a study that did not assess psychological stress [44]. However, the specific chain psychological stress → NLRP3 activation → human coronary events has not been demonstrated with anything like the strength of stress → IL-6/CRP or stress → endotheeldisfunctie. Direct stress–NLRP3 experiments remain disproportionately animal or cellular.
Calling NLRP3 an established human mediator of stress-induced ASCVD would exceed the evidence. Grade: Limited for stress-specific mediation.
10.5 Is inflammation itself a modifiable causal node?
This question can be answered with randomized evidence, which is unusual in this review. A 2025 systematic review and meta-analysis pooling 37,056 individuals across 32 randomized trials found that anti-inflammatory therapies targeting the NLRP3/IL-1β/IL-6/CRP pathway reduced myocardial infarction (RR 0.85, 95% CI 0.78–0.93) and coronary revascularisatie (RR 0.80, 0.74–0.86), but did niet significantly reduce overall ernstige ongewenste cardiovasculaire gebeurtenissen, stroke, or mortality [43].
The interpretation is precise: these randomized data support selected inflammatory pathways as modifiable causal contributors to some coronary outcomes. Pharmacologic interruption of this pathway reduces some outcomes and not others, which supports the causal relevance of inflammation to selected coronary endpoints. It does niet, however, quantify how much stress-related risk is mediated by inflammation, and it should not be read as a ceiling on what an upstream behavioural intervention could achieve: such an intervention could act simultaneously through blood pressure, autonomic regulation, sleep, behaviour, metabolism and endothelial function, and differs from a targeted drug in specificity, naleving and off-target profile.
11. Mechanism III: Endothelial and Vascular
11.1 Acute mental stress impairs endothelial function
In landmark human experimental work, acute mental stress tasks — competitive mental arithmetic, public speaking — induced transient endothelial dysfunction in healthy individuals, with brachial artery flow-mediated dilation falling significantly from baseline at 30 and 90 minutes post-stress and requiring up to four hours to recover [31]. This has been demonstrated experimentally in more than one human laboratory, using different stressors and vascular beds [31,76], and constitutes strong experimental human physiology.
11.2 It has prognostic value
The more important finding is that this response predicts outcomes. In 569 patients with coronary artery disease, mean FMD fell from 4.8% before a public-speaking stress task to 3.9% afterward; 63.3% developed stress-induced endothelial dysfunction. Over a median 3.0 years, 74 major adverse cardiovascular events occurred, and stress-induced endothelial dysfunction was associated with subdistribution HR 1.78 (95% CI 1.15–2.76). Each one-percentage-point stress-related decrease in FMD carried sHR 1.15 (1.03–1.27) [32].
A separate ischaemic heart disease cohort found that each SD worse stress-induced endothelial response predicted MACE with HR 1.35 (1.07–1.71), with impaired microvascular stress responses appearing especially prognostic in women — suggesting the cardiovascular consequences of stress may differ by sex and vascular compartment [33].
Graad: Matig–Sterk. This is a reproducible human experimental effect with demonstrated prognostic value in the population of clinical interest.
11.3 Molecular mechanism: what is human and what is not
A largely translational molecular model proposes the following: sympathetic activation stimulates the renin–angiotensin–aldosterone system and upregulates angiotensin II type 1 receptor (AT₁R) signalling in endotheelcellen; AT₁R activation stimulates NADPH oxidase, generating superoxide; superoxide reacts with stikstofoxide vormen peroxinitriet; peroxynitrite oxidizes the eNOS cofactor tetrahydrobiopterin, causing eNOS uncoupling, whereupon the enzyme produces superoxide rather than nitric oxide in a self-sustaining cycle. Reduced NO bioavailability then permits NF-κB-driven expression of VCAM-1, ICAM-1, and E-selectin, which capture circulating monocytes for transmigration into the subendotheliale ruimte.
Downstream of this, a further set of mechanisms — disruption of endothelial tight-junction proteins (ZO-1, claudin-5, occludin), MMP-9 upregulation with TIMP-1 suppression, VEGF- and angiogenin-driven intra-plaque neovascularisatie, and TNF-α-mediated impairment of endotheliale voorlopercellen — has been proposed. Each of these steps derives from animal or cell-system work rather than from human plaque, and none is individually sourced to a human study here. They are listed as candidate mechanisms, not as findings.
A necessary demarcation, and it matters more than it may appear. Two components of this account do have direct human experimental support. Selective endothelin-A receptor antagonism with intra-arterial BQ-123 prevented the prolonged endothelial dysfunction that followed a mental stress task in healthy subjects, implicating endothelin-A signalling causally in the human response [76]. And in a three-way randomized crossover study of 15 overweight or obese men, AT₁R blockade with olmesartan and ascorbic acid infusion each altered the stress-induced fall in flow-mediated dilation and the accompanying redox profile, implicating AT₁R-mediated redox imbalance [77]. Both are small studies, and the second is confined to one sex and body-composition stratum.
The remainder of the cascade — the NADPH-oxidase/peroxynitrite/tetrahydrobiopterin/eNOS-uncoupling sequence and the downstream adhesion-molecule and plaque steps — remains substantially translational. It should not be cited to the demonstration that endothelial glucocorticoid receptor signalling suppresses atherogenesis, which is an ApoE-deficient mouse experiment [45] and speaks to endothelial GR biology rather than to this pathway. The tight-junction, MMP-9/TIMP-1, VEGF/angiogenin, and endothelial progenitor components derive predominantly from animal models, cell systems, and mechanistic reviews. They are biologically coherent and worth stating — but they are hypotheses about human plaque, not observations of it, and this review declines to present them at the same evidentiary level as the FMD data in Section 11.2. Related work showing that acute mental stress rapidly redistributes leukocytes in humans, with locally derived norepinephrine increasing endothelial adhesion signalling and plaque leukocyte recruitment in mice, illustrates the same split precisely [34].
Grade: Moderate for stress-induced endothelial dysfunction in humans; Limited for the detailed downstream molecular cascade in human plaque.
12. Mechanism IV: Metabolic
Glucocorticoids increase hepatic glucose production, antagonize peripheral insulin action, and contribute to visceral adiposity through tissue-specific glucocorticoid signalling [30]. These are established features of glucocorticoid physiology; none has been demonstrated to mediate a quantified share of stress-related ASCVD.
In community populations, altered diurnal cortisol — flatter slopes, higher bedtime cortisol — is associated with type 2 diabetes, and long-term hair glucocorticoid measures correlate with cardiometabolic traits [38].
12.1 The lipid pathway requires particular caution
It is sometimes asserted that stress raises LDL-cholesterol and thereby causes atherosclerosis. This is too simple, and the evidence does not support it.
ApoB-containing lipoproteïnen remain the substrate that atherosclerotic plaque formation requires, a position supported by convergent genetic, epidemiologic and interventional evidence [75]. Psychological stress may alter diet, adiposity, insulinegevoeligheid, and hepatic metabolism, and hypercortisolaemia with elevated free fatty acid flux can plausibly increase hepatic VLDL and apoB secretion while lowering HDL cholesterol. But studies of job strain have not consistently found large adverse changes in totaal cholesterol, LDL cholesterol, or fibrinogen [39].
The defensible model is that stress interacts with pre-existing lipoprotein exposure rather than creating it. A person with low lifetime apoB exposure and high chronic stress is in a materially different position from a person with high lifetime apoB exposure and high chronic stress, and the literature gives no reason to think stress substitutes for the lipoprotein term.
12.2 Separating hormone from behaviour
The deeper problem with the metabolic literature is that in everyday chronic stress, behavioural pathways — diet, inactivity, alcohol, and sleep loss — may contribute importantly to the metabolic effects observed. Distinguishing direct glucocorticoid effects from behavioural ones in observational human data is extremely difficult, and few studies have attempted it rigorously.
Grade: Moderate overall; Limited for a stress → cortisol → dyslipidaemia → atherosclerosis pathway specifically.
13. Mechanism V: Thrombosis and Acute Triggering
These mechanisms are distinct from long-term atherogenesis and should be reported separately (Figure 4).
Acute psychological stress produces measurable haemostatic change. A systematic review found relatively consistent stress-related alterations in coagulation, fibrinolyse, haemorheology, and platelet measures, though with considerable methodological weakness. Controlled norepinephrine infusion increases factor VIII activity, fibrinogen, and D-dimer, providing direct evidence that adrenergic signalling alters coagulation [35].
The proposed components are: epinephrine binding platelet α₂-adrenergic receptors, lowering cyclic AMP and the aggregation threshold, with P-selectin and activated glycoprotein IIb/IIIa rising within minutes; elevated factor VIII, von Willebrand factor, and fibrinogen; increased tissue factor expression; and elevated plasminogeen activator inhibitor-1 impairing endogenous fibrinolysis [35].
An important nuance is usually lost. In healthy subjects, coagulation and fibrinolysis often rise together, preserving haemostatic balance. It is in people with vascular disease or other vulnerabilities that a relative prothrombotic imbalance becomes consequential. The acute-stress prothrombotic state is therefore best understood as a modifier of existing risk, not a universal hazard.
Mental stress-induced myocardial ischaemia (MSIMI) roughly doubles the risk of adverse cardiac events and mortality in patients with coronary artery disease. The supporting meta-analysis rested on only five small studies with fewer than 50 events each — a thin base for a widely cited conclusion [36]. Mechanistically, in diseased kransslagaders with endothelial dysfunction, catecholamine release fails to produce normal flow-mediated vasodilation; direct α-adrenergic stimulation of vascular smooth muscle instead produces paradoxical vasoconstriction.
Grade: Moderate–Strong for acute triggering; Moderate for the specific haemostatic mechanisms.
14. Mechanism VI: Behavioural Mediation
Multiple behavioural pathways plausibly contribute to the stress–ASCVD relationship: smoking, alcohol, diet quality, physical inactivity, sleep disruption, medication non-adherence, obesity, and co-occurring depression or anxiety. The share attributable to them is not established.
The standard analytic response is to adjust for these. Many prospective studies do so and find attenuated but still significant associations. This is often described as showing a “partly independent” effect, but the accurate statement is narrower: associations persist after adjustment for measured covariates. Statistical adjustment does not establish biological independence.
But adjustment cuts both ways, and this is under-appreciated. Chronic distress can contribute to smoking, inactivity, sleep disturbance and non-adherence, while these factors can also share upstream determinants with distress and can feed back on it. Depending on the causal structure, a given behaviour may act as a mediator, a confounder, a consequence of a common cause, or some combination. So:
- A minimally adjusted estimate retains pathways operating through behaviour, but also retains more confounding.
- A covariate-adjusted estimate conditions on measured variables and attenuates behaviourally mediated pathways — but conditioning on post-exposure variables can also induce collider bias, and it does niet by itself identify a controlled or natural direct effect.
- Neither is “the” answer, and reporting only one is misleading.
This is a point of formal causal inference, not a stylistic preference. Estimating how much of the stress–ASCVD relationship is transmitted biologically rather than behaviourally requires a specified causal estimand and mediation analysis under explicit identification assumptions — no-unmeasured-confounding of exposure–outcome, mediator–outcome, and exposure–mediator relationships, and correct measurement and temporal ordering. Ordinary multivariable covariate adjustment alone does not establish these identification assumptions and does not by itself identify a controlled or natural direct effect.
This resolves an apparent conflict in the literature. The cross-sectional path analysis showing that standard risk factors mediate most of the hair-cortisol–CAD association and the INTERHEART finding that the psychosocial–MI association persists after adjustment for income and education are not contradictory. They are estimating different quantities.
There is no defensible single percentage for how much of stress-related ASCVD is behavioural versus direct. The answer varies by stressor, population, life stage, baseline disease, and mediator definition. Any review that supplies a specific figure is over-claiming.
The 2025 AHA scientific statement on post-myocardial-infarction psychological distress explicitly identifies these behavioural routes as credible pathways by which distress worsens prognosis [48] — which is also, usefully, where the clinical leverage lies (Section 21).
Graad: Matig–Sterk.
15. Mechanistic Evidence Matrix
Table 5. Mechanisms linking psychological stress to ASCVD, graded by human evidence.
| Mechanisme | Proposed pathway | Human evidence | Consistentie | Cijfer |
| HPA-axis dysregulation | Threat circuitry → CRH/ACTH → altered cortisol level, timing, recovery | Prospective links to diurnal slope, late-night cortisol, urinary and hair glucocorticoids | Direction depends on metric; several cohorts associate flatter or less differentiated rhythms with adverse outcomes, but cardiovascular findings are not uniformly consistent in meta-analysis | Gematigd |
| Glucocorticoid receptor resistance | Repeated stress → reduced immune-cell GR signalling → failure to suppress NF-κB | Human monocyte transcriptional data in chronically stressed caregivers | Biologically coherent; few outcome-linked studies | Gematigd mechanism; Beperkt outcome mediation |
| SAM / catecholamine activation | Stress → sympathetic output → heart rate, blood pressure, vasoconstriction, immune effects | Strong acute physiology; hormone–CVD meta-analysis; controlled norepinephrine infusion | Generally consistent | Matig–Sterk |
| Hypertension / haemodynamic load | Recurrent pressor and flow changes → mechanical wall stress and sustained BP burden; possible alteration of local haemodynamic forces | Cortisol responses to mental stress predict incident hypertension [74]; terminal step independently proven causal | Consistent in direction | Matig–Sterk |
| Cytokine inflammation | Stress → adrenergic/HPA/immune signalling → IL-6, IL-1β, TNF-α, CRP | Experimental acute-stress meta-analysis; chronic-stress genomic studies | Strongest for IL-6; magnitude varies | Sterk for acute activation; Gematigd for ASCVD mediation |
| Amygdala–marrow–artery axis | Central threat response → sympathetic marrow signalling → leukopoiesis → arterial inflammation | One PET/CT cohort (n = 293, 22 events) with serial mediation; animal β3/CXCL12 chain | Highly coherent translationally; single human study | Gematigd |
| NLRP3 / IL-1β | Stress → inflammasome → IL-1β, IL-18 | NLRP3 linked to human atherosclerosis; stress-specific chain mostly animal/cellular | Stress-specific human evidence sparse | Beperkt for stress-specific mediation |
| Endotheeldisfunctie | Stress → neurohumoral and redox signalling → impaired endothelial NO-dependent function / FMD | Reproducible experimental FMD impairment; prognostic for MACE in CAD | Reproduced clinically | Matig–Sterk |
| Downstream endothelial molecular cascade | Tight-junction loss, MMP-9/TIMP-1 imbalance, VEGF/angiogenin neovascularization, EPC suppression | Predominantly animal and cell-system; mechanistic reviews | Coherent but unverified in human plaque | Beperkt |
| Insulin resistance / visceral adiposity | Cortisol + behaviour + sleep loss → insulin resistance, central adiposity, diabetes | Strong endocrine plausibility; diurnal cortisol–type 2 diabetes association | Relation plausible; mediator-specific estimates lacking | Gematigd |
| ApoB / lipoprotein pathway | Stress-related metabolic change → altered atherogenic lipoproteins | Inconsistent direct stress–lipid association in occupational cohorts | Not consistently adverse | Beperkt |
| Coagulation / bloedplaatjes | Acute stress → factor VIII, fibrinogen, vWF, platelet activity, impaired fibrinolysis | Laboratory studies and systematic review; NE infusion experiments | Broadly procoagulant but heterogeneous | Gematigd |
| Triggeren van acute voorvallen | Stress-piek → behoefte, vasoconstrictie, endotheliale en trombotische verschuiving → ischemie | Grote internationale case-crossover gegevens; MSIMI-cohorten | Sterk temporeel signaal | Matig–Sterk |
| Gedragsmatige bemiddeling | Stress → roken, dieet, inactiviteit, slaap, alcohol, therapieontrouw → HVZ | Grote observationele basis; consensusverklaringen | Herhaaldelijk waargenomen | Matig–Sterk |
Figuur 6 geeft deze matrix weer als een trajectdiagram met weging per verbinding. De vorm van het bewijs is het expliciet vermelden waard: de keten is het sterkst aan de twee uiteinden en het zwakst in het midden. Dat stress deze systemen acuut activeert is goed vastgesteld in de menselijke laboratoriumfysiologie; dat stress gebeurtenissen voorspelt is epidemiologisch goed vastgesteld. De kwantitatieve bijdrage van elke tussenliggende stap aan plaquebelasting is dat bij mensen niet.
Figuur 6. Geïntegreerd traject van psychologische stress naar atherosclerotische voorvallen, met de bewijslast per verbinding bij de mens. Labels classificeren de kracht van het menselijke bewijs voor elke pijl, niet de omvang van het effect.
16. De interventievraag: Taxonomie en de claimladder
16.1 Meditatie is niet één behandeling
Het analyseren van “meditatie” als een enkele interventie behandelt een klinisch en methodologisch heterogene klasse alsof het één behandeling is.
- Op mindfulness gebaseerde interventies (MBI's), waaronder MBSR, combineren aandachtstraining, acceptatie en niet-reactiviteit, lichaamsbewustzijn en vaak beweging, yoga en expliciete gedragsinstructie. MBSR is conventioneel een acht weken durend programma onder leiding van een instructeur met aanzienlijke thuisbeoefening.
- Op mindfulness gebaseerde cognitieve therapie (MBCT) voegt cognitief-gedragsmatige technieken toe.
- Transcendente Meditatie (TM) is een gestandaardiseerde, op mantra's gebaseerde beoefening, doorgaans twee keer per dag 15–20 minuten, onderwezen via een georganiseerde certificeringsstructuur.
- Oefeningen voor gerichte aandacht en ritmische ademhaling concentreren op een fysiologisch anker, zoals ademhalen met ongeveer zes ademhalingen per minuut.
De heterogeniteit is niet cosmetisch. Het Mindfulness-Based Blood Pressure Reduction (MB-BP) programma onderwijst expliciet een DASH-dieet, fysieke activiteit, therapietrouw en alcoholreductie naast meditatie. Een onderzoek naar MB-BP is een onderzoek naar een gedragsinterventie met meerdere componenten, en het toeschrijven van de resultaten specifiek aan meditatie is niet gerechtvaardigd [60].
Meditatie met gerichte aandacht verdient een aparte vermelding: cardiovasculaire onderzoeken bundelen aandachtsoefeningen doorgaans in bredere mindfulness-programma's in plaats van een gestandaardiseerde interventie met gerichte aandacht afzonderlijk te testen. Er is daarom onvoldoende bewijs om meditatie met gerichte aandacht te rangschikken ten opzichte van MBSR of TM voor ASCVD-eindpunten.
16.2 Het probleem met de vergelijker
Een inactieve controle — wachtlijst, geen behandeling, gebruikelijke zorg — isoleert meditatie niet. Het bundelt de aandacht van de instructeur, verwachting, sociaal contact, tijd die rustig zittend wordt doorgebracht, herhaalde metingen en de structuur van een programma. Een onderzoek met een wachtlijstcontrole isoleert daarom niet het praktijkspecifieke effect; het schat het effect van het hele pakket en de context van verwachtingen, en inactieve vergelijkers hebben de neiging om grotere schattingen op te leveren in deze literatuur.
Figuur 7 laat zien wat dit met de cijfers doet. De keuze van de vergelijker beïnvloedt het geschatte effect aanzienlijk — hoewel het type interventie, de grootte van het onderzoek, therapietrouw, populatie, achtergrondtherapie, meetmethode en heterogeniteit ook allemaal bijdragen.
Figuur 7. In meditatie-onderzoeken beïnvloedt de keuze van de vergelijker het antwoord aanzienlijk. De enige schatting voor systolische bloeddruk met matige zekerheid in het Cochrane-review — Transcedente Meditatie tegenover een actieve vergelijker — is ook de kleinste.
16.3 Vijf te scheiden claims
Omdat deze routinematig op één hoop worden gegooid, worden ze overal gescheiden (Figuur 8):
- Claim A: meditatie vermindert de waargenomen stress.
- Claim B: meditatie verandert de stressfysiologie (cortisol, HPA-functie).
- Claim C: meditation improves established risk factors (blood pressure, HRV, inflammation, metabolic markers).
- Claim D: meditation slows measurable atherosclerosis.
- Claim E: meditation reduces hard events — myocardial infarction, stroke, cardiovascular death.
Evidence weakens sharply from A to E, and E cannot be inferred from A through D.
Figure 8. Five separable claims about meditation, and the evidence for each. An intervention can reliably reduce how stressed a person feels, modestly lower their blood pressure, and still have no demonstrated effect on whether they have a heart attack.
17. The Benchmark Synthesis
De 2024 Cochrane review is the reference standard for this question. It included 81 randomized trials and 6,971 participants, requiring interventions of at least 12 weeks in adults at high cardiovascular risk or with established cardiovascular disease, and examined four prespecified comparisons. Most trials were at unclear risk of bias, many were small, and heterogeneity was substantial across most outcomes.
Table 6. Cochrane 2024 — findings by comparison.
| Vergelijking | Bloeddruk | Psychological outcomes | Clinical events | Zekerheid |
| MBIs vs active comparators (29 RCTs, 2,883 participants) | SBP MD −6.08 mmHg (−12.79 to 0.63), I² = 88%; DBP −5.18 (−10.65 to 0.29), I² = 91%; 6 trials, 388 participants | Perceived stress SMD −0.24 (−0.45 to −0.03), I² = 0%, 6 trials, 357 participants; anxiety SMD −0.06 (−0.25 to 0.13), I² = 0%; depression ≈ null; wellbeing little or no effect | None reported. Smoking cessation RR 1.45 (0.78–2.68), I² = 79% | Low for BP; moderate for perceived stress, anxiety, depression |
| MBIs vs non-active comparators (38 RCTs, 2,905 participants) | SBP MD −6.62 mmHg (−13.15 to −0.10), I² = 87%; DBP −3.35 (−5.86 to −0.85), I² = 61%; 9 trials, 379 participants | Larger effects than against active controls | One trial (110 participants): RR 0.94 (0.37–2.42) | Low for BP; very low for events |
| TM vs active comparators (8 RCTs, 830 participants; SBP analysis 8 RCTs, 774 participants) | SBP MD −2.33 mmHg (−3.99 to −0.68), I² = 2% — TM probably reduces SBP; DBP less certain | — | One trial (201 participants): RR 0.91 (0.56–1.49) | Moderate for SBP; laag for events |
| TM vs non-active comparators (2 RCTs, 186 participants) | SBP MD −6.34 mmHg (−9.86 to −2.81), I² = 0%; DBP −5.13 (−9.07 to −1.19), I² = 18%; 2 trials, 139 participants | One trial (112 participants): anxiety SMD −0.71 (−1.09 to −0.32); depression −0.48 (−0.86 to −0.11) | None reported. No adverse events or smoking data | Low for SBP; very low for DBP |
Two observations dominate. First, of 81 randomized trials, exactly two contributed cardiovascular clinical-event data — one at very low certainty (MBIs vs inactive, RR 0.94, 0.37–2.42) and one at low certainty (TM vs active, RR 0.91, 0.56–1.49) — and neither showed a detectable effect. Because the Cochrane search closed in November 2021, this characterises the trials it included rather than the entire literature to the present day. Second, the only moderate-certainty blood-pressure estimate in the entire review is also the smallest: −2.33 mmHg for TM against an active comparator, with essentially no heterogeneity (I² = 2%) and the largest participant total — 774 of the 830 participants in that comparison contributed systolic data. Every estimate near −6 mmHg carries either I² ≥ 87% or fewer than 150 participants.
The Cochrane authors’ own summary is that they found very little information on clinical endpoints, limited information on blood pressure and psychological outcomes, substantial between-study heterogeneity, and a body of evidence generally of low certainty [50].
A note on a common citation error. The −2.33 mmHg figure is frequently attributed to mindfulness-based interventions, or to a non-active comparison. It belongs to TM versus active comparators. Het onderscheid is belangrijk: het cijfer wordt vaak ingezet om te betogen dat mindfulness een betekenisvolle bloeddrukverlaging teweegbrengt, terwijl het in feite de meest rigoureus gecontroleerde — en kleinste — schatting in de review vertegenwoordigt.
18. Claim A: Ervaren stress
Mindfulness-gebaseerde interventies zorgen waarschijnlijk voor een kleine vermindering van ervaren stress in vergelijking met actieve comparatoren, in de populaties met cardiovasculair risico die Cochrane heeft opgenomen. Vergeleken met actieve comparatoren was de samengestelde schatting van Cochrane SMD −0,24 (−0,45 tot −0,03; I² = 0%; 6 onderzoeken, 357 deelnemers; matige zekerheid) — een klein effect zonder gedetecteerde statistische heterogeniteit (I² = 0%), verspreid over zes onderzoeken. Vergeleken met inactieve comparatoren zijn de effecten groter.
Twee kanttekeningen. Ten eerste waren de samengestelde effecten op angst en depressie vergeleken met actieve comparatoren nagenoeg nul (angst SMD −0,06, I² = 0%, matige zekerheid). Het verminderen van ervaren stress is niet hetzelfde als het behandelen van een angst- of depressieve stoornis, en deze literatuur ondersteunt die laatste claim niet bij cardiovasculaire populaties [50]. Ten tweede is het verschil tussen actief gecontroleerde en wachtlijst-gecontroleerde effecten op zich de bevinding: het kleinere effect vergeleken met actieve comparatoren suggereert dat aspecifieke interventie- en contexteffecten een betekenisvolle bijdrage leveren aan schattingen verkregen in ongecontroleerde ontwerpen of wachtlijstontwerpen.
Grade: Moderate.
19. Claim B: Cortisol en HPA-fysiologie
Het sterkste geaggregeerde bewijs is afkomstig van een systematische review en meta-analyse van 58 gerandomiseerde onderzoeken met 3.508 deelnemers (Figuur 9A). In bloed-, speeksel- en haarmatrices veranderden psychologische stressmanagement-interventies de cortisolspiegel met een samengestelde Hedges’ g van 0,282. Dat samengestelde cijfer betreft stressmanagement-interventies in het algemeen, niet specifiek meditatie; de schatting voor de subgroep mindfulness/meditatie was g = 0,345. De effecten waren groter voor CAR-metingen (g = 0,644) dan voor dagelijkse cortisolmetingen (g = 0,255). Per modaliteit waren mindfulness en meditatie (g = 0,345) en ontspanning (g = 0,347) het meest effectief, terwijl mind-body (g = 0,129) en gesprekstherapieën (g = 0,107) niet-significant waren [51].
Figuur 9. Meditatie verandert de stressbiologie op bescheiden en inconsistente wijze. ‘Modulatie’ is een nauwkeuriger beschrijving dan ‘cortisolverlaging’; geen enkele studie heeft aangetoond dat een door meditatie teweeggebrachte cortisolverandering een vermindering van cardiovasculaire voorvallen medieert.
Aanvullend bewijs: in 10 gerandomiseerde onderzoeken met bloedafname had meditatie een middelgroot effect op cortisol (g = 0,62, 95% BI 0,22–1,02, p = 0,003) — maar alleen in steekproeven van risicogroepen of lichamelijk zieken, niet bij gezonde deelnemers zonder risicofactoren [52]. Een meta-analyse van MBI's op speekselcortisol bij gezonde volwassenen (5 RCT's, n = 190) vond kleinere en minder consistente effecten [53].
Drie punten ter interpretatie.
Ten eerste, “modulatie” is veiliger dan “verlaging” of “normalisatie”. Afhankelijk van het basis-fenotype kan een gunstige verandering een sterkere CAR betekenen, een steilere dagelijkse daling, een lager avondcortisol of een gewijzigde reactiviteit — mogelijk in tegenovergestelde richtingen bij verschillende mensen. Het rapporteren van een samengesteld gestandaardiseerd effect als “meditatie verlaagt cortisol” is een onjuiste beschrijving van wat er gemeten is; maar evenmin tonen deze samengestelde effecten een beweging aan in de richting van een gevalideerde gezonde fysiologische referentie, wat “normalisatie” zou beweren.
Ten tweede pleit de waarneming dat actief gecontroleerde onderzoeken in die meta-analyse wel niet zwakkere cortisoleffecten lieten zien dan passief gecontroleerde onderzoeken tegen het verklaren van het volledige effect door de verwachting bij geen behandeling. Het identificeert geen meditatiespecifiek mechanisme, aangezien actieve controles sterk verschillen in geloofwaardigheid en intensiteit.
Ten derde, en doorslaggevend: geen enkele studie heeft aangetoond dat een door meditatie veroorzaakte cortisolverandering enig cardiovasculair voordeel medieert. Het observeren van een daling van cortisol en een daling van de bloeddruk in dezelfde trial bewijst niet dat de eerste de tweede veroorzaakte, laat staan dat een van beide atherosclerose voorkwam.
Graad: Beperkt–Matig. Sommige bewijzen suggereren grotere effecten in monsters van personen met een verhoogd risico of somatisch zieken, met het duidelijkste signaal in gepoolde bloed-cortisolstudies en zwakkere speekselbevindingen.
20. Claim C: Gevestigde Risicofactoren
20.1 Bloeddruk — de best ondersteunde surrogaatparameter
De Cochrane-schattingen staan in Tabel 6. Oudere TM-specifieke meta-analyses schatten grotere reducties van ongeveer −4,7/-3,2 mmHg, en een aparte TM-meta-analyse van 12 studies en 996 deelnemers rapporteerde −4,26 mmHg systolisch en −2,33 mmHg diastolisch [62,63]. De AHA-verklaring over alternatieve benaderingen van bloeddrukverlaging beoordeelde TM slechts als Klasse IIb, Bewijsniveau B, waarbij expliciet zorgen over de studiekwaliteit werden aangehaald [49], en dezelfde verklaring merkte op dat effect-schattingen in deze literatuur variëren met de studiekwaliteit.
Individuele trials illustreren waarom pooling omstreden is:
- MBSR versus progressieve spierontspanning bij 56 volwassenen met prehypertensie: de klinische SBP daalde met 4,8 mmHg versus 0,7 mmHg (p = 0,016) en de DBP daalde met 1,9 mmHg versus een stijging van 1,2 mmHg (p = 0,008) — maar de ambulante bloeddruk verschilde niet. [58]
- HARMONY: 101 volwassenen met onbehandelde stadium-1 hypertensie vertoonden nagenoeg geen verschil tussen de groepen in de 24-uurs ambulante bloeddruk na 12 weken (+0,4/0,0 versus +0,4/−0,4 mmHg) [59].
- MB-BP, een op mindfulness gebaseerd multicomponent bloeddrukprogramma in plaats van een trial met alleen meditatie: 201 deelnemers met een verhoogde spreekkamerbloeddruk vertoonden een vooraf gespecificeerd verschil tussen de groepen in spreekkamer systolische druk van −4,5 mmHg (95% BI −9,0 tot −0,1) na zes maanden vergeleken met verbeterde gebruikelijke zorg. Maar de interventie richtte zich ook op dieet, lichaamsbeweging, therapietrouw bij medicatie, alcohol en stress; de sedentaire tijd daalde met 350,8 minuten per week. Verbeterd gezondheidsgedrag is een plausibele bijdragende factor, maar het multicomponent-ontwerp voorkomt dat het bloeddrukeffect uitsluitend aan meditatie wordt toegeschreven, en het gelijktijdig optreden van gedragsverandering en bloeddrukverandering bewijst op zichzelf geen mediatie. Een secundaire analyse uit 2026 vond een kleine verbetering in de samengestelde cardiovasculaire gezondheid (SMD 0,144, 0,023–0,266), terwijl de betrouwbaarheidsintervallen van individuele componenten over het algemeen de nul doorkruisten. De hoofdonderzoeker maakte melding van eigendom van een bedrijf dat mindfulnesstraining aanbiedt, met preregistratie, beperkte datatoegang en onafhankelijke statistische analyse als gedeclareerde waarborgen [60,61].
In verschillende van deze trials veranderde de klinische bloeddruk terwijl de ambulante bloeddruk dat niet deed. Deze discrepantie rechtvaardigt voorzichtigheid, hoewel deze is gebaseerd op een klein aantal trials en niet moet worden gegeneraliseerd naar de gehele literatuur. Ambulante meting is minder gevoelig voor spreekkamer- en wittejasseneffecten en is over het algemeen prognostisch informatiever.
Grade: Moderate. Een realistische verwachting verschilt per modaliteit en comparator in plaats van uit te komen op één getal: ongeveer −2,3 mmHg systolisch voor TM tegenover een actieve comparator (matige zekerheid); grotere maar onnauwkeurige en zeer heterogene schattingen voor MBI's (lage zekerheid, betrouwbaarheidsintervallen die de nul doorkruisen of benaderen tegenover actieve comparatoren); en ongeveer −4,5 mmHg spreekkamer-systolisch voor het multicomponent MB-BP programma, wat niet uitsluitend aan meditatie kan worden toegeschreven.
20.2 Hartslagvariabiliteit
Populaire verhalen beweren dat meditatie de “vagale tonus herstelt”. Het gerandomiseerde bewijs ondersteunt dit niet als een consistent chronisch effect. Een meta-analyse van 19 RCT's gevonden Hedges’ g 0,38 (95% BI −0,014 tot 0,77; I² = 89,1%) voor vagaal gemedieerde HRV in rust — statistisch niet overtuigend en buitengewoon heterogeen. Het verwijderen van een enkele extreme uitbijter reduceerde de schatting tot 0,19 (−0,02 tot 0,39) [57].
Graad: Inconclusief.
20.3 Ontsteking
Het beeld is wisselend en, belangrijker nog, niveau-afhankelijk (Figuur 9B).
Pooled across 48 randomized trials with 4,683 participants, MBIs produced small reductions in CRP at post-treatment (standardized mean change difference −0.14, −0.26 to −0.01) and IL-6 (−0.35, −0.67 to −0.03). At follow-up, CRP remained reduced (−0.39, −0.68 to −0.10) while the IL-6 interval included no effect (−0.13, −0.29 to 0.03) [54].
But a relatively large, matched-active-control randomized trial complicates this. In 190 lonely older adults, MBSR versus an active health-enhancement programme reduced pro-inflammatory NF-κB-related gene expression (d = 0.17, p = 0.028) but did niet reduce circulating IL-6 or CRP, nor alter CREB, IRF, or glucocorticoid-receptor transcriptional activity. An earlier positive gene-expression trial had only n = 40 [55,56].
The lesson is specific and generalizable: transcriptional signalling and systemic protein biomarkers do not necessarily move together. Demonstrating a change at one level of the inflammatory cascade is not evidence of change at another, and neither is evidence of change in plaque.
Graad: Beperkt–Matig.
20.4 Metabolic outcomes
Small improvements in glucose, lipids, and metabolic-syndrome components appear in some trials but are underpowered and inconsistent. A meta-analysis in diabetes found psychological benefits from MBSR but no detectable pooled HbA1c improvement at post-intervention or follow-up [64]. Cochrane found no significant lipid or glycaemic changes for MBIs against active controls.
Behavioural change driven by these programmes may still be cardiovascularly useful — but that is a behavioural mechanism, not a demonstration of a cortisol → insulin-sensitivity pathway.
Grade: Limited.
21. Claim D: Atherosclerosis
Direct randomized evidence is sparse and inconsistent.
The most-cited trial randomized 138 hypertensive African American adults to TM versus health education. Only about 60 of the 138 randomized participants contributed paired carotid intima-mediadikte data (roughly 43.5% retention), and among those completers cIMT regressed in the TM group (−0.098 mm) while progressing in controls (+0.054 mm; p = 0.038) [65]. Attrition of this magnitude creates a high risk of attrition bias, and the finding is best regarded as preliminary.
A randomized trial conducted from 2000 to 2014 and published in 2025, in a different population and with a different follow-up structure, did not demonstrate a between-group cIMT benefit. Of 197 randomized participants, 136 completed post-test cIMT. After one year, cIMT changed by −0.0004 mm in the TM group and −0.0003 mm in health education — no significant difference. There were also no differences in lipids or blood pressure at one year. The authors noted that both groups progressed less than historical non-randomized controls, but that comparison is not randomized and cannot support a causal inference about either arm [67].
Beyond these, small mind-body studies have evaluated flow-mediated dilation or endothelial biomarkers, but none establishes that meditation changes coronary plaquevolume, carotid plaque, coronary artery calcium progression, or plaque composition.
The hierarchy matters here more than anywhere. Improving FMD is not slowing plaque. Slowing a surrogate is not preventing myocardial infarction.
Grade: Limited / Inconclusive — with the later trial’s failure to demonstrate a between-group cIMT benefit carrying substantial weight. Because populations, designs and follow-up differ, this is a failure to demonstrate benefit in a related trial rather than a strict replication attempt.
22. Claim E: Hard Clinical Events
Two small randomized trials, both from the same TM-affiliated research group at institutions linked to the organization that teaches and licenses the technique, report hard-endpoint benefit.
- 201 Black patients with coronary heart disease randomized to TM versus health education. Over a mean 5.4 years, TM was associated with a 48% reduction in the composite primary endpoint of all-cause mortality, myocardial infarction, and stroke: HR 0.52 (95% CI 0.29–0.92; p = 0.025), alongside a systolic blood-pressure reduction of approximately 4.9 mmHg [66].
- The trial published in 2025 had a null primary endpoint. This trial was conducted from 2000 to 2014 and published in 2025 after delayed analysis; it is not a newly recruited contemporary trial, and its registration (NCT05642936) post-dates data collection by many years. Its primary endpoint, carotid intima-media thickness, showed no between-group difference. The secondary event analysis reported a 65% relative MACE reduction at five years (HR 0.346, 95% CI 0.134–0.893; p = 0.017), with the 14-year analysis null (HR 0.68, 0.35–1.31) [67].
- Three features require explicit flagging. First, events were analysed across multiple maximum-follow-up windows (1, 5, 10 and 14 years) without a stated multiplicity adjustment; the five-year window is best treated as the main secondary analysis and the others as exploratory. Second, event counts are small throughout. Third, the reported ten-year result is internally inconsistent as published: the paper gives HR 0.485 with a 95% confidence interval of 0.226–1.044 alongside p = 0.0435. An interval that includes 1.0 cannot accompany a p-waarde below 0.05. Until that discrepancy is resolved by the authors, the ten-year result should not be described as statistically significant, and this review does not do so.
These findings must be weighed carefully rather than dismissed or accepted.
In their favour: both are randomized, both used an active comparator (health education rather than waitlist), and the direction is consistent.
Against them: both are small; both come from a single research group; the confidence intervals are wide (the 2025 upper bound of 0.893 sits close to unity); the 2025 trial’s own primary endpoint — cIMT — was null, so the event finding is a secondary outcome in a trial that failed its primary; multiple maximum-follow-up windows were analysed and significance was lost at 14 years; trial registration post-dated the original data collection; and both carry researcher-allegiance and institutional-affiliation concerns of a degree that would attract close scrutiny in any pharmaceutical context. The distinction matters and this review observes it: the 2025 trial explicitly declared no commercial or financial conflict of interest, while several authors hold institutional affiliations with organizations involved in teaching and researching the intervention. That is an allegiance concern, not a documented undeclared financial conflict, and should be described as such. A 2025 commentary in a major cardiology review journal advocating TM within cardiovascular prevention frameworks originates from the same investigator group and should be read with the same awareness [69].
A separate 2025 multicentre trial of meditation and health education for cardiometabolic disease prevention in 201 Black women reported no between-group difference in carotid intima-media thickness, with some metabolic signals on secondary outcomes [68]. It is a separate trial but arises from the same investigator network, and therefore does not constitute independent replication.
The Cochrane review, applying prespecified methods to trials published to November 2021, found very sparse clinical-event evidence — two comparisons, one low and one very low certainty, neither showing a detectable effect [50]. Because its search closed in 2021, Cochrane cannot by itself adjudicate the 2025 and 2026 publications discussed above; our own structured search to 20 August 2026 identified no independent replication among them.
The correct statement is therefore precise, and scoped to what we searched: in the literature identified through our search to 20 August 2026, we found no independent, replicated, low-bias randomized evidence that meditation prevents cardiovascular events or death. This is not the same as evidence of no effect. It is the absence of the evidence that would be required to make the claim — and, given a structured rather than systematic search, it is a review finding rather than a proof of non-existence.
Graad: Inconclusief.
Table 7. Meditation and stress-reduction trials and syntheses.
| Studie | Intervention vs comparator | N / duration | Principal outcomes | Effect | Principal methodological concerns |
| Cochrane review, 2024 | MBI or TM vs active or non-active | 81 RCTs; 6,971 | BP, psychological outcomes, lipids; CVD events sought | See Table 6; only 2 trials reported events | Mostly unclear; low to moderate certainty |
| Rogerson et al., 2024 | Stress-management vs pooled controls | 58 RCTs; 3,508 | Cortisol (CAR, diurnal, single-sample) | g = 0.282 overall; CAR 0.644; meditation 0.345 | Moderate; heterogeneous comparators |
| Koncz et al., 2021 | Meditation vs control | 10 RCTs (blood samples) | Blood cortisol | g = 0.62 (0.22–1.02); at-risk samples only | Moderate; small trials |
| Sanada et al., 2016 | MBI vs control, healthy adults | 5 RCTs; 190 | Salivary cortisol | Smaller, inconsistent | Gematigd |
| Dunn & Dimolareva, 2022 | MBI vs randomized controls | 48 RCTs; 4,683 | CRP, IL-6 | CRP −0.14 (−0.26 to −0.01); IL-6 −0.35 (−0.67 to −0.03) | Population and dose heterogeneity |
| MBSR gene-expression RCT, 2023 | MBSR vs active health-enhancement, older adults | 190; 8 weeks | NF-κB gene expression; IL-6; CRP | Gene expression d = 0.17 (p = 0.028); IL-6 and CRP unchanged | Low–moderate; best-designed inflammation trial |
| Brown et al., 2021 | Mindfulness / meditation vs control | 19 RCT's | Vagally mediated HRV | g = 0.38 (−0.014 to 0.77), I² = 89%; 0.19 without outlier | Extreme heterogeneity |
| Hughes et al., 2013 | MBSR vs progressive muscle relaxation | 56; 8 weeks | Clinic and ambulatory BP | Clinic SBP −4.8 vs −0.7 mmHg (p = 0.016); ambulatory null | Small, short |
| Blom et al. (HARMONY), 2014 | MBSR vs waitlist | 101; 12 weeks | 24-h ambulatory BP | +0.4/0.0 vs +0.4/−0.4 mmHg — no effect | Pilot; waitlist |
| Loucks et al. (MB-BP), 2023 | 8-wk adapted mindfulness + CV behaviour education vs enhanced usual care | 201; 6-mo follow-up | Office SBP; behaviour | SBP −4.5 mmHg (−9.0 to −0.1); sedentary time −350.8 min/wk | 17.4% loss to follow-up; multicomponent; investigator commercial interest |
| MB-BP secondary analysis, 2026 | Same programme | 201; 6 mo | Composite CV health | SMD 0.144 (0.023–0.266); component CIs cross null | Secondary analysis |
| Anderson et al., 2008 | TM vs control | meta-analyse | SBP, DBP | −4.7 mmHg SBP; −3.2 DBP | Older meta-analysis; study-quality and investigator-allegiance concerns; AHA rated TM Class IIb, LOE B |
| Castillo-Richmond et al., 2000 | TM vs health education | 138 randomized; ≈60 paired cIMT (43.5% retention) | Carotid IMT | −0.098 vs +0.054 mm (p = 0.038) | Severe attrition; small analysed sample; preliminary |
| Schneider et al., 2012 | TM vs health education, CHD patients | 201; mean 5.4 y | Composite mortality, MI, stroke | HR 0.52 (0.29–0.92), p = 0.025 | Small trial; single investigator network; allegiance concern |
| Norris et al., 2025 | TM vs health education | 197 randomized; 136 cIMT | cIMT at 12 months (primary); MACE to 14 y | cIMT null (−0.0004 vs −0.0003 mm); MACE HR 0.346 (0.134–0.893) at 5 y, null at 14 y | Primary endpoint null; secondary events across multiple windows; retrospective registration; allegiance concern |
23. Evidence Quality, Bias, and Adverse Effects
Table 8. Author-assessed narrative confidence by claim, with explicit basis for downgrade.
Downgrade domains: RoB = risk of bias · IND = indirectness · IMP = imprecision · INC = inconsistency · CONF = confounding · PB = publication bias.
| Claim | Zelfvertrouwen | Downgrade domains | Basis |
| Stress → ASCVD association (several psychosocial constructs, CHD/CVD) | Sterk | CONF | Consistentie in associaties tussen patiënt-controleonderzoeken en prospectieve cohortstudies voor diverse psychosociale constructen; beeldvorming en mechanistische studies leveren ondersteunend bewijs voor geselecteerde intermediaire paden; residuele sociaaleconomische en gedragsmatige confounding blijft aanwezig |
| Stress → causaliteit van ASCVD (klinische gebeurtenissen) | Gematigd | CONF, IND | Temporaliteit en experimentele fysiologie ondersteunen dit; geen gerandomiseerde test; residuele confounding kan niet worden uitgesloten |
| Stress → plaque-initiatie / progressie | Beperkt–Matig | IND, IMP | Direct bewijs via seriële beeldvorming bij mensen is schaars; de meeste ondersteuning is afgeleid van events en surrogaat-eindpunten |
| Amygdala–beenmerg–arterie-traject | Gematigd | IMP, RoB | Eén longitudinale beeldvormingsstudie; 22 events; observationele bemiddeling; psychometrische substudie n = 13 |
| Diurnale cortisol-ontregeling → CV-mortaliteit | Gematigd | IMP, INC | Verschillende prospectieve cohorten rapporteren nadelige associaties met vlakkere of minder gedifferentieerde ritmes, maar de aantallen cardiovasculaire gebeurtenissen zijn klein (31–32 sterfgevallen), de metingen verschillen, en een bredere meta-analyse vond geen significante random-effects associatie voor de subgroep cardiovasculaire aandoeningen [78] |
| Mendeliaanse randomisatie van cortisol → coronaire hartziekten | Beperkt–Matig | IMP, IND | Betrouwbaarheidsinterval bevat de nulwaarde; instrumenten verklaren ≈0,5% van de variantie, wat de power beperkt; SERPINA6/SERPINA1 pleiotropie onopgelost; instrumenten meten cortisol, geen stress |
| Eenmalige cortisolmeting → CV-uitkomsten | Beperkt | CONF, INC | Verzwakt tot nul na correctie (LURIC); nulresultaat in cross-sectionele studie; matrix-mismatch met chronische blootstelling |
| Hypertensie / autonoom traject | Matig–Sterk | IND | De laatste stap is onafhankelijk als causaal bewezen; de link tussen blootstelling en mediator en de gemedieerde fractie zijn niet gekwantificeerd |
| Ontsteking — acute door stress veroorzaakte activering | Sterk | — | Experimentele meta-analyse bij mensen met consistente richting |
| Ontsteking — bemiddeling van stressgerelateerd ASCVD-risico | Gematigd | IND | Anti-inflammatoire RCT's stellen de causale relevantie van ontsteking vast voor geselecteerde coronaire uitkomsten, niet de gemedieerde fractie van het stressrisico |
| Endotheeldisfunctie — acute menselijke reactie | Matig–Sterk | IMP | Reproduceerbaar experimenteel effect; prognostisch bij CAD; kleine experimentele steekproeven |
| Endotheliale moleculaire cascade (stappen stroomafwaarts) | Beperkt | IND | Voornamelijk bewijs uit dier- en celsystemen; endotheline-A en AT₁R-componenten hebben weinig ondersteuning bij mensen |
| Metabool traject | Gematigd | IND | Sterke endocriene plausibiliteit; stress-specifieke gemedieerde fractie niet gekwantificeerd |
| Lipiden / apoB-traject | Beperkt | INC | Associaties tussen stress en lipiden in beroepscohorten zijn inconsistent |
| Trombotische en acute triggering-trajecten | Matig–Sterk | RoB | Grote case-crossover data; mechanisme-studies zijn methodologisch heterogeen |
| Gedragsmatige bemiddeling | Matig–Sterk | IND | Herhaaldelijk waargenomen; geen verdedigbare enkelvoudige kwantificering van de gemedieerde fractie |
| A. Meditatie → vermindering van ervaren stress | Gematigd | IMP | SMD −0,24 ten opzichte van actieve vergelijkers, I² = 0%; klein effect, bescheiden steekproef |
| B. Meditatie → verandering in cortisol / HPA-as | Beperkt–Matig | INC, IND | Effecten voornamelijk in risicosteekproeven; heterogene matrices; gepoolde schatting niet specifiek voor meditatie; bemiddeling niet bewezen |
| C. Meditatie → bloeddruk | Gematigd | INC, IMP | Enige systolische schatting met matige zekerheid is −2,33 mmHg (TM vs. actief); MBI-schattingen zijn heterogeen (I² ≥ 87%) |
| C. Meditatie → HRV | Onbeslist | INC, IMP | Gepoold effect overschrijdt de nulwaarde; I² = 89%; gevoelig voor uitschieters |
| C. Meditatie → ontsteking | Beperkt–Matig | INC, IND | Kleine gepoolde biomarkereffecten; de best gecontroleerde trial vond verandering in genexpressie zonder verandering in CRP of IL-6 |
| D. Meditatie → verminderde atherosclerose | Beperkt / Niet eenduidig | RoB, IMP | Oorspronkelijke cIMT-bevinding had 43,5% retentie; latere trial toonde geen verschil tussen de groepen |
| E. Meditatie → vermindering van harde events | Onbeslist | RoB, IMP, PB | Twee kleine trials met mogelijke onderzoekersbinding; schaarse Cochrane-gegevens over gebeurtenissen met lage/zeer lage zekerheid; geen onafhankelijke replicatie geïdentificeerd |
23.1 Systematische problemen
Selectie van de vergelijker. Wachtlijst- en geen-behandelingscontroles neigen in deze literatuur tot grotere geschatte effecten dan actieve vergelijkers. Cochrane vond consequent grotere effecten ten opzichte van inactieve vergelijkers.
Publicatiebias en gerelateerde zorgen over rapportage. Publicatiestatus was direct geassocieerd met de effectgrootte in de literatuur over werkstress (1,43 gepubliceerd tegenover 1,16 ongepubliceerd). In de TM-literatuur leiden kleine steekproeven, mogelijkheden voor selectieve rapportage, retrospectieve registratie in sommige onderzoeken en de loyaliteit van onderzoekers tot gerelateerde maar afzonderlijk gedefinieerde zorgen, zonder een gelijkwaardige empirische kwantificering van publicatiebias.
Loyaliteit van onderzoekers en institutionele affiliatie. Bijzonder uitgesproken in TM-onderzoek, waar de trials die voordelen op harde eindpunten rapporteren afkomstig zijn van onderzoekers die institutioneel verbonden zijn aan organisaties die de techniek onderwijzen en onderzoeken. Waar financiële belangen afzonderlijk worden vermeld — zoals in het MB-BP-programma en het commentaar uit 2026 — vermeldt deze review dit expliciet; waar trials verklaren geen financieel conflict te hebben, betreft de zorg de loyaliteit en affiliatie in plaats van een niet-verklaard financieel belang. De AHA-verklaring riep expliciet op tot voldoende krachtige gerandomiseerde trials met minder dan 20% uitval uitgevoerd door onderzoekers zonder inherente vooringenomenheid ten aanzien van de uitkomst. Aan die oproep is geen gehoor gegeven [46].
Onvoldoende onderscheidingsvermogen en uitval. Onderzoeken hebben per arm vaak een te laag onderscheidingsvermogen; de uitval varieert van 17% tot meer dan 50% bij de belangrijkste trials die hier worden besproken.
Afhankelijkheid van surrogaatparameters en korte follow-up. De duur van de trials in het Cochrane-corpus moest ten minste 12 weken zijn, en de meeste waren kort in vergelijking met wat nodig zou zijn om structurele plaque-remodellering of het aantal voorvallen te beoordelen.
Omgekeerde causaliteit in cortisol-cohorten. In cohorten met bestaande hart- en vaatziekten kunnen hormoonmetingen een weerspiegeling zijn van de ernst van de ziekte, medicatie, acute ziekte, slaap of nierfunctie in plaats van psychologische stress.
23.2 Bijwerkingen
Lichaam-geest-interventies zijn over het algemeen veilig, maar niet vrij van bijwerkingen. Een systematische review uit 2020 die heterogene ontwerpen combineerde, schatte een algemene prevalentie van bijwerkingen van ongeveer 8% bij mensen die mindfulness of meditatie beoefenen — voornamelijk verhoogde angst, paniek, depressieve symptomen of depersonalisatie — in grote lijnen vergelijkbaar met de percentages die worden gerapporteerd voor standaard psychologische therapieën, hoewel de schattingen sterk varieerden per onderzoeksopzet en de rapportage aanzienlijk onvolledig was [70]. Met name stelde de Cochrane-review vast dat de meeste geïncludeerde trials bijwerkingen helemaal niet rapporteerden, wat op zichzelf een tekortkoming in de rapportage is [50].
24. Geïntegreerd model met bewijskracht per verbinding
Ziektepad (Figuur 6). De onderstaande beoordelingen zijn van toepassing op elke afzonderlijke verbinding en maken onderscheid tussen acute fysiologische zekerheid en de bemiddeling bij chronische ziekten. Chronische stress → cortico-limbische angstcircuits [Matig–Sterk] → acute HPA-as en sympathische activering [Sterk voor acute fysiologie; variabel chronisch fenotype] → catecholaminerespons [Sterk voor acute fysiologie; Matig voor associatie met chronische hart- en vaatziekten], cortisol-dysregulatie [Matig], verminderde chronische vagale tonus [Beperkt–Matig], glucocorticoïdreceptorresistentie [Matig als mechanisme; Beperkt als bemiddelaar van ASCVD] → ontsteking via hematopoëse in het beenmerg, IL-6/CRP, NF-κB [Matig–Sterk bij mensen], endotheeldisfunctie [Matig–Sterk], stress → aanhoudende bloeddrukbelasting [Matig]; bloeddruk → ASCVD [Sterk], insulineresistentie en viscerale adipositas [Matig, deels gedragsmatig], activatie van bloedplaatjes en stolling [Matig, voornamelijk acuut] → begin en progressie van atherosclerose [Beperkt–Matig: direct bewijs uit seriële beeldvorming bij mensen is schaars] → plaque-instabiliteit en trombose [Matig] → myocardinfarct, beroerte, cardiovasculaire dood [associatie Sterk; mechanisme-specifiek causaal gewicht Matig].
Interventiepad. Meditatie → vermindering van ervaren stress [Matig] → mogelijke verbetering in HPA-as en autonome regulatie [Beperkt–Matig] → verlaagde bloeddruk [Matig], enige vermindering van inflammatoire genexpressie [Beperkt], kleine metabole verandering [Beperkt] → mogelijke vermindering van atherosclerose [Niet overtuigend; vroege positieve cIMT-trial gevolgd door een latere gerelateerde trial zonder resultaat] → mogelijke vermindering van voorvallen [Inconclusive].
24.1 The two competing narratives, stated precisely
The strongest available interpretation of the mechanistic evidence is niet:
stress → continuously elevated cortisol → plaque.
A model more consistent with the available evidence — offered as a conceptual scheme, not a demonstrated serial mediation chain — is:
repeated psychological threat → altered central threat processing → repeated and dysregulated HPA and sympathetic activity → abnormal cortisol timing and reactivity, sometimes with glucocorticoid resistance and tissue-level amplification, together with catecholamine and haemodynamic activation → inflammatory, vascular, metabolic and behavioural change → increased susceptibility to atherosclerosis, and, in people who already have disease, increased vulnerability to acute triggering.
The second model accommodates what the first cannot: that some chronically stressed populations show high cortisol, others blunted reactivity, and others relatively normal circulating profiles with impaired glucocorticoid signalling.
24.2 Where stress sits relative to apoB
A point of framing that this review considers important. Atherosclerosis requires the retention of apoB-containing lipoproteins in the arterial intima and a chronic inflammatory response to them. Psychological stress does not replace that process; current atherosclerosis biology provides no basis for treating psychological stress as an alternative to apoB-containing lipoprotein retention in plaque initiation [75].
Stress is more plausibly a modifier of atherogenic lipoprotein exposure and its vascular consequences than an alternative to apoB-driven plaque biology. What it can plausibly do is modify the rate at which that process runs, and modify the probability that established plaque converts to a clinical event. The magnitude of that modification will depend heavily on baseline apoB burden, smoking, blood pressure, diabetes, sleep, age, genetics, existing plaque burden, and behaviour. This is why the same relatief risico means very different absolute things in different people — and why stress management is properly framed as a modifier of risk, not as a foundation of prevention.
25. Clinical and Prevention Implications
Stress management, including meditation, is a reasonable, low-risk adjunct for interested patients — particularly for blood pressure, psychological wellbeing, and behavioural self-regulation. It should niet replace statins or other apoB-lowering therapy, bloeddrukverlagende middelen, smoking cessation, diabetes treatment, physical activity, hartrevalidatie, or any other guideline-directed intervention. This is also the position of the American Heart Association, which concluded that meditation “may be considered as an adjunct” while noting that benefits remain to be better established [46,47].
Staged, actionable recommendations:
- Assess psychosocial stressors, depression, anxiety, and social isolation as risk markers — particularly in patients with unexplained risk, poor control, or after myocardial infarction. The value of screening lies in identifying people who need behavioural support, not in generating a risk score.
- Address established behavioural risk factors and psychosocial barriers alongside guideline-directed prevention. Smoking, physical activity, sleep, alcohol use and medication adherence are clinically important behavioural factors that can accompany psychological distress and should be addressed according to established prevention guidance. This is where the practical leverage is likely to lie, though the ordering is a clinical judgment rather than a directly tested comparison.
- Optimize guideline-directed prevention regardless of stress status — blood pressure, LDL cholesterol and apoB, glucose, smoking. Stress status does not change these targets.
- Offer meditation or structured stress reduction to patients who want it, waarbij het verwachte voordeel eerlijk wordt geschetst: een bescheiden daling van de bloeddruk en waargenomen stress, onbewezen vermindering van incidenten. Waar stress bijdraagt aan hypertensie, slecht slapen, inactiviteit, ongezond eten of moeite met het opvolgen van de behandeling, is de indicatie voor interventie sterker — hoewel de relatieve bijdrage van gedragsmatige versus directe fysiologische bemiddeling niet is vastgesteld.
- Vraag geen cortisolmeting aan voor cardiovasculaire risicostratificatie. Het blijft een onderzoeksinstrument, behalve wanneer het syndroom van Cushing klinisch wordt vermoed. In LURIC vertoonde serumcortisol in de ochtend geen onafhankelijk verband met cardiovasculaire mortaliteit na correctie voor conventionele risicofactoren [27], en geen enkele cortisolmeting is in een formele incrementele voorspellingsanalyse aangetoond om de risicoschatting te verbeteren of om responders op de behandeling te identificeren.
- Presenteer meditatie niet als een alternatief voor farmacotherapie. De meest ingrijpende schade op dit gebied is niet de interventie — het is de vervanging.
- Adviseer patiënten met een vastgestelde coronaire hartziekte over acute triggers waar klinisch passend. Dit is een apart en beter onderbouwd fenomeen dan chronische atherogenese. Merk echter op dat bewijs voor acute triggers niet bewijst dat voorlichting hierover incidenten voorkomt; geen enkele trial heeft dat onderzocht.
26. Drempels die deze conclusies zouden veranderen
Vooraf aangeven welk bewijs iemand van mening zou doen veranderen, is een discipline waar deze literatuur baat bij zou hebben.
- Aan onafhankelijk uitgevoerde, actief gecontroleerde, event-driven gerandomiseerde trial, met a priori voldoende power voor een klinisch aannemelijke MACE-reductie gezien het verwachte baseline-incidentiepercentage, de follow-upduur, therapieontrouw en concurrerende risico's, die aantoont dat meditatie MACE vermindert, zou rechtvaardigen om het te verheffen van aanvullende naar aanbevolen therapie. Onafhankelijke replicatie door onderzoekers zonder interventiespecifieke belangen zou het vertrouwen wezenlijk vergroten.
- Replicatie van de bevinding over de amygdala–beenmerg–slagader in een groter cohort met voldoende incidenten zou dat pad verschuiven van Matig naar Sterk.
- Aantonen dat het experimenteel wijzigen van een nadelig diurnaal cortisolpatroon in een vooraf gespecificeerde richting het aantal incidenten vermindert — en niet louter ermee correleert — zou monitoring van het cortisolritme rechtvaardigen en cortisol vaststellen als een aanpasbaar doelwit in plaats van een meetwaarde.
- Serie coronaire beeldvorming in een gerandomiseerde trial naar stressvermindering waarbij een veranderde plaquebelasting of fenotype wordt aangetoond, zou de leemte in claim D rechtstreeks opvullen.
- Sterkere genetische instrumenten voor cortisol, die aanzienlijk meer dan 0,5% van de variantie verklaren, zouden de causale schatting in beide richtingen scherper maken.
We hebben geen van deze geïdentificeerd in onze zoekopdracht tot 20 augustus 2026.
27. Belangrijke onbeantwoorde onderzoeksvragen
- Vermindert het verminderen van stress, op welke manier dan ook, harde cardiovasculaire incidenten in een voldoende krachtige, bias-arme, onafhankelijke gerandomiseerde trial?
- Verandert stressvermindering de seriële coronaire plaquebelasting of inflammatoire plaquefenotype?
- Is aanpassing van een nadelig diurnaal cortisolpatroon op zichzelf cardioprotectief, of is het patroon slechts een marker van onderliggende gezondheid?
- Welk meditatiedype, welke dosis, frequentie en duur — indien aanwezig — is het meest effectief, via welk mechanisme, tegen een active controle?
- Hoeveel van het verband tussen stress en ASCVD is echt causaal versus verstoord door sociaaleconomische positie en gedrag?
- Kunnen haarcortisol of cortison incrementele voorspellende waarde toevoegen bovenop standaard risicofactoren?
- Identificeren baseline neuroimaging- of cortisolfenotypes subgroepen die onevenredig veel baat hebben bij mind-body-interventie?
- Verschillen de effecten naar geslacht, ras, sociaaleconomische stressbelasting, PTSS- of depressiestatus, of baseline HPA-fenotype?
- Wijzigen stressverminderende praktijken reproduceerbaar de immuungenexpressie, en zo ja, via welke epigenetische mechanismen — inclusief FKBP5-gerelateerde regulatie en GR-signalering?
Het veld heeft behoefte aan betere bemiddelingsontwerpen: een ideale studie zou een gestandaardiseerde interventie randomiseren, herhaaldelijk ervaren stress, slaap, gedrag, ambulante bloeddruk, catecholaminen, speekselcortisol op meerdere tijdstippen, haarglucocorticoïden, inflammatoire signalering, endotheelfunctie en gevalideerde arteriële beeldvorming meten, en vervolgens beoordeelde cardiovasculaire gebeurtenissen volgen. Zonder die temporele mediatorstructuur kunnen een waargenomen daling van cortisol en een waargenomen daling van de bloeddruk niet aantonen dat de eerste de tweede veroorzaakte.
28. Conclusies: Directe antwoorden op de kernvragen
Tabel 9. Samenvatting van de antwoorden.
| Vraag | Antwoord | Cijfer |
| Verhogen chronische psychosociale stressoren het risico op ASCVD? | Verschillende afzonderlijke constructen — werkstress, ervaren stress, eenzaamheid en sociaal isolement — zijn elk geassocieerd met een bescheiden hoger risico. Gecorrigeerde prospectieve schattingen zijn gewoonlijk ~1,2–1,3 voor diverse psychosociale constructen; case-controle- en trigger-schattingen zijn groter en beantwoorden andere vragen | Vereniging Sterk |
| Hoe sterk is het causale bewijs? | Matig. Ondersteund door temporaliteit, consistentie en menselijke experimentele fysiologie, maar wezenlijk zwakker dan het causale bewijs voor apoB-blootstelling, roken en bloeddruk; residuele confounding blijft mogelijk | Gematigd |
| Welke mechanismen hebben het sterkste menselijke bewijs? | Autonome en hemodynamische activering; inflammatie; endotheeldisfunctie; gedragsmatige bemiddeling; acute triggering. Brein-merg-slagader-signalering is overtuigend, maar rust op één studie | Matig–Sterk |
| Welke rol speelt cortisol? | Een aspecifieke biomarker van HPA/glucocorticoïden-fysiologie en een plausibele mediator; een kleine causale bijdrage is mogelijk maar onbewezen. Niet de enige overdrager van stress | Beperkt–Matig voor causaliteit |
| Is een verhoogd cortisolgehalte pathogeen, of is dysregulatie het betere model? | Dysregulatie is het betere kader, zonder één verplicht fenotype. Duidelijk hypercortisolisme is ontegenzeggelijk pathogeen, maar is niet de gebruikelijke toestand bij chronische stress | Sterk bewijs tegen het eenvoudige model; Gematigd voor enig specifiek gedisreguleerd fenotype |
| Hoeveel wordt gemedieerd door bloeddruk, inflammatie, insulineresistentie, adipositas, slaap en gedrag? | Onbekend, en waarschijnlijk heterogeen over verschillende populaties en stressoren. Geen enkel percentage is verdedigbaar; minimaal gecorrigeerde en voor covariabelen gecorrigeerde schattingen beantwoorden verschillende vragen, en geen van beide identificeert een direct biologisch effect | — |
| Vermindert meditatie ervaren stress? | Ja, bescheiden; het effect neemt af ten opzichte van geloofwaardige actieve controles | Gematigd |
| Verandert meditatie cortisol of de HPA-fysiologie? | Kleine tot matige gepoolde effecten, voornamelijk in risicogroepen. ‘Modulatie’ is nauwkeuriger dan algemene ‘verlaging’ of ‘normalisering’; een gunstige richting hangt af van het baseline HPA-fenotype en de cortisolmaatstaf. Mediatie van voordeel is onbewezen | Beperkt–Matig |
| Verbetert meditatie vastgestelde risicofactoren? | Bloeddruk bescheiden — ongeveer −2,3 mmHg systolisch voor TM versus actieve vergelijkingsgroepen in de Cochrane-schatting met matige zekerheid, met grotere maar minder zekere schattingen in andere vergelijkingen; HRV niet overtuigend; inflammatie inconsistent; metabole markers niet betrouwbaar | Gematigd voor bloeddruk |
| Vertraagt meditatie atherosclerose? | Niet consistent aangetoond. Een vroege kleine trial rapporteerde cIMT-voordeel met aanzienlijke uitval; een latere gerandomiseerde trial in een andere populatie toonde geen voordeel tussen de groepen aan | Beperkt / Niet eenduidig |
| Voorkomt meditatie hartinfarcten, beroertes of cardiovasculaire sterfte? | Niet vastgesteld. Twee kleine trials met mogelijke belangenverstrengeling suggereren voordeel; geen onafhankelijke replicatie; Cochrane vond schaars bewijs van lage/zeer lage zekerheid voor incidenten | Onbeslist |
28.1 Wat gerechtvaardigd is, en wat overdreven is
Gerechtvaardigd. Several forms of chronic psychosocial stress and distress are prospectively associated with modestly higher ASCVD risk after adjustment for measured covariates, and probably contribute causally to some degree. HPA-axis dysregulation — not simple hypercortisolism — is a more defensible physiological framework, though no single dysregulated phenotype is established. Acute emotional stress can trigger events in people with existing disease. Meditation lowers perceived stress, modestly lowers blood pressure, is generally low risk, and is a reasonable adjunct within a complete prevention strategy — though adverse psychological experiences do occur and cardiovascular trials have reported harms incompletely.
Overreach. That stress is a major independent driver of atherosclerosis comparable to lipids or smoking. That cortisol testing is clinically useful for cardiovascular risk. That meditation “prevents heart attacks or strokes.” That meditation “reverses atherosclerosis.” That meditation “normalizes cortisol to prevent cardiovascular disease.” That any of this justifies deferring or substituting for guideline-directed therapy.
The gap between these two lists is where most public communication on this topic goes wrong — and, because cumulative apoB exposure drives atherosclerotic risk over time [75], the substitution error is not a harmless one.
29. Limitations of This Review
This is a narrative evidence review, not a systematic review with a registered protocol, prespecified search strategy, or formal risk-of-bias instrument applied to each included study. Study selection reflects the judgement of the author, informed by four independently prepared source syntheses, and may not be exhaustive.
The grading scheme in Section 2.3 is explicit but is not GRADE, and the grades are the author’s assessments rather than formal consensus ratings. Where full texts were paywalled, quantitative values were taken from published abstracts. Effect estimates drawn from meta-analyses inherit the limitations of those analyses, including heterogeneity and the publication bias documented in Section 7.2.
The review is weighted toward literature published in English and toward cohorts in high-income countries, with the notable exceptions of INTERHEART and INTERSTROKE. Finally, this is a rapidly moving area — the Cochrane authors themselves noted a large number of ongoing eligible studies — and conclusions about Claims D and E in particular should be expected to change.
30. References
- Rosengren A, Hawken S, Ôunpuu S, Sliwa K, Zubaid M, Almahmeed WA, et al. Association of psychosocial risk factors with risk of acute myocardial infarction in 11 119 cases and 13 648 controls from 52 countries (the INTERHEART study): case-control study. Lancet. 2004;364(9438):953–62. doi:10.1016/S0140-6736(04)17019-0. PMID: 15364186.
- O’Donnell MJ, Xavier D, Liu L, Zhang H, Chin SL, Rao-Melacini P, et al. Risk factors for ischaemic and intracerebral haemorrhagic stroke in 22 countries (the INTERSTROKE study): a case-control study. Lancet. 2010;376(9735):112–23. doi:10.1016/S0140-6736(10)60834-3. PMID: 20561675.
- Kivimäki M, Nyberg ST, Batty GD, Fransson EI, Heikkilä K, Alfredsson L, et al. Job strain as a risk factor for coronary heart disease: a collaborative meta-analysis of individual participant data. Lancet. 2012;380(9852):1491–7. doi:10.1016/S0140-6736(12)60994-5. PMID: 22981903.
- Huang Y, Xu S, Hua J, Zhu D, Liu C, Hu Y, et al. Association between job strain and risk of incident stroke: a meta-analysis. Neurology. 2015;85(19):1648–54. doi:10.1212/WNL.0000000000002098. PMID: 26468409.
- Fransson EI, Nyberg ST, Heikkilä K, Alfredsson L, Bjorner JB, Borritz M, et al. Job strain and the risk of stroke: an individual-participant data meta-analysis. Stroke. 2015;46(2):557–9. doi:10.1161/STROKEAHA.114.008019. PMID: 25563644.
- Richardson S, Shaffer JA, Falzon L, Krupka D, Davidson KW, Edmondson D. Meta-analysis of perceived stress and its association with incident coronary heart disease. Am J Cardiol. 2012;110(12):1711–6. doi:10.1016/j.amjcard.2012.08.004. PMID: 22975465.
- Valtorta NK, Kanaan M, Gilbody S, Ronzi S, Hanratty B. Loneliness and social isolation as risk factors for coronary heart disease and stroke: systematic review and meta-analysis of longitudinal observational studies. Heart. 2016;102(13):1009–16. doi:10.1136/heartjnl-2015-308790. PMID: 27091846. PMCID: PMC4941172.
- Schulz R, Beach SR. Caregiving as a risk factor for mortality: the Caregiver Health Effects Study. JAMA. 1999;282(23):2215–9. doi:10.1001/jama.282.23.2215. PMID: 10605972.
- Smyth A, O’Donnell M, Lamelas P, Teo K, Rangarajan S, Yusuf S; INTERHEART Investigators. Physical activity and anger or emotional upset as triggers of acute myocardial infarction: the INTERHEART study. Circulation. 2016;134(15):1059–67. doi:10.1161/CIRCULATIONAHA.116.023142. PMID: 27753614.
- Tsai S-Y, Chi N-F, Wang Y-C, et al. Association of stress hormones and the risk of cardiovascular diseases: a systematic review and meta-analysis. Int J Cardiol Cardiovasc Risk Prev. 2024;23:200305. doi:10.1016/j.ijcrp.2024.200305. PMID: 39319239. PMCID: PMC11420448. Outcome is broad cardiovascular disease, not ASCVD specifically.
- Tawakol A, Ishai A, Takx RAP, Figueroa AL, Ali A, Kaiser Y, et al. Relation between resting amygdalar activity and cardiovascular events: a longitudinal and cohort study. Lancet. 2017;389(10071):834–45. doi:10.1016/S0140-6736(16)31714-7. PMID: 28088338.
- Heidt T, Sager HB, Courties G, Dutta P, Iwamoto Y, Zaltsman A, et al. Chronic variable stress activates hematopoietic stem cells. Nat Med. 2014;20(7):754–8. doi:10.1038/nm.3589. PMID: 24952646.
- Marsland AL, Walsh C, Lockwood K, John-Henderson NA. The effects of acute psychological stress on circulating and stimulated inflammatory markers: a systematic review and meta-analysis. Brain Behav Immun. 2017;64:208–19. doi:10.1016/j.bbi.2017.01.011. PMID: 28089638.
- Miller GE, Chen E, Sze J, Marin T, Arevalo JMG, Doll R, et al. A functional genomic fingerprint of chronic stress in humans: blunted glucocorticoid and increased NF-κB signaling. Biol Psychiatry. 2008;64(4):266–72. doi:10.1016/j.biopsych.2008.03.017. PMID: 18440494.
- Cohen S, Janicki-Deverts D, Doyle WJ, Miller GE, Frank E, Rabin BS, et al. Chronic stress, glucocorticoid receptor resistance, inflammation, and disease risk. Proc Natl Acad Sci U S A. 2012;109(16):5995–9. doi:10.1073/pnas.1118355109. PMID: 22474371.
- Kumari M, Shipley M, Stafford M, Kivimäki M. Association of diurnal patterns in salivary cortisol with all-cause and cardiovascular mortality: findings from the Whitehall II study. J Clin Endocrinol Metab. 2011;96(5):1478–85. doi:10.1210/jc.2010-2137. PMID: 21346074.
- Karl S, Johar H, Ladwig KH, Peters A, Lederbogen F. Dysregulated diurnal cortisol patterns are associated with cardiovascular mortality: findings from the KORA-F3 study. Psychoneuroendocrinology. 2022;141:105753. doi:10.1016/j.psyneuen.2022.105753. PMID: 35395560.
- Ronaldson A, Kidd T, Poole L, Leigh E, Jahangiri M, Steptoe A. Diurnal cortisol rhythm is associated with adverse cardiac events and mortality in coronary artery bypass patients. J Clin Endocrinol Metab. 2015;100(10):3676–82. doi:10.1210/jc.2015-2617. PMID: 26305622. PMCID: PMC4889728.
- Vogelzangs N, Beekman ATF, Milaneschi Y, Bandinelli S, Ferrucci L, Penninx BWJH. Urinary cortisol and six-year risk of all-cause and cardiovascular mortality. J Clin Endocrinol Metab. 2010;95(11):4959–64. doi:10.1210/jc.2010-0192. PMID: 20739384.
- van der Valk ES, Mohseni M, Iyer AM, et al. Long-term glucocorticoid exposure and incident cardiovascular diseases — the Lifelines cohort. J Clin Endocrinol Metab. 2024;109(10):2520–9. doi:10.1210/clinem/dgae081. PMID: 38500477. PMCID: PMC11403319. Outcome is broad CVD.
- Stomby A, Strömberg S, Theodorsson E, Faresjö ÅO, Jones M, Faresjö T. Standard modifiable cardiovascular risk factors mediate the association between elevated hair cortisol concentrations and coronary artery disease. Front Cardiovasc Med. 2022;8:765000. doi:10.3389/fcvm.2021.765000. PMID: 35146006. PMCID: PMC8821522. Cross-sectional mediation analysis; not a SCAPIS analysis.
- Hamer M, Endrighi R, Venuraju SM, Lahiri A, Steptoe A. Cortisol responses to mental stress and the progression of coronary artery calcification in healthy men and women. PLoS One. 2012;7(2):e31356. doi:10.1371/journal.pone.0031356. PMID: 22328931. PMCID: PMC3273460.
- Hajat A, Diez-Roux AV, Sanchez BN, Holvoet P, Bild D, Seeman T, et al. Examining the association between salivary cortisol levels and subclinical measures of atherosclerosis: the Multi-Ethnic Study of Atherosclerosis. Psychoneuroendocrinology. 2013;38(7):1036–46. doi:10.1016/j.psyneuen.2012.10.007. PMID: 23146655. PMCID: PMC4020284.
- Flynn S, Srikanthan P, Ravellette K, Inoue K, Watson K, Horwich T. Urinary cortisol and cardiovascular events in women vs. men: the Multi-Ethnic Study of Atherosclerosis. Am Heart J Plus. 2023;36:100344. doi:10.1016/j.ahjo.2023.100344. PMID: 37982128. PMCID: PMC10655947.
- Crawford AA, Soderberg S, Kirschbaum C, Murphy L, Eliasson M, Ebrahim S, et al. Morning plasma cortisol as a cardiovascular risk factor: findings from prospective cohort and Mendelian randomization studies. Eur J Endocrinol. 2019;181(4):429–38. doi:10.1530/EJE-19-0161. PMID: 31325907. PMCID: PMC6733337.
- Crawford AA, Bankier S, Altmaier E, Barnes CLK, Clark DW, Ermel R, et al. Variation in the SERPINA6/SERPINA1 locus alters morning plasma cortisol, hepatic corticosteroid binding globulin expression, gene expression in peripheral tissues, and risk of cardiovascular disease. J Hum Genet. 2021;66(6):625–36. doi:10.1038/s10038-020-00895-6. PMID: 33469137.
- Pilz S, Theiler-Schwetz V, Trummer C, et al. Associations of serum cortisol with cardiovascular risk and mortality in patients referred to coronary angiography (LURIC). J Endocr Soc. 2021;5(5):bvab017. doi:10.1210/jendso/bvab017. PMID: 33869979. PMCID: PMC8041336.
- Limumpornpetch P, Morgan AW, Tiganescu A, Baxter PD, Nyawira Nyaga V, Pujades-Rodriguez M, et al. The effect of endogenous Cushing syndrome on all-cause and cause-specific mortality. J Clin Endocrinol Metab. 2022;107(8):2377–88. doi:10.1210/clinem/dgac265. PMID: 35486378. PMCID: PMC9282270.
- Reynolds RM, Ilyas B, Price JF, Fowkes FGR, Newby DE, Webb DJ, Walker BR. Circulating plasma cortisol concentrations are not associated with coronary artery disease or peripheral vascular disease. QJM. 2009;102(7):469–75. doi:10.1093/qjmed/hcp057. PMID: 19458201.
- Ortiz R, Kluwe B, Lazarus S, Teruel MN, Joseph JJ. Cortisol and cardiometabolic disease: a target for advancing health equity. Trends Endocrinol Metab. 2022;33(11):786–97. doi:10.1016/j.tem.2022.08.002. PMID: 36266164. PMCID: PMC9676046. Narrative review; cited as a secondary synthesis for glucocorticoid receptor, pre-receptor metabolism and cardiometabolic framework, not as primary evidence for any individual molecular step.
- Ghiadoni L, Donald AE, Cropley M, et al. Mental stress induces transient endothelial dysfunction in humans. Circulation. 2000;102(20):2473–8. doi:10.1161/01.CIR.102.20.2473. PMID: 11076819. Small experimental sample.
- Lima BB, Hammadah M, Kim JH, et al. Association of transient endothelial dysfunction induced by mental stress with major adverse cardiovascular events in men and women with coronary artery disease. JAMA Cardiol. 2019;4(10):988–96. doi:10.1001/jamacardio.2019.3252. PMID: 31509180. PMCID: PMC6739728.
- Sullivan S, Young A, Garcia M, et al. Sex differences in vascular response to mental stress and adverse cardiovascular events among patients with ischemic heart disease. Arterioscler Thromb Vasc Biol. 2023;43(5):e112–e120. doi:10.1161/ATVBAHA.122.318576. PMID: 36857628. PMCID: PMC10164352.
- Hinterdobler J, Schott S, Jin H, et al. Acute mental stress drives vascular inflammation and promotes plaque destabilization in mouse atherosclerosis. Eur Heart J. 2021;42(39):4077–88. doi:10.1093/eurheartj/ehab371. PMID: 34279021. PMCID: PMC8516477. Human data concern leukocyte redistribution; plaque destabilization is mouse evidence.
- Thrall G, Lane D, Carroll D, Lip GYH. A systematic review of the effects of acute psychological stress and physical activity on haemorheology, coagulation, fibrinolysis and platelet reactivity: implications for the pathogenesis of acute coronary syndromes. Thromb Res. 2007;120(6):819–47. doi:10.1016/j.thromres.2007.01.004. PMID: 17321571.
- Wei J, Rooks C, Ramadan R, Shah AJ, Bremner JD, Quyyumi AA, et al. Meta-analysis of mental stress-induced myocardial ischemia and subsequent cardiac events in patients with coronary artery disease. Am J Cardiol. 2014;114(2):187–92. doi:10.1016/j.amjcard.2014.04.022. PMID: 24856319.
- Kivimäki M, Steptoe A. Effects of stress on the development and progression of cardiovascular disease. Nat Rev Cardiol. 2018;15(4):215–29. doi:10.1038/nrcardio.2017.189. PMID: 29213140.
- Hackett RA, Steptoe A, Kumari M. Association of diurnal patterns in salivary cortisol with type 2 diabetes in the Whitehall II study. J Clin Endocrinol Metab. 2014;99(12):4625–31. doi:10.1210/jc.2014-2459. PMID: 25215558.
- Alfredsson L, Hammar N, Fransson E, et al. Job strain and major risk factors for coronary heart disease among employed males and females in a Swedish study on work, lipids and fibrinogen. Scand J Work Environ Health. 2002;28(4):238–48. doi:10.5271/sjweh.671. PMID: 12199425.
- Brindle RC, Pearson A, Ginty AT. Adverse childhood experiences (ACEs) relate to blunted cardiovascular and cortisol reactivity to acute laboratory stress: a systematic review and meta-analysis. Neurosci Biobehav Rev. 2022;134:104530. doi:10.1016/j.neubiorev.2022.104530. PMID: 35031343.
- Salomon RE, Tan KR, Vaughan A, Adynski H, Muscatell KA. Minimally-invasive methods for examining biological changes in response to chronic stress: a scoping review. Int J Nurs Stud. 2020;103:103419. doi:10.1016/j.ijnurstu.2019.103419. PMID: 31945603. PMCID: PMC7067628.
- Chauntry AJ, Diaz KM, Sloan RP, et al. Psychobiological reactivity to acute psychological stress as a predictor of cardiovascular disease and mortality: the Multi-Ethnic Study of Atherosclerosis. Psychoneuroendocrinology. 2026;183:107657. doi:10.1016/j.psyneuen.2025.107657. PMID: 41135261.
- Pan Y, Fan F, Jiang J, Zhang Y. Clinical outcomes of anti-inflammatory therapies inhibiting the NLRP3/IL-1β/IL-6/CRP pathway in coronary artery disease patients: a systematic review and meta-analysis. Inflamm Res. 2025;74:99. doi:10.1007/s00011-025-02058-9. PMID: 40583093. PMCID: PMC12206679.
- Bando S, Fukuda D, Soeki T, et al. Expression of NLRP3 in subcutaneous adipose tissue is associated with coronary atherosclerosis. Atherosclerosis. 2015;242(2):407–14. doi:10.1016/j.atherosclerosis.2015.07.043. PMID: 26282945. NLRP3 measured in subcutaneous adipose tissue; psychological stress not assessed.
- Goodwin JE, Feng Y, Velazquez H, Zhou H, Sessa WC. Endothelial glucocorticoid receptor suppresses atherogenesis — brief report. Arterioscler Thromb Vasc Biol. 2015;35(4):779–82. doi:10.1161/ATVBAHA.114.304525. PMID: 25810297. PMCID: PMC4375730. ApoE-deficient mouse model; not human evidence.
- Levine GN, Lange RA, Bairey-Merz CN, Davidson RJ, Jamerson K, Mehta PK, et al. Meditation and cardiovascular risk reduction: a scientific statement from the American Heart Association. J Am Heart Assoc. 2017;6(10):e002218. doi:10.1161/JAHA.117.002218. PMID: 28963100.
- Levine GN, Cohen BE, Commodore-Mensah Y, Fleury J, Huffman JC, Khalid U, et al. Psychological health, well-being, and the mind-heart-body connection: a scientific statement from the American Heart Association. Circulation. 2021;143(10):e763–83. doi:10.1161/CIR.0000000000000947. PMID: 33486973.
- Levine GN, Carney RM, Cohen BE, et al. Post-myocardial infarction psychological distress: a scientific statement from the American Heart Association. Circulation. 2025;152:e298–e310. doi:10.1161/CIR.0000000000001381. PMID: 40977387. PMCID: PMC12919889.
- Brook RD, Appel LJ, Rubenfire M, Ogedegbe G, Bisognano JD, Elliott WJ, et al. Beyond medications and diet: alternative approaches to lowering blood pressure — a scientific statement from the American Heart Association. Hypertension. 2013;61(6):1360–83. doi:10.1161/HYP.0b013e318293645f. PMID: 23608661.
- Rees K, Takeda A, Court R, Kudrna L, Hartley L, Ernst E. Meditation for the primary and secondary prevention of cardiovascular disease. Cochrane Database Syst Rev. 2024;2(2):CD013358. doi:10.1002/14651858.CD013358.pub2. PMID: 38358047. PMCID: PMC10867897.
- Rogerson O, Wilding S, Prudenzi A, O’Connor DB. Effectiveness of stress management interventions to change cortisol levels: a systematic review and meta-analysis. Psychoneuroendocrinology. 2024;159:106415. doi:10.1016/j.psyneuen.2023.106415. PMID: 37879237.
- Koncz A, Demetrovics Z, Takacs ZK. Meditation interventions efficiently reduce cortisol levels of at-risk samples: a meta-analysis. Health Psychol Rev. 2021;15(1):56–84. doi:10.1080/17437199.2020.1760727. PMID: 32635830.
- Sanada K, Montero-Marin J, Alda Díez M, Salas-Valero M, Pérez-Yus MC, Morillo H, et al. Effects of mindfulness-based interventions on salivary cortisol in healthy adults: a meta-analytical review. Front Physiol. 2016;7:471. doi:10.3389/fphys.2016.00471. PMID: 27807420. PMCID: PMC5069287.
- Dunn TJ, Dimolareva M. The effect of mindfulness-based interventions on immunity-related biomarkers: a comprehensive meta-analysis of randomised controlled trials. Clin Psychol Rev. 2022;92:102124. doi:10.1016/j.cpr.2022.102124. PMID: 35078038.
- Lindsay EK, Marsland AL, Cole SW, et al. Mindfulness-based stress reduction reduces proinflammatory gene regulation but not systemic inflammation among older adults: a randomized controlled trial. Psychosom Med. 2024;86(5):463–72. doi:10.1097/PSY.0000000000001264. PMID: 37982547. PMCID: PMC11098967. Published online 2023.
- Creswell JD, Irwin MR, Burklund LJ, Lieberman MD, Arevalo JMG, Ma J, Breen EC, Cole SW. Mindfulness-Based Stress Reduction training reduces loneliness and pro-inflammatory gene expression in older adults: a small randomized controlled trial. Brain Behav Immun. 2012;26(7):1095–101. doi:10.1016/j.bbi.2012.07.006. PMID: 22820409. PMCID: PMC3635809.
- Brown L, Rando AA, Eichel K, Van Dam NT, Celano CM, Huffman JC, et al. The effects of mindfulness and meditation on vagally mediated heart rate variability: a meta-analysis. Psychosom Med. 2021;83(6):631–40. doi:10.1097/PSY.0000000000000900. PMID: 33395216.
- Hughes JW, Fresco DM, Myerscough R, van Dulmen MHM, Carlson LE, Josephson R. Randomized controlled trial of mindfulness-based stress reduction for prehypertension. Psychosom Med. 2013;75(8):721–8. doi:10.1097/PSY.0b013e3182a3e4e5. PMID: 24127622.
- Blom K, Baker B, How M, Dai M, Irvine J, Abbey S, et al. Hypertension analysis of stress reduction using mindfulness meditation and yoga: results from the HARMONY randomized controlled trial. Am J Hypertens. 2014;27(1):122–9. doi:10.1093/ajh/hpt134. PMID: 24038797.
- Loucks EB, Schuman-Olivier Z, Saadeh FB, et al. Effect of adapted mindfulness training in participants with elevated office blood pressure: the MB-BP study — a randomized clinical trial. J Am Heart Assoc. 2023;12(11):e028712. doi:10.1161/JAHA.122.028712. PMID: 37218591. PMCID: PMC10381983. Multicomponent intervention; investigator commercial interest disclosed.
- Wu F, Brewer LC, Neves VV, Scarpaci MM, Saadeh FB, Proulx JA, Loucks EB. Impact of the mindfulness-based blood pressure reduction (MB-BP) program on cardiovascular health: a randomized clinical trial. Am J Prev Cardiol. 2026;27:101584. doi:10.1016/j.ajpc.2026.101584. PMID: 42291030. PMCID: PMC13261222.
- Anderson JW, Liu C, Kryscio RJ. Blood pressure response to Transcendental Meditation: a meta-analysis. Am J Hypertens. 2008;21(3):310–6. doi:10.1038/ajh.2007.65. PMID: 18311126.
- Bai Z, Chang J, Chen C, Li P, Yang K, Chi I. Investigating the effect of transcendental meditation on blood pressure: a systematic review and meta-analysis. J Hum Hypertens. 2015;29(11):653–62. doi:10.1038/jhh.2015.6. PMID: 25673114.
- Fisher V, Li WW, Malabu U. The effectiveness of mindfulness-based stress reduction (MBSR) on the mental health, HbA1c, and mindfulness of diabetes patients: a systematic review and meta-analysis of randomised controlled trials. Appl Psychol Health Well Being. 2023;15(4):1733–49. doi:10.1111/aphw.12441. PMID: 36855248.
- Castillo-Richmond A, Schneider RH, Alexander CN, Cook R, Myers H, Nidich S, et al. Effects of stress reduction on carotid atherosclerosis in hypertensive African Americans. Stroke. 2000;31(3):568–73. doi:10.1161/01.STR.31.3.568. PMID: 10700487.
- Schneider RH, Grim CE, Rainforth MV, Kotchen T, Nidich SI, Gaylord-King C, et al. Stress reduction in the secondary prevention of cardiovascular disease: randomized, controlled trial of Transcendental Meditation and health education in Blacks. Circ Cardiovasc Qual Outcomes. 2012;5(6):750–8. doi:10.1161/CIRCOUTCOMES.112.967406. PMID: 23149426.
- Norris KC, Salerno J, Bairey Merz CN, Kaushik V, Gelleta S, Castillo A, Nidich S, Gaylord-King C, Schneider RH. A randomized controlled trial of meditation and health education on carotid intima-media thickness and major adverse cardiovascular events in Black men and women. Front Med (Lausanne). 2025;12:1513699. doi:10.3389/fmed.2025.1513699. PMID: 40177279. PMCID: PMC11962031. Trial conducted 2000–2014; registered retrospectively (NCT05642936). Declares no commercial or financial conflict of interest; author institutional affiliations constitute an allegiance concern.
- Gaylord-King C, Harris CL, Xu S, Salerno JW, Walton KG, Bairey-Merz CN, Nidich S, Schneider RH. A multicenter randomized controlled trial of meditation and health education in the prevention of cardiometabolic disease in Black women. J Womens Health. 2025;34(10):1247–56. doi:10.1177/15409996251364663. PMID: 40759176.
- Schneider RH, Norris KC, Brook RD. Transcendental Meditation to combat psychosocial stress, hypertension and cardiovascular disease. Nat Rev Cardiol. 2026;23(1):4–5. doi:10.1038/s41569-025-01235-x. PMID: 41266880. Commentary, not primary outcome evidence; cited to document investigator allegiance. Disclosed conflicts include an author commercial interest.
- Farias M, Maraldi E, Wallenkampf KC, Lucchetti G. Adverse events in meditation practices and meditation-based therapies: a systematic review. Acta Psychiatr Scand. 2020;142(5):374–93. doi:10.1111/acps.13225. PMID: 32820538.
- Landsbergis P, Schnall P. Job strain and coronary heart disease [correspondence]. Lancet. 2013;381(9865):448. doi:10.1016/S0140-6736(13)60242-1. PMID: 23399068.
- Choi B, Schnall P, Ko S, Dobson M, Baker D. Job strain and coronary heart disease [correspondence]. Lancet. 2013;381(9865):448. doi:10.1016/S0140-6736(13)60243-3. PMID: 23399069.
- Kivimäki M, Singh-Manoux A, Nyberg S, Batty GD. Job strain and coronary heart disease — authors’ reply. Lancet. 2013;381(9865):448–9. doi:10.1016/S0140-6736(13)60244-5. PMID: 23399067.
- Hamer M, Steptoe A. Cortisol responses to mental stress and incident hypertension in healthy men and women. J Clin Endocrinol Metab. 2012;97(1):E29–34. doi:10.1210/jc.2011-2132. PMID: 22031509.
- Borén J, Chapman MJ, Krauss RM, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease: pathophysiological, genetic, and therapeutic insights — a consensus statement from the European Atherosclerosis Society Consensus Panel. Eur Heart J. 2020;41(24):2313–30. doi:10.1093/eurheartj/ehz962. PMID: 32052833. PMCID: PMC7308544.
- Spieker LE, Hürlimann D, Ruschitzka F, Corti R, Enseleit F, Shaw S, Hayoz D, Deanfield JE, Lüscher TF, Noll G. Mental stress induces prolonged endothelial dysfunction via endothelin-A receptors. Circulation. 2002;105(24):2817–20. doi:10.1161/01.CIR.0000021598.15895.34. PMID: 12070106.
- Rocha HNM, Batista GMS, Storch AS, Garcia VP, Teixeira GF, Mentzinger J, Gomes EAC, Campos MO, Nóbrega ACL, Rocha NG. Mental stress induces endothelial dysfunction by AT1R-mediated redox imbalance in overweight/obese men. Braz J Med Biol Res. 2023;56:e12547. doi:10.1590/1414-431X2023e12547. PMID: 36995873. PMCID: PMC10041671. Three-way randomized crossover, n = 15; single sex and body-composition stratum.
- Adam EK, Quinn ME, Tavernier R, McQuillan MT, Dahlke KA, Gilbert KE. Diurnal cortisol slopes and mental and physical health outcomes: a systematic review and meta-analysis. Psychoneuroendocrinology. 2017;83:25–41. doi:10.1016/j.psyneuen.2017.05.018. PMID: 28578301. PMCID: PMC5568897. 179 associations from 80 studies to January 2015; overall r = 0.147; cardiovascular-disease subgroup not significant in random-effects analysis.
Verification Note
Quantitative estimates were cross-checked against the primary publication or the cited systematic review wherever available. INTERHEART and INTERSTROKE figures are reported with 99% confidence intervals per the original study designs; all other intervals are 95% unless stated.
Three points of interpretation are flagged for the reader. First, the Tawakol psychometric substudy comprised n = 13 participants, and correlations from that substudy should be treated as exploratory. Second, the trial published in 2025 reports a ten-year hazard ratio of 0.485 with a 95% confidence interval of 0.226–1.044 alongside p = 0.0435; these are internally inconsistent as published, and this review therefore does not describe that result as statistically significant. Third, the Transcendental Meditation hard-endpoint literature (references 65–69) should be read with explicit awareness of researcher allegiance and institutional affiliation; where a financial interest is separately disclosed — as for the MB-BP programme (reference 60) and the 2026 commentary (reference 69) — this is stated, and where trials declare no financial conflict the concern is allegiance rather than undeclared financial interest.
Figures 1A and 6 are schematic representations, not plots of measured data. All other figures plot values reported in the cited primary sources.

