
Lipoprotein(a): How Much Worse Does It Make Heart Disease?
1. What Lipoprotein(a) Is
Lipoproteína(a), abbreviated Lp(a), is a low-density lipoproteína (LDL)–like particle containing one molecule of apolipoproteína B-100 (ApoB) covalently linked to a second proteína, apolipoprotein(a), or apo(a). Apo(a) is encoded by the gen LPA and contains repeated kringle-IV domains; variation in the number and sequence of those repeats is a principal reason plasma concentrations differ by orders of magnitude between individuals.
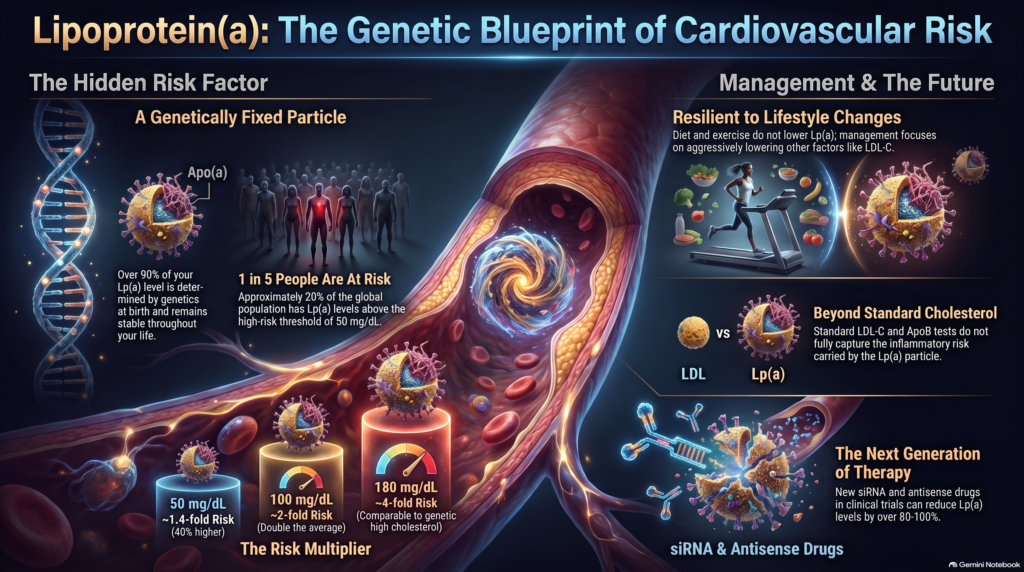
Lp(a) concentration is predominantly genetically determined. The 2022 European Ateroesclerosis Society (EAS) consensus statement attributes more than 90% of interindividual variation to genetic variability at the LPA locus [1]. Concentrations are generally stable enough that a single adult measurement is sufficient for risk assessment, although kidney, liver and thyroid disease, pregnancy, the menopausia transition, and certain medications can alter measured levels [1,2].
Lp(a) is often somewhat higher in women after menopause, although the magnitude varies by population and study [1,2]. Median concentrations also differ among ancestry groups, with wide within-group distributions — addressed quantitatively in Section 6.
Lp(a) should not be treated as simply another LDL-C measurement. Every Lp(a) particle contains ApoB and can enter the arterial wall, while the attached apo(a) makes Lp(a) an important carrier of oxidized phospholipids that may promote inflammatory and calcific processes [1]. Conventional LDL-C and ApoB measurements therefore do not fully capture the cardiovascular risk associated with Lp(a).
Units: mg/dL versus nmol/L
La Lp(a) se expresa como masa (mg/dL) o como concentración de partículas (nmol/L). Dado que las isoformas de la apo(a) difieren sustancialmente en su masa molecular, una partícula que porta una isoforma grande pesa más que una que porta una isoforma pequeña. Por lo tanto, no existe un factor de conversión fijo que sea válido universalmente. Las expresiones emparejadas como “50 mg/dL ≈ 125 nmol/L” son aproximaciones epidemiológicas que se utilizan para comunicar el riesgo —incluso en la propia guía de 2026— y no son conversiones de laboratorio. Mantenga las unidades reportadas por el laboratorio y no aplique una conversión fija de masa a molar.
2. ¿Es la Lp(a) un factor causal?
La evidencia de que los niveles elevados de Lp(a) son una causa y no solo un marcador de riesgo es inusualmente sólida para un biomarcador, que se apoya en tres líneas convergentes: prospectiva epidemiología, humano genética incluyendo Aleatorización mendeliana, y una relación dosis-respuesta constante.
En el Emerging Risk Factors Collaboration, 126 634 personas de 36 estudios prospectivos aportaron aproximadamente 1,3 millones de años-persona de seguimiento, durante los cuales se registraron 22 076 primeros eventos graves vasculares o no vasculares, incluidos 9 336 enfermedad coronaria (CHD) y 1.903 accidentes cerebrovasculares isquémicos. La razón de riesgo ajustada de cardiopatía coronaria fue de 1,13 (IC 95 %: 1,09–1,18) por cada aumento de 3,5 veces en el nivel habitual de Lp(a) [3].
Los estudios genéticos refuerzan la inferencia causal, ya que los alelos de la LPA se determinan en el momento de la concepción y no están sujetos a causalidad inversa. En tres estudios realizados en Copenhague, con un total de 40 486 participantes, los análisis genéticos respaldaron la causalidad; en el Estudio del Corazón de la Ciudad de Copenhague, la variable instrumental cociente de riesgos instantáneos fue de 1,22 (IC 95 %: 1,09–1,37) por cada duplicación de la Lp(a) predicha genéticamente [4]. En PROCARDIS, las variantes rs10455872 y rs3798220 del gen LPA presentaron razones de probabilidad de cardiopatía coronaria (CHD) por alelo de 1,70 (IC 95 % 1,49–1,95) y 1,92 (IC 95 % 1,48–2,49) [5].
La distinción que importa desde el punto de vista clínico: este conjunto de pruebas respalda firmemente que los niveles elevados de Lp(a) son un factor causal de la ASCVD. No establece que reducir los niveles de Lp(a) con un medicamento, a partir de la mediana edad, revierta ese riesgo lo suficiente como para prevenir eventos. Esa cuestión se aborda en las secciones 12 a 14.
3. ¿En qué medida aumenta el Lp(a) el riesgo cardiovascular?
El resumen más claro a nivel poblacional de la actualidad se encuentra en la Tabla 4 del 2026 ACC/AHA Multisociety Dyslipidemia Guideline [2]. En comparación con una mediana poblacional de aproximadamente 20 nmol/L (unos 7 mg/dL), la guía estima el riesgo de ASCVD de la siguiente manera.
| Nivel de Lp(a) | Percentil aproximado | Riesgo relativo estimado de ASCVD | Interpretación |
| <30 mg/dL (<75 nmol/L) | No se indica específicamente en la tabla de directrices | Referencia | Rango de riesgo más bajo relacionado con la Lp(a); no es un “riesgo cero” |
| 30–49 mg/dL (75–124 nmol/L) | No se especifica con precisión | ~1,2 veces | Aumento modesto del riesgo relativo |
| 50 mg/dL (125 nmol/L) | ~80.º | ~1,4 veces | Un riesgo relativo estimado de ASCVD aproximadamente 40% mayor que la mediana de referencia |
| 100 mg/dL (250 nmol/L) | ~95.º | ~2 veces | Aproximadamente el doble del riesgo estimado de ASCVD |
| 150 mg/dL (350 nmol/L) | No se especifica; se encuentra entre los valores de referencia del percentil ~95 (100 mg/dL) y el percentil ~99 (180 mg/dL) establecidos en la guía. | ~3 veces | Estimación de riesgo muy alta a nivel poblacional |
| 180 mg/dL (430 nmol/L) | ~99.º | ~4 veces | Riesgo estimado comparable al de los heterocigotos hipercolesterolemia familiar |
Tabla 1. Riesgo relativo estimado de ASCVD según las directrices de la ACC/AHA de 2026, en función de la concentración de Lp(a).
Advertencias importantes que se indican en la propia guía: estos valores se derivan de UK Biobank, sirven como guía general, pueden variar entre otras poblaciones y utilizan únicamente una equivalencia aproximada entre mg/dL y nmol/L [2]. Se trata de estimaciones a nivel poblacional, no específicas de cada paciente calculadora de riesgo.
Estas estimaciones son promedios poblacionales, no un destino ineludible. Describen cómo varían las tasas de incidencia entre grupos de personas con diferentes concentraciones de Lp(a); no predicen lo que le sucederá a una persona en particular.
La Lp(a) se comporta como una variable continua factor de riesgo. There is no biological cliff between 49 and 51 mg/dL; risk rises continuously rather than switching on at a single threshold. UK Biobank demonstrates this directly: among 460,506 participants followed for a median of 11.2 years, 22,401 incident ASCVD events occurred, median Lp(a) was 19.6 nmol/L, and risk increased approximately linearly at a hazard ratio of 1.11 (95% CI 1.10–1.12) per 50-nmol/L increment [6].
Separately, and at a different threshold, UK Biobank reported that among participants without previous ASCVD, 12.2% had Lp(a) ≥150 nmol/L, with an adjusted hazard ratio of 1.50 (95% CI 1.44–1.56); among those with preexisting ASCVD, prevalence was 20.3% and the hazard ratio 1.16 (95% CI 1.05–1.27) [6]. This ≥150 nmol/L figure must not be confused with, or used to corroborate, a 150 mg/dL (350 nmol/L) exposure — they are very different concentrations.
Why some studies report threefold to fourfold risk
Apparently divergent estimates can often be explained in substantial part by differences in endpoint, comparator, Lp(a) threshold, population, and statistical model rather than by direct contradiction.
In the Copenhagen City Heart Study, 9,330 participants were followed for 10 years and 498 developed infarto de miocardio (MI). Compared with Lp(a) below 5 mg/dL, adjusted MI hazard ratios in women were 1.1 (95% CI 0.6–1.9) at 5–29 mg/dL, 1.7 (1.0–3.1) at 30–84 mg/dL, 2.6 (1.2–5.9) at 85–119 mg/dL, and 3.6 (1.7–7.7) at 120 mg/dL or above. In men the corresponding figures were 1.5 (0.9–2.3), 1.6 (1.0–2.6), 2.6 (1.2–5.5), and 3.7 (1.7–8.0) [7].
It is therefore correct to say that extreme Lp(a) was associated with approximately threefold to fourfold higher MI risk in that cohort. It is not correct to equate that with the guideline’s approximately twofold estimate at 100 mg/dL: the Copenhagen extreme category was 120 mg/dL or above versus a very low comparator of under 5 mg/dL, with an MI-specific endpoint, whereas the guideline estimate is broad ASCVD at 100 mg/dL versus a population-median reference in UK Biobank-derived modeling.
4. Translating Relative Risk Into Absolute Terms
A hazard ratio of 1.4 denotes approximately 40% higher estimated instantaneous event hazard under the proportional-hazards model. It does not mean a 40% probability of having an event, and it is not mathematically identical to multiplying an individual’s 10-year event probability by 1.4.
The following table is an arithmetic illustration only, assuming the stated multiplier behaves as a simple risk ratio applied directly to a baseline probability.
| Hypothetical baseline 10-year risk | RR 1.2 | RR 1.4 | RR 1.7 | RR 2.0 |
| 5% | 6% | 7% | 8.5% | 10% |
| 10% | 12% | 14% | 17% | 20% |
| 20% | 24% | 28% | 34% | 40% |
| 30% | 36% | 42% | 51% | 60% |
Table 2. Pure arithmetic illustration assuming a risk ratio acts multiplicatively on baseline probability. These values are not individualized Lp(a)-adjusted risk predictions.
These are arithmetic illustrations assuming the stated multiplier behaves as a risk ratio applied directly to baseline probability. They are not individualized predictions, and an individual’s risk should not be estimated by multiplying the output of a clinical risk calculator by a hazard ratio or odds ratio reported in a study. The 2026 guideline Lp(a) values are not validated multipliers for an individual clinical risk score.
The clinical point the table makes is nonetheless important: the same multiplier adds far more riesgo absoluto to a person whose baseline is already high. Copenhagen provides real, study-specific absolute figures. Among fumar, hypertensive participants older than 60, 10-year MI risk was approximately 20% in women and 35% in men with Lp(a) of 120 mg/dL or above, compared with approximately 10% and 19% respectively at under 5 mg/dL [7]. Even in that high-risk subgroup, elevated Lp(a) changed probability rather than making MI inevitable.
5. How Common Is Elevated Lp(a)?
Approximately one in five people has Lp(a) at or above commonly used high-risk thresholds of roughly 50 mg/dL or 125 nmol/L, depending on the assay and reporting units, making elevated Lp(a) very common worldwide [1]. The exact global burden depends on the threshold, the assay, and the demographic distribution examined, so a single precise headcount should be treated with caution. The 2026 guideline places 50 mg/dL near the 80th percentile, 100 mg/dL near the 95th, and 180 mg/dL near the 99th [2].
6. Ancestry
Lp(a) distributions differ by ancestry. In UK Biobank, median concentrations were approximately 19 nmol/L in White, 31 nmol/L in South Asian, 75 nmol/L in Black, and 16 nmol/L in Chinese participants. The association between rising Lp(a) and ASCVD was directionally similar across the major groups studied, with hazard ratios per 50 nmol/L of approximately 1.11, 1.10, and 1.07 in White, South Asian, and Black participants respectively; subgroup estimates outside the White group are less precise because of smaller sample sizes [6].
The 2026 guideline similarly notes that concentrations tend to be highest among people of African and South Asian ancestry, while the relative-risk association remains broadly similar across ancestry groups [2].
These are population distributions with wide within-group variation. They do not justify inferring an individual’s Lp(a) concentration or cardiovascular risk from ancestry alone. The only way to know a person’s Lp(a) is to measure it.
7. Lp(a) in People Who Already Have Cardiovascular Disease
In a Copenhagen secondary-prevention cohort of 2,527 people with prior enfermedad cardiovascular followed for a median of five years, 493 experienced a evento cardiovascular adverso mayor (MACE). Event rates were 29, 35, 42, and 54 per 1,000 person-years at Lp(a) under 10, 10–49, 50–99, and 100 mg/dL or above respectively. Relative to under 10 mg/dL, adjusted incidence-rate ratios were 1.28 (95% CI 1.03–1.58), 1.44 (95% CI 1.12–1.85), and 2.14 (95% CI 1.57–2.92) [8].
In UK Biobank, the relative association at Lp(a) ≥150 nmol/L was smaller in participants with established ASCVD (HR 1.16, 95% CI 1.05–1.27) than in those without prior ASCVD (HR 1.50, 95% CI 1.44–1.56), although absolute event risk was higher in prevención secundaria [6].
Evidence from the PCSK9-inhibitor trials
En Fourier, 25,096 patients with established ASCVD had Lp(a) measured and were followed for a median of 2.2 years. Among placebo-treated participants, the highest Lp(a) cuartil carried an adjusted hazard ratio of 1.22 (95% CI 1.01–1.48) for coronary death, myocardial infarction, or urgent revascularización compared with the lowest quartile, independently of LDL-C. Evolocumab reduced Lp(a) by a median of 26.9% [9].
In secondary analyses of that trial, patients with higher baseline Lp(a) appeared to derive greater coronary benefit: the hazard ratio was 0.77 (95% CI 0.67–0.88) above the median baseline Lp(a) versus 0.93 (95% CI 0.80–1.08) below it, with a three-year absolute risk reduction of 2.49% versus 0.95% and numbers needed to treat of 40 versus 105. The interaction P value was 0.07 and therefore did not reach conventional statistical significance. This is a subgroup finding within a randomized trial, not the primary randomized comparison [9].
En Odisea OUTCOMES, 18,924 patients following an síndrome coronario agudo were followed for a median of 2.8 years on intensive estatinas therapy. Baseline Lp(a) independently predicted recurrent events. In post-hoc analyses, alirocumab-associated reductions in Lp(a) were independently associated with fewer cardiovascular events; however, these analyses cannot establish that the Lp(a) reduction itself caused the event reduction, because alirocumab simultaneously produces large reductions in LDL-C and ApoB [10,11].
Both trials therefore support elevated Lp(a) as a marker of riesgo residual in treated patients, and both are consistent with — but do not prove — a benefit attributable to Lp(a) lowering itself.
8. Does Very Low LDL-C Eliminate the Risk?
La reducción del colesterol LDL (LDL-C) disminuye considerablemente el riesgo cardiovascular, pero no parece eliminar el riesgo residual asociado a la Lp(a). Un análisis a nivel de participantes realizado en 2025 con 27 658 personas en seis ensayos controlados con placebo de estatinas reveló que, incluso en el cuartil más bajo de colesterol LDL alcanzado —de 3,1 a 77,0 mg/dL —, una Lp(a) superior a 50 mg/dL se asoció con un razón de riesgo de ASCVD de 1,38 (IC 95 %: 1,06–1,79) en comparación con valores de 50 mg/dL o menos. La categoría combinada más alta de Lp(a) elevada y el nivel más alto de colesterol LDL (LDL-C) alcanzado presentó una razón de riesgo de 1,90 (IC 95 %: 1,46–2,48) [12].
Dado que ese cuartil más bajo abarca de 3,1 a 77,0 mg/dL, el análisis demuestra la persistencia del riesgo incluso con niveles de LDL-C relativamente bajos, pero no ofrece una estimación específica para niveles de LDL-C inferiores a 55 mg/dL. No se debe deducir de estos datos una cifra específica del riesgo residual en ese umbral.
La formulación defendible: la reducción intensiva del colesterol LDL y la ApoB disminuye el riesgo absoluto general de ASCVD, pero los datos disponibles no establecen una concentración de colesterol LDL a partir de la cual desaparezca la asociación con niveles elevados de Lp(a).
9. Lp(a) y ApoB: se superponen, pero no son intercambiables
La concentración plasmática de ApoB es un indicador práctico del número de partículas de lipoproteínas aterogénicas circulantes que contienen ApoB, incluidas las LDL, VLDL restos, IDL, y Lp(a). Debido a que cada partícula de Lp(a) contiene en sí misma una ApoB-100 La molécula, la Lp(a) y la ApoB no son vías biológicas independientes; se superponen.
Lo que distingue a la Lp(a) es su biología adicional relacionada con la apo(a) y los fosfolípidos oxidados. Los análisis de ajuste y mediación sugieren que los marcadores lipídicos e inflamatorios convencionales —incluidos el colesterol LDL (LDL-C), el colesterol no-HDL (non-HDL-C), la apolipoproteína B (ApoB) y la proteína C-reactiva de alta sensibilidad (hsCRP)— explican solo una pequeña parte de la asociación entre la Lp(a) y la ASCVD [13].
Un análisis genético de 2024 estimó que la asociación con la cardiopatía coronaria (CHD) por cada incremento de 50 nmol/L en la Lp(a)-ApoB era sustancialmente mayor que la asociación para el mismo incremento en LDL-ApoB, con una relación estimada por partícula de aproximadamente 6,6 (IC 95 %: 5,1–8,8) [14]. Se trata de una estimación del tamaño del efecto mediante aleatorización mendeliana que se basa en supuestos metodológicos. No constituye una prueba de que ninguna partícula individual de Lp(a) sea, literalmente, 6.6 veces más dañina desde el punto de vista biológico que una partícula de LDL.
Ambos hallazgos son compatibles: la Lp(a) contribuye a la ApoB total, al tiempo que conlleva un riesgo que no queda adecuadamente reflejado solo con la concentración convencional de ApoB.
10. Lp(a) y estenosis aórtica calcificada
De los 77 680 participantes de Copenhague a los que se les hizo un seguimiento durante un máximo de 20 años, 454 desarrollaron estenosis aórtica. En comparación con los niveles de Lp(a) inferiores a 5 mg/dL, las razones de riesgo ajustadas aumentaron a 1,6 (IC 95%: 1,1–2,4) en el rango de 20 a 64 mg/dL, 2,0 (IC 95%: 1,2–3,4) en el rango de 65 a 90 mg/dL, y 2,9 (IC 95%: 1,8–4,9) por encima de los 90 mg/dL. El análisis de variables instrumentales genéticas arrojó un riesgo relativo de 1,6 (IC 95 %: 1,2–2,1) por cada aumento de 10 veces en el nivel de Lp(a), lo que respalda una contribución causal [15].
En un análisis independiente realizado en Copenhague, cada aumento de 10 veces en el nivel de Lp(a) se asoció con una razón de probabilidades de 1,62 (IC 95 %: 1,48–1,77) para la válvula aórtica calcificación y un cociente de riesgo de 1,54 (IC 95 %: 1,38–1,71) para la válvula aórtica estenosis, de los cuales aproximadamente 31% del efecto se deben a la calcificación [16].
Entre los pacientes que ya padecían estenosis aórtica, un estudio prospectivo con 145 pacientes reveló que los niveles más elevados de Lp(a) y fosfolípidos oxidados se asociaban con una mayor actividad de calcificación valvular y una progresión más rápida del calcio en la tomografía computarizada y de los parámetros hemodinámicos. Los participantes en el tercil superior de Lp(a), en comparación con los dos terciles inferiores, presentaban un mayor riesgo de sustitución de la válvula aórtica o de muerte (razón de riesgo 1,87; IC 95 %: 1,13–3,08); los parámetros relacionados con los fosfolípidos oxidados mostraron asociaciones similares. Los experimentos in vitro complementarios respaldaron un mecanismo procalcificante [17]. Estos hallazgos observacionales y mecánicos respaldan la base biológica, pero no demuestran que reducir farmacológicamente los niveles de Lp(a) frene la estenosis aórtica ya establecida. Hasta la fecha, ningún ensayo aleatorio ha demostrado que reducir los niveles de Lp(a) prevenga la progresión de la estenosis aórtica o reduzca la necesidad de reemplazo valvular.
Lp(a) is also linked to atherothrombosis and aortic-valve stenosis independent of inflamación. In 68,090 Copenhagen participants followed for a median of 8.1 years, Lp(a) of 70 mg/dL or above versus 6 mg/dL or below was associated with an ASCVD hazard ratio of 1.61 (95% CI 1.43–1.81) among those with Proteína C reactiva under 2 mg/L and 1.57 (95% CI 1.36–1.82) among those with CRP of 2 mg/L or above, interaction P = 0.87 [18].
11. Does High Lp(a) Mean You Will Have a Heart Attack?
No. Lp(a) changes probability; it does not determine outcome. Even in the Copenhagen high-risk subgroup — smokers with hipertensión over age 60 and Lp(a) of 120 mg/dL or above — 10-year MI risk was approximately 20% in women and 35% in men, not 100% [7]. Other baseline-risk profiles differ substantially.
A person with high Lp(a) but excellent presión arterial, no diabetes, no smoking, low ApoB and LDL-C, and favorable imaging may have a much lower absolute risk than someone with the same Lp(a) plus multiple major risk factors. Age, smoking, blood pressure, diabetes, enfermedad renal, cumulative ApoB and LDL exposure, historial familiar, and existing atherosclerosis jointly determine absolute cardiovascular risk alongside Lp(a) [2].
12. Currently Available Treatments
The treatment section must distinguish three separate questions: does the treatment change Lp(a); does it reduce cardiovascular events overall; and has any event benefit been proven to result specifically from lowering Lp(a)? These are not interchangeable.
| Terapia | Effect on Lp(a) | Approximate LDL-C effect [2] | Evidence and safety | Cardiovascular outcome status |
| Estatinas | On average a modest increase; pooled statin-to-placebo ratio of geometric means 1.11 (95% CI 1.07–1.14); statin-arm mean changes about +8.5% to +19.6% | Moderate-intensity ~30% to <50%; high-intensity ≥50% | Participant-level metaanálisis, n = 5,256. Whether the modest rise independently affects outcomes is uncertain. | Substantial ASCVD benefit via LDL/ApoB lowering. Not a reason to withhold indicated statin therapy. |
| Ezetimiba | Small and inconsistent. A seven-trial meta-analysis of ezetimibe monotherapy reported −7.06% (95% CI −11.95 to −2.18) [19]; a broader analysis including combination therapy found no statistically significant reduction (−2.59%, 95% CI −8.26 to 3.08) [20] | Approximately 15–20% additional lowering when added to a statin | Estimates differ substantially between syntheses. | Its clinical role is LDL-C lowering, not targeted Lp(a) reduction; no Lp(a)-specific outcome evidence. |
| PCSK9 monoclonal antibodies | Mean approximately −27% (95% CI −29.8 to −24.1); evolocumab −29.35%, alirocumab −24.50% | Approximately 50–60% | Meta-analysis of 47 randomized trials, 67,057 participants [21]. | Overall event reduction proven; the incremental causal contribution of Lp(a) lowering is unproven. |
| Inclisiran | Modest — approximately 18–22% in pooled trial analyses [22,23] | Approximately 50%; pooled ORION-9/10/11 analysis (n = 3,660) placebo-corrected reduction −50.7% [23] | Injection-site adverse events 5.0% versus 0.7% with placebo in the pooled Orión analysis [23]. | No dedicated proof that its modest Lp(a) reduction causes event reduction. |
| Niacina | Approximately −21% in the AIM-HIGH Lp(a) analysis [24] | Modest | HPS2-THRIVE: major vascular events 13.2% vs 13.7%, rate ratio 0.96 (95% CI 0.90–1.03), P = 0.29, with excess serious adverse events [25]. | No added benefit on contemporary therapy. Should not be prescribed solely to lower Lp(a). |
| Lipoprotein apheresis | Approximately −60% to −70% acutely; 68.1% mean single-treatment reduction in Pro(a)LiFe [26,27] | Large acute reduction per session, with rebound between sessions | Levels rebound between sessions, so the time-averaged reduction is smaller than the immediate post-procedure reduction. | Uncontrolled before-after cohorts report large event-rate reductions [26,27]; confusor, selection, and regression to the mean prevent causal claims. |
Table 3. Effects of currently available therapies on Lp(a) and on cardiovascular outcomes.
On statins specifically: the pooled participant-level meta-analysis confirms a modest average increase in Lp(a) [28]. Whether that increase independently affects outcomes is uncertain, and it is not a reason to stop indicated statin therapy, because the LDL and ApoB lowering statins achieve has established cardiovascular benefit.
13. Investigational Lp(a)-Targeted Therapies
A new class of agents lowers Lp(a) far more dramatically than any conventional lipid therapy. These trials establish pharmacodynamic proof, not clinical-outcome proof.
The key distinction is that lowering a laboratory value is not the same as proving fewer infartos cardíacos o golpes.
A biomarker reduction of 90% must not be translated into an assumed 90% reduction in events.
| Agent (class) | Trial and size | Lp(a) reduction | Safety findings |
| Pelacarsen (antisense oligonucleotide) | Phase 2, n = 286 [29] | Up to 80% mean reduction at the highest regimen | Injection-site reactions most common; no major platelet, liver, or renal imbalance in phase 2 |
| Olpasiran (siRNA) | OCEAN(a)-DOSE, n = 281 [30] | Placebo-adjusted −70.5%, −97.4%, −101.1%, and −100.5% by regimen at week 36 | Overall adverse events similar to placebo; injection-site reactions most common |
| Lepodisiran (siRNA) | ALPACA, n = 320 [31] | Pooled 400 mg: placebo-adjusted time-averaged −93.9% (95% CI −95.1 to −92.5), days 60–180 | 35 serious adverse events, none deemed treatment-related; generally mild injection-site reactions in up to 12% |
| Zerlasiran (siRNA) | ALPACAR-360, n = 178 [32] | Time-averaged −85.6%, −82.8%, and −81.3% by regimen (all >80%) | Mild injection-site pain in approximately 2.3–7.1%; 20 serious adverse events in 17 patients, none considered drug-related |
| Muvalaplin (oral small molecule) | KRAKEN, n = 233 [33] | Up to −85.8% using the intact-Lp(a) assay; approximately −70% by apo(a) assay | No major safety or tolerability concern reported over the trial period |
Table 4. Phase 2 biomarker results for Lp(a)-targeted agents.
Placebo-adjusted values slightly beyond 100% reflect the statistical adjustment calculation, not physically negative Lp(a) concentrations.
14. The Dedicated Outcomes Trials
These trials are the decisive tests of whether lowering Lp(a) prevents cardiovascular events. Lp(a)HORIZON’s registered primary endpoint is time to first expanded major adverse cardiovascular event in patients with established cardiovascular disease and Lp(a) ≥70 mg/dL, with a second primary analysis in those ≥90 mg/dL. Registry status is fast-moving content and must be re-verified immediately before publication.
| Trial (agent) | Registry ID | Estado | Enrollment | Estimated primary completion |
| Lp(a)HORIZON (pelacarsen) | NCT04023552 | Active, not recruiting; no results posted; record last updated 6 May 2026 and last verified May 2026; sponsor Novartis | 8,323 (actual) | 30 June 2026 (estimated) |
| OCEAN(a)-Outcomes (olpasiran) | NCT05581303 | Active, not recruiting; no results posted; record updated 27 February 2026. Established ASCVD with Lp(a) ≥200 nmol/L; eligible ASCVD includes prior MI or PCI with stenting plus an additional risk factor; anticipated follow-up approximately four years | 7,297 (actual) | 31 March 2028 |
| ACCLAIM-Lp(a) (lepodisiran) | NCT06292013 | Active, not recruiting; no results posted; record updated 18 June 2026. Lp(a) ≥175 nmol/L; addendum adds approximately 1,700 participants | 17,300 (estimated) | March 2029 |
| MOVE-Lp(a) (muvalaplin) | NCT07157774 | Recruiting; no results posted; record updated 7 July 2026 | 10,450 (estimated); actual start 2 September 2025 | March 2031 |
Table 5. Dedicated Lp(a)-lowering cardiovascular-outcomes programs, per ClinicalTrials.gov as cited in the August 2026 audit.
A further pelacarsen study, ADD-VANTAGE (NCT06813911), is a recruiting phase 3 study of pelacarsen on a background of inclisiran in patients with elevated Lp(a) and established ASCVD. As checked on 28 August 2026, ClinicalTrials.gov listed the record as last updated 17 June 2026, with no results posted, estimated enrollment of 340, and estimated primary completion 3 February 2028. Its primary endpoint is change in Lp(a) rather than cardiovascular events, so it is a biomarker study and should not be grouped with the dedicated cardiovascular-outcomes trials in Table 5 [38].
As of 28 August 2026, the primary ClinicalTrials.gov records for the major dedicated Lp(a)-lowering cardiovascular-outcomes programs show no posted results. Selective pharmacologic Lp(a) lowering has therefore not yet been demonstrated in a dedicated randomized outcomes trial to reduce cardiovascular events.
Lp(a)HORIZON remains listed as active, not recruiting, despite a 30 June 2026 estimated primary-completion date; OCEAN(a)-Outcomes and ACCLAIM-Lp(a) remain active but not recruiting, and MOVE-Lp(a) is recruiting. A passed estimated date is not evidence that a trial should be described as completed or that any result exists.
15. How Much Would Lp(a) Need to Fall?
Two Mendelian-randomization analyses have estimated the lifelong genetically proxied Lp(a) difference associated with a CHD-risk difference comparable to that associated with 1 mmol/L (38.67 mg/dL) lower LDL-C. Burgess and colleagues estimated 101.5 mg/dL (95% CI 71.0–137.0), reporting an odds ratio of 0.942 per 10 mg/dL lower genetically predicted Lp(a) [39]. Lamina and Kronenberg estimated 65.7 mg/dL (95% CI 46.3–88.3) [40].
The estimates differ in important part because of differences in Lp(a) distributions, assay calibration, and analytical design across the underlying datasets. Both analyses used predominantly European-ancestry datasets and assay-dependent Lp(a) mass measurements.
Both imply that substantial absolute differences in lifelong Lp(a) exposure correspond to clinically meaningful differences in CHD risk. Neither establishes what reduction a drug must achieve over a finite treatment period, and neither should be presented as a validated pharmacologic target. Lifelong genetic exposure beginning at conception is not equivalent to years of drug therapy begun after placa has accumulated.
A separate observational modeling projection from the Copenhagen secondary-prevention cohort estimated that lowering Lp(a) by approximately 50 mg/dL (105 nmol/L) over five years might correspond to 20% lower MACE, and approximately 99 mg/dL (212 nmol/L) to 40% lower MACE [8]. These are modeled projections from observational data, not trial-proven treatment effects.
16. Who Should Be Tested
The 2026 ACC/AHA Multisociety Dislipidemia Guideline recommends measuring Lp(a) at least once in adulthood, and the EAS consensus supports the same approach [2,1]. Measurement is particularly informative in premature ASCVD, a strong family history of premature cardiovascular disease, familial hipercolesterolemia, recurrent events despite well-controlled LDL-C, and calcific aortic stenosis.
Cascade Lp(a) testing of familiares de primer grado is reasonable when markedly elevated Lp(a) is identified. In ordinary practice this means measuring the Lp(a) concentration in relatives, not genotyping them.
Repeat measurement is generally unnecessary, because Lp(a) is predominantly genetically determined and generally stable over time. Repeat testing may nevertheless be appropriate when disease, pregnancy or menopause-related changes, medications, assay uncertainty, or Lp(a)-directed therapy could materially alter the measured concentration.
17. What This Means for You
Lp(a) is an inherited, cholesterol-containing lipoprotein particle that can substantially increase the risk of heart attack, stroke, and aortic-valve disease. At around 50 mg/dL, average relative ASCVD risk is roughly 40% higher than at the guideline’s reference median; at very high levels around 180 mg/dL, average relative risk may be about four times higher [2]. That does not mean a heart attack is inevitable.
Because lifestyle change does not lower Lp(a) appreciably [1,2], healthy behavior should not be judged by whether the Lp(a) number falls. Exercise, avoiding tobacco, maintaining healthy body composition, controlling blood pressure and diabetes, and following a heart-healthy dietary pattern act on the other components of absolute risk. Lowering LDL-C and ApoB is a central evidence-based strategy, because these are modifiable causal exposures that add to the inherited Lp(a)-associated risk.
LDL-C goals should be individualized by risk category rather than applied uniformly. The 2026 guideline recommends LDL-C below 55 mg/dL for very-high-risk ASCVD and below 70 mg/dL for ASCVD not meeting very-high-risk criteria. In prevención primaria con ateroesclerosis subclínica, progressively higher calcio en las arterias coronarias (CAC) burden supports progressively more intensive LDL-C lowering: CAC of 100–299 or at or above the 75th percentile supports LDL-C below 70 mg/dL; CAC of 300–999 supports below 70 mg/dL with at least a 50% reduction, and intensification toward below 55 mg/dL is reasonable in selected patients; CAC of 1000 or above supports below 55 mg/dL with at least a 50% reduction [2].
CAC scoring can be useful selectively — in selected primary-prevention adults for whom the treatment decision remains uncertain after conventional risk assessment and consideration of risk enhancers such as elevated Lp(a). Elevated Lp(a) by itself does not create a universal indication for a calcium scan [2].
Where CAC is obtained, it strongly modifies absolute risk in people with elevated Lp(a). In MESA, elevated Lp(a) with a CAC score of zero was not significantly associated with higher ASCVD risk than low Lp(a) with CAC of zero (hazard ratio 1.31, 95% CI 0.73–2.35), whereas elevated Lp(a) together with CAC of 100 or above identified markedly higher risk (hazard ratio 4.71, 95% CI 3.01–7.40) [41]. A 2026 multicohort study of 11,319 participants followed for a mean of 14.8 years found that elevated Lp(a) above 50 mg/dL was associated with higher ASCVD risk even among people with a CAC score of zero (hazard ratio 1.28, 95% CI 1.01–1.60), although absolute event rates in that group remained low at 4.9 versus 3.8 per 1,000 person-years [42]. A CAC score of zero should therefore be read as low observed absolute plaque-related risk over the period studied, not as evidence that lifelong Lp(a)-associated risk has disappeared. CAC measures disease already present; Lp(a) measures a lifelong causal exposure [1,2].
Until dedicated outcome trials of Lp(a)-specific drugs report, the most evidence-based strategy is intensive, guideline-directed management of every modifiable cardiovascular risk factor, particularly LDL-C and ApoB.
18. Evidence Hierarchy
- Strong evidence: Lp(a) is a causal, continuously graded risk factor for ASCVD, supported by cohortes prospectivas, LPA genetics, Mendelian aleatorización, and dose–response. Lp(a) makes a causal contribution to calcific aortic-valve disease.
- Moderate-to-strong evidence: elevated Lp(a) remains associated with residual ASCVD risk in statin-treated and aggressively LDL-lowered populations. Conventional ApoB does not fully capture Lp(a)-associated risk. Elevated Lp(a) predicts recurrent events in established ASCVD.
- Moderate evidence: the genetically estimated per-particle atherogenicity of Lp(a) relative to LDL. Post-hoc PCSK9-inhibitor analyses suggesting greater absolute benefit at higher baseline Lp(a).
- Emerging evidence: whether pharmacologic Lp(a) lowering reduces cardiovascular events. Biomarker efficacy of the investigational agents is established; cardiovascular-outcome efficacy remains unproven in the audited primary data.
So, How Much Worse Does Lp(a) Make Heart Disease?
- Elevated Lp(a) is common: approximately one in five people has a concentration at or above commonly used high-risk thresholds of roughly 50 mg/dL or 125 nmol/L.
- Risk rises continuously rather than switching on at a threshold. The 2026 guideline estimates approximately 1.2-fold ASCVD risk at 30–49 mg/dL, 1.4-fold at 50 mg/dL, 2-fold at 100 mg/dL, 3-fold at 150 mg/dL, and 4-fold at 180 mg/dL, compared with a population median of about 7 mg/dL (20 nmol/L). These are UK Biobank-derived general-guide estimates.
- Extreme concentrations have been associated with roughly threefold to fourfold higher MI risk in some cohorts — in Copenhagen, at 120 mg/dL or above versus under 5 mg/dL, with an MI-specific endpoint. That is a different question from the guideline’s broad-ASCVD estimate at 100 mg/dL.
- In people who already have cardiovascular disease, higher Lp(a) predicts more recurrent events, with adjusted incidence-rate ratios rising to 2.14 at 100 mg/dL or above versus under 10 mg/dL.
- Low LDL-C does not eliminate the risk. Lp(a)-associated risk persisted in the lowest achieved-LDL-C quartile of pooled statin trials, and it is incompletely represented by conventional ApoB measurement — even though each Lp(a) particle itself contributes one ApoB-100 molecule.
- Very high Lp(a) is associated with roughly threefold higher incident aortic-stenosis risk in Copenhagen data, and genetic evidence supports a causal contribution to calcific aortic-valve disease.
- What patients can do now: measure Lp(a) once; if elevated, intensify guideline-directed control of every modifiable risk factor, with LDL-C goals set by risk category; consider CAC selectively when a primary-prevention treatment decision remains uncertain; and arrange cascade testing of first-degree relatives.
- What remains unknown: whether profoundly lowering Lp(a) prevents cardiovascular events. As of 28 August 2026, no dedicated phase 3 Lp(a)-lowering outcomes result had been posted. Lp(a)HORIZON, OCEAN(a)-Outcomes, ACCLAIM-Lp(a), and MOVE-Lp(a) are designed to answer that question, with estimated primary completions from 2026 through 2031.
Referencias
- Kronenberg F, Mora S, Stroes ESG, et al. Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: a European Atherosclerosis Society consensus statement. Eur Heart J. 2022;43(39):3925–3946. DOI: 10.1093/eurheartj/ehac361. PMID: 36036785.
- 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia. Circulation. 2026. DOI: 10.1161/CIR.0000000000001423. PMID: 41824590.
- Erqou S, Kaptoge S, Perry PL, et al; Emerging Risk Factors Collaboration. Lipoprotein(a) concentration and the risk of coronary heart disease, stroke, and nonvascular mortality. JAMA. 2009;302(4):412–423. DOI: 10.1001/jama.2009.1063. PMID: 19622820.
- Kamstrup PR, Tybjærg-Hansen A, Steffensen R, Nordestgaard BG. Genetically elevated lipoprotein(a) and increased risk of myocardial infarction. JAMA. 2009;301(22):2331–2339. DOI: 10.1001/jama.2009.801. PMID: 19509380.
- Clarke R, Peden JF, Hopewell JC, et al; PROCARDIS Consortium. Genetic variants associated with Lp(a) lipoprotein level and coronary disease. N Engl J Med. 2009;361(26):2518–2528. DOI: 10.1056/NEJMoa0902604. PMID: 20032323.
- Patel AP, Wang M, Pirruccello JP, et al. Lp(a) concentrations and incident atherosclerotic cardiovascular disease: new insights from a large national biobank. Arterioscler Thromb Vasc Biol. 2021;41(1):465–474. DOI: 10.1161/ATVBAHA.120.315291. PMID: 33115266.
- Kamstrup PR, Benn M, Tybjærg-Hansen A, Nordestgaard BG. Extreme lipoprotein(a) levels and risk of myocardial infarction in the general population: the Copenhagen City Heart Study. Circulation. 2008;117(2):176–184. DOI: 10.1161/CIRCULATIONAHA.107.715698. PMID: 18086931.
- Madsen CM, Kamstrup PR, Langsted A, Varbo A, Nordestgaard BG. Lipoprotein(a)-lowering by 50 mg/dL (105 nmol/L) may be needed to reduce cardiovascular disease 20% in secondary prevention. Arterioscler Thromb Vasc Biol. 2020;40(1):255–266. DOI: 10.1161/ATVBAHA.119.312951. PMID: 31578080.
- O’Donoghue ML, Fazio S, Giugliano RP, et al. Lipoprotein(a), PCSK9 inhibition, and cardiovascular risk: insights from the FOURIER trial. Circulation. 2019;139(12):1483–1492. DOI: 10.1161/CIRCULATIONAHA.118.037184. PMID: 30586750.
- Bittner VA, Szarek M, Aylward PE, et al; ODYSSEY OUTCOMES Committees and Investigators. Effect of alirocumab on lipoprotein(a) and cardiovascular risk after acute coronary syndrome. J Am Coll Cardiol. 2020;75(2):133–144. DOI: 10.1016/j.jacc.2019.10.057. PMID: 31948641.
- Szarek M, Bittner VA, Aylward P, et al; ODYSSEY OUTCOMES Investigators. Lipoprotein(a) lowering by alirocumab reduces the total burden of cardiovascular events independent of low-density lipoprotein cholesterol lowering. Eur Heart J. 2020;41(44):4245–4255. DOI: 10.1093/eurheartj/ehaa649. PMID: 33051646.
- Bhatia HS, Wandel S, Willeit P, et al. Independence of lipoprotein(a) and LDL cholesterol-mediated cardiovascular risk: a participant-level meta-analysis. Circulation. 2025;151(4):312–321. DOI: 10.1161/CIRCULATIONAHA.124.069556. PMID: 39492722.
- Thomas PE, Vedel-Krogh S, Kamstrup PR, Nordestgaard BG. Lipoprotein(a) cardiovascular risk explained by LDL cholesterol, non-HDL cholesterol, apoB, or hsCRP is minimal. J Am Coll Cardiol. 2025;85(21):2046–2051. DOI: 10.1016/j.jacc.2025.02.024. PMID: 40266171.
- Björnson E, Adiels M, Taskinen MR, et al. Lipoprotein(a) is markedly more atherogenic than LDL: an apolipoprotein B-based genetic analysis. J Am Coll Cardiol. 2024;83(3):385–395. DOI: 10.1016/j.jacc.2023.10.039. PMID: 38233012.
- Kamstrup PR, Tybjærg-Hansen A, Nordestgaard BG. Elevated lipoprotein(a) and risk of aortic valve stenosis in the general population. J Am Coll Cardiol. 2014;63(5):470–477. DOI: 10.1016/j.jacc.2013.09.038. PMID: 24161338.
- Kaltoft M, Langsted A, Nordestgaard BG. Elevated lipoprotein(a) in mitral and aortic valve calcification and disease: the Copenhagen General Population Study. Atherosclerosis. 2022;349:166–174. DOI: 10.1016/j.atherosclerosis.2021.11.029. PMID: 34903381.
- Zheng KH, Tsimikas S, Pawade T, et al. Lipoprotein(a) and oxidized phospholipids promote valve calcification in patients with aortic stenosis. J Am Coll Cardiol. 2019;73(17):2150–2162. DOI: 10.1016/j.jacc.2019.01.070. PMID: 31047003.
- Thomas PE, Vedel-Krogh S, Kamstrup PR, Nordestgaard BG. Lipoprotein(a) is linked to atherothrombosis and aortic valve stenosis independent of C-reactive protein. Eur Heart J. 2023;44(16):1449–1460. DOI: 10.1093/eurheartj/ehad055. PMID: 36805188.
- Awad K, Mikhailidis DP, Katsiki N, Muntner P, Banach M; Lipid and Blood Pressure Meta-Analysis Collaboration (LBPMC) Group. Effect of ezetimibe monotherapy on plasma lipoprotein(a) concentrations in patients with primary hypercholesterolemia: a systematic review and meta-analysis of randomized controlled trials. Drugs. 2018;78(4):453–462. DOI: 10.1007/s40265-018-0870-1. PMID: 29396832.
- Sahebkar A, Simental-Mendía LE, Pirro M, Banach M, Watts GF, Sirtori C, Al-Rasadi K, Atkin SL. Impact of ezetimibe on plasma lipoprotein(a) concentrations as monotherapy or in combination with statins: a systematic review and meta-analysis of randomized controlled trials. Sci Rep. 2018;8(1):17887. DOI: 10.1038/s41598-018-36204-7. PMID: 30552391.
- Rivera FB, Cha SW, Louisse CL, et al. Impact of proprotein convertase subtilisin/kexin type 9 inhibitors on lipoprotein(a): a meta-analysis and meta-regression of randomized controlled trials. JACC Adv. 2025;4(2):101549. DOI: 10.1016/j.jacadv.2024.101549. PMID: 39877671.
- Ray KK, Wright RS, Kallend D, et al; ORION-10 and ORION-11 Investigators. Two phase 3 trials of inclisiran in patients with elevated LDL cholesterol. N Engl J Med. 2020;382(16):1507–1519. DOI: 10.1056/NEJMoa1912387. PMID: 32187462.
- Wright RS, Ray KK, Raal FJ, et al. Pooled patient-level analysis of inclisiran trials in patients with familial hypercholesterolemia or atherosclerosis. J Am Coll Cardiol. 2021;77(9):1182–1193. DOI: 10.1016/j.jacc.2020.12.058. PMID: 33663735.
- Albers JJ, Slee A, O’Brien KD, et al. Relationship of apolipoproteins A-1 and B, and lipoprotein(a) to cardiovascular outcomes: the AIM-HIGH trial. J Am Coll Cardiol. 2013;62(17):1575–1579. DOI: 10.1016/j.jacc.2013.06.051. PMID: 23973688.
- HPS2-THRIVE Collaborative Group. Effects of extended-release niacin with laropiprant in high-risk patients. N Engl J Med. 2014;371(3):203–212. DOI: 10.1056/NEJMoa1300955. PMID: 25014686.
- Leebmann J, Roeseler E, Julius U, et al. Lipoprotein apheresis in patients with maximally tolerated lipid-lowering therapy, lipoprotein(a)-hyperlipoproteinemia, and progressive cardiovascular disease. Circulation. 2013;128(24):2567–2576. DOI: 10.1161/CIRCULATIONAHA.113.002432. PMID: 24056686.
- Roeseler E, Julius U, Heigl F, et al; Pro(a)LiFe-Study Group. Lipoprotein apheresis for lipoprotein(a)-associated cardiovascular disease: prospective 5-year results. Arterioscler Thromb Vasc Biol. 2016;36(9):2019–2027. DOI: 10.1161/ATVBAHA.116.307983. PMID: 27417585.
- Tsimikas S, Gordts PLSM, Nora C, Yeang C, Witztum JL. Statin therapy increases lipoprotein(a) levels. Eur Heart J. 2020;41(24):2275–2284. DOI: 10.1093/eurheartj/ehz310. PMID: 31111151.
- Tsimikas S, Karwatowska-Prokopczuk E, Gouni-Berthold I, et al. Lipoprotein(a) reduction in persons with cardiovascular disease. N Engl J Med. 2020;382(3):244–255. DOI: 10.1056/NEJMoa1905239. PMID: 31893580.
- O’Donoghue ML, Rosenson RS, Gencer B, et al. Small interfering RNA to reduce lipoprotein(a) in cardiovascular disease. N Engl J Med. 2022;387(20):1855–1864. DOI: 10.1056/NEJMoa2211023. PMID: 36342163.
- Nissen SE, Ni W, Shen X, et al; ALPACA Trial Investigators. Lepodisiran — a long-duration small interfering RNA targeting lipoprotein(a). N Engl J Med. 2025;392(17):1673–1683. DOI: 10.1056/NEJMoa2415818. PMID: 40162643.
- Nissen SE, Wang Q, Nicholls SJ, et al. Zerlasiran — a small-interfering RNA targeting lipoprotein(a): a phase 2 randomized clinical trial (ALPACAR-360). JAMA. 2024;332(23):1992–2002. DOI: 10.1001/jama.2024.21957. PMID: 39556769.
- Nicholls SJ, Ni W, Rhodes GM, et al. Oral muvalaplin for lowering of lipoprotein(a): a randomized clinical trial (KRAKEN). JAMA. 2025;333(3):222–231. DOI: 10.1001/jama.2024.24017. PMID: 39556768.
- Lp(a)HORIZON (pelacarsen). ClinicalTrials.gov identifier NCT04023552. https://clinicaltrials.gov/study/NCT04023552
- OCEAN(a)-Outcomes (olpasiran). ClinicalTrials.gov identifier NCT05581303. https://clinicaltrials.gov/study/NCT05581303
- ACCLAIM-Lp(a) (lepodisiran). ClinicalTrials.gov identifier NCT06292013. https://clinicaltrials.gov/study/NCT06292013
- MOVE-Lp(a) (muvalaplin). ClinicalTrials.gov identifier NCT07157774. https://clinicaltrials.gov/study/NCT07157774
- ADD-VANTAGE (pelacarsen on a background of inclisiran). ClinicalTrials.gov identifier NCT06813911. https://clinicaltrials.gov/study/NCT06813911
- Burgess S, Ference BA, Staley JR, et al. Association of LPA variants with risk of coronary disease and the implications for lipoprotein(a)-lowering therapies: a Mendelian randomization analysis. JAMA Cardiol. 2018;3(7):619–627. DOI: 10.1001/jamacardio.2018.1470. PMID: 29926099.
- Lamina C, Kronenberg F; Lp(a)-GWAS-Consortium. Estimation of the required lipoprotein(a)-lowering therapeutic effect size for reduction in coronary heart disease outcomes: a Mendelian randomization analysis. JAMA Cardiol. 2019;4(6):575–579. DOI: 10.1001/jamacardio.2019.1041. PMID: 31017618.
- Mehta A, Vasquez N, Ayers CR, Patel J, et al. Independent association of lipoprotein(a) and coronary artery calcification with atherosclerotic cardiovascular risk. J Am Coll Cardiol. 2022;79(8):757–768. DOI: 10.1016/j.jacc.2021.11.058. PMID: 35210030.
- Bhatia HS, Fan Y, Dharmavaram G, Zou H, et al. Use of coronary artery calcium scoring in individuals with elevated lipoprotein(a): a multicohort study. J Am Coll Cardiol. 2026;87(20):2864–2872. DOI: 10.1016/j.jacc.2026.02.5067. PMID: 41837904. PMCID: PMC13221166.

