
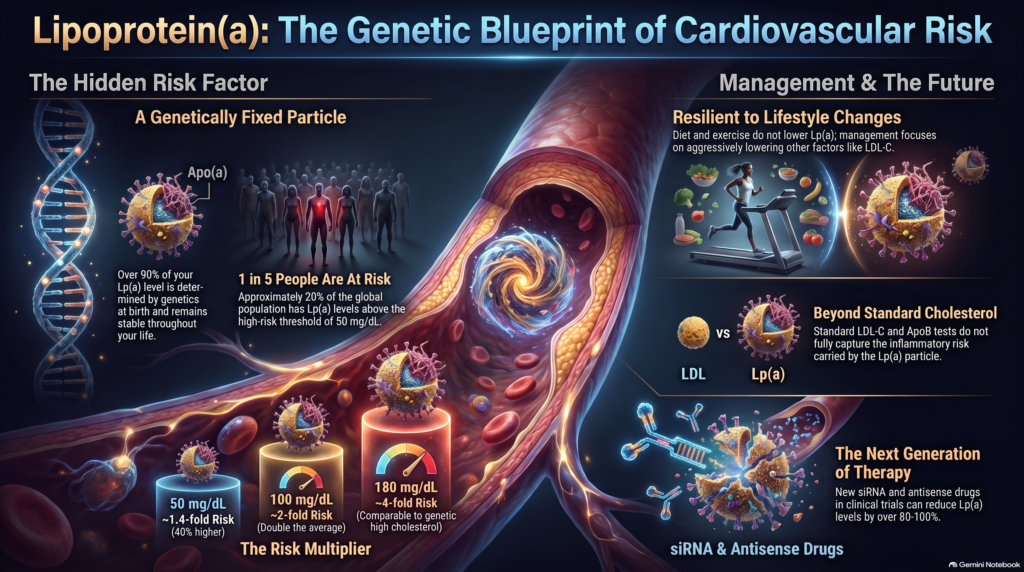
Lipoprotein(a): How Much Worse Does It Make Heart Disease?
1. What Lipoprotein(a) Is
Lipoproteïne(a), abbreviated Lp(a), is a low-density lipoproteïne (LDL)–like particle containing one molecule of apolipoproteïne B-100 (ApoB) covalently linked to a second eiwit, apolipoprotein(a), or apo(a). Apo(a) is encoded by the LPA-gen and contains repeated kringle-IV domains; variation in the number and sequence of those repeats is a principal reason plasma concentrations differ by orders of magnitude between individuals.
Lp(a) concentration is predominantly genetically determined. The 2022 European Aderverkalking Society (EAS) consensus statement attributes more than 90% of interindividual variation to genetic variability at the LPA locus [1]. Concentrations are generally stable enough that a single adult measurement is sufficient for risk assessment, although kidney, liver and thyroid disease, pregnancy, the menopauze transition, and certain medications can alter measured levels [1,2].
Lp(a) is often somewhat higher in women after menopause, although the magnitude varies by population and study [1,2]. Median concentrations also differ among ancestry groups, with wide within-group distributions — addressed quantitatively in Section 6.
Lp(a) should not be treated as simply another LDL-C measurement. Every Lp(a) particle contains ApoB and can enter the arterial wall, while the attached apo(a) makes Lp(a) an important carrier of oxidized phospholipids that may promote inflammatory and calcific processes [1]. Conventional LDL-C and ApoB measurements therefore do not fully capture the cardiovascular risk associated with Lp(a).
Units: mg/dL versus nmol/L
Lp(a) is reported either as mass (mg/dL) or as particle concentration (nmol/L). Because apo(a) isoforms differ substantially in molecular mass, a particle carrying a large isoform weighs more than one carrying a small isoform. There is consequently no universally valid fixed conversion factor. Paired expressions such as “50 mg/dL ≈ 125 nmol/L” are epidemiological approximations used for risk communication — including by the 2026 guideline itself — not laboratory conversions. Preserve the laboratory’s reported units and do not apply a fixed mass-to-molar conversion.
2. Is Lp(a) Causal?
The evidence that elevated Lp(a) is causal rather than merely a risk marker is unusually strong for a biomarker, resting on three converging lines: prospective epidemiologie, human genetica including Mendeliana randomisatie, and a consistent dose–response relationship.
In de Emerging Risk Factors Collaboration, 126,634 people from 36 prospective studies contributed approximately 1.3 million person-years of follow-up, during which 22,076 first major vascular or nonvascular outcomes were recorded, including 9,336 kransslagaderziekte (CHD) outcomes and 1,903 ischemic strokes. The adjusted CHD risk ratio was 1.13 (95% CI 1.09–1.18) per 3.5-fold higher usual Lp(a) [3].
Genetic studies strengthen the causal inference because LPA alleles are assigned at conception and are not subject to omgekeerde causaliteit. Across three Copenhagen studies totaling 40,486 participants, genetic analyses supported causality; in the Copenhagen City Heart Study the instrumental-variable hazardratio was 1.22 (95% CI 1.09–1.37) per genetically predicted doubling of Lp(a) [4]. In PROCARDIS, the LPA variants rs10455872 and rs3798220 carried per-allele CHD odds ratios of 1.70 (95% CI 1.49–1.95) and 1.92 (95% CI 1.48–2.49) [5].
The distinction that matters clinically: this body of evidence strongly supports elevated Lp(a) as a causal contributor to ASCVD. It does not establish that lowering Lp(a) with a drug, begun in middle age, reverses enough of that risk to prevent events. That question is addressed in Sections 12 through 14.
3. How Much Does Lp(a) Increase Cardiovascular Risk?
The clearest contemporary population-level summary is Table 4 of the 2026 ACC/AHA Multisociety Dyslipidemia Guideline [2]. Relative to a population median of approximately 20 nmol/L (about 7 mg/dL), the guideline estimates ASCVD risk as follows.
| Lp(a) level | Approx. percentile | Estimated relative ASCVD risk | Interpretatie |
| <30 mg/dL (<75 nmol/L) | Not specifically stated in guideline table | Referentie | Lower Lp(a)-related risk range; not “zero risk” |
| 30–49 mg/dL (75–124 nmol/L) | Not precisely specified | ~1.2-fold | Modest relative-risk increment |
| 50 mg/dL (125 nmol/L) | ~80th | ~1.4-fold | About 40% greater relative estimated ASCVD risk than the reference median |
| 100 mg/dL (250 nmol/L) | ~95th | ~2-fold | Approximately double the estimated ASCVD risk |
| 150 mg/dL (350 nmol/L) | Not specifically stated; lies between the guideline’s ~95th-percentile (100 mg/dL) and ~99th-percentile (180 mg/dL) anchors | ~3-fold | Very high population-level risk estimate |
| 180 mg/dL (430 nmol/L) | ~99th | ~4-fold | Estimated risk comparable to heterozygous familiaire hypercholesterolemie |
Table 1. 2026 ACC/AHA guideline estimated relative ASCVD risk by Lp(a) concentration.
Essential caveats stated by the guideline itself: these values are derived from UK Biobank, are intended as a general guide, may differ among other populations, and use only approximate equivalence between mg/dL and nmol/L [2]. They are population-level estimates, not a patient-specific risk calculator.
These estimates are population averages, not destiny. They describe how event rates differ between groups of people at different Lp(a) concentrations; they do not forecast what will happen to any one person.
Lp(a) behaves as a continuous risicofactor. There is no biological cliff between 49 and 51 mg/dL; risk rises continuously rather than switching on at a single threshold. UK Biobank demonstrates this directly: among 460,506 participants followed for a median of 11.2 years, 22,401 incident ASCVD events occurred, median Lp(a) was 19.6 nmol/L, and risk increased approximately linearly at a hazard ratio of 1.11 (95% CI 1.10–1.12) per 50-nmol/L increment [6].
Separately, and at a different threshold, UK Biobank reported that among participants without previous ASCVD, 12.2% had Lp(a) ≥150 nmol/L, with an adjusted hazard ratio of 1.50 (95% CI 1.44–1.56); among those with preexisting ASCVD, prevalence was 20.3% and the hazard ratio 1.16 (95% CI 1.05–1.27) [6]. This ≥150 nmol/L figure must not be confused with, or used to corroborate, a 150 mg/dL (350 nmol/L) exposure — they are very different concentrations.
Why some studies report threefold to fourfold risk
Apparently divergent estimates can often be explained in substantial part by differences in endpoint, comparator, Lp(a) threshold, population, and statistical model rather than by direct contradiction.
In the Copenhagen City Heart Study, 9,330 participants were followed for 10 years and 498 developed myocardinfarct (MI). Compared with Lp(a) below 5 mg/dL, adjusted MI hazard ratios in women were 1.1 (95% CI 0.6–1.9) at 5–29 mg/dL, 1.7 (1.0–3.1) at 30–84 mg/dL, 2.6 (1.2–5.9) at 85–119 mg/dL, and 3.6 (1.7–7.7) at 120 mg/dL or above. In men the corresponding figures were 1.5 (0.9–2.3), 1.6 (1.0–2.6), 2.6 (1.2–5.5), and 3.7 (1.7–8.0) [7].
It is therefore correct to say that extreme Lp(a) was associated with approximately threefold to fourfold higher MI risk in that cohort. It is not correct to equate that with the guideline’s approximately twofold estimate at 100 mg/dL: the Copenhagen extreme category was 120 mg/dL or above versus a very low comparator of under 5 mg/dL, with an MI-specific endpoint, whereas the guideline estimate is broad ASCVD at 100 mg/dL versus a population-median reference in UK Biobank-derived modeling.
4. Translating Relative Risk Into Absolute Terms
A hazard ratio of 1.4 denotes approximately 40% higher estimated instantaneous event hazard under the proportional-hazards model. It does not mean a 40% probability of having an event, and it is not mathematically identical to multiplying an individual’s 10-year event probability by 1.4.
The following table is an arithmetic illustration only, assuming the stated multiplier behaves as a simple risk ratio applied directly to a baseline probability.
| Hypothetical baseline 10-year risk | RR 1.2 | RR 1.4 | RR 1.7 | RR 2.0 |
| 5% | 6% | 7% | 8.5% | 10% |
| 10% | 12% | 14% | 17% | 20% |
| 20% | 24% | 28% | 34% | 40% |
| 30% | 36% | 42% | 51% | 60% |
Table 2. Pure arithmetic illustration assuming a risk ratio acts multiplicatively on baseline probability. These values are not individualized Lp(a)-adjusted risk predictions.
These are arithmetic illustrations assuming the stated multiplier behaves as a risk ratio applied directly to baseline probability. They are not individualized predictions, and an individual’s risk should not be estimated by multiplying the output of a clinical risk calculator by a hazard ratio or odds ratio reported in a study. The 2026 guideline Lp(a) values are not validated multipliers for an individual clinical risk score.
The clinical point the table makes is nonetheless important: the same multiplier adds far more absoluut risico to a person whose baseline is already high. Copenhagen provides real, study-specific absolute figures. Among roken, hypertensive participants older than 60, 10-year MI risk was approximately 20% in women and 35% in men with Lp(a) of 120 mg/dL or above, compared with approximately 10% and 19% respectively at under 5 mg/dL [7]. Even in that high-risk subgroup, elevated Lp(a) changed probability rather than making MI inevitable.
5. How Common Is Elevated Lp(a)?
Approximately one in five people has Lp(a) at or above commonly used high-risk thresholds of roughly 50 mg/dL or 125 nmol/L, depending on the assay and reporting units, making elevated Lp(a) very common worldwide [1]. The exact global burden depends on the threshold, the assay, and the demographic distribution examined, so a single precise headcount should be treated with caution. The 2026 guideline places 50 mg/dL near the 80th percentile, 100 mg/dL near the 95th, and 180 mg/dL near the 99th [2].
6. Ancestry
Lp(a) distributions differ by ancestry. In UK Biobank, median concentrations were approximately 19 nmol/L in White, 31 nmol/L in South Asian, 75 nmol/L in Black, and 16 nmol/L in Chinese participants. The association between rising Lp(a) and ASCVD was directionally similar across the major groups studied, with hazard ratios per 50 nmol/L of approximately 1.11, 1.10, and 1.07 in White, South Asian, and Black participants respectively; subgroup estimates outside the White group are less precise because of smaller sample sizes [6].
The 2026 guideline similarly notes that concentrations tend to be highest among people of African and South Asian ancestry, while the relative-risk association remains broadly similar across ancestry groups [2].
These are population distributions with wide within-group variation. They do not justify inferring an individual’s Lp(a) concentration or cardiovascular risk from ancestry alone. The only way to know a person’s Lp(a) is to measure it.
7. Lp(a) in People Who Already Have Cardiovascular Disease
In a Copenhagen secondary-prevention cohort of 2,527 people with prior hart- en vaatziekten followed for a median of five years, 493 experienced a ernstige nadelige cardiovasculaire gebeurtenis (MACE). Event rates were 29, 35, 42, and 54 per 1,000 person-years at Lp(a) under 10, 10–49, 50–99, and 100 mg/dL or above respectively. Relative to under 10 mg/dL, adjusted incidence-rate ratios were 1.28 (95% CI 1.03–1.58), 1.44 (95% CI 1.12–1.85), and 2.14 (95% CI 1.57–2.92) [8].
In UK Biobank, the relative association at Lp(a) ≥150 nmol/L was smaller in participants with established ASCVD (HR 1.16, 95% CI 1.05–1.27) than in those without prior ASCVD (HR 1.50, 95% CI 1.44–1.56), although absolute event risk was higher in secundaire preventie [6].
Evidence from the PCSK9-inhibitor trials
In Fourier, 25,096 patients with established ASCVD had Lp(a) measured and were followed for a median of 2.2 years. Among placebo-treated participants, the highest Lp(a) kwartiel carried an adjusted hazard ratio of 1.22 (95% CI 1.01–1.48) for coronary death, myocardial infarction, or urgent revascularisatie compared with the lowest quartile, independently of LDL-C. Evolocumab reduced Lp(a) by a median of 26.9% [9].
In secondary analyses of that trial, patients with higher baseline Lp(a) appeared to derive greater coronary benefit: the hazard ratio was 0.77 (95% CI 0.67–0.88) above the median baseline Lp(a) versus 0.93 (95% CI 0.80–1.08) below it, with a three-year absolute risk reduction of 2.49% versus 0.95% and numbers needed to treat of 40 versus 105. The interaction P value was 0.07 and therefore did not reach conventional statistical significance. This is a subgroup finding within a randomized trial, not the primary randomized comparison [9].
In Odyssee OUTCOMES, 18,924 patients following an acuut coronair syndroom were followed for a median of 2.8 years on intensive statine therapy. Baseline Lp(a) independently predicted recurrent events. In post-hoc analyses, alirocumab-associated reductions in Lp(a) were independently associated with fewer cardiovascular events; however, these analyses cannot establish that the Lp(a) reduction itself caused the event reduction, because alirocumab simultaneously produces large reductions in LDL-C and ApoB [10,11].
Both trials therefore support elevated Lp(a) as a marker of restrisico in treated patients, and both are consistent with — but do not prove — a benefit attributable to Lp(a) lowering itself.
8. Does Very Low LDL-C Eliminate the Risk?
Het verlagen van het LDL-C-gehalte vermindert het cardiovasculaire risico aanzienlijk, maar lijkt het aan Lp(a) gerelateerde restrisico niet volledig weg te nemen. Uit een analyse op deelnemersniveau uit 2025 onder 27.658 mensen in zes placebogecontroleerde statineonderzoeken bleek dat zelfs in het laagste kwartiel van bereikt LDL-C — 3,1 tot 77,0 mg/dL — Lp(a) boven 50 mg/dL geassocieerd was met een ASCVD-hazardratio van 1,38 (95% CI 1,06–1,79) in vergelijking met 50 mg/dL of lager. De hoogste gecombineerde categorie van verhoogd Lp(a) en de hoogste bereikte LDL-C-waarde ging gepaard met een hazardratio van 1,90 (95% CI 1,46–2,48) [12].
Aangezien dat laagste kwartiel zich uitstrekt van 3,1 tot 77,0 mg/dL, toont de analyse aan dat er ook bij een relatief laag bereikt LDL-C-gehalte nog steeds een risico bestaat, maar biedt zij geen specifieke schatting voor een LDL-C-gehalte onder de 55 mg/dL. Uit deze gegevens mag geen specifiek cijfer voor het restrisico bij die drempelwaarde worden afgeleid.
De verdedigbare formulering: een intensieve verlaging van LDL-C en ApoB vermindert het totale absolute ASCVD-risico, maar uit de beschikbare gegevens blijkt niet bij welke LDL-C-concentratie het verband met een verhoogd Lp(a)-gehalte verdwijnt.
9. Lp(a) en ApoB: overlappend, maar niet onderling uitwisselbaar
De ApoB-concentratie in het plasma is een praktische indicator voor het aantal circulerende atherogene lipoproteïnedeeltjes die ApoB bevatten, waaronder LDL, VLDL restanten, IDL, en Lp(a). Omdat elk Lp(a)-deeltje zelf één ApoB-100 Molecuul, Lp(a) en ApoB vormen geen afzonderlijke biologische routes; ze overlappen elkaar.
Wat Lp(a) onderscheidt, is de aanvullende biologie die verband houdt met apo(a) en geoxideerde fosfolipiden. Aanpassings- en mediatieanalyses suggereren dat conventionele lipiden- en ontstekingsmarkers — waaronder LDL-C, non-HDL-C, ApoB en hsCRP — slechts een klein deel van het verband tussen Lp(a) en ASCVD verklaren [13].
In een genetische analyse uit 2024 werd geschat dat het verband met CHD per 50 nmol/L genetisch geschatte toename in Lp(a)-ApoB aanzienlijk groter was dan de associatie voor dezelfde toename in LDL-ApoB, met een geschatte verhouding per deeltje van ongeveer 6,6 (95% CI 5,1–8,8) [14]. Dit is een schatting van de effectgrootte op basis van Mendeliaanse randomisatie, waarbij methodologische aannames worden gehanteerd. Het is geen bewijs dat elk afzonderlijk Lp(a)-deeltje letterlijk 6,6 keer zo schadelijk is als een LDL-deeltje.
Deze twee bevindingen sluiten op elkaar aan: Lp(a) draagt bij aan het totale ApoB-gehalte, maar brengt tegelijkertijd een risico met zich mee dat niet voldoende tot uiting komt in de conventionele ApoB-concentratie alleen.
10. Lp(a) en calcificerende aortaklepstenose
Van de 77.680 deelnemers uit Kopenhagen die tot wel 20 jaar lang werden gevolgd, kregen er 454 aortaklepstenose. In vergelijking met een Lp(a)-waarde van minder dan 5 mg/dL stegen de gecorrigeerde hazard ratio’s tot 1,6 (95% BI 1,1–2,4) bij 20–64 mg/dL, 2,0 (95% CI 1,2–3,4) bij 65–90 mg/dL en 2,9 (95% CI 1,8–4,9) bij meer dan 90 mg/dL. Genetische analyse met instrumentele variabelen leverde een relatief risico van 1,6 (95% CI 1,2–2,1) per 10-voudige stijging van Lp(a), wat wijst op een causale bijdrage [15].
In een afzonderlijke analyse uit Kopenhagen ging elke 10-voudige stijging van het Lp(a)-gehalte gepaard met een oddsratio van 1,62 (95% betrouwbaarheidsinterval 1,48–1,77) voor aortaklep verkalking en een hazardratio van 1,54 (95% BI 1,38–1,71) voor de aortaklep stenose, waarbij ongeveer 31% van het effect via verkalking tot stand komt [16].
Bij patiënten die al aortastenose hadden, bleek uit een prospectief onderzoek onder 145 patiënten dat hogere Lp(a)- en geoxideerde fosfolipidenwaarden geassocieerd waren met een grotere mate van klepverkalking en een snellere progressie van zowel de CT-calciumwaarden als de hemodynamische parameters. Deelnemers in het bovenste Lp(a)-tertiel hadden, in vergelijking met de twee onderste tertielen, een hoger risico op aortaklepvervanging of overlijden (hazardratio 1,87, 95% BI 1,13–3,08); gerelateerde waarden voor geoxideerde fosfolipiden vertoonden vergelijkbare associaties. Bijbehorende in-vitro-experimenten ondersteunden een procalcificerend mechanisme [17]. Deze observationele en mechanistische bevindingen ondersteunen de biologische grondgedachte, maar bewijzen niet dat een farmacologische verlaging van Lp(a) de ontwikkeling van bestaande aortastenose zal vertragen. Er is tot nu toe geen gerandomiseerde studie die heeft aangetoond dat een verlaging van Lp(a) de progressie van aortastenose voorkomt of het aantal klepvervangingen vermindert.
Lp(a) is also linked to atherothrombosis and aortic-valve stenosis independent of ontsteking. In 68,090 Copenhagen participants followed for a median of 8.1 years, Lp(a) of 70 mg/dL or above versus 6 mg/dL or below was associated with an ASCVD hazard ratio of 1.61 (95% CI 1.43–1.81) among those with C-reactieve proteïne under 2 mg/L and 1.57 (95% CI 1.36–1.82) among those with CRP of 2 mg/L or above, interaction P = 0.87 [18].
11. Does High Lp(a) Mean You Will Have a Heart Attack?
No. Lp(a) changes probability; it does not determine outcome. Even in the Copenhagen high-risk subgroup — smokers with hypertensie over age 60 and Lp(a) of 120 mg/dL or above — 10-year MI risk was approximately 20% in women and 35% in men, not 100% [7]. Other baseline-risk profiles differ substantially.
A person with high Lp(a) but excellent bloeddruk, no diabetes, no smoking, low ApoB and LDL-C, and favorable imaging may have a much lower absolute risk than someone with the same Lp(a) plus multiple major risk factors. Age, smoking, blood pressure, diabetes, nierziekte, cumulative ApoB and LDL exposure, familiegeschiedenis, and existing atherosclerosis jointly determine absolute cardiovascular risk alongside Lp(a) [2].
12. Currently Available Treatments
The treatment section must distinguish three separate questions: does the treatment change Lp(a); does it reduce cardiovascular events overall; and has any event benefit been proven to result specifically from lowering Lp(a)? These are not interchangeable.
| Therapie | Effect on Lp(a) | Approximate LDL-C effect [2] | Evidence and safety | Cardiovascular outcome status |
| Statines | On average a modest increase; pooled statin-to-placebo ratio of geometric means 1.11 (95% CI 1.07–1.14); statin-arm mean changes about +8.5% to +19.6% | Moderate-intensity ~30% to <50%; high-intensity ≥50% | Participant-level meta-analyse, n = 5,256. Whether the modest rise independently affects outcomes is uncertain. | Substantial ASCVD benefit via LDL/ApoB lowering. Not a reason to withhold indicated statin therapy. |
| Ezetimib | Small and inconsistent. A seven-trial meta-analysis of ezetimibe monotherapy reported −7.06% (95% CI −11.95 to −2.18) [19]; a broader analysis including combination therapy found no statistically significant reduction (−2.59%, 95% CI −8.26 to 3.08) [20] | Approximately 15–20% additional lowering when added to a statin | Estimates differ substantially between syntheses. | Its clinical role is LDL-C lowering, not targeted Lp(a) reduction; no Lp(a)-specific outcome evidence. |
| PCSK9 monoclonal antibodies | Mean approximately −27% (95% CI −29.8 to −24.1); evolocumab −29.35%, alirocumab −24.50% | Approximately 50–60% | Meta-analysis of 47 randomized trials, 67,057 participants [21]. | Overall event reduction proven; the incremental causal contribution of Lp(a) lowering is unproven. |
| Inclisiran | Modest — approximately 18–22% in pooled trial analyses [22,23] | Approximately 50%; pooled ORION-9/10/11 analysis (n = 3,660) placebo-corrected reduction −50.7% [23] | Injection-site adverse events 5.0% versus 0.7% with placebo in the pooled ORION analysis [23]. | No dedicated proof that its modest Lp(a) reduction causes event reduction. |
| Niacine | Approximately −21% in the AIM-HIGH Lp(a) analysis [24] | Modest | HPS2-THRIVE: major vascular events 13.2% vs 13.7%, rate ratio 0.96 (95% CI 0.90–1.03), P = 0.29, with excess serious adverse events [25]. | No added benefit on contemporary therapy. Should not be prescribed solely to lower Lp(a). |
| Lipoprotein apheresis | Approximately −60% to −70% acutely; 68.1% mean single-treatment reduction in Pro(a)LiFe [26,27] | Large acute reduction per session, with rebound between sessions | Levels rebound between sessions, so the time-averaged reduction is smaller than the immediate post-procedure reduction. | Uncontrolled before-after cohorts report large event-rate reductions [26,27]; verwarrend, selection, and regression to the mean prevent causal claims. |
Table 3. Effects of currently available therapies on Lp(a) and on cardiovascular outcomes.
On statins specifically: the pooled participant-level meta-analysis confirms a modest average increase in Lp(a) [28]. Whether that increase independently affects outcomes is uncertain, and it is not a reason to stop indicated statin therapy, because the LDL and ApoB lowering statins achieve has established cardiovascular benefit.
13. Investigational Lp(a)-Targeted Therapies
A new class of agents lowers Lp(a) far more dramatically than any conventional lipid therapy. These trials establish pharmacodynamic proof, not clinical-outcome proof.
The key distinction is that lowering a laboratory value is not the same as proving fewer hartaanvallen of beroertes.
A biomarker reduction of 90% must not be translated into an assumed 90% reduction in events.
| Agent (class) | Trial and size | Lp(a) reduction | Safety findings |
| Pelacarsen (antisense oligonucleotide) | Phase 2, n = 286 [29] | Up to 80% mean reduction at the highest regimen | Injection-site reactions most common; no major platelet, liver, or renal imbalance in phase 2 |
| Olpasiran (siRNA) | OCEAN(a)-DOSE, n = 281 [30] | Placebo-adjusted −70.5%, −97.4%, −101.1%, and −100.5% by regimen at week 36 | Overall adverse events similar to placebo; injection-site reactions most common |
| Lepodisiran (siRNA) | ALPACA, n = 320 [31] | Pooled 400 mg: placebo-adjusted time-averaged −93.9% (95% CI −95.1 to −92.5), days 60–180 | 35 serious adverse events, none deemed treatment-related; generally mild injection-site reactions in up to 12% |
| Zerlasiran (siRNA) | ALPACAR-360, n = 178 [32] | Time-averaged −85.6%, −82.8%, and −81.3% by regimen (all >80%) | Mild injection-site pain in approximately 2.3–7.1%; 20 serious adverse events in 17 patients, none considered drug-related |
| Muvalaplin (oral small molecule) | KRAKEN, n = 233 [33] | Up to −85.8% using the intact-Lp(a) assay; approximately −70% by apo(a) assay | No major safety or tolerability concern reported over the trial period |
Table 4. Phase 2 biomarker results for Lp(a)-targeted agents.
Placebo-adjusted values slightly beyond 100% reflect the statistical adjustment calculation, not physically negative Lp(a) concentrations.
14. The Dedicated Outcomes Trials
These trials are the decisive tests of whether lowering Lp(a) prevents cardiovascular events. Lp(a)HORIZON’s registered primary endpoint is time to first expanded major adverse cardiovascular event in patients with established cardiovascular disease and Lp(a) ≥70 mg/dL, with a second primary analysis in those ≥90 mg/dL. Registry status is fast-moving content and must be re-verified immediately before publication.
| Trial (agent) | Registry ID | Status | Enrollment | Estimated primary completion |
| Lp(a)HORIZON (pelacarsen) | NCT04023552 | Active, not recruiting; no results posted; record last updated 6 May 2026 and last verified May 2026; sponsor Novartis | 8,323 (actual) | 30 June 2026 (estimated) |
| OCEAN(a)-Outcomes (olpasiran) | NCT05581303 | Active, not recruiting; no results posted; record updated 27 February 2026. Established ASCVD with Lp(a) ≥200 nmol/L; eligible ASCVD includes prior MI or PCI with stenting plus an additional risk factor; anticipated follow-up approximately four years | 7,297 (actual) | 31 March 2028 |
| ACCLAIM-Lp(a) (lepodisiran) | NCT06292013 | Active, not recruiting; no results posted; record updated 18 June 2026. Lp(a) ≥175 nmol/L; addendum adds approximately 1,700 participants | 17,300 (estimated) | March 2029 |
| MOVE-Lp(a) (muvalaplin) | NCT07157774 | Recruiting; no results posted; record updated 7 July 2026 | 10,450 (estimated); actual start 2 September 2025 | March 2031 |
Table 5. Dedicated Lp(a)-lowering cardiovascular-outcomes programs, per ClinicalTrials.gov as cited in the August 2026 audit.
A further pelacarsen study, ADD-VANTAGE (NCT06813911), is a recruiting phase 3 study of pelacarsen on a background of inclisiran in patients with elevated Lp(a) and established ASCVD. As checked on 28 August 2026, ClinicalTrials.gov listed the record as last updated 17 June 2026, with no results posted, estimated enrollment of 340, and estimated primary completion 3 February 2028. Its primary endpoint is change in Lp(a) rather than cardiovascular events, so it is a biomarker study and should not be grouped with the dedicated cardiovascular-outcomes trials in Table 5 [38].
As of 28 August 2026, the primary ClinicalTrials.gov records for the major dedicated Lp(a)-lowering cardiovascular-outcomes programs show no posted results. Selective pharmacologic Lp(a) lowering has therefore not yet been demonstrated in a dedicated randomized outcomes trial to reduce cardiovascular events.
Lp(a)HORIZON remains listed as active, not recruiting, despite a 30 June 2026 estimated primary-completion date; OCEAN(a)-Outcomes and ACCLAIM-Lp(a) remain active but not recruiting, and MOVE-Lp(a) is recruiting. A passed estimated date is not evidence that a trial should be described as completed or that any result exists.
15. How Much Would Lp(a) Need to Fall?
Two Mendelian-randomization analyses have estimated the lifelong genetically proxied Lp(a) difference associated with a CHD-risk difference comparable to that associated with 1 mmol/L (38.67 mg/dL) lower LDL-C. Burgess and colleagues estimated 101.5 mg/dL (95% CI 71.0–137.0), reporting an odds ratio of 0.942 per 10 mg/dL lower genetically predicted Lp(a) [39]. Lamina and Kronenberg estimated 65.7 mg/dL (95% CI 46.3–88.3) [40].
The estimates differ in important part because of differences in Lp(a) distributions, assay calibration, and analytical design across the underlying datasets. Both analyses used predominantly European-ancestry datasets and assay-dependent Lp(a) mass measurements.
Both imply that substantial absolute differences in lifelong Lp(a) exposure correspond to clinically meaningful differences in CHD risk. Neither establishes what reduction a drug must achieve over a finite treatment period, and neither should be presented as a validated pharmacologic target. Lifelong genetic exposure beginning at conception is not equivalent to years of drug therapy begun after tandplak has accumulated.
A separate observational modeling projection from the Copenhagen secondary-prevention cohort estimated that lowering Lp(a) by approximately 50 mg/dL (105 nmol/L) over five years might correspond to 20% lower MACE, and approximately 99 mg/dL (212 nmol/L) to 40% lower MACE [8]. These are modeled projections from observational data, not trial-proven treatment effects.
16. Who Should Be Tested
The 2026 ACC/AHA Multisociety Dyslipidemie Guideline recommends measuring Lp(a) at least once in adulthood, and the EAS consensus supports the same approach [2,1]. Measurement is particularly informative in premature ASCVD, a strong family history of premature cardiovascular disease, familial hypercholesterolemie, recurrent events despite well-controlled LDL-C, and calcific aortic stenosis.
Cascade Lp(a) testing of eerstegraads verwanten is reasonable when markedly elevated Lp(a) is identified. In ordinary practice this means measuring the Lp(a) concentration in relatives, not genotyping them.
Repeat measurement is generally unnecessary, because Lp(a) is predominantly genetically determined and generally stable over time. Repeat testing may nevertheless be appropriate when disease, pregnancy or menopause-related changes, medications, assay uncertainty, or Lp(a)-directed therapy could materially alter the measured concentration.
17. What This Means for You
Lp(a) is an inherited, cholesterol-containing lipoprotein particle that can substantially increase the risk of heart attack, stroke, and aortic-valve disease. At around 50 mg/dL, average relative ASCVD risk is roughly 40% higher than at the guideline’s reference median; at very high levels around 180 mg/dL, average relative risk may be about four times higher [2]. That does not mean a heart attack is inevitable.
Because lifestyle change does not lower Lp(a) appreciably [1,2], healthy behavior should not be judged by whether the Lp(a) number falls. Exercise, avoiding tobacco, maintaining healthy body composition, controlling blood pressure and diabetes, and following a heart-healthy dietary pattern act on the other components of absolute risk. Lowering LDL-C and ApoB is a central evidence-based strategy, because these are modifiable causal exposures that add to the inherited Lp(a)-associated risk.
LDL-C goals should be individualized by risk category rather than applied uniformly. The 2026 guideline recommends LDL-C below 55 mg/dL for very-high-risk ASCVD and below 70 mg/dL for ASCVD not meeting very-high-risk criteria. In primaire preventie met subklinische atherosclerose, progressively higher kransslagaderkalk (CAC) burden supports progressively more intensive LDL-C lowering: CAC of 100–299 or at or above the 75th percentile supports LDL-C below 70 mg/dL; CAC of 300–999 supports below 70 mg/dL with at least a 50% reduction, and intensification toward below 55 mg/dL is reasonable in selected patients; CAC of 1000 or above supports below 55 mg/dL with at least a 50% reduction [2].
CAC scoring can be useful selectively — in selected primary-prevention adults for whom the treatment decision remains uncertain after conventional risk assessment and consideration of risk enhancers such as elevated Lp(a). Elevated Lp(a) by itself does not create a universal indication for a calcium scan [2].
Where CAC is obtained, it strongly modifies absolute risk in people with elevated Lp(a). In MESA, elevated Lp(a) with a CAC score of zero was not significantly associated with higher ASCVD risk than low Lp(a) with CAC of zero (hazard ratio 1.31, 95% CI 0.73–2.35), whereas elevated Lp(a) together with CAC of 100 or above identified markedly higher risk (hazard ratio 4.71, 95% CI 3.01–7.40) [41]. A 2026 multicohort study of 11,319 participants followed for a mean of 14.8 years found that elevated Lp(a) above 50 mg/dL was associated with higher ASCVD risk even among people with a CAC score of zero (hazard ratio 1.28, 95% CI 1.01–1.60), although absolute event rates in that group remained low at 4.9 versus 3.8 per 1,000 person-years [42]. A CAC score of zero should therefore be read as low observed absolute plaque-related risk over the period studied, not as evidence that lifelong Lp(a)-associated risk has disappeared. CAC measures disease already present; Lp(a) measures a lifelong causal exposure [1,2].
Until dedicated outcome trials of Lp(a)-specific drugs report, the most evidence-based strategy is intensive, guideline-directed management of every modifiable cardiovascular risk factor, particularly LDL-C and ApoB.
18. Evidence Hierarchy
- Strong evidence: Lp(a) is a causal, continuously graded risk factor for ASCVD, supported by prospectieve cohorten, LPA genetics, Mendelian randomisatie, and dose–response. Lp(a) makes a causal contribution to calcific aortic-valve disease.
- Moderate-to-strong evidence: elevated Lp(a) remains associated with residual ASCVD risk in statin-treated and aggressively LDL-lowered populations. Conventional ApoB does not fully capture Lp(a)-associated risk. Elevated Lp(a) predicts recurrent events in established ASCVD.
- Moderate evidence: the genetically estimated per-particle atherogenicity of Lp(a) relative to LDL. Post-hoc PCSK9-inhibitor analyses suggesting greater absolute benefit at higher baseline Lp(a).
- Emerging evidence: whether pharmacologic Lp(a) lowering reduces cardiovascular events. Biomarker efficacy of the investigational agents is established; cardiovascular-outcome efficacy remains unproven in the audited primary data.
So, How Much Worse Does Lp(a) Make Heart Disease?
- Elevated Lp(a) is common: approximately one in five people has a concentration at or above commonly used high-risk thresholds of roughly 50 mg/dL or 125 nmol/L.
- Risk rises continuously rather than switching on at a threshold. The 2026 guideline estimates approximately 1.2-fold ASCVD risk at 30–49 mg/dL, 1.4-fold at 50 mg/dL, 2-fold at 100 mg/dL, 3-fold at 150 mg/dL, and 4-fold at 180 mg/dL, compared with a population median of about 7 mg/dL (20 nmol/L). These are UK Biobank-derived general-guide estimates.
- Extreme concentrations have been associated with roughly threefold to fourfold higher MI risk in some cohorts — in Copenhagen, at 120 mg/dL or above versus under 5 mg/dL, with an MI-specific endpoint. That is a different question from the guideline’s broad-ASCVD estimate at 100 mg/dL.
- In people who already have cardiovascular disease, higher Lp(a) predicts more recurrent events, with adjusted incidence-rate ratios rising to 2.14 at 100 mg/dL or above versus under 10 mg/dL.
- Low LDL-C does not eliminate the risk. Lp(a)-associated risk persisted in the lowest achieved-LDL-C quartile of pooled statin trials, and it is incompletely represented by conventional ApoB measurement — even though each Lp(a) particle itself contributes one ApoB-100 molecule.
- Very high Lp(a) is associated with roughly threefold higher incident aortic-stenosis risk in Copenhagen data, and genetic evidence supports a causal contribution to calcific aortic-valve disease.
- What patients can do now: measure Lp(a) once; if elevated, intensify guideline-directed control of every modifiable risk factor, with LDL-C goals set by risk category; consider CAC selectively when a primary-prevention treatment decision remains uncertain; and arrange cascade testing of first-degree relatives.
- What remains unknown: whether profoundly lowering Lp(a) prevents cardiovascular events. As of 28 August 2026, no dedicated phase 3 Lp(a)-lowering outcomes result had been posted. Lp(a)HORIZON, OCEAN(a)-Outcomes, ACCLAIM-Lp(a), and MOVE-Lp(a) are designed to answer that question, with estimated primary completions from 2026 through 2031.
Referenties
- Kronenberg F, Mora S, Stroes ESG, et al. Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: a European Atherosclerosis Society consensus statement. Eur Heart J. 2022;43(39):3925–3946. DOI: 10.1093/eurheartj/ehac361. PMID: 36036785.
- 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia. Circulation. 2026. DOI: 10.1161/CIR.0000000000001423. PMID: 41824590.
- Erqou S, Kaptoge S, Perry PL, et al; Emerging Risk Factors Collaboration. Lipoprotein(a) concentration and the risk of coronary heart disease, stroke, and nonvascular mortality. JAMA. 2009;302(4):412–423. DOI: 10.1001/jama.2009.1063. PMID: 19622820.
- Kamstrup PR, Tybjærg-Hansen A, Steffensen R, Nordestgaard BG. Genetically elevated lipoprotein(a) and increased risk of myocardial infarction. JAMA. 2009;301(22):2331–2339. DOI: 10.1001/jama.2009.801. PMID: 19509380.
- Clarke R, Peden JF, Hopewell JC, et al; PROCARDIS Consortium. Genetic variants associated with Lp(a) lipoprotein level and coronary disease. N Engl J Med. 2009;361(26):2518–2528. DOI: 10.1056/NEJMoa0902604. PMID: 20032323.
- Patel AP, Wang M, Pirruccello JP, et al. Lp(a) concentrations and incident atherosclerotic cardiovascular disease: new insights from a large national biobank. Arterioscler Thromb Vasc Biol. 2021;41(1):465–474. DOI: 10.1161/ATVBAHA.120.315291. PMID: 33115266.
- Kamstrup PR, Benn M, Tybjærg-Hansen A, Nordestgaard BG. Extreme lipoprotein(a) levels and risk of myocardial infarction in the general population: the Copenhagen City Heart Study. Circulation. 2008;117(2):176–184. DOI: 10.1161/CIRCULATIONAHA.107.715698. PMID: 18086931.
- Madsen CM, Kamstrup PR, Langsted A, Varbo A, Nordestgaard BG. Lipoprotein(a)-lowering by 50 mg/dL (105 nmol/L) may be needed to reduce cardiovascular disease 20% in secondary prevention. Arterioscler Thromb Vasc Biol. 2020;40(1):255–266. DOI: 10.1161/ATVBAHA.119.312951. PMID: 31578080.
- O’Donoghue ML, Fazio S, Giugliano RP, et al. Lipoprotein(a), PCSK9 inhibition, and cardiovascular risk: insights from the FOURIER trial. Circulation. 2019;139(12):1483–1492. DOI: 10.1161/CIRCULATIONAHA.118.037184. PMID: 30586750.
- Bittner VA, Szarek M, Aylward PE, et al; ODYSSEY OUTCOMES Committees and Investigators. Effect of alirocumab on lipoprotein(a) and cardiovascular risk after acute coronary syndrome. J Am Coll Cardiol. 2020;75(2):133–144. DOI: 10.1016/j.jacc.2019.10.057. PMID: 31948641.
- Szarek M, Bittner VA, Aylward P, et al; ODYSSEY OUTCOMES Investigators. Lipoprotein(a) lowering by alirocumab reduces the total burden of cardiovascular events independent of low-density lipoprotein cholesterol lowering. Eur Heart J. 2020;41(44):4245–4255. DOI: 10.1093/eurheartj/ehaa649. PMID: 33051646.
- Bhatia HS, Wandel S, Willeit P, et al. Independence of lipoprotein(a) and LDL cholesterol-mediated cardiovascular risk: a participant-level meta-analysis. Circulation. 2025;151(4):312–321. DOI: 10.1161/CIRCULATIONAHA.124.069556. PMID: 39492722.
- Thomas PE, Vedel-Krogh S, Kamstrup PR, Nordestgaard BG. Lipoprotein(a) cardiovascular risk explained by LDL cholesterol, non-HDL cholesterol, apoB, or hsCRP is minimal. J Am Coll Cardiol. 2025;85(21):2046–2051. DOI: 10.1016/j.jacc.2025.02.024. PMID: 40266171.
- Björnson E, Adiels M, Taskinen MR, et al. Lipoprotein(a) is markedly more atherogenic than LDL: an apolipoprotein B-based genetic analysis. J Am Coll Cardiol. 2024;83(3):385–395. DOI: 10.1016/j.jacc.2023.10.039. PMID: 38233012.
- Kamstrup PR, Tybjærg-Hansen A, Nordestgaard BG. Elevated lipoprotein(a) and risk of aortic valve stenosis in the general population. J Am Coll Cardiol. 2014;63(5):470–477. DOI: 10.1016/j.jacc.2013.09.038. PMID: 24161338.
- Kaltoft M, Langsted A, Nordestgaard BG. Elevated lipoprotein(a) in mitral and aortic valve calcification and disease: the Copenhagen General Population Study. Atherosclerosis. 2022;349:166–174. DOI: 10.1016/j.atherosclerosis.2021.11.029. PMID: 34903381.
- Zheng KH, Tsimikas S, Pawade T, et al. Lipoprotein(a) and oxidized phospholipids promote valve calcification in patients with aortic stenosis. J Am Coll Cardiol. 2019;73(17):2150–2162. DOI: 10.1016/j.jacc.2019.01.070. PMID: 31047003.
- Thomas PE, Vedel-Krogh S, Kamstrup PR, Nordestgaard BG. Lipoprotein(a) is linked to atherothrombosis and aortic valve stenosis independent of C-reactive protein. Eur Heart J. 2023;44(16):1449–1460. DOI: 10.1093/eurheartj/ehad055. PMID: 36805188.
- Awad K, Mikhailidis DP, Katsiki N, Muntner P, Banach M; Lipid and Blood Pressure Meta-Analysis Collaboration (LBPMC) Group. Effect of ezetimibe monotherapy on plasma lipoprotein(a) concentrations in patients with primary hypercholesterolemia: a systematic review and meta-analysis of randomized controlled trials. Drugs. 2018;78(4):453–462. DOI: 10.1007/s40265-018-0870-1. PMID: 29396832.
- Sahebkar A, Simental-Mendía LE, Pirro M, Banach M, Watts GF, Sirtori C, Al-Rasadi K, Atkin SL. Impact of ezetimibe on plasma lipoprotein(a) concentrations as monotherapy or in combination with statins: a systematic review and meta-analysis of randomized controlled trials. Sci Rep. 2018;8(1):17887. DOI: 10.1038/s41598-018-36204-7. PMID: 30552391.
- Rivera FB, Cha SW, Louisse CL, et al. Impact of proprotein convertase subtilisin/kexin type 9 inhibitors on lipoprotein(a): a meta-analysis and meta-regression of randomized controlled trials. JACC Adv. 2025;4(2):101549. DOI: 10.1016/j.jacadv.2024.101549. PMID: 39877671.
- Ray KK, Wright RS, Kallend D, et al; ORION-10 and ORION-11 Investigators. Two phase 3 trials of inclisiran in patients with elevated LDL cholesterol. N Engl J Med. 2020;382(16):1507–1519. DOI: 10.1056/NEJMoa1912387. PMID: 32187462.
- Wright RS, Ray KK, Raal FJ, et al. Pooled patient-level analysis of inclisiran trials in patients with familial hypercholesterolemia or atherosclerosis. J Am Coll Cardiol. 2021;77(9):1182–1193. DOI: 10.1016/j.jacc.2020.12.058. PMID: 33663735.
- Albers JJ, Slee A, O’Brien KD, et al. Relationship of apolipoproteins A-1 and B, and lipoprotein(a) to cardiovascular outcomes: the AIM-HIGH trial. J Am Coll Cardiol. 2013;62(17):1575–1579. DOI: 10.1016/j.jacc.2013.06.051. PMID: 23973688.
- HPS2-THRIVE Collaborative Group. Effects of extended-release niacin with laropiprant in high-risk patients. N Engl J Med. 2014;371(3):203–212. DOI: 10.1056/NEJMoa1300955. PMID: 25014686.
- Leebmann J, Roeseler E, Julius U, et al. Lipoprotein apheresis in patients with maximally tolerated lipid-lowering therapy, lipoprotein(a)-hyperlipoproteinemia, and progressive cardiovascular disease. Circulation. 2013;128(24):2567–2576. DOI: 10.1161/CIRCULATIONAHA.113.002432. PMID: 24056686.
- Roeseler E, Julius U, Heigl F, et al; Pro(a)LiFe-Study Group. Lipoprotein apheresis for lipoprotein(a)-associated cardiovascular disease: prospective 5-year results. Arterioscler Thromb Vasc Biol. 2016;36(9):2019–2027. DOI: 10.1161/ATVBAHA.116.307983. PMID: 27417585.
- Tsimikas S, Gordts PLSM, Nora C, Yeang C, Witztum JL. Statin therapy increases lipoprotein(a) levels. Eur Heart J. 2020;41(24):2275–2284. DOI: 10.1093/eurheartj/ehz310. PMID: 31111151.
- Tsimikas S, Karwatowska-Prokopczuk E, Gouni-Berthold I, et al. Lipoprotein(a) reduction in persons with cardiovascular disease. N Engl J Med. 2020;382(3):244–255. DOI: 10.1056/NEJMoa1905239. PMID: 31893580.
- O’Donoghue ML, Rosenson RS, Gencer B, et al. Small interfering RNA to reduce lipoprotein(a) in cardiovascular disease. N Engl J Med. 2022;387(20):1855–1864. DOI: 10.1056/NEJMoa2211023. PMID: 36342163.
- Nissen SE, Ni W, Shen X, et al; ALPACA Trial Investigators. Lepodisiran — a long-duration small interfering RNA targeting lipoprotein(a). N Engl J Med. 2025;392(17):1673–1683. DOI: 10.1056/NEJMoa2415818. PMID: 40162643.
- Nissen SE, Wang Q, Nicholls SJ, et al. Zerlasiran — a small-interfering RNA targeting lipoprotein(a): a phase 2 randomized clinical trial (ALPACAR-360). JAMA. 2024;332(23):1992–2002. DOI: 10.1001/jama.2024.21957. PMID: 39556769.
- Nicholls SJ, Ni W, Rhodes GM, et al. Oral muvalaplin for lowering of lipoprotein(a): a randomized clinical trial (KRAKEN). JAMA. 2025;333(3):222–231. DOI: 10.1001/jama.2024.24017. PMID: 39556768.
- Lp(a)HORIZON (pelacarsen). ClinicalTrials.gov identifier NCT04023552. https://clinicaltrials.gov/study/NCT04023552
- OCEAN(a)-Outcomes (olpasiran). ClinicalTrials.gov identifier NCT05581303. https://clinicaltrials.gov/study/NCT05581303
- ACCLAIM-Lp(a) (lepodisiran). ClinicalTrials.gov identifier NCT06292013. https://clinicaltrials.gov/study/NCT06292013
- MOVE-Lp(a) (muvalaplin). ClinicalTrials.gov identifier NCT07157774. https://clinicaltrials.gov/study/NCT07157774
- ADD-VANTAGE (pelacarsen on a background of inclisiran). ClinicalTrials.gov identifier NCT06813911. https://clinicaltrials.gov/study/NCT06813911
- Burgess S, Ference BA, Staley JR, et al. Association of LPA variants with risk of coronary disease and the implications for lipoprotein(a)-lowering therapies: a Mendelian randomization analysis. JAMA Cardiol. 2018;3(7):619–627. DOI: 10.1001/jamacardio.2018.1470. PMID: 29926099.
- Lamina C, Kronenberg F; Lp(a)-GWAS-Consortium. Estimation of the required lipoprotein(a)-lowering therapeutic effect size for reduction in coronary heart disease outcomes: a Mendelian randomization analysis. JAMA Cardiol. 2019;4(6):575–579. DOI: 10.1001/jamacardio.2019.1041. PMID: 31017618.
- Mehta A, Vasquez N, Ayers CR, Patel J, et al. Independent association of lipoprotein(a) and coronary artery calcification with atherosclerotic cardiovascular risk. J Am Coll Cardiol. 2022;79(8):757–768. DOI: 10.1016/j.jacc.2021.11.058. PMID: 35210030.
- Bhatia HS, Fan Y, Dharmavaram G, Zou H, et al. Use of coronary artery calcium scoring in individuals with elevated lipoprotein(a): a multicohort study. J Am Coll Cardiol. 2026;87(20):2864–2872. DOI: 10.1016/j.jacc.2026.02.5067. PMID: 41837904. PMCID: PMC13221166.

