I. Executive Summary: The Necessity of Training Modification
The management of Atrial FibrillationAtrial fibrillation, often shortened to AFib, is a fast and irregular heartbeat that starts in the upper chambers of the heart. (Afib) in the Masters athleteA masters athlete is a competitor over about 35 who trains and races seriously, often for decades. (defined generally as age 35 and above, and specifically in this context as 50+) presents a critical challenge that necessitates a nuanced shift in training philosophy. While chronic endurance training offers broad cardiovascular benefits, it is fundamentally a dose-dependent risk factorA risk factor is something that raises your chance of developing a disease — high cholesterol particles, high blood pressure, smoking, diabetes, family history. for atrial arrhythmias. For an athlete who has undergone treatment (ablation or pharmacological therapy) for Afib, continuing intense, high-volume training carries a substantial probability of arrhythmia recurrence and disease progression.
The primary conclusion supported by electrophysiology research is that the Masters athlete (50+) diagnosed and treated for Afib should immediately and significantly moderate the volume and intensity of endurance training. This reduction is required not merely for symptomatic relief but as a therapeutic strategy to stabilize the atrial substrate and reduce long-term morbidity. The goal should be to maintain high cardiovascular fitness through structured, moderate-to-vigorous activity, while actively mitigating the structural and electrical strain associated with peak endurance performance.
Key Pillars for Clinical Management:
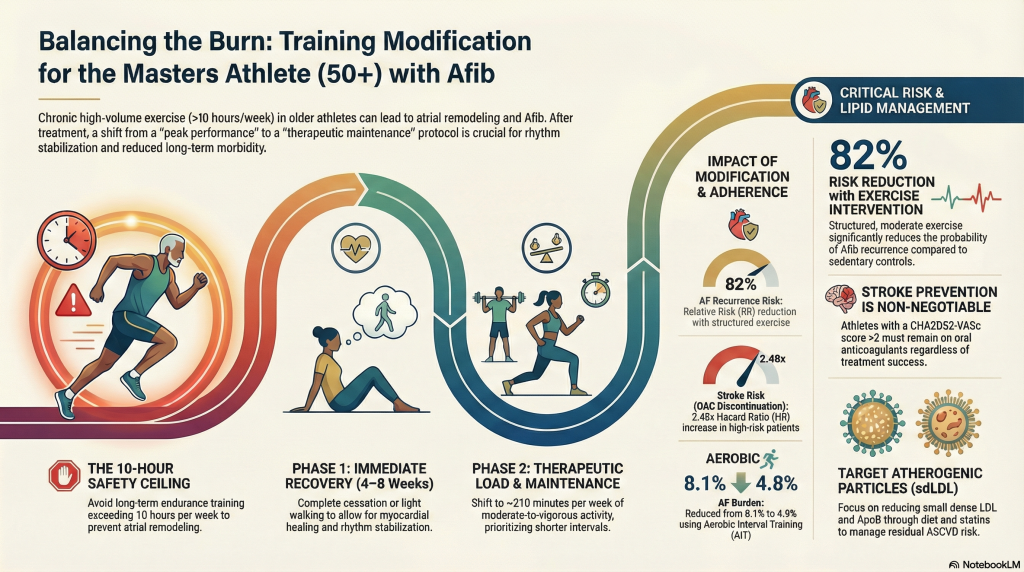
- Training Dose Adjustment: Shift training volume away from chronic, high-intensity endurance training (typically defined as >10 hours per week over many years 1).
- Rhythm Stability and Recurrence Risk: Implement therapeutic exercise protocols, such as Aerobic Interval Training (AIT)A structured exercise method alternating short bouts of high-intensity effort with active recovery periods — for example, four minutes at near-maximal exertion followed by three minutes easy — shown in clinical studies to reduce AF burden and improve VO₂ max more effectively than continuous steady-state training., which have been shown to actively reduce Afib burden.2
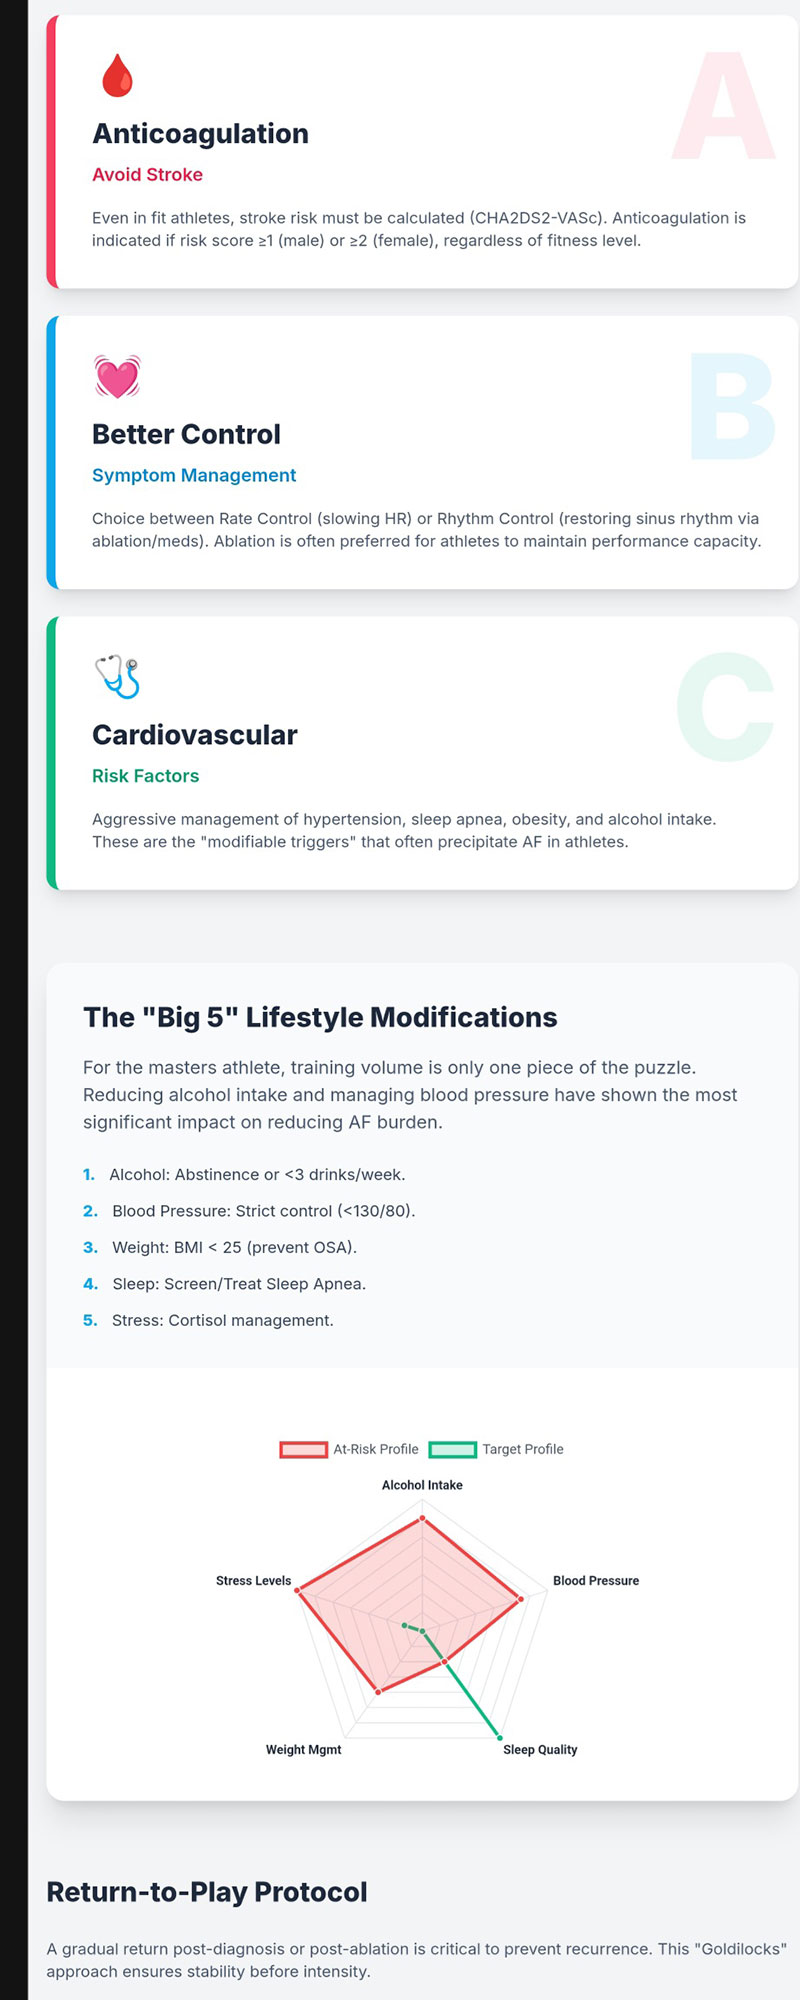
- StrokeA stroke happens when blood flow to part of the brain stops, either from a blockage or from bleeding. Prevention: AdherenceAdherence means actually taking your medicine the way it was prescribed, day after day. to Oral Anticoagulation (OAC)Drug therapy that reduces the blood's ability to clot, used in atrial fibrillation to prevent stroke caused by clots forming in the atria; common agents include warfarin and the newer direct oral anticoagulants (DOACs). guidelines based on individual risk scores (e.g., CHA2DS2-VASc) is critical and often outweighs athletic goals, as successful ablation does not universally guarantee safety from stroke.4
II. Pathophysiology and Statistical Probability of Afib Recurrence
A. The Causal Mechanism: Endurance Training and Atrial Remodeling
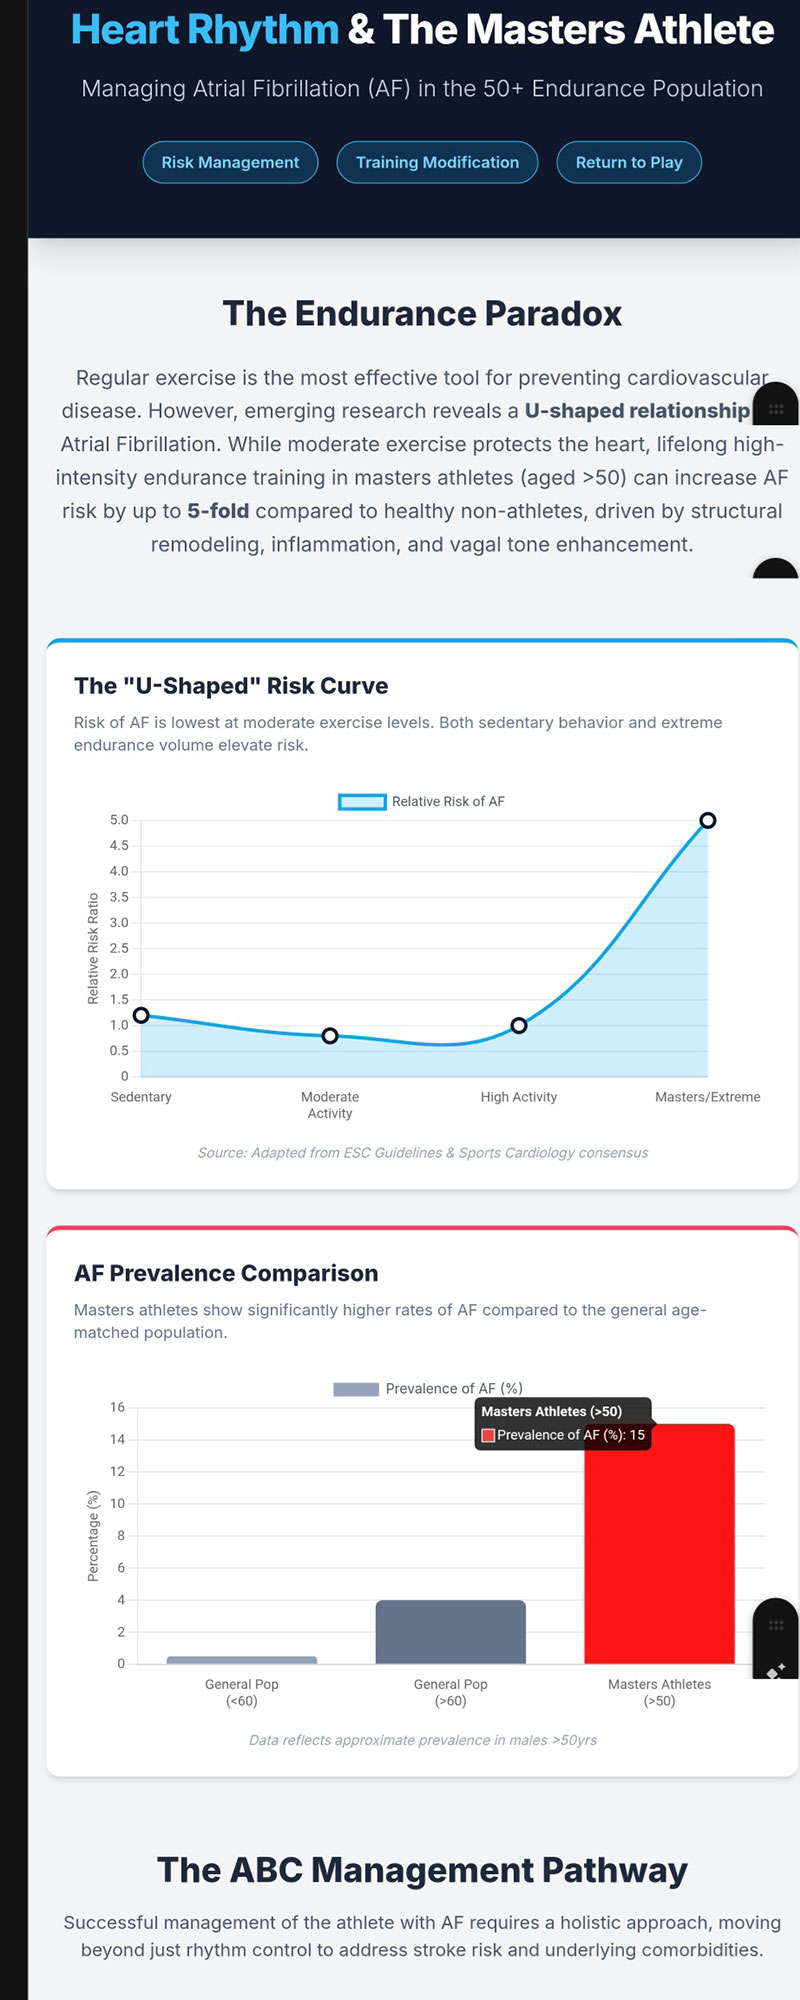
The risk of Afib in Masters athletesCompetitive or highly trained endurance athletes typically defined as individuals over the age of 35 who have engaged in years of high-intensity or high-volume training; they are the primary population studied in the athlete paradox research because their long exercise histories can paradoxically be associated with elevated coronary calcium scores. is inextricably linked to the physiological adaptations induced by sustained, high-volume training, often summarized by the J- or U-shaped curve model of exercise dose and cardiovascular risk.5
Cardiac Structural and Electrical Substrate
Chronic volume loading inherent to endurance sports (such as cycling, running, or swimming) results in specific cardiac remodeling, leading to the “athlete’s heart”.7 While much attention is paid to ventricular changes, it is the atrial remodelingStructural and electrical changes in the atria — including enlargement, wall thickening, fibrosis, and altered ion-channel expression — that develop in response to chronic pressure or volume overload; in endurance athletes, sustained high cardiac output drives this process and increases AF susceptibility. that predisposes the athlete to Afib. This remodeling includes:
- Biatrial DilationEnlargement of both the left and right atria, a structural change driven in endurance athletes by years of high cardiac output and sustained volume loading; it creates a stretched, electrically unstable tissue environment that predisposes to atrial fibrillation.: Enlargement of both the left and right atria.7
- Myocardial Fibrosis: The development of microscopic scarring (fibrosis) within the atrial walls.8
This fibrosis is particularly dangerous because it creates an electrically heterogeneous tissue environment, providing a substrate highly conducive to the formation of macro-reentry electrical circuits. These circuits sustain the disorganized electrical activity characteristic of Afib.8
Autonomic Imbalances as Triggers
In addition to structural changes, endurance athletes experience profound fluctuations in their autonomic nervous system. They typically exhibit exaggerated vagal toneThe level of activity of the parasympathetic (vagus nerve) branch of the autonomic nervous system acting on the heart; high vagal tone slows the resting heart rate and is generally cardioprotective, but in extreme endurance athletes it has been proposed to contribute to atrial fibrillation risk. at rest, leading to sinus bradycardia. However, intense or competitive exercise induces a powerful sympathetic surge. This swing in autonomic activity significantly shortens the atrial refractory periodThe brief interval after each electrical activation during which atrial muscle cells cannot respond to a new stimulus; when this period is shortened — as occurs during sympathetic surges or with vagal tone — the atria become more vulnerable to rapid, disorganized firing and AF onset., acting as a potent ectopic trigger that can initiate Afib episodes.8 In the Masters athlete (50+), the combination of exercise-induced remodeling and age-related risk factors (such as hypertensionHypertension is the medical term for high blood pressure. or obesityObesity means carrying enough excess body fat to affect health., even if well-controlled) compounds this electrophysiological vulnerability.1
B. Statistical Data on Recurrence Probability Post-Treatment
The probability of remaining free from atrial arrhythmia after treatment is notably challenged by the continuation of the underlying etiological stimulus (intense training).
Recurrence Post-Catheter Ablation (PVI)
For athletes undergoing catheter ablationA procedure in which a cardiologist threads a thin flexible tube (catheter) into the heart and uses energy — typically radiofrequency heat or cryotherapy — to destroy small areas of tissue responsible for triggering abnormal electrical signals; the main interventional treatment for AF., specifically Pulmonary Vein IsolationThe most common catheter ablation technique for AF, in which the four pulmonary veins — the usual sources of the triggering electrical impulses — are electrically disconnected from the rest of the left atrium. (PVI), the recurrence rates are often problematic. Observational data suggest that endurance athletes tend to experience higher rates of atrial arrhythmia recurrence than sedentary non-athletes after the procedure.10 Crucially, this recurrence often manifests not as the original Afib, but as atypical flutterA form of atrial flutter whose reentrant circuit does not follow the classic right-atrial pathway but instead arises from fibrotic or scarred tissue elsewhere in the atria; in athletes post-ablation, it often signals disease progression beyond the originally isolated pulmonary vein triggers..10 This phenomenon suggests that the disease process has progressed, with the original pulmonary vein triggers successfully isolated, but the underlying fibrotic substrate driving new arrhythmias elsewhere in the atrial tissue (non-pulmonary vein dependent).10
One study comparing PVI outcomes reported that athletes experienced similar arrhythmia-free survival at 3 years compared to non-endurance controls (87% vs. 85%, p=0.88).9 However, another comparison showed recurrence rates (freedom from AF and antiarrhythmic therapy) were 34% in athletes versus 48% in controls after 3 years.9 The implication of this variation is that while PVI may be effective initially for vagally-mediated Afib common in athletes, the long-term maintenance of intense training will relentlessly drive further remodeling and increase the probability of eventual recurrence or progression to more complex arrhythmias like atrial flutter.10
Quantitative Benefit of Training Modification
A structured reduction and modification of exercise volume are strongly supported by outcome data, translating to a favorable reduction in recurrence probability.
- Relative RiskRelative risk compares two groups: this group had 30 percent fewer heart attacks than that group. Reduction: Structured exercise intervention has been associated with an overall reduced risk of AF recurrenceThe return of atrial fibrillation after a period of successful rhythm control, whether achieved by ablation or medication; in endurance athletes, recurrence rates after a single ablation are approximately 40%, and persistent atrial enlargement and fibrosis are the main predictors. compared to control groups, quantified by a Relative Risk (RR) of 82 (95% CI: 0.68 to 0.99, p=0.04).3 This reduction suggests that thoughtful exercise prescription, focused on health maintenance rather than maximum performance, can be genuinely therapeutic.
- Reduction in Afib Burden: Specifically, structured Aerobic Interval Training (AIT) was found to reduce the mean time an athlete spent in Afib from 1% to 8.1% compared to a control group, alongside improvements in cardiopulmonary fitness (V02max).2
C. The Unacceptable Risk of Stroke
The decision to continue intense training must be weighed against the persistent risk of stroke, particularly because the athlete is over 50 years of age. Age 50+ likely results in a CHA2DS2-VASc scoreA clinical scoring tool used to estimate stroke risk in patients with atrial fibrillation, assigning points for risk factors such as age, sex, hypertension, diabetes, heart failure, prior stroke, and vascular disease; a score of 2 or higher typically triggers a recommendation for oral anticoagulation. of at least 1 (for age), possibly 2 or higher if other risk factors like hypertension or diabetesDiabetes is a condition where blood sugar stays too high, either because the body makes too little insulin or because it stops responding to the insulin it makes. are present.4
Stroke prevention guidelines dictate the use of Oral Anticoagulation (OAC) based on the CHA2DS2-VASc score, regardless of the perceived success of Afib treatment.
- OAC Discontinuation Risk: Observational studies indicate that for patients with a CHA2DS2-VASc score > 2, discontinuing OAC >3 months after catheter ablation led to a substantially increased stroke risk, quantified by a Hazard RatioA hazard ratio compares how quickly events happen in two groups. A ratio of 0.75 means events occurred at three-quarters the rate in the treated group. (HR) of 2.48 (95% CI, 1.11–5.52; P<0.05).4
- Ablation Limitations: Randomized clinical trialsA clinical trial is a study where researchers give one group a treatment and another group a placebo or standard care, then compare what happens. have, to date, not demonstrated reductions in stroke risk after catheter ablation.4
This data underscores the fact that ablation treats the arrhythmia symptom, but may not fully resolve the underlying pathology that drives thromboembolic risk. Therefore, the probability of stroke is overwhelmingly dependent on the CHA2DS2-VASc score, not on the ability to return to intense training. If OAC is required, the athlete must be counseled that contact or high-trauma sports are contraindicated due to bleeding risk.11
III. Suggested Course of Action: Detailed Training and Clinical Protocols
The course of action for the Masters athlete (50+) with treated Afib should focus on risk mitigation and structured exercise for cardiac resilience.
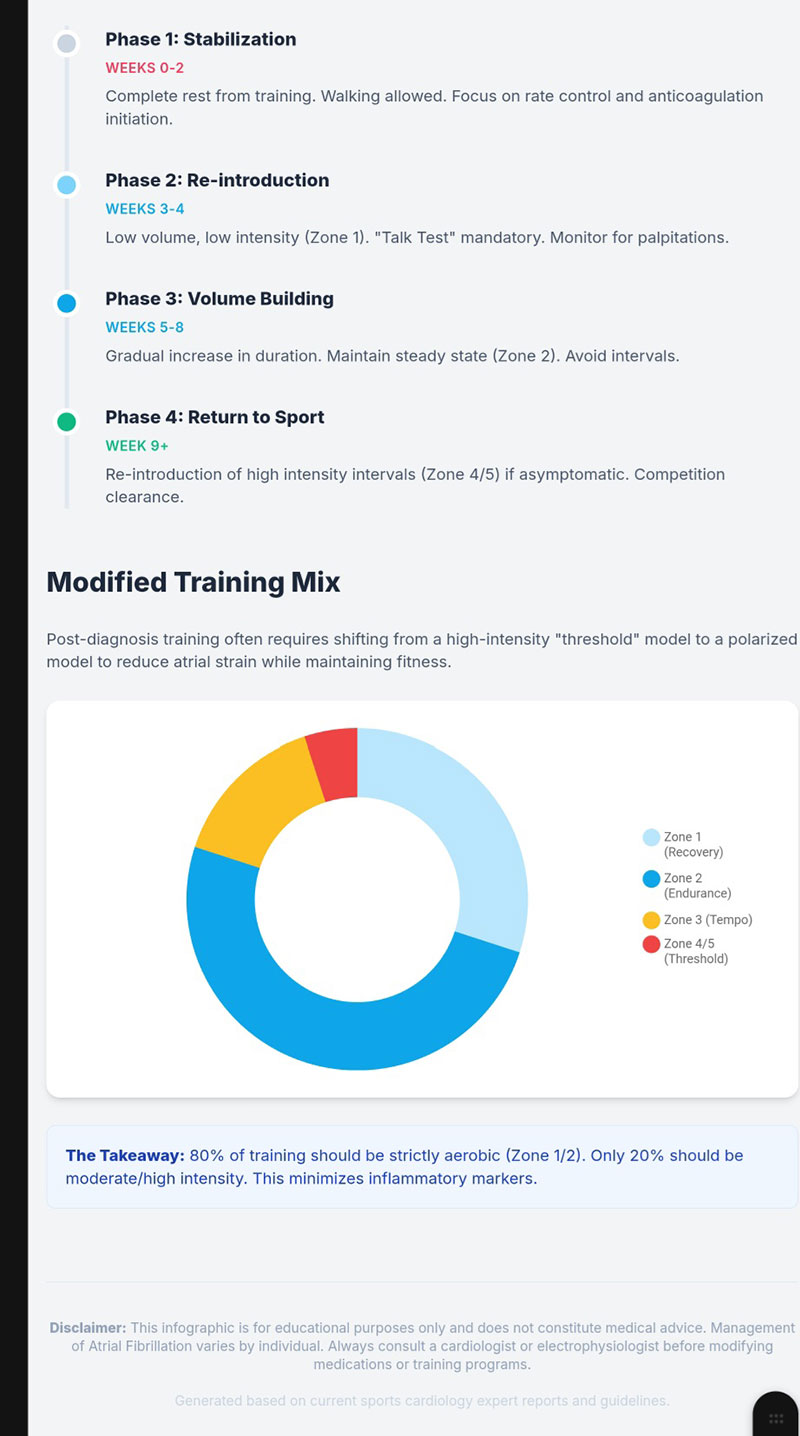
A. Phased Training Modification Protocol
The transition from a high-volume endurance regimen to a therapeutic regimen requires structured phasing and communication, especially regarding the established link between high-intensity training and Afib burden.5
| Phase | Duration | Activity/Goal | Clinical Rationale and Guidance |
| Phase 1: Immediate Post-Treatment Recovery | Initial 4–8 Weeks | Complete cessation or very light, non-competitive activity (e.g., walking). | Allows for myocardial healing and stabilization of sinus rhythm following ablation or cardioversion.12 Resumption of structured sports activity should begin only one month after ablation, provided the procedure is verified as successful.11 |
| Phase 2: Therapeutic Load & Maintenance | Ongoing (Long-Term) | Moderate-to-Vigorous Structured Aerobic ExerciseAerobic exercise is steady activity that gets you breathing harder for a while, like walking fast, cycling, swimming, or jogging., prioritizing shorter, higher-intensity intervals (AIT) over long, continuous duration. | The primary long-term objective is to maintain cardiorespiratory fitnessCardiorespiratory fitness is how well your heart, lungs, and muscles work together to use oxygen during hard exercise. It is often measured as VO2 max. (improved V02max) and cardiac function (improved Left Ventricular Ejection FractionThe percentage of blood pumped out of the heart's main pumping chamber with each beat; a normal value is 55 percent or above, and a rising ejection fraction after heart disease is a measurable sign of cardiac recovery., LVEF 3), while avoiding the chronic volume strain that induced the Afib.13 The suggested target is approximately 210 minutes per week of moderate-to-vigorous aerobic exercise.4 |
The importance of using Aerobic Interval Training (AIT) in Phase 2 cannot be overstated, as subgroup analysis suggests interval training offers greater benefit in reducing AF recurrence compared to continuous training.3 A generalized return to long, slow distance training (>10 hours/week) should be actively discouraged, as this risks re-inducing the remodeling that caused the original arrhythmia.1
B. Clinical Management Considerations
- Antiarrhythmic Medication and Performance: Athletes are often intolerant of or unwilling to take medications like Beta-blockers, as these drugs profoundly reduce peak exercise capacityExercise capacity is a quantitative measure of the maximum physical work a person can perform, typically assessed during a graded stress test as peak workload in watts, peak oxygen consumption (VO2 max), or metabolic equivalents (METs). In the article, a decline in exercise capacity four months after stenting indicated that the procedure alone had not resolved the underlying disease., measured by V02max.14 Catheter ablation is frequently preferred because it offers the possibility of eradicating Afib and allowing a return to competition without daily performance-limiting drug therapy.14 If “pill-in-the-pocket” Class I drugs (flecainide or propafenone) are used for acute cardioversion, the athlete must refrain from intensive sports until two half-lives of the drug have elapsed (up to 2 days) due to the risk of pro-arrhythmic effects during adrenergic stress.11
- Monitoring and Evaluation: All athletes must be managed in a specialized sports cardiology center.1 Exercise stress testing should be conducted using protocols that mimic the athlete’s sport to ensure the ventricular rate remains controlled during maximal exertion, confirming therapeutic efficacy.1
- Anticoagulation Status: OAC status must be re-evaluated continuously. In high-risk athletes (CHA2DS2-VASc >2), OAC must be continued indefinitely, even if Afib appears suppressed.4 This clinical requirement guides participation in sports; sports with high risk of bodily contact or trauma are strictly not recommended for anticoagulated individuals.11
IV. Summary and Integration of Lipid Management (Stoicescu et al., 2025)
The holistic management of a Masters athlete (50+) requires addressing not only the electrophysiological disorder (Afib) but also the generalized cardiovascular risk, including lipid metabolism. The provided review paper, “HDLHDL, or high-density lipoprotein, is the particle often called "good cholesterol." It picks up cholesterol from tissues and carries it back to the liver. Function Versus Small Dense LDLSmall dense LDL particles are LDL particles that are smaller and carrying less cholesterol than usual.: Cardiovascular Benefits and Implications” 15, provides essential context for managing atherosclerotic risk (ASCVD) in this population.
A. Paper Summary: HDL Function Versus Small Dense LDL
The review by Stoicescu, Vacarescu, and Cozma highlights a significant paradigm shift in lipidology: the focus has moved away from High-Density LipoproteinA lipoprotein is a tiny package that carries fat and cholesterol through your bloodstream. Since fat won't dissolve in water, it needs a protein wrapper to travel. CholesterolCholesterol is a waxy substance your body needs. It goes into cell walls, hormones, vitamin D, and the bile that digests your food. You would die without it. (HDL-C) concentration toward functional capacity and aggressive reduction of atherogenic particlesAtherogenic particles are the ApoB-containing lipoproteins—including LDL, IDL, VLDL, and lipoprotein(a)—that can enter and be retained in the artery wall to initiate and sustain plaque growth; the article uses the term to describe what must be lowered substantially and sustainably to achieve plaque regression..17
- HDL Focus: Function over Quantity: While HDL traditionally was considered cardioprotective, pharmacologically increasing HDL-C concentration—via agents like NiacinNiacin is vitamin B3, which at very high doses lowers LDL and raises HDL. (AIM-HIGH, HPS2-THRIVE trialsA large randomized trial testing whether adding extended-release niacin plus laropiprant to background statin therapy reduced major vascular events in high-risk patients; it found no meaningful cardiovascular benefit and identified increased rates of serious adverse events, effectively ending niacin as a mainstream cardiovascular therapy.) or CETP inhibitorsA class of drugs designed to block cholesterol ester transfer protein, an enzyme that shuttles cholesterol from HDL to LDL particles; clinical trials such as ILLUMINATE and ACCELERATE showed that pharmacologically raising HDL-C this way did not reduce cardiovascular events, shifting the field's focus toward HDL function rather than concentration. (ILLUMINATE, ACCELERATE trialsA large randomized trial of evacetrapib that substantially raised HDL-cholesterol and lowered LDL-cholesterol yet failed to reduce cardiovascular outcomes in high-risk patients, further supporting the view that HDL-C is a marker rather than a causal protective factor.)—did not consistently reduce cardiovascular events.16 The predictive and protective value lies instead in HDL functionality, particularly its Cholesterol Efflux CapacityCholesterol efflux capacity is a laboratory test of how well someone's HDL actually pulls cholesterol out of cells — a measure of function rather than quantity. (CEC), which represents its ability to remove cholesterol from macrophagesA macrophage is a large immune cell that swallows debris and invaders. The name literally means "big eater." in arterial plaquesA deposit within the artery wall made up of lipids, immune cells, cellular debris, and fibrous tissue that accumulates over time and can narrow or block blood flow; also called an atherosclerotic lesion or atheroma..16
- sdLDL: The Principal Atherogenic Target: Small Dense Low-Density Lipoprotein (sdLDL) particles are identified as critically atherogenic.16 Their physical characteristics—small size, higher density, and low antioxidantAn antioxidant is a substance that mops up damaging molecules in the body. Vitamin E and beta-carotene are examples. content—allow them to penetrate the arterial intimaThe intima is the innermost layer of an artery wall, sitting just beneath the smooth lining. efficiently and undergo oxidative modification.15 Furthermore, their prolonged plasma half-life (up to 74 hours) increases their exposure time to the endothelial environment.15 Elevated sdLDL concentrations are strongly associated with increased ASCVD event risk (Adjusted HRs: 1.21 to 1.52).16
- Therapeutic Consensus: Current guidelines prioritize reducing the overall burden of atherogenic lipoproteins, measured pragmatically by non-HDL-C or ApolipoproteinAn apolipoprotein is a protein attached to a fat-carrying particle in your blood. Fat and water don't mix, so these proteins act like a wrapper that lets fat travel safely through the bloodstream. B (ApoBApoB is a protein that sits on the outside of every cholesterol particle that can get stuck in your artery wall and cause plaque. Each of those particles carries exactly one ApoB.), which effectively targets sdLDL and remnant particles. StatinsA statin slows the enzyme your liver uses to make cholesterol. Your liver responds by pulling more cholesterol out of your blood, which is where the real benefit comes from. and PCSK9 inhibitorsA PCSK9 inhibitor is a medicine that blocks that cholesterol-destroying protein, leaving more docking ports available to clear particles from the blood. remain the foundation of therapy, reducing LDL-C and ApoB.16
B. Third-Order Integration: Dual Risk Management Strategy
The physiological mechanisms driving Afib risk (remodeling/fibrosis) and those driving atherosclerotic risk (sdLDL accumulation/inflammationInflammation is your immune system's response to injury or something it treats as an invader. It brings swelling, heat, and cleanup cells.) often overlap in the aging athlete. The approach must be comprehensive.
The necessity of managing Afib recurrence through exercise moderation paradoxically supports optimizing lipid profileA blood test panel that measures total cholesterol, LDL cholesterol, HDL cholesterol, and triglycerides, used to assess cardiovascular risk and monitor the effect of dietary or drug interventions. via lifestyle:
- Lifestyle Synergy: Structured physical activity (moderate-to-vigorous exercise) and appropriate dietary modifications (e.g., Mediterranean, rich in unsaturated fatsUnsaturated fat is liquid at room temperature and comes from plants and fish — olive oil, nuts, seeds, avocado, seed oils. like olive oilOlive oil is the main fat of the Mediterranean diet, rich in monounsaturated fat and, in the extra virgin form, in plant compounds called polyphenols. 16, and low in refined carbohydratesCarbohydrates are the sugars and starches in food — bread, rice, pasta, fruit, potatoes, sweets.) simultaneously address both cardiac risks. These changes improve overall cardiometabolic profile, enhance HDL functional capacity (increasing CEC and antioxidant potential), and reduce plasma triglyceride levels, thereby diminishing the hepatic production of sdLDL.16
- Targeted Residual RiskResidual risk is the risk that remains after you have done the obvious things — cholesterol treated, blood pressure controlled, not smoking. Mitigation (Omega-3): Given the high ASCVD risk associated with sdLDL and remnant particles, pharmacological intervention may be warranted if hypertriglyceridemia (e.g., > 150 mg/dL) persists despite optimal statin therapy and lifestyle changes. High-dose pharmaceutical-grade Eicosapentaenoic Acid (EPA) demonstrated a 25% relative risk reduction in major cardiovascular events in the REDUCE-IT trialA large randomized trial of 8,179 high-risk, statin-treated patients assigned to icosapent ethyl 4 g/day or mineral oil placebo; it reported a 25% relative risk reduction in major cardiovascular events and a number needed to treat of 21 over a median of 4.9 years..16 This is a targeted therapy for the residual risk driven by sdLDL.
- Critical Nuance in EPA Use: A vital consideration for a patient with established Afib is the recognized possibility of increased Afib incidence associated with high-dose omega-3 fatty acidsOmega-3s are fats found mainly in oily fish, walnuts, and flaxseed..16 The decision to use high-dose EPA requires careful consultation with the electrophysiologistA cardiologist subspecialist who focuses on the electrical system of the heart, diagnosing and treating arrhythmias; responsible for performing catheter ablation and managing AF in athletes. to balance the certain benefit of ASCVD risk reduction against the potential for exacerbating the underlying arrhythmia.
V. Conclusions and Recommendations
For the Masters athlete (age 50+) successfully treated for Atrial Fibrillation, the clinical data strongly indicate that continued intense training represents an elevated, medically unacceptable risk to long-term cardiac stability. The need to slow and restructure intense training is a mandatory component of therapy, not a subjective lifestyle choice.
The statistical probabilities overwhelmingly support intervention:
- The probability of Afib recurrence and progression (e.g., to atypical flutter) remains high if the athlete maintains chronic, high-volume endurance training, as this perpetuates the underlying atrial fibrosisMicroscopic scarring of atrial muscle tissue, often resulting from chronic mechanical stretch or inflammation; fibrosis disrupts normal electrical conduction and is a well-established predictor of AF recurrence after ablation..8
- Implementing a structured, therapeutic exercise dose (approximately 210 minutes per week of moderate-to-vigorous activity, favoring intervals) actively reduces the probability of AF recurrence (RR 82).3
- The probability of a stroke event increases substantially (HR > 2.5) if a high-risk athlete (CHA2DS2-VASc >2) prematurely discontinues OAC, underscoring that rhythm stability does not negate thromboembolic risk.4
Recommended Course of Action
- Mandatory Training Shift: The athlete must transition their training goal from maximal endurance performance to cardiovascular health maintenance. This involves reducing volume below chronic high-dose thresholds (i.e., less than 10 hours per week of high-intensity activity) and emphasizing structured interval training for sustained fitness and reduced Afib burden.
- Stroke Prevention Adherence: OAC status must adhere strictly to guideline recommendations based on the CHA2DS2-VASc score. For most Masters athletes over 50 with treated Afib, continued OAC is required, necessitating the avoidance of contact or high-trauma sports.
- Holistic Risk Management: Integrate the management of Afib with the control of atherosclerotic risk (ASCVD). Prioritize lifestyle factors (dietary fat composition, carbohydrate restriction) that enhance HDL function and reduce the highly atherogenic sdLDL particles.16 Any adjunctive therapy, such as high-dose EPA for hypertriglyceridemia, requires careful consideration due to the potential interaction with Afib burden.
- Expert Monitoring: The athlete’s return to play and training intensity must be guided by a cardiology team specializing in sports electrophysiology, using serial monitoring and exercise stress testing to confirm rhythm and rate control during exertion.1
References
- Mont L, Elosua R, Brugada J. Endurance sport practice as a risk factor for atrial fibrillation and atrial flutter. Europace. 2009;11(1):11-17. doi:10.1093/europace/eun289
- Malmo V, Nes BM, Amundsen BH, et al. Aerobic Interval Training Reduces the Burden of Atrial Fibrillation in the Short Term: A Randomized Trial. Circulation. 2016;133(5):466-473. doi:10.1161/CIRCULATIONAHA.115.018220
- Fukata E, Hardani R, Mukti N, Pranawa F, Rusnanta F, Rizal A. Physical Exercise Intervention Improves Cardiac Function and Reduce Recurrences in Non-permanent Atrial Fibrillation: A Systematic Review and Meta-analysis. J Saudi Heart Assoc. 2025;37(4):1459. Published 2025 Oct 10. doi:10.37616/2212-5043.1459
- Noseworthy PA, Yao X, Deshmukh AJ, et al. Patterns of Anticoagulation Use and Cardioembolic Risk After Catheter Ablation for Atrial Fibrillation. J Am Heart Assoc. 2015;4(11):e002597. Published 2015 Nov 5. doi:10.1161/JAHA.115.002597
- Guasch E, Mont L. Diagnosis, pathophysiology, and management of exercise-induced arrhythmias. Nat Rev Cardiol. 2017;14(2):88-101. doi:10.1038/nrcardio.2016.173
- Pelliccia A, Maron BJ, Di Paolo FM, et al. Prevalence and clinical significance of left atrial remodeling in competitive athletes. J Am Coll Cardiol. 2005;46(4):690-696. doi:10.1016/j.jacc.2005.04.052
- Benito B, Gay-Jordi G, Serrano-Mollar A, et al. Cardiac arrhythmogenic remodeling in a rat model of long-term intensive exercise training. Circulation. 2011;123(1):13-22. doi:10.1161/CIRCULATIONAHA.110.938282
- Katritsis G, Calkins H. Catheter Ablation of Atrial Fibrillation – Techniques and Technology. Arrhythm Electrophysiol Rev. 2012;1(1):29-33. doi:10.15420/aer.2012.1.29
- Calvo N, Mont L, Tamborero D, et al. Efficacy of circumferential pulmonary vein ablation of atrial fibrillation in endurance athletes. Europace. 2010;12(1):30-36. doi:10.1093/europace/eup320
- Heidbüchel H, Panhuyzen-Goedkoop N, Corrado D, et al. Recommendations for participation in leisure-time physical activity and competitive sports in patients with arrhythmias and potentially arrhythmogenic conditions Part I: Supraventricular arrhythmias and pacemakers. Eur J Cardiovasc Prev Rehabil. 2006;13(4):475-484. doi:10.1097/01.hjr.0000216543.54066.72
- Pelliccia A, Sharma S, Gati S, et al. 2020 ESC Guidelines on sports cardiology and exercise in patients with cardiovascular disease. Eur Heart J. 2021;42(1):17-96. doi:10.1093/eurheartj/ehaa605
- Elliott AD, Mahajan R, Lau DH, Sanders P. Atrial Fibrillation in Endurance Athletes: From Mechanism to Management. Cardiol Clin. 2016;34(4):567-578. doi:10.1016/j.ccl.2016.06.006
- Menezes AR, Lavie CJ, De Schutter A, et al. Lifestyle modification in the prevention and treatment of atrial fibrillation. Prog Cardiovasc Dis. 2015;58(2):117-125. doi:10.1016/j.pcad.2015.07.001
- Lobo HM, Naves ÍG, Marçal SB, Canzi CC, Rodrigues ABS, Menezes AS Jr. Atrial Fibrillation in Endurance Training Athletes: Scoping Review. Rev Cardiovasc Med. 2023;24(6):155. Published 2023 May 26. doi:10.31083/j.rcm2406155
- Stoicescu C, Vacarescu C, Cozma D. HDL Function Versus Small Dense LDL: Cardiovascular Benefits and Implications. J Clin Med. 2025;14(14):4945. Published 2025 Jul 12. doi:10.3390/jcm14144945
- Bhatt DL, Steg PG, Miller M, et al. Cardiovascular Risk Reduction with Icosapent Ethyl for Hypertriglyceridemia. N Engl J Med. 2019;380(1):11-22. doi:10.1056/NEJMoa1812792
- Rohatgi A, Khera A, Berry JD, et al. HDL cholesterol efflux capacity and incident cardiovascular events. N Engl J Med. 2014;371(25):2383-2393. doi:10.1056/NEJMoa1409065

