
The Evolution of Cardiovascular Risk Assessment and Lipid Management:
A Life-Course Analysis from 1960 to 2026
Introduction
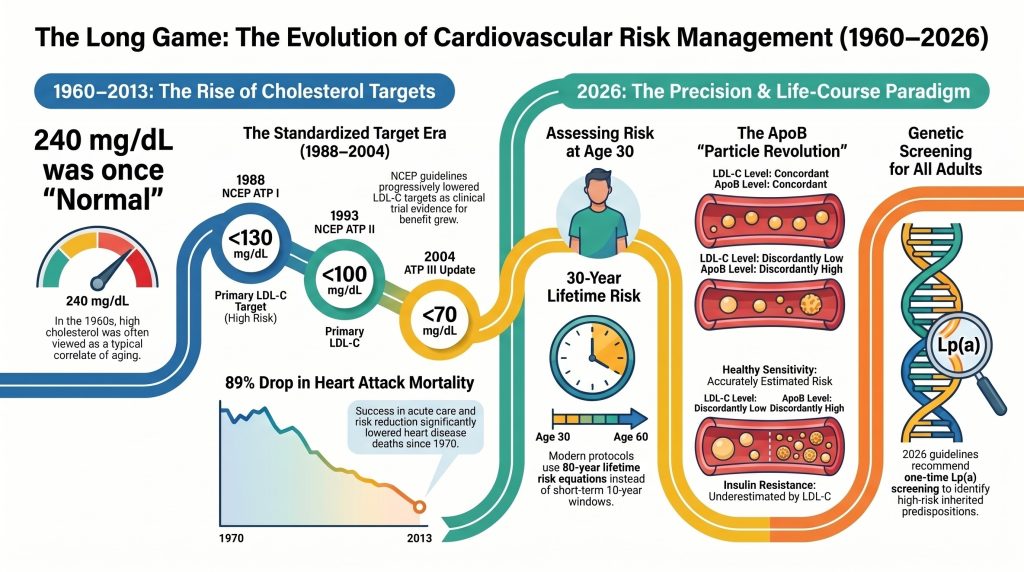
The historical trajectory of cardiovascular medicine represents a profound shift from reactive management of end-stage clinical events to a proactive, life-course paradigm centered on the physiological drivers of atherosclerosisAtherosclerosis is the disease behind most heart attacks and many strokes. Cholesterol particles get stuck in the wall of an artery, the body sends immune cells to clean up, and over years that mess hardens into plaque.. Since the mid-twentieth century, the medical community’s understanding of lipid metabolism has evolved from a focus on crude total cholesterolTotal cholesterol adds together the cholesterol in all your particles, harmful and helpful alike. measurements to a nuanced appreciation of lipoproteinA lipoprotein is a tiny package that carries fat and cholesterol through your bloodstream. Since fat won't dissolve in water, it needs a protein wrapper to travel. particle concentration, genetic predisposition, and the cumulative burden of atherogenic exposure. As of 2026, the clinical focus has moved toward identifying risk decades before the onset of symptomatic disease, utilizing advanced biomarkersA biomarker is something measurable in the body that tells you about health or disease — a lab value, a scan result, a blood pressure reading. such as ApolipoproteinAn apolipoprotein is a protein attached to a fat-carrying particle in your blood. Fat and water don't mix, so these proteins act like a wrapper that lets fat travel safely through the bloodstream. B (ApoBApoB is a protein that sits on the outside of every cholesterol particle that can get stuck in your artery wall and cause plaque. Each of those particles carries exactly one ApoB.) and Lipoprotein(a)Lipoprotein(a), written Lp(a) and said "L-P-little-a," is an LDL-like particle with an extra sticky protein attached. [Lp(a)], and incorporating polygenic risk scoresA polygenic risk score adds up the effects of many small genetic variants to estimate your inherited risk of a disease. into standardized assessment tools.1
Historical Shifts in Cholesterol Guidelines and Clinical Targets
The conceptualization of cholesterolCholesterol is a waxy substance your body needs. It goes into cell walls, hormones, vitamin D, and the bile that digests your food. You would die without it. as a primary agent of vascular pathology was not an immediate consensus but rather a hard-won evolution through decades of epidemiological observation and clinical trialA clinical trial is a study where researchers give one group a treatment and another group a placebo or standard care, then compare what happens. evidence. In the 1960s, the ‘cholesterol controversy’ was at its zenith, with researchers debating whether blood lipids were merely correlates of aging or causative agents of heart disease.2
The Pre-NCEP Era and the Rise of the Lipid Hypothesis
Prior to the formalization of national guidelines, ‘acceptable’ total cholesterol levels were remarkably high by modern standards. In the 1960s and early 1970s, clinicians commonly regarded total cholesterol levels of 240 mg/dL or higher as normal for aging adults. This perception was rooted in average population levels of the time, where the mean total cholesterol for U.S. adults aged 20–74 was approximately 222 mg/dL between 1959 and 1962.3 Early interventions were primarily dietary. The American Heart Association issued its first formal dietary recommendations in 1961 and updated them in 1968, advocating restriction of saturated fatSaturated fat is the kind that stays solid at room temperature — butter, the fat in red meat, coconut oil, and palm oil. and dietary cholesterolDietary cholesterol is the cholesterol in food — eggs, shrimp, liver, and other animal products.. These early targets reflected a nascent understanding that dietary saturated fat influenced serum cholesterol levels, though the magnitude of this effect was often overestimated in isolation from the broader dietary context.4
The National Cholesterol Education Program and the Adult Treatment Panels
The 1980s marked a pivotal transition with the establishment of the National Cholesterol Education Program (NCEP)The National Cholesterol Education Program was a U.S. government initiative launched in 1985 that produced a series of Adult Treatment Panel (ATP) reports — ATP I in 1988, ATP II in 1993, and ATP III in 2001 — which established the first standardised numerical LDL-C targets and shaped clinical cholesterol management for several decades.. The release of the first Adult Treatment Panel (ATP I) report in 1988 provided the first standardized framework for identifying and treating high blood cholesterol.5
Table 1. Evolution of U.S. Cholesterol Guidelines, 1988–2026
| Guideline Report | Year | Primary Focus | LDL-C Targets / Key Changes |
| NCEP ATP I | 1988 | Primary preventionPrimary prevention is treating someone who has never had a heart attack or stroke, to keep the first one from happening.; total cholesterol and LDL-C screening. | LDL-C <160 mg/dL (low risk); <130 mg/dL (high risk). |
| NCEP ATP II | 1993 | Secondary preventionSecondary prevention is treating someone who has already had a heart attack, stroke, or stent, to stop the next one. for established CHD; emphasized HDL-C. | LDL-C <100 mg/dL for secondary prevention. |
| NCEP ATP III | 2001 | 10-year risk assessment (Framingham); CHD ‘risk equivalents’ including diabetesDiabetes is a condition where blood sugar stays too high, either because the body makes too little insulin or because it stops responding to the insulin it makes.. | Optimal LDL-C <100 mg/dL; low HDL-C defined as <40 mg/dL. |
| ATP III Update | 2004 | Intensified therapy for ‘very high risk’ individuals. | Optional LDL-C <70 mg/dL for very high risk. |
| 2013 ACC/AHA | 2013 | Abandoned treat-to-target; identified four statinA statin slows the enzyme your liver uses to make cholesterol. Your liver responds by pulling more cholesterol out of your blood, which is where the real benefit comes from. benefit groups. | High- vs. moderate-intensity statin therapy; no specific LDL-C target. |
| 2018 AHA/ACC Multisociety | 2018 | Return to thresholds; risk-based escalation with non-statin agents. | LDL-C <70 mg/dL (high risk); <55 mg/dL (very high risk). |
| 2026 ACC/AHA DyslipidemiaDyslipidemia is the medical word for an unhealthy pattern of fats in the blood. It can mean high LDL, high triglycerides, low HDL, or some combination. Guideline | 2026 | Life-course prevention; PREVENT equationsThe PREVENT (Predicting Risk of Cardiovascular Disease EVENTs) equations are a cardiovascular risk model adopted in the 2026 ACC/AHA guidelines that estimate both 10-year and 30-year lifetime risk of ASCVD, replacing the older Framingham-based Pooled Cohort Equations and enabling earlier risk stratification beginning at age 30. for 10- and 30-year risk; ApoB and Lp(a) screening. | LDL-C <55 mg/dL (very high risk); universal one-time Lp(a) testing. |
NCEP = National Cholesterol Education Program; ATP = Adult Treatment Panel; ACC = American College of Cardiology; AHA = American Heart Association.
The rationale for progressively lower targets was driven by a robust accumulation of evidence from randomized controlled trialsA randomized controlled trial assigns people to a treatment or a comparison group purely by chance, then follows both groups.. The Lipid Research Clinics Coronary Primary Prevention Trial (LRC-CPPT) in 1984 demonstrated that for every 1% reduction in total cholesterol, CHD risk fell by approximately 2%, providing an early statistical foundation for aggressive lipid-lowering.6 Subsequent trials in the 1990s and early 2000s—the Scandinavian Simvastatin Survival Study (4S)The 4S trial was a landmark 1994 randomised controlled trial that demonstrated simvastatin significantly reduced all-cause mortality and major cardiovascular events in patients with established coronary heart disease and elevated cholesterol, providing the first definitive evidence that statin therapy saves lives in secondary prevention., the Cholesterol and Recurrent Events trial (CARE), and the Long-Term Intervention with PravastatinA moderate-intensity statin that lowers LDL-C roughly 22–32% across common licensed doses; because it is not metabolized through the CYP3A4 pathway and is hydrophilic, it is often preferred when muscle tolerability is a concern. in Ischaemic Disease (LIPID) study—consistently showed that lowering LDL-C reduced major adverse cardiovascular eventsA major adverse cardiovascular event, or MACE, is a bundle of bad outcomes counted together in a study — typically cardiovascular death, heart attack, and stroke. (MACE), leading to broad adoption of the ‘lower is better’ philosophy.7
The 2013 Paradigm Shift and the Move to Statin Intensity
A significant disruption occurred in 2013 with the release of the ACC/AHA cholesterol guidelines. This report moved away from specific LDL-C numerical targets, instead identifying four ‘statin benefit groups’ where evidence for risk reduction was most compelling: (1) individuals with clinical atherosclerotic cardiovascular diseaseCardiovascular disease is the umbrella term for problems with the heart and blood vessels, including heart attacks, strokes, and blocked leg arteries. (ASCVD); (2) individuals with primary LDL-C elevations ≥190 mg/dL; (3) individuals aged 40–75 years with diabetes and LDL-C 70–189 mg/dL; and (4) individuals aged 40–75 years without clinical ASCVD or diabetes, with LDL-C 70–189 mg/dL and an estimated 10-year ASCVD risk ≥7.5%.8 This approach prioritized the intensity of statin therapy over the achievement of a specific LDL-C level. However, this shift was controversial, as many clinicians felt it reduced motivation for patient adherenceAdherence means actually taking your medicine the way it was prescribed, day after day. and neglected individual variability in drug response.9
The Return to Targets and the 2026 Life-Course Paradigm
The 2018 ACC/AHA Multisociety guidelines and the 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia restored explicit LDL-C treatment targets with a significantly expanded scope. Published in the Journal of the American College of Cardiology and co-published in Circulation, the 2026 guideline emphasizes earlier risk assessment beginning at age 30 and mandates use of the PREVENT (Predicting Risk of Cardiovascular Disease EVENTs) equations to estimate both 10-year and 30-year lifetime risk.1 For adults aged 30–79 years without known ASCVD and with LDL-C 70–189 mg/dL, the PREVENT-ASCVD equations classify 10-year risk as low (<3%), borderline (3% to <5%), intermediate (5% to <10%), or high (≥10%). For very high-risk individuals (defined as those with multiple major ASCVD events or one major event plus multiple high-risk conditions), the guideline recommends an LDL-C target of <55 mg/dL.1 This reflects the modern understanding that atherosclerosis is a lifelong cumulative process, where the ‘area under the curve’ of atherogenic lipoprotein exposure determines ultimate event risk.10
Population Averages Versus Optimal Biological Health
A central theme in contemporary lipidology is the recognition that ‘average’ or ‘normal’ cholesterol levels in industrialized populations do not represent health but rather a high-risk baseline shaped by diet, physical inactivity, and metabolic disease.11
NHANES Trends in Mean Cholesterol: 1960 to Present
Data from the National Health and Nutrition Examination Survey (NHANES) document a steady decline in mean total cholesterol among U.S. adults aged 20–74 years, from approximately 222 mg/dL in 1959–1962 to 197 mg/dL by 2007–2008.3 Despite this encouraging trend, the mean U.S. adult cholesterol profile continues to facilitate atherosclerotic plaquePlaque is the buildup of cholesterol, immune cells, scar tissue, and calcium inside an artery wall. progression. The prevalence of high total cholesterol (≥240 mg/dL) declined from approximately 20% in 1988–1994 to 11.3% in 2021–2023, though this plateau has persisted since approximately 2013–2014.12
Table 2. NHANES Trends in Total Cholesterol and LDL-C in U.S. Adults Aged 20–74 Years
| NHANES Period | Mean Total Cholesterol (mg/dL) | Mean LDL-C (mg/dL) | Prevalence of High TC (≥240 mg/dL) |
| 1959–1962 | ~222 | N/A | High (estimated) |
| 1971–1975 | ~216 | N/A | N/A |
| 1976–1980 | ~213 | ~137 | N/A |
| 1988–1994 | ~206 | ~129 | ~20% |
| 2007–2008 | ~197 | ~116 | ~17% |
| 2021–2023 | N/A | N/A | ~11.3% |
Sources: Carroll et al. (2012); Curtin et al. (2024). N/A = data not available from cited surveys.
The prevalence of metabolic dysfunction—characterized by obesityObesity means carrying enough excess body fat to affect health., hyperinsulinemia, and insulin resistanceInsulin resistance is when your cells stop responding well to insulin, so your pancreas has to pump out more and more to do the same job.—has shifted the ‘normal’ distribution toward higher triglyceridesTriglycerides are the main form of fat in your blood and in your body's storage. and lower HDL-C, creating a population where the average individual is actively developing vascular lesionsIn cardiology, a lesion refers to a discrete area of atherosclerotic plaque narrowing a coronary artery, typically described by the percentage of luminal obstruction it causes. The article describes four residual lesions too small in vessel diameter to accept a stent after the most critical one was treated..13 In striking contrast, human neonates typically possess LDL-C levels between 30 and 70 mg/dL, consistent with levels observed in wild-type primates and other mammals that do not spontaneously develop atherosclerosis.14
Lessons from the Tsimane of the Bolivian Amazon
The TsimaneThe Tsimane are an indigenous forager-horticulturalist population of the Bolivian Amazon whose traditional lifestyle—characterized by high physical activity and low average LDL cholesterol of around 91 mg/dL—is associated with markedly low rates of coronary calcification, with 85 percent of adults over 40 showing no detectable coronary calcium. population of the Bolivian Amazon provides a unique biological benchmark. A landmark 2017 cross-sectional cohort studyA cohort study follows a large group of people over time, recording what they eat or do and what happens to their health years later. published in The Lancet found that the Tsimane have the lowest reported prevalence of coronary atherosclerosis of any population yet studied—five times lower than comparable U.S. populations.15 In a sample of 705 adults aged 40–94 years, 85% had a coronary artery calcium (CAC)Coronary artery calcium is a measure of calcified plaque deposits in the walls of the coronary arteries, quantified by CT scan and expressed as an Agatston score; higher scores indicate greater cumulative plaque burden and predict future cardiovascular events. score of zero, and among those aged over 75 years, 65% still had no measurable coronary calcificationCalcification is when calcium gets deposited into a plaque, turning part of it hard and bony.—a five-fold lower prevalence than age-matched Americans in the Multi-Ethnic Study of Atherosclerosis (MESA)A large prospective cohort study of adults initially free of cardiovascular disease that has provided foundational data on coronary artery calcium scoring, demonstrating a strong graded association between CAC burden and future coronary events and validating the risk implications of a CAC score of zero..15
The mean LDL-C of Tsimane participants was 91 mg/dL and mean HDL-C was 39.5 mg/dL.15 Notably, this low burden of atherosclerosis persisted despite elevated systemic inflammationInflammation is your immune system's response to injury or something it treats as an invader. It brings swelling, heat, and cleanup cells.: high-sensitivity C-reactive proteinC-reactive protein, or CRP, is a substance your liver makes when there is inflammation somewhere in your body. A sensitive version of the test, hs-CRP, is used to estimate heart risk. exceeded the clinical cutoff of 3.0 mg/dL in 51% of Tsimane participants, attributable to a high infectious and parasitic burden rather than vascular inflammation.15 These findings suggest that atherosclerosis is not an inevitable consequence of aging or inflammation alone, but requires a critical threshold of circulating atherogenic lipoprotein exposure—a threshold exceeded in virtually all contemporary Western populations.15
Apolipoprotein B as a Superior Measure of Atherogenic Risk
While LDL-C measures the total mass of cholesterol within LDLLDL, or low-density lipoprotein, is the main particle that carries cholesterol through your blood — and the main one that gets stuck in artery walls. particles, it does not account for the total number of atherogenic lipoprotein particles or the heterogeneity of their composition. Apolipoprotein B (ApoB) is the structural proteinProtein is the nutrient your body uses to build and repair muscle and tissue. present in a 1:1 ratio on every potentially atherogenic particleAtherogenic particles are the ApoB-containing lipoproteins—including LDL, IDL, VLDL, and lipoprotein(a)—that can enter and be retained in the artery wall to initiate and sustain plaque growth; the article uses the term to describe what must be lowered substantially and sustainably to achieve plaque regression., including VLDLVLDL, or very-low-density lipoprotein, is the particle your liver makes to ship triglycerides out to the rest of the body., IDLIDL, or intermediate-density lipoprotein, is a particle that forms partway through the process of a big triglyceride-carrying particle shrinking down into an LDL particle., LDL, and Lp(a).16
The Mechanistic Case for ApoB Superiority
The emerging consensus in lipidology holds that the total number of atherogenic particles is the primary driver of the ‘response-to-retention’ mechanism of atherosclerosis initiation. Atherosclerosis begins when ApoB-containing particlesLipoproteins—including LDL, IDL, VLDL, and their remnants—that each carry one molecule of apolipoprotein B on their surface; particle number (rather than cholesterol mass alone) is a key driver of atherosclerosis because each particle can be retained in the arterial wall. traverse the endothelial barrier and become trapped within the subendothelial proteoglycan matrixThe subendothelial proteoglycan matrix is the structural meshwork of proteoglycans — including versican, biglycan, and heparan sulfate — lying just beneath the endothelial lining of artery walls; ApoB-containing lipoprotein particles that cross the endothelium become physically trapped here, where they are oxidised and initiate the atherosclerotic process..17 Because each such particle carries one ApoB molecule, ApoB measurement directly quantifies the total atherogenic particle burdenParticle burden refers to the total number of atherogenic lipoprotein particles circulating in the plasma, best measured by ApoB; it is distinguished from cholesterol mass because it is the physical count of particles — not the amount of cholesterol they carry — that determines how frequently lipoproteins infiltrate and become entrapped in the arterial wall. delivered to the arterial wall—a metric more physiologically precise than the cholesterol content of LDL particles alone.16
Discordance Between ApoB and LDL-C in Metabolic Disease
The limitations of LDL-C are most apparent in individuals with insulinInsulin is a hormone made by your pancreas. Its main job is letting sugar move out of your blood and into your cells for fuel. resistance, type 2 diabetes, or hypertriglyceridemia. Metabolic dysfunction leads to hepatic overproduction of large, triglyceride-rich VLDL particles. In the circulation, cholesteryl esterCholesteryl esters are storage forms of cholesterol in which a fatty acid is attached to cholesterol; they accumulate in large quantities inside foam cells and the extracellular spaces of plaques, and their depletion—measured as regression of the lipid-rich pool—is a primary marker of plaque improvement in primate regression studies. transfer protein (CETPCETP is a protein that swaps cholesterol and triglycerides between HDL and the harmful ApoB particles.) exchanges triglycerides from VLDL for cholesterol esters in LDL particles, and the resulting triglyceride-enriched LDL undergoes hydrolysis by hepatic lipaseHepatic lipase is a liver-produced enzyme that hydrolyses triglyceride-enriched LDL particles in the circulation, converting them into smaller, denser LDL; its activity is upregulated in insulin-resistant states, accelerating the production of small dense LDL and the discordance between LDL-C and ApoB. to yield small, dense LDL (sdLDL).18 These sdLDL particles are cholesterol-depleted per particle, producing paradoxically low LDL-C values despite a high total ApoB (and particle) count. A systematic reviewA systematic review searches for every study on a question using a pre-declared method, then assesses them by consistent criteria. and meta-analysisA meta-analysis statistically combines the results of many separate studies into one overall estimate. demonstrated that such ApoB/LDL-C discordanceSee ApoB Discordance for the full entry. is prevalent in metabolic disease and is associated with significant underestimation of cardiovascular risk.13
Table 3. ApoB/LDL-C Discordance Patterns by Metabolic State
| Metabolic State | LDL-C Level | ApoB Level | Clinical Implication |
| Healthy insulin sensitivityInsulin sensitivity is how well your cells respond to insulin. It is the opposite of insulin resistance. | Concordant (e.g., 100 mg/dL) | Concordant (e.g., 80 mg/dL) | Risk accurately estimated by either metric. |
| Insulin resistance / type 2 diabetes | Discordantly low (e.g., 90 mg/dL) | Discordantly high (e.g., 110 mg/dL) | Risk underestimated by LDL-C alone. |
| High saturated fat intake (large LDL phenotype) | Discordantly high (e.g., 160 mg/dL) | Relatively lower (e.g., 100 mg/dL) | Risk may be overestimated by LDL-C. |
Adapted from: Tsoupras et al. (2024); Fahed et al. (2022).
Analyses of NHANES data have shown that approximately 20% of the general U.S. population exhibits clinically significant discordance between ApoB and LDL-C, with this proportion rising substantially among those with metabolic syndromeMetabolic syndrome is a cluster of five problems that tend to travel together: a large waist, high triglycerides, low HDL, high blood pressure, and high blood sugar. Having three or more counts..19 Individuals with high ApoB but concordantly low LDL-C demonstrate significantly higher rates of coronary arteryAn artery is a blood vessel that carries blood away from the heart to the rest of the body. calcification and chronic kidney diseaseChronic kidney disease is a lasting reduction in the kidneys' ability to filter waste from the blood. than those with the inverse pattern, confirming that particle number is the mechanistically relevant driver of atherogenesisAtherogenesis is the step-by-step process of a plaque forming..20
Small, Dense LDL: The Mechanistic Link
Small, dense LDL particles are uniquely hazardous for three principal reasons. First, their reduced size facilitates penetration of the arterial intimaThe intima is the innermost layer of an artery wall, sitting just beneath the smooth lining.. Second, they exhibit enhanced affinity for subendothelial proteoglycans, leading to prolonged retention at the site of atherogenesis. Third, they are more susceptible to oxidative modification—the prerequisite step for macrophageA macrophage is a large immune cell that swallows debris and invaders. The name literally means "big eater." uptake and foam cellA foam cell is an immune cell that has eaten so much trapped cholesterol that it swells up and looks foamy under a microscope. formation.21 Clinically, a patient with a ‘normal’ LDL-C but elevated ApoB or LDL particle numberLDL particle number counts how many LDL particles are circulating, rather than how much cholesterol they contain. carries a risk profile that is systematically concealed by standard lipid screening.13
Lipoprotein(a): The Genetic Vanguard of ASCVD Risk
Lipoprotein(a) [Lp(a)] has only recently attained widespread clinical recognition despite being identified in the 1960s. Its Lp(a) levels are approximately 70–90% genetically determined by variation at the LPA gene locus and are not meaningfully altered by lifestyle modification or conventional statin therapy.22
Role in Atherogenesis, Thrombosis, and Valvular Disease
Lp(a) consists of an LDL-like lipoprotein with an additional glycoprotein, apolipoprotein(a) [apo(a)], covalently attached to the ApoB-100ApoB-100 is the full-length form of apolipoprotein B found on LDL, VLDL, IDL, and remnant lipoproteins; its positively charged amino-acid domains bind ionically to negatively charged proteoglycan side chains in the arterial wall, physically trapping the particle in the intima and initiating plaque formation. molecule via a disulfide bond.22 This structural configuration confers dual pathogenicity: Lp(a) is both highly atherogenic through its retention in the subendothelial spaceThe subendothelial space is the narrow gap just beneath the artery's inner lining, between that single layer of cells and the muscle beneath. and is potentially prothrombotic through the structural homology of apo(a) with plasminogenA blood protein that is converted to the clot-dissolving enzyme plasmin; apo(a) in Lp(a) shares strong structural homology with plasminogen, allowing Lp(a) to competitively interfere with clot breakdown., which may interfere with fibrinolysisThe physiological process by which the body dissolves blood clots through the enzyme plasmin; Lp(a) impairs this process by competing with plasminogen for fibrin-binding sites, reducing clot clearance and increasing the risk of an occlusive cardiac event..23 Elevated Lp(a) is also a major independent risk factorA risk factor is something that raises your chance of developing a disease — high cholesterol particles, high blood pressure, smoking, diabetes, family history. for calcific aortic valveThe aortic valve is the one-way gate between the heart's main pumping chamber and the aorta. stenosisStenosis is narrowing — usually described as a percentage, like a 70 percent blockage.; individuals with the highest Lp(a) levels face substantially higher risk of aortic valve replacement or aortic valve-related death.24
Screening Recommendations and Emerging Therapies
The 2026 ACC/AHA Dyslipidemia Guideline recommends at least one lifetime measurement of Lp(a) for all adults to identify individuals with high inherited cardiovascular risk.1 Elevated Lp(a)—generally defined as ≥50 mg/dL (or ≥125 nmol/L)—affects an estimated 20–25% of the global population, representing over 1.5 billion individuals, and contributes substantially to residual cardiovascular riskThe continuing probability of major cardiovascular events that remains even after recognized risk factors such as LDL cholesterol and blood pressure have been brought under control, attributable to persistent calcification, arterial stiffness, low-grade inflammation, and incomplete plaque stabilization. that is not addressed by statin therapy.23
Table 4. Emerging RNA-Based Therapies Targeting Lp(a) as of 2026
| Treatment Class | Mechanism of Action | Lp(a) Reduction | Development Status (2026) |
| Antisense oligonucleotides (ASO) | Binds to LPA mRNA to promote degradation via RNase H. | ~70–80% | PelacarsenPelacarsen is an RNA-targeted therapy (an antisense oligonucleotide) designed to lower lipoprotein(a) by reducing its production in the liver; it is given by intravenous or subcutaneous injection every few weeks and is currently in late-stage trials to determine whether Lp(a) reduction translates into fewer cardiovascular events.: Phase 3 cardiovascular outcomes trial (HORIZON) completed; results awaited. |
| siRNA therapies | Cleaves LPA mRNA via the RISC complex. | ~80–95% | OlpasiranOlpasiran is a small-interfering RNA (siRNA) drug in phase 3 clinical development that dramatically reduces circulating Lp(a) levels by silencing the gene responsible for its production in the liver. (OCEAN[a]-OUTCOMES trial ongoing); Lepodisiran (Phase 3). |
| Oral small-molecule inhibitors | Disrupts the hepatic assembly of apo(a) and ApoB. | Significant reduction | Muvalaplin: Phase 2 completed; Phase 3 planned. |
Sources: Tsimikas (2022); Kronenberg & Mora (2025). RISC = RNA-induced silencing complex; mRNA = messenger RNA.
While these therapies are still awaiting definitive cardiovascular outcome trial results, they represent a transformative paradigm shift in our ability to pharmacologically address a previously ‘unreachable’ genetic risk factor.25
Cardiovascular Mortality Trends: 1970 to 2022
The decline in cardiovascular mortality since 1970 represents one of the most remarkable public health achievements of the modern era. A comprehensive analysis of U.S. National Vital Statistics System data for adults aged 25 years and older, published in the Journal of the American Heart Association in 2025, found that in 1970 heart disease accounted for 41% of all deaths; by 2022, this had fallen to 24%—an overall reduction in age-adjusted heart disease mortality of 66%.26
Deconstructing the Decline
Age-adjusted mortalityAge-adjusted mortality is a death rate that has been statistically corrected so that differences in the age structure of populations — or of the same population over time — do not distort comparisons. It answers the question: would the death rate have changed if the age mix had stayed constant? from acute myocardial infarctionSee Heart Attack for the full entry. (AMI) declined by 89% from 1970 to 2022, while total ischemic heart diseaseA condition in which reduced blood supply to the heart muscle, usually from coronary artery atherosclerosis, causes symptoms such as angina or myocardial infarction. mortality fell by 81% over the same period.26 A landmark analysis by Ford et al. (2007) decomposed the decline in U.S. coronary heart diseaseCoronary heart disease is the narrowing or blockage of the arteries that supply blood to the heart muscle, caused by the buildup of atherosclerotic plaque; it is the leading cause of heart attack and cardiac death worldwide. deaths between 1980 and 2000, attributing approximately 44% to risk factor reductions (predominantly smokingSmoking damages the lining of your blood vessels, raises blood pressure, makes blood clot more easily, and speeds up plaque growth. cessation, lower mean blood pressureBlood pressure is the force of blood pushing against your artery walls. It is written as two numbers, like 120/80. The top number is the pressure when your heart squeezes, the bottom is when it relaxes., and lower mean total cholesterol) and approximately 47% to improved medical and surgical treatments (including secondary prevention after MI, acute AMI treatments, and heart failureHeart failure means the heart cannot pump well enough to meet the body's needs. The name is misleading — it does not mean the heart has stopped. management).27
Table 5. Estimated Contributions to the Decline in U.S. Coronary Heart Disease Mortality, 1980–2000
| Factor | Estimated Contribution | Primary Mechanisms |
| Risk factor reductions | ~44% | Decline in smoking prevalence (~42% in 1965 to ~25% in 1995); lower mean systolic blood pressureSystolic blood pressure is the top number — the pressure in your arteries while your heart is squeezing.; lower mean total cholesterol. |
| Medical and surgical treatments | ~47% | Secondary prevention after MI (~11%); acute AMI treatments (thrombolytics, PCI) (~10%); heart failure management (~9%); coronary revascularizationRevascularization is a medical or surgical procedure—such as coronary artery bypass grafting or percutaneous coronary intervention—performed to restore blood flow through a blocked or narrowed coronary artery, addressing the physical obstruction rather than the underlying atherogenic process. (~5%). |
| Other / unexplained | ~9% | Including changes in physical activity, diet, and unmeasured confoundersA confounder is a variable that is associated with both the exposure being studied (such as TMAO) and the outcome (such as heart disease), making it appear as though one causes the other when a third factor is actually responsible. The article lists renal function, insulin resistance, systemic inflammation, and age as major confounders that inflate the apparent cardiovascular risk of high TMAO in…. |
Adapted from: Ford et al. N Engl J Med. 2007;356:2388–2398. MI = myocardial infarction; PCI = percutaneous coronary intervention.
However, a critical finding from the 2025 JAHA analysis reveals a concerning compositional shift: while deaths from acute myocardial infarction fell by 89%, mortality from non-ischemic heart conditions substantially increased. Deaths from heart failure rose by 146%, hypertensive heart disease by 106%, and arrhythmias by 450% over the study period.26 This pattern indicates that modern medicine has succeeded in preventing death from acute ischemic events—largely by converting them into survivable occurrences—but that the underlying atherosclerotic disease process, and the chronic organ damage that accrues over decades, continues largely unabated.26
Effectiveness of Statins: Relative Versus Absolute Risk Reduction
The success of statins is frequently expressed in terms of relative riskRelative risk compares two groups: this group had 30 percent fewer heart attacks than that group. reduction (RRR). A Cholesterol Treatment Trialists’ (CTT) Collaboration meta-analysis of data from 170,000 participants in 26 randomized trials demonstrated a consistent ~21% proportional reduction in major vascular events per 1.0 mmol/L (38.7 mg/dL) reduction in LDL-C.28
Absolute Risk Reductions and the NNT Debate
Despite consistent relative benefits, a 2022 systematic review and meta-analysis of 21 eligible randomized trials published in JAMA Internal Medicine by Byrne et al. demonstrated that absolute riskAbsolute risk is the real chance that something will happen to you, written as a percentage. If your absolute risk of a heart attack in the next ten years is 12 percent, that means about 12 out of every 100 people like you would have one. reductions (ARRs) are substantially more modest, particularly in primary prevention settings.29
Table 6. Relative Risk Reduction, Absolute Risk Reduction, and NNT for Statin Therapy (pooled primary and secondary prevention trials; mean follow-up 4.4 years)
| Outcome | Relative Risk Reduction (95% CI) | Absolute Risk Reduction (95% CI) | Number Needed to TreatNumber needed to treat, or NNT, is how many people must take a treatment for one of them to benefit. |
| All-cause mortalityAll-cause mortality means death from any cause at all, not just heart disease — the broadest, hardest-to-game outcome a study can measure. | 9% (5–14%) | 0.8% (0.4–1.2%) | ~125 |
| Myocardial infarction | 29% (22–34%) | 1.3% (0.9–1.7%) | ~77 |
| StrokeA stroke happens when blood flow to part of the brain stops, either from a blockage or from bleeding. | 14% (5–22%) | 0.4% (0.2–0.6%) | ~250 |
Source: Byrne P, et al. JAMA Intern Med. 2022;182:474–481. CI = confidence intervalA confidence interval is the range of values that are statistically compatible with what a study found.; NNT = number needed to treat (calculated from ARR).
This RRR/ARR discrepancy has fueled debate over the sufficiency of current lipid-lowering strategies, particularly in low-risk primary prevention populations where baseline event rates are low. However, the 2026 guideline framework advocates a ‘life-course’ perspective: while the 5-year ARR for a low-risk individual starting statin therapy in middle age may be modest, the cumulative prevention of atherosclerotic plaque burdenPlaque burden is the total amount of plaque in your arteries, everywhere — not just at the single worst spot. over 30–40 years could yield substantially larger lifetime benefits.1 The CTT CollaborationThe Cholesterol Treatment Trialists' Collaboration pools the raw data from every major statin trial rather than just comparing published summaries. has reinforced this point, demonstrating that the proportional risk reduction is consistent across all baseline risk levels, meaning individuals who initiate therapy earlier—when absolute risk is lower—may accumulate the greatest lifetime benefit.28
Critical Synthesis: Toward a Precision Prevention Paradigm
Current cholesterol-focused strategies have achieved historically unprecedented reductions in acute cardiovascular mortality, yet substantial gaps remain. The longstanding focus on 10-year risk estimation in middle-aged individuals frequently misidentifies those with high lifetime risk who could benefit from earlier intervention.1
Persistent Gaps in Current Models
Metabolic oversight remains a critical vulnerability: traditional LDL-C metrics systematically underestimate cardiovascular risk in individuals with insulin resistance or type 2 diabetes, who may have elevated atherogenic particle burdens (as reflected by ApoB) despite apparently ‘normal’ LDL-C.13 Genetic blind spots persist, as standard lipid panels have historically been unable to detect elevated Lp(a) or polygenic predispositions to high LDL-C.22 Furthermore, the shift from AMI mortality toward heart failure, hypertensive heart disease, and arrhythmias—documented in the 2025 JAHA analysis—indicates that contemporary medicine is managing the sequelae of atherosclerosis rather than eradicating the disease process early enough in the life course.26
The 2026 Framework: Precision, Biomarker Refinement, and Genomic Integration
The 2026 ACC/AHA Dyslipidemia Guideline represents a move toward ‘precision prevention.’ Key advances include earlier risk assessment (beginning at age 30), use of the PREVENT equations for both 10- and 30-year risk estimates, selective incorporation of ApoB to resolve LDL-C/particle discordance, and universal one-time Lp(a) testing.1 The guideline also endorses selective use of coronary artery calcium (CAC) scoringA non-contrast, ECG-gated CT scan that detects and quantifies calcified plaque in the coronary arteries; the resulting Agatston score reflects the extent of coronary calcification and serves as a direct, disease-based measure of atherosclerotic burden rather than a statistical estimate of risk. for risk reclassificationIn cardiovascular risk assessment, reclassification refers to the process by which an additional test — such as a CAC scan or ApoB measurement — moves a patient from one risk category to another, prompting a change in treatment decisions that a standard risk calculator alone would not have triggered. in individuals with borderline or intermediate 10-year risk.1
Table 7. Key Advances in the 2026 Precision Prevention Framework
| Advancement | Description | Impact on Risk Assessment |
| PREVENT Equations | 10- and 30-year risk tools incorporating kidney function (eGFR) and metabolic healthMetabolic health describes how well your body handles blood sugar, blood pressure, fats, and body fat storage.; replaces Pooled Cohort EquationsThe Pooled Cohort Equations are the risk calculator the American College of Cardiology and American Heart Association currently recommend, estimating your ten-year odds of a heart attack or stroke from age, cholesterol, blood pressure, diabetes, and smoking status., which overestimated 10-year risk by 40–50%. | Enables quantification of lifetime risk in younger adults (ages 30–79), facilitating early lifestyle and pharmacological intervention. |
| Selective ApoB Measurement | Quantifies total atherogenic particle burden; resolves LDL-C/ApoB discordanceA clinical pattern in which a patient's measured LDL cholesterol mass appears acceptable while the ApoB particle count is elevated, indicating more atherogenic particles than the cholesterol number alone would suggest; common in metabolic syndrome and hypertriglyceridemia.. | Identifies metabolically unhealthy individuals whose risk is systematically underestimated by LDL-C. |
| Universal Lp(a) Screening | One-time measurement recommended for all adults to detect inherited Lp(a) elevation. | Identifies the ~20–25% of the population with genetically elevated Lp(a) who carry residual riskResidual risk is the risk that remains after you have done the obvious things — cholesterol treated, blood pressure controlled, not smoking. not addressed by conventional therapy. |
| CAC Scoring | Selective use for risk reclassification in borderline- and intermediate-risk individuals. | Provides direct anatomic evidence of subclinical atherosclerosisSubclinical atherosclerosis means plaque is present but has not yet caused any symptoms or events. to guide statin initiation or de-intensification decisions. |
| Polygenic Risk Scores (PRS) | Combines thousands of common genetic variants into a composite cardiovascular disease risk score. | Reclassifies individuals with ‘borderline’ clinical risk to high-risk based on genetic susceptibility; incorporated into 2026 guideline narrative. |
Sources: Blumenthal et al. (2026); Khan et al. (2024); Khera et al. (2018).
In conclusion, the evolution of cardiovascular care since the 1960s has been a journey from managing crises to modifying biology. While the ‘average’ Western population remains at a pathologically elevated baseline, the tools available in 2026 allow for a level of personalized, life-course prevention that could theoretically render atherosclerotic events increasingly rare rather than the leading cause of death. Future research must prioritize cost-effectiveness and equitable scalability of advanced biomarker testing, as well as the long-term impact of ‘primordial’ prevention strategies aimed at maintaining LDL-C and ApoB at near-physiological levels throughout adult life.11014
References
- Writing Committee Members, Blumenthal RS, Morris PB, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. Published online March 13, 2026. doi:10.1161/CIR.0000000000001423
- Steinberg D. Thematic review series: the pathogenesis of atherosclerosis. An interpretive history of the cholesterol controversy: part I. J Lipid Res. 2004;45(9):1583-1593. doi:10.1194/jlr.R400003-JLR200
- Carroll MD, Lacher DA, Sorlie PD, et al. Trends in serum lipids and lipoproteins of adults, 1960-2002. JAMA. 2005;294(14):1773-1781. doi:10.1001/jama.294.14.1773
- Hooper L, Martin N, Jimoh OF, Kirk C, Foster E, Abdelhamid AS. Reduction in saturated fat intake for cardiovascular disease. Cochrane Database Syst Rev. 2020;5(5):CD011737. Published 2020 May 19. doi:10.1002/14651858.CD011737.pub2
- Report of the National Cholesterol Education Program Expert Panel on Detection, Evaluation, and Treatment of High Blood Cholesterol in Adults. The Expert Panel. Arch Intern Med. 1988;148(1):36-69.
- The Lipid Research Clinics Coronary Primary Prevention Trial results. I. Reduction in incidence of coronary heart disease. JAMA. 1984;251(3):351-364. doi:10.1001/jama.1984.03340270029025
- Baigent C, Keech A, Kearney PM, et al. Efficacy and safety of cholesterol-lowering treatment: prospective meta-analysis of data from 90,056 participants in 14 randomised trials of statins. Lancet. 2005;366(9493):1267-1278. doi:10.1016/S0140-6736(05)67394-1
- Stone NJ, Robinson JG, Lichtenstein AH, et al. 2013 ACC/AHA guideline on the treatment of blood cholesterol to reduce atherosclerotic cardiovascular risk in adults: a report of the American College of Cardiology/American Heart Association Task Force on Practice Guidelines. J Am Coll Cardiol. 2014;63(25 Pt B):2889-2934. doi:10.1016/j.jacc.2013.11.002
- Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Circulation. 2019;139(25):e1082-e1143. doi:10.1161/CIR.0000000000000625
- Ference BA, Ginsberg HN, Graham I, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease. 1. Evidence from genetic, epidemiologic, and clinical studies. A consensus statement from the European Atherosclerosis Society Consensus Panel. Eur Heart J. 2017;38(32):2459-2472. doi:10.1093/eurheartj/ehx144
- Reiner Ž. Hypertriglyceridaemia and risk of coronary artery disease. Nat Rev Cardiol. 2017;14(7):401-411. doi:10.1038/nrcardio.2017.31
- Carroll MD, Fryar CD, Gwira JA, Iniguez M. Total and High-density Lipoprotein Cholesterol in Adults: United States, August 2021-August 2023. NCHS Data Brief. 2024;(515):CS354900. doi:10.15620/cdc/165796
- Tsoupras A, Lordan R, Zabetakis I. Inflammation, not Cholesterol, Is a Cause of Chronic Disease. Nutrients. 2018;10(5):604. Published 2018 May 12. doi:10.3390/nu10050604
- Napoli C, Glass CK, Witztum JL, Deutsch R, D’Armiento FP, Palinski W. Influence of maternal hypercholesterolaemia during pregnancy on progression of early atherosclerotic lesions in childhood: Fate of Early Lesions in Children (FELIC) study. Lancet. 1999;354(9186):1234-1241. doi:10.1016/S0140-6736(99)02131-5
- Kaplan H, Thompson RC, Trumble BC, et al. Coronary atherosclerosis in indigenous South American Tsimane: a cross-sectional cohort study. Lancet. 2017;389(10080):1730-1739. doi:10.1016/S0140-6736(17)30752-3
- Ference BA, Graham I, Tokgozoglu L, Catapano AL. Impact of Lipids on Cardiovascular Health: JACC Health Promotion Series. J Am Coll Cardiol. 2018;72(10):1141-1156. doi:10.1016/j.jacc.2018.06.046
- Williams KJ, Tabas I. The response-to-retention hypothesis of early atherogenesis. Arterioscler Thromb Vasc Biol. 1995;15(5):551-561. doi:10.1161/01.atv.15.5.551
- Ivanova EA, Myasoedova VA, Melnichenko AA, Grechko AV, Orekhov AN. Small Dense Low-Density Lipoprotein as Biomarker for Atherosclerotic Diseases. Oxid Med Cell Longev. 2017;2017:1273042. doi:10.1155/2017/1273042
- Witt C, Renfroe LG, Lyons TS. Discordance between serum cholesterol concentration and atherogenic lipoprotein particle number in people with metabolic disease: A systematic review. Diabetes Obes Metab. 2025;27(6):2940-2954. doi:10.1111/dom.16335
- Pischon T, Girman CJ, Sacks FM, Rifai N, Stampfer MJ, Rimm EB. Non-high-density lipoprotein cholesterol and apolipoprotein B in the prediction of coronary heart disease in men. Circulation. 2005;112(22):3375-3383. doi:10.1161/CIRCULATIONAHA.104.532499
- Ivanova EA, Myasoedova VA, Melnichenko AA, Grechko AV, Orekhov AN. Small Dense Low-Density Lipoprotein as Biomarker for Atherosclerotic Diseases. Oxid Med Cell Longev. 2017;2017:1273042. doi:10.1155/2017/1273042
- Tsimikas S. A Test in Context: Lipoprotein(a): Diagnosis, Prognosis, Controversies, and Emerging Therapies. J Am Coll Cardiol. 2017;69(6):692-711. doi:10.1016/j.jacc.2016.11.042
- Kronenberg F, Mora S, Stroes ESG, et al. Lipoprotein(a) in atherosclerotic cardiovascular disease and aortic stenosis: a European Atherosclerosis Society consensus statement. Eur Heart J. 2022;43(39):3925-3946. doi:10.1093/eurheartj/ehac361
- Coassin S, Kronenberg F. Lipoprotein(a) beyond the kringle IV repeat polymorphism: The complexity of genetic variation in the LPA gene. Atherosclerosis. 2022;349:17-35. doi:10.1016/j.atherosclerosis.2022.04.003
- Perez AD, Simpson RJ Jr, Komé AM, Lopez ST. Emerging therapies targeting lipoprotein(a): Pharmacologic advances and future directions. J Pharmacol Exp Ther. 2025;392(12):103695. doi:10.1016/j.jpet.2025.103695
- King SJ, Wangdak Yuthok TY, Bacong AM, et al. Heart Disease Mortality in the United States, 1970 to 2022. J Am Heart Assoc. 2025;14(13):e038644. doi:10.1161/JAHA.124.038644
- Ford ES, Ajani UA, Croft JB, et al. Explaining the decrease in U.S. deaths from coronary disease, 1980-2000. N Engl J Med. 2007;356(23):2388-2398. doi:10.1056/NEJMsa053935
- Cholesterol Treatment Trialists’ (CTT) Collaboration, Baigent C, Blackwell L, et al. Efficacy and safety of more intensive lowering of LDL cholesterol: a meta-analysis of data from 170,000 participants in 26 randomised trials. Lancet. 2010;376(9753):1670-1681. doi:10.1016/S0140-6736(10)61350-5
- Byrne P, Demasi M, Jones M, Smith SM, O’Brien KK, DuBroff R. Evaluating the Association Between Low-Density Lipoprotein Cholesterol Reduction and Relative and Absolute Effects of Statin Treatment: A Systematic Review and Meta-analysis. JAMA Intern Med. 2022;182(5):474-481. doi:10.1001/jamainternmed.2022.0134

