
Is Atherosclerosis Biologically Eliminated at Ultra-Low Lifelong LDL Levels?
A Critical Evaluation of the “Zero-Risk” Hypothesis
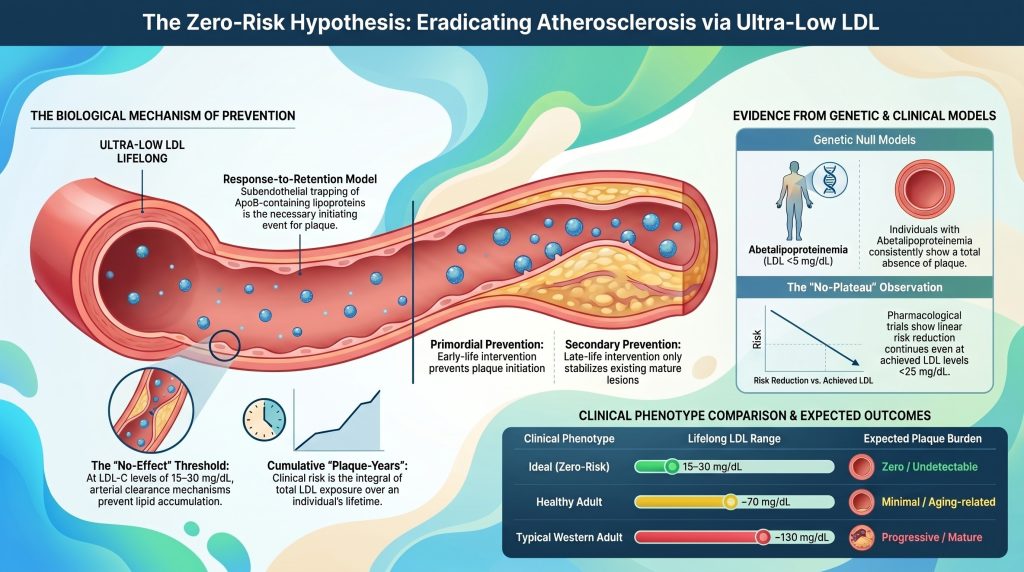
Atherosclerotic cardiovascular diseaseCardiovascular disease is the umbrella term for problems with the heart and blood vessels, including heart attacks, strokes, and blocked leg arteries. (ASCVD) has long been framed as an inevitable consequence of human senescence, yet contemporary molecular biology and genetic epidemiologyEpidemiology is the study of health patterns in large groups of people — who gets sick, where, and what they had in common. increasingly converge on a substrate-dependent model in which the disease is, in principle, biologically avoidable [1], [2]. The premise of the “zero-risk” hypothesis is that atherosclerosisAtherosclerosis is the disease behind most heart attacks and many strokes. Cholesterol particles get stuck in the wall of an artery, the body sends immune cells to clean up, and over years that mess hardens into plaque. is primarily an apolipoproteinAn apolipoprotein is a protein attached to a fat-carrying particle in your blood. Fat and water don't mix, so these proteins act like a wrapper that lets fat travel safely through the bloodstream. B (ApoBApoB is a protein that sits on the outside of every cholesterol particle that can get stuck in your artery wall and cause plaque. Each of those particles carries exactly one ApoB.)–driven disorder [2], [3]. By maintaining lifelong exposure to ultra-low levels of low-density lipoproteinA lipoprotein is a tiny package that carries fat and cholesterol through your bloodstream. Since fat won't dissolve in water, it needs a protein wrapper to travel. cholesterolCholesterol is a waxy substance your body needs. It goes into cell walls, hormones, vitamin D, and the bile that digests your food. You would die without it. (LDL-C) and its corresponding ApoB particle concentration—approximately 10–20 mg/dL (0.26–0.52 mmol/L), near the physiological newborn baseline—the probability of initiating the pathognomonicA pathognomonic sign is one so specifically characteristic of a particular disease that its presence alone is sufficient to confirm the diagnosis; in HoFH, cutaneous and tendon xanthomas appearing before age four are considered pathognomonic because they are caused by cholesterol spillover so extreme it is almost exclusively seen in this condition. lesionIn cardiology, a lesion refers to a discrete area of atherosclerotic plaque narrowing a coronary artery, typically described by the percentage of luminal obstruction it causes. The article describes four residual lesions too small in vessel diameter to accept a stent after the most critical one was treated. of atherosclerosis (subendothelial retentionSubendothelial retention is the process by which ApoB-containing lipoprotein particles that have crossed the endothelial barrier become electrostatically bound to proteoglycans in the arterial intima and are unable to diffuse back into the bloodstream; it is considered the non-redundant first step in atherosclerosis under the response-to-retention framework. of atherogenic lipoproteins) may be reduced to a level that is biologically negligible [2], [4]. This report evaluates whether such ultra-low exposure effectively eliminates disease initiation, or whether residual pathways involving inflammationInflammation is your immune system's response to injury or something it treats as an invader. It brings swelling, heat, and cleanup cells., lipoprotein(a)Lipoprotein(a), written Lp(a) and said "L-P-little-a," is an LDL-like particle with an extra sticky protein attached. [Lp(a)], and endothelial dysfunctionEndothelial dysfunction is when that thin lining stops doing its job well. Vessels don't widen properly, and the barrier gets leakier. retain the capacity to seed arterial plaqueA deposit within the artery wall made up of lipids, immune cells, cellular debris, and fibrous tissue that accumulates over time and can narrow or block blood flow; also called an atherosclerotic lesion or atheroma. independently of ApoB [5], [6].
The Response-to-Retention Model: A Deterministic Framework for Initiation
The theoretical basis for the biological elimination of atherosclerosis rests on the response-to-retention hypothesisThe response-to-retention hypothesis is the leading mechanistic account of early atherosclerosis, holding that the initiating event is the binding and trapping of apoB-containing lipoprotein particles to proteoglycans in the arterial intima, before inflammation or foam cell formation occurs., which identifies subendothelial trapping of ApoB-containing lipoproteins as the necessary and sufficient initiating event for atherogenesisAtherogenesis is the step-by-step process of a plaque forming. [1], [7]. While traditional models emphasized frank endothelial injury as the primary trigger, current evidence indicates that an intact, though dysfunctional, endotheliumThe endothelium is the ultra-thin, slippery lining on the inside of every blood vessel. It is only one cell thick. typically overlies early and intermediate lesions [1], [8]. Disease initiation occurs when lipoproteins smaller than approximately 70 nm in diameter—including LDLLDL, or low-density lipoprotein, is the main particle that carries cholesterol through your blood — and the main one that gets stuck in artery walls., triglyceride-rich remnants, and Lp(a)—traverse the endothelial barrier and enter the tunica intimaThe intima is the innermost layer of an artery wall, sitting just beneath the smooth lining. [2], [7].
Molecular Interactions within the Intimal Matrix
Within the intima, retained particles interact with the extracellular matrixThe extracellular matrix is the scaffolding of collagen and other fibers that holds tissue together and gives an artery wall its strength. (ECM), particularly with negatively charged proteoglycans such as versicanVersican is a large sulfated proteoglycan found in the arterial intima whose negatively charged glycosaminoglycan chains bind ionically to apoB-100 on lipoprotein particles, contributing to their retention in the artery wall as an early step in atherosclerosis., perlecan, biglycanBiglycan is a small leucine-rich proteoglycan present in the arterial subendothelial matrix that, along with versican and decorin, binds apoB-containing lipoprotein particles through ionic interactions, contributing to their retention in the intima as an initiating step in atherosclerosis., and decorin [1], [7]. Positively charged regions of ApoB, specifically sequences rich in lysine and arginineArginine is an amino acid found in whole foods such as walnuts that serves as the biochemical precursor the body uses to synthesize nitric oxide, thereby supporting endothelial relaxation and healthy blood vessel dilation. residues, bind electrostatically to the glycosaminoglycanGlycosaminoglycans are long, negatively charged sugar chains that are major components of the arterial extracellular matrix and plaque connective tissue; in cynomolgus macaque plaques they are prominent structural constituents that persist after regression of the lipid-rich components. (GAG) chains of these proteoglycans [1]. This is not passive entrapment; it is a critical biochemical event that prolongs the residence time of the lipoprotein within the arterial wall by an order of magnitude relative to plasma transit [9].
| Proteoglycan | Interaction with ApoB Lipoproteins | Role in Atherogenesis |
| Versican | Large aggregating proteoglycan that expands intimal volume | Promotes lipoprotein trapping and smooth muscle cellSmooth muscle cells make up the middle layer of an artery and control how much the vessel tightens or relaxes. migration [7] |
| Perlecan | Basement-membrane heparan sulfateHeparan sulfate is a negatively charged glycosaminoglycan, similar to chondroitin sulfate, found on proteoglycans in the arterial extracellular matrix; alongside chondroitin sulfate, it participates in the electrostatic binding of ApoB-100–containing lipoproteins that initiates plaque formation. proteoglycan | Structural scaffold facilitating early particle retention [7] |
| Biglycan | Small leucine-rich proteoglycan with high ApoB affinity | Correlates with development of lipid-rich necrotic coreThe lipid-rich necrotic core is the soft, fat- and inflammatory-cell-laden interior of an advanced atherosclerotic plaque; it is the most rupture-prone compartment and the one most responsive to lipid lowering, which can shrink and stabilize it even when surrounding calcified tissue remains. [7] |
| Decorin | Interacts with collagen and LDL particles | Modulates fibrotic response and lipoprotein aggregation [7] |
Prolonged intimal residence renders retained lipoproteins highly susceptible to chemical modification, including oxidation, glycation, enzymatic cleavage, and aggregation [1], [9]. Modified particles trigger a maladaptive immune response [1], [7]. Endothelial cellsThe thin layer of cells lining the inner surface of all blood vessels; they regulate vascular tone, prevent clotting, and control the passage of substances into the artery wall — and their dysfunction is an early, critical step in atherosclerosis. activated by modified lipids and mechanical stressors express adhesion molecules (VCAM-1VCAM-1 is a sticky molecule that appears on an inflamed vessel lining and grabs passing white blood cells so they can burrow into the wall., ICAM-1ICAM-1 is a molecule that appears on the surface of the blood vessel lining and acts like Velcro, catching passing immune cells.) and secrete chemokines that recruit monocytes into the subendothelial spaceThe subendothelial space is the narrow gap just beneath the artery's inner lining, between that single layer of cells and the muscle beneath. [1], [10]. These monocytes differentiate into macrophagesA macrophage is a large immune cell that swallows debris and invaders. The name literally means "big eater." that internalize modified lipoproteins via scavenger receptors and transform into lipid-laden foam cellsA foam cell is an immune cell that has eaten so much trapped cholesterol that it swells up and looks foamy under a microscope.—the morphological hallmark of the fatty streakA fatty streak is the earliest visible stage of atherosclerosis — a flat yellow smear of cholesterol-filled immune cells just under the artery lining. [10].
Thermodynamic and Kinetic Limits of Retention
The probability of particle retention is a function of the local concentration of ApoB particles and the availability of proteoglycan bindingProteoglycan binding is the electrochemical interaction by which positively charged lysine- and arginine-rich regions of ApoB latch onto the negatively charged glycosaminoglycan chains of intimal matrix proteins such as biglycan, versican, perlecan, and decorin. This binding dramatically prolongs the residence time of a lipoprotein particle within the artery wall, making it far more susceptible t… sites within the matrix [7]. In a stochastic model of the arterial wall, the rate of lipid accumulation is determined by the flux of lipoproteins into the intima and the kinetics of proteoglycan binding [9]. At ultra-low circulating concentrations (e.g., LDL-C ≈ 15 mg/dL), the number of particles available for transcytosisTranscytosis is the process by which a cell picks something up on one side, carries it across, and releases it on the other. is vastly reduced [2], [11].
If the rate of particle entry is low enough that the arterial wall’s endogenous clearance mechanisms—macrophage-mediated phagocytosis and HDL-mediated reverse cholesterol transportReverse cholesterol transport is the process of moving cholesterol out of tissues, including artery walls, and back to the liver for disposal. HDL particles do the hauling.—can remove particles before pro-inflammatory modification, the inflammatory cascade is never initiated [1], [12]. This is the mechanistic basis for a biological “no-effect” threshold for ApoB concentration, below which the probability of initiating a lesion approaches zero [7].
The Quantitative Relationship of Cumulative Exposure: Plaque-Years
Clinical risk of ASCVD reflects not instantaneous LDL-C but the integral of exposure over time, a concept now formalized as “cumulative LDL exposure” or “plaque-yearsPlaque-years is a measure of cumulative lifetime exposure to LDL cholesterol, calculated as the integral of LDL-C concentration over time (approximated as LDL-C × age), used to quantify the total atherogenic burden an artery wall has experienced. Research has identified heuristic thresholds—around 5,000 for low risk and above 14,000 for very high risk—that correspond to progressively greater prob…” [13], [14]. Under this framework, atherosclerosis is a disease of gradual substrate accumulation, and the time to a clinical event is determined by how quickly an individual crosses a personal plaque thresholdThe plaque threshold is the individual-specific cumulative level of atherogenic lipoprotein exposure at which enough lesion burden has accumulated to produce a clinically meaningful cardiovascular event such as a heart attack or stroke. Risk factors such as hypertension, diabetes, and smoking effectively lower this threshold, meaning events occur at a smaller cumulative exposure, while a metaboli… [13]. Domanski and colleagues formally demonstrated in a pooled analysis of 4,958 participants from ARICARIC, the Atherosclerosis Risk in Communities study, has followed thousands of American adults since the late 1980s., CARDIACARDIA has followed young adults from their twenties into later life, tracking fitness, cholesterol, blood pressure, and what eventually happened to them., MESAMESA, the Multi-Ethnic Study of Atherosclerosis, followed thousands of adults with no known heart disease, scanning their arteries and tracking outcomes., and the Framingham Offspring Study that the cumulative burden of LDL-C exposure, the time course of that exposure, and the slope of LDL-C change over time each independently predicted incident cardiovascular events [14].
Defining the Plaque-Year Thresholds
Analysis of epidemiologic and Mendelian randomizationMendelian randomization is a clever research method that uses the genes people were born with as a natural experiment. data permits tentative quantification of cumulative-exposure thresholds [13], [15]. Published thresholds remain approximate and cohort-dependent rather than formally validated across populations, and the values below are best regarded as heuristic estimates drawn from long-term cohort and Mendelian randomizationRandomization is the process of assigning trial participants to treatment or control groups by chance, ensuring that known and unknown confounding factors are evenly distributed; when randomization fails—as auditors found occurred in PREDIMED—the groups may differ in ways that distort the apparent treatment effect. data [13]–[15].
| Risk Metric (Men) | Approx. Cumulative LDL Exposure (g·yr/dL) | Lifetime Major Event Risk (approx.) |
| Low-Risk Threshold | ~ 5,000 | < 10% probability of event [13], [14] |
| Intermediate Threshold | ~ 8,000 | Approximate median age for non-zero CAC (~age 55–60) [13], [16] |
| High-Risk Threshold | ~ 11,000 | >20% probability of event [13], [14] |
| Very High-Risk Threshold | ~ 14,000 | Approximate median age for CAC ≥ 100 [13], [16] |
Note: Thresholds for women are generally higher (estimated by roughly 20–30% at comparable risk strata), consistent with the observed later-life onset of ASCVD in women and premenopausal attenuation of LDL transcytosis and arterial-wall biology [13].
Influence of Secondary Risk Factors on the Retention Threshold
Cumulative LDL exposure required to initiate events is not static; it is modulated by the biological environment of the arteryAn artery is a blood vessel that carries blood away from the heart to the rest of the body. [13]. HypertensionHypertension is the medical term for high blood pressure., diabetesDiabetes is a condition where blood sugar stays too high, either because the body makes too little insulin or because it stops responding to the insulin it makes., and smokingSmoking damages the lining of your blood vessels, raises blood pressure, makes blood clot more easily, and speeds up plaque growth. effectively lower the threshold by increasing particle retention or accelerating inflammatory response to retained lipids [2], [17].
- Hypertension: Elevated blood pressureBlood pressure is the force of blood pushing against your artery walls. It is written as two numbers, like 120/80. The top number is the pressure when your heart squeezes, the bottom is when it relaxes. increases LDL transcytosis across the endothelium and promotes synthesis of proteoglycans with higher ApoB affinity [7]. Shear stress on existing plaquesPlaque is the buildup of cholesterol, immune cells, scar tissue, and calcium inside an artery wall. raises rupture likelihood [13].
- Type 2 diabetes / insulin resistanceInsulin resistance is when your cells stop responding well to insulin, so your pancreas has to pump out more and more to do the same job.: Chronic dysglycemia and hyperinsulinemia injure the arterial wall, promote adverse remodeling, and narrow the coronary lumenThe lumen is the open channel inside a blood vessel where blood actually flows., so even small plaques become hemodynamically significant and thrombi more likely to be occlusive [14].
- Smoking: Tobacco exposure causes direct endothelial damage and oxidative stressOxidative stress is an imbalance between damaging reactive molecules and the body's ability to neutralize them., accelerating intimal lipoprotein modification [2].
- Androgen abuse: In young male anabolic-androgenic steroid users, plaque volumePlaque volume is the total physical amount of plaque in a stretch of artery, measured in cubic millimeters. and coronary artery calcium (CAC)Coronary artery calcium is a measure of calcified plaque deposits in the walls of the coronary arteries, quantified by CT scan and expressed as an Agatston score; higher scores indicate greater cumulative plaque burden and predict future cardiovascular events. scores correlate strongly with lifetime exposure, consistent with an independent acceleration of atherogenesis [18].
For a metabolically healthy individual with controlled blood pressure and no inflammatory comorbidity, the arterial wall can tolerate a higher cumulative burden before clinical disease manifests [13]. Under the zero-risk hypothesisThe zero-risk hypothesis proposes that atherosclerosis is not an inevitable consequence of aging but a substrate-dependent disease that requires sustained exposure to ApoB-containing lipoproteins to initiate; if lifelong circulating ApoB and LDL-C are kept near newborn baseline levels (roughly 10–20 mg/dL), the probability of initiating any atherosclerotic lesion approaches zero., maintaining LDL-C ≈ 15 mg/dL across an 80-year lifespan yields only ~1,200 g·yr/dL of cumulative exposureCumulative exposure is the total amount of harmful cholesterol particles your arteries have been soaked in across your entire life — how high, multiplied by how long.—well below the ~5,000 g·yr/dL heuristic low-risk threshold and roughly an order of magnitude below thresholds associated with clinically meaningful event probabilities [13].
Genetic Null Models: Experiments of Nature
The most rigorous test of whether atherosclerosis can be eliminated lies in human genetic models of lifelong ultra-low ApoB exposure [2], [3]. These “experiments of nature” provide the strongest available evidence that, in the near-absence of atherogenic particlesAtherogenic particles are the ApoB-containing lipoproteins—including LDL, IDL, VLDL, and lipoprotein(a)—that can enter and be retained in the artery wall to initiate and sustain plaque growth; the article uses the term to describe what must be lowered substantially and sustainably to achieve plaque regression., disease initiation is profoundly attenuated [19], [20]. Case-report numbers remain small and autopsy data are limited, so claims of “complete” absence should be interpreted as “markedly reduced burden beyond what is plausibly attributable to chance alone” rather than mathematically zero.
Abetalipoproteinemia (ABL) and MTTP Deficiency
Abetalipoproteinemia is an autosomal recessive disorder caused by biallelic loss-of-function mutations in MTTP, which is essential for assembly and secretion of ApoB-containing lipoproteins in the liver and intestine [19], [21]. Affected individuals have near-total absence of ApoB-containing lipoproteins in circulation; total cholesterolTotal cholesterol adds together the cholesterol in all your particles, harmful and helpful alike. is typically < 30 mg/dL and LDL-C < 5 mg/dL (often undetectable) [19].
Despite severe non-cardiac pathology (fat malabsorption, acanthocytosis, spinocerebellar degeneration, retinitis pigmentosa), clinical and limited autopsy evidence indicate a striking paucity of atherosclerotic lesions in ABL patients [19], [21]. CardiomyopathyCardiomyopathy is disease of the heart muscle itself, rather than of the arteries feeding it. and arrhythmias, when they occur, are attributed predominantly to fat-soluble vitamin deficiency (vitamin E) rather than ischemiaIschemia is when a tissue is not getting enough blood and oxygen for what it is being asked to do. [19]. ABL thus functions as the closest available human null model for ApoB-driven atherosclerosis.
Familial Hypobetalipoproteinemia (FHBL)
FHBL results from heterozygous or biallelic APOB mutations producing truncated, secretion-incompetent proteinsProtein is the nutrient your body uses to build and repair muscle and tissue. [22].
- Heterozygous FHBL: LDL-C typically 20–50 mg/dL, with markedly reduced lifetime ASCVD risk [22], [23].
- Homozygous / compound heterozygousCompound heterozygous describes a genetic state in which an individual inherits two different pathogenic mutations in the same gene—one from each parent—rather than two copies of the identical mutation; in HoFH, compound heterozygosity for two distinct LDLR mutations still abolishes or severely impairs LDL receptor function and produces the full HoFH phenotype. FHBL: LDL-C often < 10 mg/dL; phenotype resembles ABL and exhibits similarly marked protection against atherosclerotic disease on imaging and in available autopsy reports [22], [23].
| Genetic Disorder | Mechanism | LDL-C (mg/dL) | ASCVD Phenotype |
| Abetalipoproteinemia | MTTP LOF; no particle assembly | < 5 | Markedly reduced / absent plaque [19] |
| Homozygous FHBL | APOB LOF; truncated proteins | < 10 | Markedly reduced / absent plaque [22], [23] |
| PCSK9PCSK9 is a protein made by your liver that destroys the docking ports your liver uses to pull cholesterol out of your blood. LOF (compound het.) | Enhanced LDLRLDLR is the gene that builds the LDL receptor, the docking port your liver uses to pull cholesterol particles out of circulation. recycling; rapid LDL clearance | ~ 14–15 | Healthy phenotype; no documented ASCVD in index case [24] |
| ANGPTL3ANGPTL3 is a protein that slows the breakdown of triglyceride-rich particles in the blood. Deficiency | Increased LPL/EL activity; low TG and LDL | ~ 30–40 | Markedly reduced CAD (~34–41% lower odds) [25], [26] |
PCSK9 and ANGPTL3: The “Healthy” Ultra-Low Phenotype
Unlike ABL, which carries severe non-cardiac morbidity, loss-of-function variants in PCSK9 and ANGPTL3 produce ultra-low LDL-C without fat malabsorption or hepatic steatosis [3], [27]. The first reported compound heterozygous PCSK9 LOF individual, a healthy fertile African American woman described by Zhao and colleagues, had an LDL-C of approximately 14 mg/dL (0.36 mmol/L) and was clinically unremarkable, demonstrating that lifelong near-absence of circulating PCSK9 is compatible with normal human physiology [24]. In the Atherosclerosis Risk in Communities (ARIC) cohort, heterozygous PCSK9 LOF variants (PCSK9 Y142X and C679X) were associated with a 28% lower LDL-C and an 88% reduction in coronary heart diseaseCoronary heart disease is the narrowing or blockage of the arteries that supply blood to the heart muscle, caused by the buildup of atherosclerotic plaque; it is the leading cause of heart attack and cardiac death worldwide. incidence over approximately 15 years in Black participants, with a more modest ~47% reduction tied to PCSK9 R46L carriers in White participants [28]. Extended over a lifetime of exposure, the risk reduction approaches the near-complete protection observed in ABL and homozygous FHBL [2].
ANGPTL3 deficiency produces “combined hypolipidemia” with low LDL-C, HDL-C, and triglyceridesTriglycerides are the main form of fat in your blood and in your body's storage. [27]. In Stitziel’s 2017 analysis, three compound-heterozygous individuals had zero coronary plaque on CT angiography versus a mean 39% plaque burdenPlaque burden is the total amount of plaque in your arteries, everywhere — not just at the single worst spot. in matched relatives; heterozygous LOF carriers exhibited approximately 34% lower odds of coronary artery diseaseCoronary artery disease is plaque buildup in the arteries feeding the heart muscle. (OR 0.66; 95% CI 0.44–0.98) [25]. Dewey and colleagues replicated this signal in 58,335 DiscovEHR participants, reporting a 41% lower odds of CAD (OR 0.59; 95% CI 0.41–0.85; p = 0.004) [26]. Critically, quantitative imaging confirms that ANGPTL3 LOF carriers do not have increased hepatic fat, distinguishing this pathway as a favorable target for long-term pharmacological mimicry [27].
Pharmacologic Evidence: The “Lower Is Better” Paradigm
Genetic models speak to lifelong exposure; pharmacologic trials test the effect of lowering LDL-C later in life, typically in individuals with existing subclinical or clinical disease [2].
Meta-Regression and the Linearity of Benefit
Data from the Cholesterol Treatment Trialists (CTT) Collaboration and subsequent non-statin trials (ezetimibeEzetimibe is a pill that blocks your intestines from absorbing cholesterol., PCSK9 inhibitorsA PCSK9 inhibitor is a medicine that blocks that cholesterol-destroying protein, leaving more docking ports available to clear particles from the blood.) demonstrate a remarkably consistent dose-responseA dose-response relationship means more of something produces more of an effect, in a consistent gradient.: every 1 mmol/L (38.7 mg/dL) reduction in LDL-C corresponds to approximately a 22% reduction in major vascular events per year of treatment, with the relationship remaining linear even at the lowest achieved levels examined [29], [30]. This relationship is effectively agnostic to the mechanism by which LDL-C is lowered [15], [31].
| Clinical TrialA clinical trial is a study where researchers give one group a treatment and another group a placebo or standard care, then compare what happens. / Analysis | Achieved LDL-C (mg/dL) | Key Finding |
| CTT Meta-analysisA meta-analysis statistically combines the results of many separate studies into one overall estimate. | Range 60–180 | ~22% RR reduction per 1 mmol/L (38.7 mg/dL) [29] |
| IMPROVE-ITIMPROVE-IT added ezetimibe to a statin after a heart attack, testing whether lowering LDL by a non-statin mechanism would help. (ezetimibe + simvastatin) | 53.7 vs 69.5 (TWA) | HR 0.936 (0.89–0.99) for primary endpoint; benefit beyond statinA statin slows the enzyme your liver uses to make cholesterol. Your liver responds by pulling more cholesterol out of your blood, which is where the real benefit comes from. alone [30] |
| FOURIERFOURIER tested evolocumab, a PCSK9 inhibitor, in patients who already had cardiovascular disease and were on statins. (evolocumabEvolocumab is an injectable cholesterol medicine in the PCSK9 inhibitor family, usually given every two to four weeks.) | Median ~30 (subgroup <20) | Linear benefit continued to LDL-C < 20 mg/dL [32], [33] |
| ODYSSEYODYSSEY OUTCOMES tested alirocumab in patients recovering from a recent heart attack. OUTCOMES (alirocumabAlirocumab, sold as Praluent, is an injectable antibody that blocks PCSK9, given every two to four weeks.) | ~53 (48-wk mean) | HR 0.85 MACE; first mortality signal for PCSK9i (HR 0.85) [34] |
| PROLONG-ANG3 (solbinsiran) | Phase 2; sustained reduction | siRNA targeting ANGPTL3; durable ApoB and TG lowering [35] |
| CORALreef Lipids (enlicitide) | ~60 on background statin | Oral PCSK9 inhibitor; Phase 3 LDL-C reduction [36] |
The significance of these pharmacologic data lies in the “no-plateau” observation [32], [37]. Event reduction continues linearly even at achieved LDL-C below 20 mg/dL, suggesting that the biological drivers of atherosclerosis remain substrate-limited at the extremes of the lipid spectrum [2], [32].
Residual Disease versus New Initiation
A critical distinction must be drawn between primary and secondary preventionSecondary prevention is treating someone who has already had a heart attack, stroke, or stent, to stop the next one. [13]. Among trial participants achieving very low LDL-C, a meaningful fraction still experience events [38]. This residual riskResidual risk is the risk that remains after you have done the obvious things — cholesterol treated, blood pressure controlled, not smoking. is not a failure of the zero-risk hypothesis but rather the predictable consequence of the irreversible structural features of advanced plaque [2]. Once a lesion has developed a necrotic coreThe necrotic core is the dead, mushy center of an advanced plaque, built from immune cells that ate trapped cholesterol and then died in place. and a thinned fibrous capThe fibrous cap is the tough layer of tissue covering a plaque, separating its greasy core from the bloodstream., rupture can be triggered by local mechanical forces or systemic inflammation largely independent of current LDL-C [2], [39]. The zero-risk hypothesis concerns disease initiation, not terminal rupture of pre-existing plaque [1]. Were ultra-low lipoprotein levels maintained from birth, the substrate for acute events (mature, unstable plaqueAn unstable plaque is an atherosclerotic lesion with a thin fibrous cap, a large lipid-rich necrotic core, and active inflammation, making it prone to rupture even when it is not large enough to meaningfully restrict blood flow or cause symptoms.) would simply fail to form [2], [14].
Residual Risk Pathways: Can Inflammation or Lp(a) Initiate Disease Alone?
Falsifying the zero-risk hypothesis requires identifying a non-ApoB pathway capable of independently initiating atherosclerosis in the absence of atherogenic lipoproteins [5], [6].
Lipoprotein(a) and the Structural Necessity of ApoB
Lp(a) is a complex particle consisting of an LDL-like ApoB-100ApoB-100 is the full-length form of apolipoprotein B found on LDL, VLDL, IDL, and remnant lipoproteins; its positively charged amino-acid domains bind ionically to negatively charged proteoglycan side chains in the arterial wall, physically trapping the particle in the intima and initiating plaque formation. core covalently bound to apolipoprotein(a) [40]. It is independently associated with ASCVD risk even when LDL-C is optimally controlled [5]. Mechanistically, Lp(a) is more atherogenic than LDL on a per-particle basis because of its propensity for matrix binding and its cargo of oxidized phospholipids (OxPLs), which drive robust inflammation [40], [41]. Critically, however, every Lp(a) particle requires an ApoB-100 scaffold; in ABL and homozygous FHBL, Lp(a) cannot be synthesized because ApoB secretion is absent [19], [22]. Thus, Lp(a) does not represent a non-ApoB initiation pathway but a quantitatively more atherogenic subclass of the ApoB-containing lipoprotein family.
Inflammation as a Potentiator, Not an Initiator
The role of inflammation (IL-6Interleukin-6, or IL-6, is a signaling molecule the immune system uses to spread an inflammatory message through the body., IL-1β, hsCRP) in ASCVD is well established, and the CANTOS trialThe CANTOS (Canakinumab Anti-inflammatory Thrombosis Outcomes Study) trial was a landmark randomized controlled trial that tested whether canakinumab, an IL-1β inhibitor, could reduce cardiovascular events in high-risk patients with elevated hs-CRP after myocardial infarction; its positive results provided the first direct clinical evidence that inflammation is a causal, therapeutically modifiabl… demonstrated that canakinumab-mediated blockade of IL-1β reduces cardiovascular events without changing lipid levels [42]. Nevertheless, current consensus is that inflammation operates as a physiologic response of the arterial wall to retained lipoproteins rather than as an autonomous initiator [7]. In wild-type animal models, systemic inflammation does not generate atherosclerosis in the absence of hyperlipidemia [43]. Arterial-wall inflammation, monocyte recruitment, and foam-cell formation are downstream consequences of lipoprotein retention [1]. Chronic inflammatory diseases (e.g., rheumatoid arthritisRheumatoid arthritis is an autoimmune disease in which the immune system attacks the joints., SLE) lower the threshold for retention-driven lesion formation, but they do not initiate atherosclerosis where the ApoB substrate is absent [7].
Imaging the Ultra-Low End: Subclinical Evidence
Coronary artery calcium (CAC) scoringA non-contrast, ECG-gated CT scan that detects and quantifies calcified plaque in the coronary arteries; the resulting Agatston score reflects the extent of coronary calcification and serves as a direct, disease-based measure of atherosclerotic burden rather than a statistical estimate of risk., intravascular ultrasoundIntravascular ultrasound, or IVUS, uses a tiny ultrasound probe threaded inside a coronary artery to photograph the wall from within. (IVUS), optical coherence tomographyOptical coherence tomography, or OCT, threads a light-based probe into a coronary artery. It sees roughly ten times finer detail than ultrasound. (OCT), and coronary CT angiographyCoronary CT angiography, or CCTA, is a CT scan done with dye in your veins that produces detailed pictures of your heart's arteries. (CCTA) provide complementary windows into the presence and composition of subclinical plaque at extreme lipid strata [16], [44].
The Power of Zero CAC
A CAC score of zero is a robust marker of low short-term event risk, but its interpretation is age-dependent [16], [45]. In younger populations (age < 45), zero CAC is common even among those with significant LDL exposure because calcificationCalcification is when calcium gets deposited into a plaque, turning part of it hard and bony. is a late-stage stabilization marker [45]. Conversely, zero CAC in an elderly individual is uncommon and identifies exceptional resistance to atherogenesis, often associated with genetically low ApoB or favorable matrix biology [16], [46].
| CAC Category | Agatston UnitsAgatston units are the standardized scoring units used to quantify coronary artery calcium on a CT scan, calculated from the density and area of calcified lesions; a score of zero indicates no detectable calcified plaque, while scores of 300 or above — found exclusively in the athlete group in the UK Masters study — reflect heavy calcification. | Clinical Significance |
| Zero | 0 | No detectable calcification; very low short-term ASCVD risk [16] |
| Mild | 1–99 | Early atherosclerotic burden; supports risk up-classification [16] |
| Moderate | 100–399 | Significant plaque; 10-yr event risk typically exceeds 7.5% [16] |
| Severe | ≥ 400 | Very high risk; often treated as ASCVD equivalent [16] |
IVUS and the Threshold for Regression
Intravascular imaging trials consistently show that deep LDL-C lowering can reverse net plaque burden [47], [48]. The ASTEROID trialA landmark 2006 serial IVUS study in which rosuvastatin 40 mg daily for 24 months produced statistically significant reductions in both percent atheroma volume and total atheroma volume, providing the first large-scale evidence that intensive statin therapy can regress coronary plaque. achieved mean LDL-C of 60.8 mg/dL with rosuvastatinRosuvastatin, sold as Crestor, is the most potent statin available and stays largely in the liver rather than spreading through the body. 40 mg and demonstrated regression of percent atheroma volumePercent atheroma volume, or PAV, is the share of an artery segment taken up by plaque rather than open channel. (PAV) across multiple imaging parameters [47]. SATURNSATURN compared the two strongest statins head to head at maximum dose, measuring coronary plaque with intravascular ultrasound. corroborated regression at LDL-C in the 60–70 mg/dL range [48]. GLAGOVGLAGOV added a PCSK9 inhibitor to statin therapy and measured coronary plaque with intravascular ultrasound before and after. extended the relationship into the PCSK9-inhibitor era, showing continuous linear regression with evolocumab down to LDL-C < 40 mg/dL, with no apparent plateau [49].
- Regression: Reduction in PAV is observed consistently when LDL-C falls below ~70 mg/dL, with the magnitude of regression scaling with the depth of LDL-C reduction [47]–[49].
- Stabilization: At ultra-low levels, plaques undergo beneficial remodeling; the lipid-rich core shrinks and the fibrous cap thickens and becomes collagen-rich, converting a “vulnerable” lesion into a structurally stable one [49], [50].
Under the zero-risk hypothesis, early-life maintenance of LDL-C ≈ 15 mg/dL would prevent formation of the lipid-rich core entirely; regression and stabilization become moot because there is no lesion to regress [2].
Temporal Considerations: Early-Life Exposure versus Adult Intervention
The cumulative-exposure framework emphasizes that the age at which LDL lowering begins matters as much as its intensity [13].
The Window of Opportunity
Ference and colleagues’ landmark 2012 Mendelian randomization analysis pooled nine SNPs across six LDL-regulating genes and found that each standard unit of genetically lower LDL-C produced approximately a three-fold greater proportional reduction in coronary heart disease than the same magnitude of late-life statin-induced LDL-C lowering [15]. Specifically, lifelong exposure to ~1 mmol/L lower LDL-C was associated with roughly a 54–55% reduction in CHD risk, versus approximately a 22% relative riskRelative risk compares two groups: this group had 30 percent fewer heart attacks than that group. reduction per mmol/L with statin therapy initiated in midlife [15], [29]. This discrepancy arises because early intervention prevents lesion initiation, whereas late intervention merely slows progression of already-mature plaques [2], [14].
For a metabolically healthy individual:
- Maintaining LDL-C ≈ 15 mg/dL lifelong: Prevents plaque initiation; lifetime risk approaches zero [2], [15].
- Reducing LDL-C to ≈ 15 mg/dL at age 40: Halts further progression, stabilizes existing subclinical plaque, and delays clinical events by an estimated 10–20 years depending on baseline plaque burden [13], [14].
- Reducing LDL-C to ≈ 15 mg/dL after a clinical event: Reduces recurrence risk by stabilizing vulnerable plaquesA vulnerable plaque is one at high risk of cracking open: a thin cap, a large greasy core, active inflammation, and often outward bulging of the artery.; does not eliminate residual risk arising from irreversible structural damage [34], [50].
The biological primacy of primary—and ideally primordial—prevention follows directly: maintaining physiologic lipoprotein levels from the earliest stages of life avoids the transition from subclinical to clinically dangerous burden [3].
Theoretical and Mechanistic Limits: Stochastic versus Zero Risk
Is the elimination of atherosclerosis absolute, or does a biological floor persist?
Stochastic Retention at Extreme Lows
Atherosclerosis initiation is fundamentally a probabilistic process [7]. Even at LDL-C ≈ 15 mg/dL, an ApoB particle could in principle enter the arterial wall, bind a proteoglycan, and undergo oxidation [7]. However, the probability of enough such particles being retained in a single focal region to trigger a self-perpetuating inflammatory response becomes vanishingly small at ultra-low concentrations [7], [9].
Arterial-wall biology incorporates multiple fail-safe mechanisms:
- Resident scavenging: Healthy intimal macrophages can clear small quantities of modified lipoprotein without becoming foam cells or secreting pro-inflammatory cytokines [1].
- HDLHDL, or high-density lipoprotein, is the particle often called "good cholesterol." It picks up cholesterol from tissues and carries it back to the liver./ApoA-I efflux: HDL functions as a bidirectional lipid vector capable of removing excess cholesterol from the intima; at low ApoB influx, efflux capacity easily maintains homeostatic balance [8], [51].
- Matrix integrity: In the absence of sustained lipid retention, the intima remains thin and structurally intact, with preserved elastic fibersFiber is the part of plant food your body cannot digest. It is found in beans, oats, vegetables, fruit, and whole grains. and minimal proteoglycan expansion [9].
At the zero-risk target of LDL-C ≈ 15 mg/dL, the probability of plaque initiation may not be mathematically zero but is effectively zero in biological and clinical terms: accumulation would never reach the critical mass required for disease within a human lifespan [2], [14]. The Horus studyThe Horus study used CT imaging to assess 137 mummies from four ancient populations spanning more than 4,000 years, finding probable or definite atherosclerosis in 34 percent, demonstrating that arterial disease predates modern industrialized diet and lifestyle. of 137 mummies across 4,000 years of history—including Tsimane-like pre-industrial and ancient peoples—documents vascular calcification in every era examined, but notably, pre-industrial populations with very low LDL-C (e.g., the contemporary TsimaneThe Tsimane are an indigenous forager-horticulturalist population of the Bolivian Amazon whose traditional lifestyle—characterized by high physical activity and low average LDL cholesterol of around 91 mg/dL—is associated with markedly low rates of coronary calcification, with 85 percent of adults over 40 showing no detectable coronary calcium., with mean LDL-C ~91 mg/dL and the lowest prevalence of coronary atherosclerosis measured in any human population) exhibit only low rates of subclinical CAC even in the elderly [52], [53]. Extrapolating to lifelong LDL-C of 15 mg/dL implies burden far below even this baseline.
Synthesis of the Zero-Risk Hypothesis Outcomes
Three hypothesis variants can be tested against the evidence reviewed above.
Strong Form: Zero-Risk Hypothesis
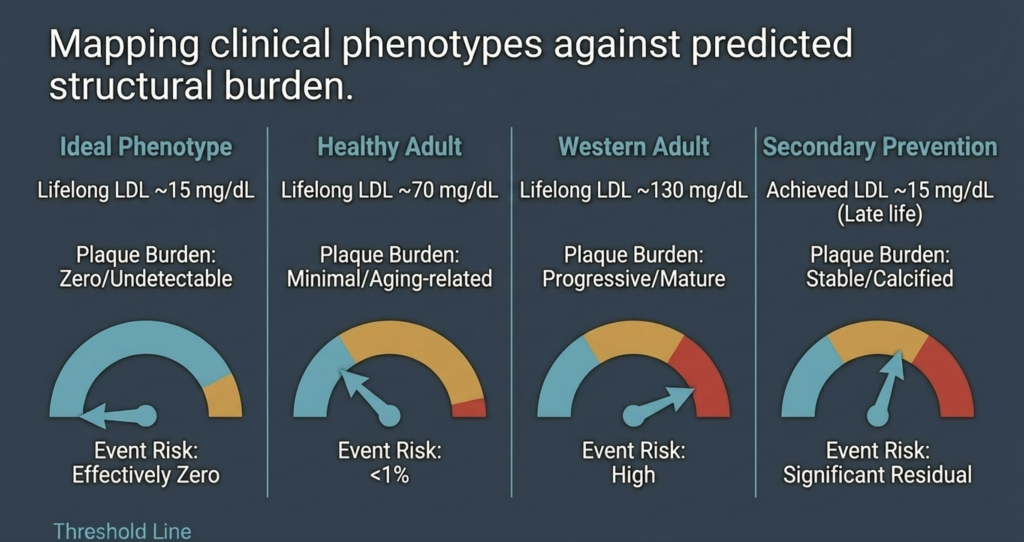
Lifelong LDL-C ≈ 15 mg/dL in a metabolically healthy individual produces effectively zero probability of clinically meaningful atherosclerosis. Evaluation: supported by human genetic null models (ABL, homozygous FHBL) where atherosclerotic burden is markedly reduced or absent [19], [22], by the physiologic newborn LDL-C baseline, and by the consistent absence of events in ultra-low-exposure genetic cohorts [2], [24].
Weak Form: Asymptotic Hypothesis
Risk approaches zero but never fully reaches it because of stochastic retention or non-ApoB pathways. Evaluation: supported by the fundamentally probabilistic nature of particle–wall interactions [7]. Extreme age or severe systemic inflammation could, in principle, cause minimal intimal changes, though such lesions would likely remain subclinical across the human lifespan [7].
Null Hypothesis
Atherosclerosis still occurs at meaningful rates independent of LDL at very low levels. Evaluation: refuted for the ideal phenotype [2], [15]. Residual risk observed in treated secondary-prevention populations is consistently attributable to pre-existing plaque and to non-LDL ApoB-containing particlesLipoproteins—including LDL, IDL, VLDL, and their remnants—that each carry one molecule of apolipoprotein B on their surface; particle number (rather than cholesterol mass alone) is a key driver of atherosclerosis because each particle can be retained in the arterial wall. (triglyceride-rich remnants and Lp(a)) rather than to a non-ApoB mechanism of initiation [5], [40].
| Clinical Phenotype | Expected Plaque Burden | Event Risk Probability |
| Ideal phenotype (lifelong LDL-C ~15 mg/dL) | Zero / undetectable | Effectively zero [15] |
| Healthy adult (lifelong LDL-C ~70 mg/dL) | Minimal / aging-related | Low (~5–10%) [14] |
| Western adult (lifelong LDL-C ~130 mg/dL) | Progressive / mature | High [2], [14] |
| Secondary prevention (achieved LDL-C ~15 mg/dL) | Stable / calcified | Significant residual [34] |
Conclusion: Redefining the Threshold of Human Health
The evaluation of the zero-risk hypothesis supports the view that atherosclerosis is a substrate-dependent disease requiring a minimum lifelong cumulative exposure to ApoB-containing lipoproteins to initiate [2], [14]. The quantitative relationship between cumulative exposure and plaque formation implies that maintaining LDL-C in the 10–20 mg/dL range from birth delays disease initiation beyond the biological limits of human longevity [13], [15].
Genetic models (abetalipoproteinemia, homozygous FHBL, and healthy ultra-low phenotypes from PCSK9 and ANGPTL3 loss of function) demonstrate that such low levels are both safe and compatible with a marked reduction—and in some cases apparent absence—of atherosclerotic plaque, acknowledging that case numbers remain limited [19], [22], [24], [25]. While residual risks driven by Lp(a), remnants, and inflammation persist in patients with mature disease, these factors are insufficient to initiate atherogenesis in the near-total absence of ApoB particles [2], [40].
The implication for preventive cardiology is substantial [3]. Rather than managing risk as an inevitable consequence of aging, the proper objective is primordial preventionPrimordial prevention is a strategy aimed at stopping the development of cardiovascular risk factors in the first place—rather than treating risk factors or existing disease—by keeping atherogenic exposures near zero from birth or early life. It is distinguished from primary prevention, which targets people who already have risk factors but no clinical disease.: maintaining physiologic lipoprotein levels throughout the earliest stages of life to eliminate the substrate for atherogenesis [2], [15]. This paradigm suggests that heart disease—the leading cause of death worldwide—is biologically eradicable if ApoB particle retention is prevented throughout the human lifespan [2], [14].
References
- J. Borén, M. J. Chapman, R. M. Krauss, C. J. Packard, J. F. Bentzon, C. J. Binder, M. J. Daemen, L. L. Demer, R. A. Hegele, S. J. Nicholls, B. G. Nordestgaard, G. F. Watts, E. Bruckert, S. Fazio, B. A. Ference, I. Graham, J. D. Horton, U. Landmesser, U. Laufs, L. Masana, G. Pasterkamp, F. J. Raal, K. K. Ray, H. Schunkert, M.-R. Taskinen, B. van de Sluis, O. Wiklund, L. Tokgözoğlu, A. L. Catapano, and H. N. Ginsberg, “Low-density lipoproteins cause atherosclerotic cardiovascular disease: pathophysiological, genetic, and therapeutic insights—a consensus statement from the European Atherosclerosis Society Consensus Panel,” Eur. Heart J., vol. 41, no. 24, pp. 2313–2330, Jun. 2020, doi: 10.1093/eurheartj/ehz962.
- B. A. Ference, H. N. Ginsberg, I. Graham, K. K. Ray, C. J. Packard, E. Bruckert, R. A. Hegele, R. M. Krauss, F. J. Raal, H. Schunkert, G. F. Watts, J. Borén, S. Fazio, J. D. Horton, L. Masana, S. J. Nicholls, B. G. Nordestgaard, B. van de Sluis, M.-R. Taskinen, L. Tokgözoğlu, U. Landmesser, U. Laufs, O. Wiklund, J. K. Stock, M. J. Chapman, and A. L. Catapano, “Low-density lipoproteins cause atherosclerotic cardiovascular disease. 1. Evidence from genetic, epidemiologic, and clinical studies,” Eur. Heart J., vol. 38, no. 32, pp. 2459–2472, Aug. 2017, doi: 10.1093/eurheartj/ehx144.
- A. L. Catapano, I. Graham, G. De Backer, O. Wiklund, M. J. Chapman, H. Drexel, A. W. Hoes, C. S. Jennings, U. Landmesser, T. R. Pedersen, Ž. Reiner, G. Riccardi, M.-R. Taskinen, L. Tokgözoğlu, W. M. M. Verschuren, P. Vlachopoulos, D. A. Wood, and J. L. Zamorano, “2016 ESC/EAS guidelines for the management of dyslipidaemias,” Eur. Heart J., vol. 37, no. 39, pp. 2999–3058, Oct. 2016, doi: 10.1093/eurheartj/ehw272.
- J. H. O’Keefe, L. Cordain, W. H. Harris, R. M. Moe, and R. Vogel, “Optimal low-density lipoprotein is 50 to 70 mg/dl: lower is better and physiologically normal,” J. Am. Coll. Cardiol., vol. 43, no. 11, pp. 2142–2146, Jun. 2004, doi: 10.1016/j.jacc.2004.03.046.
- B. G. Nordestgaard, M. J. Chapman, K. Ray, J. Borén, F. Andreotti, G. F. Watts, H. Ginsberg, P. Amarenco, A. Catapano, O. S. Descamps, E. Fisher, P. T. Kovanen, J. A. Kuivenhoven, P. Lesnik, L. Masana, Z. Reiner, M. R. Taskinen, L. Tokgözoğlu, and A. Tybjærg-Hansen, “Lipoprotein(a) as a cardiovascular risk factor: current status,” Eur. Heart J., vol. 31, no. 23, pp. 2844–2853, Dec. 2010, doi: 10.1093/eurheartj/ehq386.
- B. G. Nordestgaard and A. Varbo, “Triglycerides and cardiovascular disease,” Lancet, vol. 384, no. 9943, pp. 626–635, Aug. 2014, doi: 10.1016/S0140-6736(14)61177-6.
- I. Tabas, K. J. Williams, and J. Borén, “Subendothelial lipoprotein retention as the initiating process in atherosclerosis: update and therapeutic implications,” Circulation, vol. 116, no. 16, pp. 1832–1844, Oct. 2007, doi: 10.1161/CIRCULATIONAHA.106.676890.
- P. Libby, “The changing landscape of atherosclerosis,” Nature, vol. 592, no. 7855, pp. 524–533, Apr. 2021, doi: 10.1038/s41586-021-03392-8.
- D. C. Schwenke and T. E. Carew, “Initiation of atherosclerotic lesions in cholesterol-fed rabbits. II. Selective retention of LDL vs. selective increases in LDL permeability in susceptible sites of arteries,” Arteriosclerosis, vol. 9, no. 6, pp. 908–918, Nov./Dec. 1989, doi: 10.1161/01.atv.9.6.908.
- R. Ross, “Atherosclerosis—an inflammatory disease,” N. Engl. J. Med., vol. 340, no. 2, pp. 115–126, Jan. 1999, doi: 10.1056/NEJM199901143400207.
- F. Mach, C. Baigent, A. L. Catapano, K. C. Koskinas, M. Casula, L. Badimon, M. J. Chapman, G. G. De Backer, V. Delgado, B. A. Ference, I. M. Graham, A. Halliday, U. Landmesser, B. Mihaylova, T. R. Pedersen, G. Riccardi, D. J. Richter, M. S. Sabatine, M.-R. Taskinen, L. Tokgözoğlu, and O. Wiklund, “2019 ESC/EAS guidelines for the management of dyslipidaemias: lipid modification to reduce cardiovascular risk,” Eur. Heart J., vol. 41, no. 1, pp. 111–188, Jan. 2020, doi: 10.1093/eurheartj/ehz455.
- A. R. Tall and L. Yvan-Charvet, “Cholesterol, inflammation and innate immunity,” Nat. Rev. Immunol., vol. 15, no. 2, pp. 104–116, Feb. 2015, doi: 10.1038/nri3793.
- J. Brandts and K. K. Ray, “The LDL cumulative exposure hypothesis: evidence and practical applications,” Nat. Rev. Cardiol., vol. 21, no. 9, pp. 600–608, Sep. 2024, doi: 10.1038/s41569-024-01039-5.
- M. J. Domanski, X. Tian, C. O. Wu, J. P. Reis, A. K. Dey, Y. Gu, L. Zhao, S. Bae, K. Liu, A. A. Hasan, D. Zimrin, M. R. Farkouh, A. R. Hong, D. M. Lloyd-Jones, and V. Fuster, “Time course of LDL cholesterol exposure and cardiovascular disease event risk,” J. Am. Coll. Cardiol., vol. 76, no. 13, pp. 1507–1516, Sep. 2020, doi: 10.1016/j.jacc.2020.07.059.
- B. A. Ference, W. Yoo, I. Alesh, N. Mahajan, K. K. Mirowska, A. Mewada, J. Kahn, L. Afonso, K. A. Williams, and J. M. Flack, “Effect of long-term exposure to lower low-density lipoprotein cholesterol beginning early in life on the risk of coronary heart disease: a Mendelian randomization analysis,” J. Am. Coll. Cardiol., vol. 60, no. 25, pp. 2631–2639, Dec. 2012, doi: 10.1016/j.jacc.2012.09.017.
- R. Detrano, A. D. Guerci, J. J. Carr, D. E. Bild, G. Burke, A. R. Folsom, K. Liu, S. Shea, M. Szklo, D. A. Bluemke, D. H. O’Leary, R. Tracy, K. Watson, N. D. Wong, and R. A. Kronmal, “Coronary calcium as a predictor of coronary events in four racial or ethnic groups,” N. Engl. J. Med., vol. 358, no. 13, pp. 1336–1345, Mar. 2008, doi: 10.1056/NEJMoa072100.
- S. Yusuf, S. Hawken, S. Ôunpuu, T. Dans, A. Avezum, F. Lanas, M. McQueen, A. Budaj, P. Pais, J. Varigos, and L. Lisheng, “Effect of potentially modifiable risk factors associated with myocardial infarction in 52 countries (the INTERHEART study): case-control study,” Lancet, vol. 364, no. 9438, pp. 937–952, Sep. 2004, doi: 10.1016/S0140-6736(04)17018-9.
- A. L. Baggish, R. B. Weiner, G. Kanayama, J. I. Hudson, M. H. Picard, A. M. Hutter Jr., and H. G. Pope Jr., “Cardiovascular toxicity of illicit anabolic-androgenic steroid use,” Circulation, vol. 135, no. 21, pp. 1991–2002, May 2017, doi: 10.1161/CIRCULATIONAHA.116.026945.
- A. J. Hooper, B. A. Burnett, and J. R. Burnett, “Abetalipoproteinemia,” GeneReviews® [Internet], Univ. of Washington, Seattle, updated Jul. 2023. [Online]. Available: https://www.ncbi.nlm.nih.gov/books/NBK532447/.
- J. C. Cohen, E. Boerwinkle, T. H. Mosley Jr., and H. H. Hobbs, “Sequence variations in PCSK9, low LDL, and protection against coronary heart disease,” N. Engl. J. Med., vol. 354, no. 12, pp. 1264–1272, Mar. 2006, doi: 10.1056/NEJMoa054013.
- M. M. Berriot-Varoqueaux, L. P. Aggerbeck, M. Samson-Bouma, and J. R. Wetterau, “The role of the microsomal triglyceride transfer protein in abetalipoproteinemia,” Annu. Rev. Nutr., vol. 20, pp. 663–697, 2000, doi: 10.1146/annurev.nutr.20.1.663.
- S. G. Young and A. J. Hooper, “APOB-related familial hypobetalipoproteinemia,” GeneReviews® [Internet], Univ. of Washington, Seattle, updated Feb. 2021. [Online]. Available: https://www.ncbi.nlm.nih.gov/books/NBK570370/.
- L. Tarugi, E. Averna, E. Di Leo, A. Cefalù, D. Noto, S. Magnolo, M. Cattin, S. Bertolini, and M. Calandra, “Molecular diagnosis of hypobetalipoproteinemia: an ENID review,” Atherosclerosis, vol. 195, no. 2, pp. e19–e27, Dec. 2007, doi: 10.1016/j.atherosclerosis.2007.05.003.
- Z. Zhao, Y. Tuakli-Wosornu, T. A. Lagace, L. Kinch, N. V. Grishin, J. D. Horton, J. C. Cohen, and H. H. Hobbs, “Molecular characterization of loss-of-function mutations in PCSK9 and identification of a compound heterozygote,” Am. J. Hum. Genet., vol. 79, no. 3, pp. 514–523, Sep. 2006, doi: 10.1086/507488.
- N. O. Stitziel, A. V. Khera, X. Wang, A. J. Bierhals, A. C. Vourakis, A. E. Sperry, P. Natarajan, D. Klarin, C. A. Emdin, S. M. Zekavat, A. Nomura, J. Erdmann, H. Schunkert, N. J. Samani, W. E. Kraus, S. H. Shah, B. Yu, E. Boerwinkle, D. J. Rader, N. Gupta, P. M. Frossard, A. Rasheed, J. Danesh, E. S. Lander, S. Gabriel, D. Saleheen, K. Musunuru, and S. Kathiresan, “ANGPTL3 deficiency and protection against coronary artery disease,” J. Am. Coll. Cardiol., vol. 69, no. 16, pp. 2054–2063, Apr. 2017, doi: 10.1016/j.jacc.2017.02.030.
- F. E. Dewey, V. Gusarova, R. L. Dunbar, C. O’Dushlaine, C. Schurmann, O. Gottesman, S. McCarthy, C. V. Van Hout, S. Bruse, H. M. Dansky, J. B. Leader, M. F. Murray, M. D. Ritchie, H. L. Kirchner, D. H. Ledbetter, J. Penn, A. Lopez, I. B. Borecki, J. D. Overton, J. G. Reid, D. J. Carey, A. J. Murphy, G. D. Yancopoulos, A. Baras, J. Gromada, and A. R. Shuldiner, “Genetic and pharmacologic inactivation of ANGPTL3 and cardiovascular disease,” N. Engl. J. Med., vol. 377, no. 3, pp. 211–221, Jul. 2017, doi: 10.1056/NEJMoa1612790.
- K. Musunuru, J. P. Pirruccello, R. Do, G. M. Peloso, C. Guiducci, C. Sougnez, K. V. Garimella, S. Fisher, J. Abreu, A. J. Barry, T. Fennell, E. Banks, L. Ambrogio, K. Cibulskis, A. Kernytsky, E. Gonzalez, N. Rudzicz, J. C. Engert, M. A. DePristo, M. J. Daly, J. C. Cohen, H. H. Hobbs, D. Altshuler, G. Schonfeld, S. B. Gabriel, P. Yue, and S. Kathiresan, “Exome sequencing, ANGPTL3 mutations, and familial combined hypolipidemia,” N. Engl. J. Med., vol. 363, no. 23, pp. 2220–2227, Dec. 2010, doi: 10.1056/NEJMoa1002926.
- C. Baigent, L. Blackwell, J. Emberson, L. E. Holland, C. Reith, N. Bhala, R. Peto, E. H. Barnes, A. Keech, J. Simes, and R. Collins (Cholesterol Treatment Trialists’ Collaboration), “Efficacy and safety of more intensive lowering of LDL cholesterol: a meta-analysis of data from 170,000 participants in 26 randomised trials,” Lancet, vol. 376, no. 9753, pp. 1670–1681, Nov. 2010, doi: 10.1016/S0140-6736(10)61350-5.
- Cholesterol Treatment Trialists’ (CTT) Collaboration, “Efficacy and safety of LDL-lowering therapy among men and women: meta-analysis of individual data from 174 000 participants in 27 randomised trials,” Lancet, vol. 385, no. 9976, pp. 1397–1405, Apr. 2015, doi: 10.1016/S0140-6736(14)61368-4.
- C. P. Cannon, M. A. Blazing, R. P. Giugliano, A. McCagg, J. A. White, P. Theroux, H. Darius, B. S. Lewis, T. O. Ophuis, J. W. Jukema, G. M. De Ferrari, W. Ruzyllo, P. De Lucca, K. Im, E. A. Bohula, C. Reist, S. D. Wiviott, A. M. Tershakovec, T. A. Musliner, E. Braunwald, and R. M. Califf, “Ezetimibe added to statin therapy after acute coronary syndromes,” N. Engl. J. Med., vol. 372, no. 25, pp. 2387–2397, Jun. 2015, doi: 10.1056/NEJMoa1410489.
- J. Silverman, L. A. Ballantyne, D. A. Bhatt, S. D. Wiviott, M. S. Sabatine, and Cholesterol Treatment Trialists, “Association between lowering LDL-C and cardiovascular risk reduction among different therapeutic interventions: a systematic review and meta-analysis,” JAMA, vol. 316, no. 12, pp. 1289–1297, Sep. 2016, doi: 10.1001/jama.2016.13985.
- M. S. Sabatine, R. P. Giugliano, A. C. Keech, N. Honarpour, S. D. Wiviott, S. A. Murphy, J. F. Kuder, H. Wang, T. Liu, S. M. Wasserman, P. S. Sever, and T. R. Pedersen, “Evolocumab and clinical outcomes in patients with cardiovascular disease,” N. Engl. J. Med., vol. 376, no. 18, pp. 1713–1722, May 2017, doi: 10.1056/NEJMoa1615664.
- R. P. Giugliano, T. R. Pedersen, A. C. Keech, A. Park, S. D. Wiviott, S. A. Murphy, J. F. Kuder, H. Wang, T. Liu, J. Lopez, and M. S. Sabatine, “Clinical efficacy and safety of achieving very low LDL-cholesterol concentrations with the PCSK9 inhibitor evolocumab: a prespecified secondary analysis of the FOURIER trial,” Lancet, vol. 390, no. 10106, pp. 1962–1971, Oct. 2017, doi: 10.1016/S0140-6736(17)32290-0.
- G. G. Schwartz, P. G. Steg, M. Szarek, D. L. Bhatt, V. A. Bittner, R. Diaz, J. M. Edelberg, S. G. Goodman, C. Hanotin, R. A. Harrington, J. W. Jukema, G. Lecorps, K. W. Mahaffey, A. Moryusef, R. Pordy, K. Quintero, M. T. Roe, W. J. Sasiela, J.-F. Tamby, P. Tricoci, H. D. White, A. M. Zeiher, and ODYSSEY OUTCOMES Committees and Investigators, “Alirocumab and cardiovascular outcomes after acute coronary syndrome,” N. Engl. J. Med., vol. 379, no. 22, pp. 2097–2107, Nov. 2018, doi: 10.1056/NEJMoa1801174.
- C. M. Ballantyne, J. P. Kastelein, L. A. Leiter, S. J. Nicholls, and colleagues, “Durability and efficacy of solbinsiran, a GalNAc-conjugated siRNA targeting ANGPTL3, in adults with mixed dyslipidaemia (PROLONG-ANG3): a double-blind, randomised, placebo-controlled, phase 2 trial,” Lancet, 2025 (advance online publication).
- S. J. Nicholls, C. M. Ballantyne, and colleagues (CORALreef Lipids Investigators), “Efficacy and safety of enlicitide, an oral PCSK9 inhibitor, in adults with hypercholesterolemia: the Phase 3 CORALreef Lipids trial,” N. Engl. J. Med., 2025 (publication pending).
- M. Bhandari, S. M. Nissen, and colleagues, “How low can you go? New evidence supports no lower bound to low-density lipoprotein cholesterol level in secondary prevention,” Circulation, vol. 147, no. 19, pp. 1433–1435, May 2023, doi: 10.1161/CIRCULATIONAHA.123.064041.
- P. M. Ridker, N. Mora, L. Rose, and JUPITER Trial Study Group, “Percent reduction in LDL cholesterol following high-intensity statin therapy: potential implications for guidelines and for the prescription of emerging lipid-lowering agents,” Eur. Heart J., vol. 37, no. 17, pp. 1373–1379, May 2016, doi: 10.1093/eurheartj/ehw046.
- P. Libby, P. M. Ridker, and G. K. Hansson, “Progress and challenges in translating the biology of atherosclerosis,” Nature, vol. 473, no. 7347, pp. 317–325, May 2011, doi: 10.1038/nature10146.
- S. Tsimikas, “A test in context: lipoprotein(a): diagnosis, prognosis, controversies, and emerging therapies,” J. Am. Coll. Cardiol., vol. 69, no. 6, pp. 692–711, Feb. 2017, doi: 10.1016/j.jacc.2016.11.042.
- S. Tsimikas, H.-K. Gordts, C. Nora, C. Yeang, and J. L. Witztum, “Statin therapy increases lipoprotein(a) levels,” Eur. Heart J., vol. 41, no. 24, pp. 2275–2284, Jun. 2020, doi: 10.1093/eurheartj/ehz310.
- P. M. Ridker, B. M. Everett, T. Thuren, J. G. MacFadyen, W. H. Chang, C. Ballantyne, F. Fonseca, J. Nicolau, W. Koenig, S. D. Anker, J. J. P. Kastelein, J. H. Cornel, P. Pais, D. Pella, J. Genest, R. Cifkova, A. Lorenzatti, T. Forster, Z. Kobalava, L. Vida-Simiti, M. Flather, H. Shimokawa, H. Ogawa, M. Dellborg, P. R. F. Rossi, R. P. T. Troquay, P. Libby, R. J. Glynn, and CANTOS Trial Group, “Antiinflammatory therapy with canakinumab for atherosclerotic disease,” N. Engl. J. Med., vol. 377, no. 12, pp. 1119–1131, Sep. 2017, doi: 10.1056/NEJMoa1707914.
- A. Daugherty, S. E. Tall, M. J. Daemen, E. Falk, E. M. Fisher, E. Garcia-Cardena, A. R. Lusis, A. P. Owens III, M. E. Rosenfeld, and I. Tabas, “Recommendation on design, execution, and reporting of animal atherosclerosis studies: a scientific statement from the American Heart Association,” Arterioscler. Thromb. Vasc. Biol., vol. 37, no. 9, pp. e131–e157, Sep. 2017, doi: 10.1161/ATV.0000000000000062.
- M. J. Budoff, S. Achenbach, R. S. Blumenthal, J. J. Carr, J. G. Goldin, P. Greenland, A. D. Guerci, J. A. Lima, D. J. Rader, G. D. Rubin, L. J. Shaw, S. E. Wiegers, American Heart Association Committee on Cardiovascular Imaging and Intervention, American Heart Association Council on Cardiovascular Radiology and Intervention, American Heart Association Committee on Cardiac Imaging, “Assessment of coronary artery disease by cardiac computed tomography: a scientific statement from the AHA,” Circulation, vol. 114, no. 16, pp. 1761–1791, Oct. 2006, doi: 10.1161/CIRCULATIONAHA.106.178458.
- H. S. Hecht, “Coronary artery calcium scanning: past, present, and future,” JACC Cardiovasc. Imaging, vol. 8, no. 5, pp. 579–596, May 2015, doi: 10.1016/j.jcmg.2015.02.006.
- K. Nasir, M. B. Rivera, R. Blankstein, M. J. Blaha, A. D. Choi, R. S. Blumenthal, M. G. Silverman, A. Dardari, J. Berman, J. Yeboah, M. J. Budoff, J. J. Carr, and M. Cainzos-Achirica, “Implications of coronary artery calcium testing for primary prevention,” J. Am. Coll. Cardiol., vol. 66, no. 15, pp. 1657–1668, Oct. 2015, doi: 10.1016/j.jacc.2015.07.066.
- S. E. Nissen, S. J. Nicholls, I. Sipahi, P. Libby, J. S. Raichlen, C. M. Ballantyne, J. Davignon, R. Erbel, J. C. Fruchart, J.-C. Tardif, P. Schoenhagen, T. Crowe, V. Cain, K. Wolski, M. Goormastic, and E. M. Tuzcu, “Effect of very high-intensity statin therapy on regression of coronary atherosclerosis: the ASTEROID trial,” JAMA, vol. 295, no. 13, pp. 1556–1565, Apr. 2006, doi: 10.1001/jama.295.13.jpc60002.
- S. E. Nissen, S. J. Nicholls, K. Wolski, R. Nesto, S. Kupfer, A. Perez, H. Jure, R. De Larochellière, C. S. Staniloae, K. Mavromatis, J. Saw, B. Hu, A. M. Lincoff, E. M. Tuzcu, and PERISCOPE Investigators, “Effect of rosuvastatin versus atorvastatin on progression of coronary atherosclerosis in patients with coronary artery disease (SATURN),” N. Engl. J. Med., vol. 365, no. 22, pp. 2078–2087, Dec. 2011, doi: 10.1056/NEJMoa1110874.
- S. J. Nicholls, R. Puri, T. Anderson, C. M. Ballantyne, L. Cho, J. J. P. Kastelein, W. Koenig, R. Somaratne, H. Kassahun, J. Yang, S. M. Wasserman, R. Scott, I. Ungi, J. Podolec, A. O. Ophuis, J. H. Cornel, M. Borgman, D. M. Brennan, and S. E. Nissen, “Effect of evolocumab on progression of coronary disease in statin-treated patients: the GLAGOV randomized clinical trial,” JAMA, vol. 316, no. 22, pp. 2373–2384, Dec. 2016, doi: 10.1001/jama.2016.16951.
- A. V. Khera, E. S. Everett, M. G. Caulfield, F. E. Hantgan, J. Deasy, R. K. Scott, P. S. Sever, J. Barton, L. Heller, A. Nambi, and M. S. Sabatine, “Evolocumab, plaque regression, and clinical outcomes,” J. Am. Coll. Cardiol., vol. 75, no. 9, pp. 1037–1050, Mar. 2020, doi: 10.1016/j.jacc.2019.12.052.
- D. J. Rader and G. K. Hovingh, “HDL and cardiovascular disease,” Lancet, vol. 384, no. 9943, pp. 618–625, Aug. 2014, doi: 10.1016/S0140-6736(14)61217-4.
- R. C. Thompson, A. H. Allam, G. P. Lombardi, L. S. Wann, M. L. Sutherland, J. D. Sutherland, M. A. Soliman, B. Frohlich, D. T. Mininberg, J. M. Monge, C. M. Vallodolid, S. L. Cox, G. A. El-Maksoud, I. Badr, M. I. Miyamoto, A. el-Halim Nur el-Din, J. Narula, C. E. Finch, and G. S. Thomas, “Atherosclerosis across 4000 years of human history: the Horus study of four ancient populations,” Lancet, vol. 381, no. 9873, pp. 1211–1222, Apr. 2013, doi: 10.1016/S0140-6736(13)60598-X.
- H. Kaplan, R. C. Thompson, B. C. Trumble, L. S. Wann, A. H. Allam, B. Beheim, B. Frohlich, M. L. Sutherland, J. D. Sutherland, J. Stieglitz, D. E. Rodriguez, D. E. Michalik, C. J. Rowan, G. P. Lombardi, R. Bedi, C. E. Garcia, J. K. Min, J. Narula, C. E. Finch, M. Gurven, and G. S. Thomas, “Coronary atherosclerosis in indigenous South American Tsimane: a cross-sectional cohort study,” Lancet, vol. 389, no. 10080, pp. 1730–1739, Apr. 2017, doi: 10.1016/S0140-6736(17)30752-3.

