
1. What counts as a silent ASCVD event
Eight entities are routinely conflated. They have different denominators, different ascertainment methods, and different implications, and their statistics must not be pooled.
| Category | Definition | What it is not |
| Silent myocardial infarction | Objective evidence of prior infarction — qualifying pathological Q waves, or imaging evidence of myocardial loss or scar in an ischemic distribution after excluding nonischemic explanations — not recognized when it occurred [1]. | Not a claim about what the person felt. It is a claim about what was diagnosed. |
| Unrecognized myocardial infarction | Umbrella term covering both truly asymptomatic events and events with mild, atypical or misinterpreted symptoms [2]. | Not interchangeable with asymptomatic. This review uses unrecognized wherever the evidence is diagnostic. |
| Silent myocardial ischemia | Transient supply–demand mismatch without angina, reversible, demonstrable on ambulatory or stress testing. | Not an infarction. A positive stress test is not a count of previous heart attacks. |
| Sudden cardiac death as first manifestation | Fatal arrest in a person with no previously recognized cardiovascular diagnosis [3]. | An outcome, not a synonym for infarction. It may arise from an old scar, cardiomyopathy, or a primary electrical disorder. |
| Silent (covert) cerebral infarction | Brain infarction on MRI or CT without a history of acute neurological dysfunction attributable to that lesion [4]. | Not white matter hyperintensity, not an enlarged perivascular space, not a microbleed. Those are separate markers [5]. |
| Unrecognized or minimally symptomatic stroke | Brain infarction that did produce symptoms — brief imbalance, transient visual change — not attributed to stroke [4]. | Distinct from a covert infarct found incidentally. Here symptoms occurred but were misread. |
| Asymptomatic atherosclerosis | Coronary calcium, carotid plaque, aortic plaque, or reduced ankle-brachial index found before any clinical event [6]. | NOT a silent event. Plaque is a risk marker. Classifying it as an event inflates every downstream statistic. |
| Silent peripheral arterial disease | Ankle-brachial index at or below 0.90 without reported ischemic leg symptoms [7]. | Not an acute event. Chronic subclinical disease, prognostically important, but not something that happened on a date. |
Definitions follow the Universal Definitions of Myocardial Infarction [1,8] and the AHA/ASA statement on covert cerebrovascular disease [4].
The Fourth Universal Definition states that prior or silent infarction may be diagnosed by abnormal Q waves with or without symptoms in the absence of non-ischemic causes, by imaging evidence of loss of viable myocardium in an ischemic pattern, or by pathoanatomical findings [1]. The Fifth Universal Definition, published in 2026, adds that pathological Q waves have limited specificity and should where possible be confirmed by imaging, preferably cardiac magnetic resonance with late gadolinium enhancement, and cautions that the term silent can in some cases be misleading [8].
On the cerebral side, the AHA/ASA statement recognizes three cardinal manifestations — silent brain infarcts, white matter hyperintensities of presumed vascular origin, and cerebral microbleeds — and prefers covert to silent [4]. A further caution belongs in any ASCVD review: not every covert brain infarct is atherosclerotic. Some arise from large-artery disease, others from atrial fibrillation or another embolic source, and many deep lesions from small-vessel disease [4,9]. The vascular burden is broader than the specifically atherosclerotic burden.
2. How many occur in the United States
The AHA Heart Disease and Stroke Statistics Update reports 371,506 U.S. deaths from coronary heart disease in 2022 and 165,393 from stroke. Based on surveillance from 2005 to 2014, it estimates roughly 605,000 new and 200,000 recurrent myocardial infarctions annually, with average age at first infarction of 65.6 years in men and 72.0 years in women [10]. U.S. stroke incidence is conventionally cited as approximately 795,000 per year, about 87% ischemic [10].
Two cautions. These rest on a surveillance window that closed more than a decade ago. The report describes approximately 170,000 silent infarctions within that estimated 805,000 annual total of first and recurrent events — about 21%, which is the basis for public summaries describing roughly one in five heart attacks as silent. These are surveillance-based estimates carrying no confidence interval, not a contemporary national census of imaging-confirmed unrecognized MI.
Cohort data give a different and better-characterized picture. In ARIC, among 9,498 participants initially free of cardiovascular disease, investigators detected 317 ECG-defined unrecognized and 386 clinically documented infarctions over a median 8.9 years — 45.1% of detected incident infarctions were unrecognized [11]. In Framingham, more than 25% of 708 infarctions among 5,127 participants were discovered only through routine biennial electrocardiography [2]. In MESA, cardiac MRI found myocardial scar in 146 of 1,840 participants, of which 114 had not been identified by ECG or clinical adjudication [12] — though that study included both ischemic and non-ischemic scar patterns, so its frequently quoted unrecognized share is a percentage of scars, not of heart attacks.
Applying any of these cohort proportions to the national total would combine different definitions, eras, and age structures. These cohorts establish a substantial burden of unrecognized infarction, but this review does not establish a contemporary national annual count of imaging-confirmed silent MI.
2.1 Sudden cardiac death
Sudden cardiac death accounts for approximately half of cardiac deaths, and coronary disease underlies the majority [3]. The Finnish Fingesture study provides the clearest quantification: among 5,869 consecutive autopsy-verified sudden cardiac deaths between 1998 and 2017, 4,392 were attributed to coronary artery disease; of those, 3,122 occurred in people with no previously diagnosed coronary disease; and of those, 1,322 of the 3,120 with complete autopsy information (42.4%) had myocardial scarring indicating a previous silent infarction. Among the 187 people with silent MI who had an ECG recorded before death, 125 (67%) had abnormal findings [3].
Two interpretive limits. This is the probability of finding an old infarct among people who died suddenly, not the probability that a living person with a silent infarct will die suddenly. And a single-country autopsy series is not a U.S. or global estimate.
Nor does first recognized presentation mean no prior symptoms. In an Oregon study of 839 people aged 35 to 65 who suffered cardiac arrest and had symptom data available, 51% had warning symptoms in the preceding four weeks, most commonly chest discomfort or breathlessness [13]. Recall bias and incomplete symptom data apply.
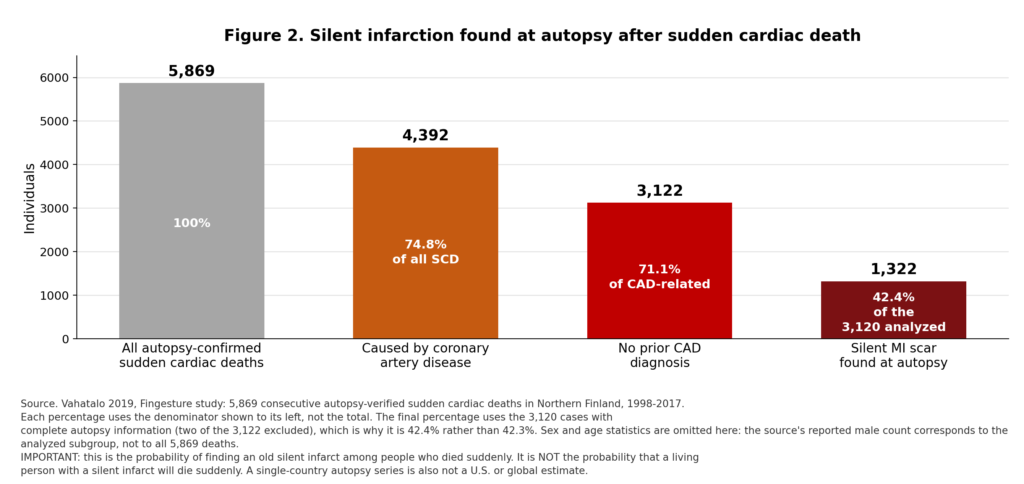
Figure 2 (repeated from Part One). Fingesture autopsy series [3]. Percentages use the denominators indicated in the graphic. The final percentage is 1,322 of 3,120 analyzed cases (42.4%), after excluding two cases with incomplete autopsy information.
3. How many occur worldwide
Every global figure here is modeled. Global Burden of Disease 2021 estimated 11.9 million incident strokes worldwide (95% uncertainty interval 10.7–13.2 million), including 7.8 million ischemic strokes (6.7–8.9 million) [14]. These describe clinical stroke burden; they are not a census of incidental MRI lesions.
No globally representative surveillance system supplies annual counts of unrecognized infarction confirmed by standardized cardiac MRI, nor of completely symptom-free infarctions. Regional cohorts — Icelandic, Dutch, American, Scandinavian — demonstrate that the problem exists internationally. They do not establish a world total. Population-level neuroimaging and cardiac MRI registries are largely absent from low- and middle-income countries, where most cardiovascular deaths occur.
| Two rules this review does not break
Silent myocardial infarctions and silent brain infarctions are never added together. They are different diseases, ascertained by different modalities, in different denominators, with different natural histories. No worldwide count of silent events is produced. Applying regional imaging prevalences to the world population would be an extrapolation layered on an extrapolation. Figures of that kind circulate widely; none that this review could trace rests on peer-reviewed global data. |
Table 1. Silent and unrecognized myocardial infarction
| Estimate | Population / dates | Method | Value | Numerator / denominator | Limitations |
| Unrecognized share of incident MI | Framingham, U.S., publication 1984 [2] | Biennial serial ECG | >25% of MIs unrecognized | 708 MIs among 5,127 participants | Historical diagnostic era; ECG-based; higher share in women (35%) than men (28%) [15] |
| Truly silent share | Framingham, as above [2] | Serial ECG plus symptom interview | Almost half of unrecognized MIs were silent; remainder atypical | Of the >25% unrecognized | The direct measurement of the three-way split identified by this review. 1984 data; recall-dependent; must not be applied to modern percentages |
| Silent share of incident MI | ARIC, U.S., median 8.9 y follow-up [11] | Serial 12-lead ECG, Minnesota coding | 45.1% | 317 of 703 detected incident MIs | Misses some infarctions; imperfect sensitivity, specificity and ascertainment of recognized events affect the estimated fraction; surveillance from 1987–1998 |
| Unrecognized MI prevalence | ICELAND MI, ages 67–93, scanned 2004–2007 [16] | Cardiac MRI, late gadolinium enhancement | 17% (95% CI 14–19%) | 157 of 936 | Elderly, ethnically homogeneous cohort; prevalence not incidence; 2012 analysis — the 2018 report uses a slightly different analytic sample from the same cohort |
| Same people, ECG only | ICELAND MI [16] | Electrocardiogram | 5% (95% CI 4–6%) | 46 of 936 | Same participants as the row above; the contrast is the finding |
| Recognized MI prevalence | ICELAND MI [16,17] | Clinical history and record review | 9.7% | 91 of 935 | Depends on prior healthcare access |
| Unrecognized share of all MIs | ICELAND MI [16,17] | Cardiac MRI vs clinical record | 63% | 156 of 247 detected MIs | Cohort is elderly; share expected lower at younger ages |
| Unrecognized MI in diabetes | ICELAND MI diabetic subgroup [16] | Cardiac MRI | 21% | 72/337 | Subgroup analysis; 95% CI 17%–26% |
| Myocardial scar prevalence | MESA, U.S., CMR 2010–2012, mean age 68 [12] | Cardiac MRI | Any scar 146/1,840 (7.9%); previously unrecognized 114/1,840 (6.2%) | As stated | Includes ischemic AND non-ischemic scar patterns; the unrecognized share is a share of scars, not of heart attacks |
| Estimated annual MI incidence, U.S. | U.S., surveillance 2005–2014 [10] | Clinical ascertainment | ~605,000 new, ~200,000 recurrent per year | National estimate | Surveillance window predates the report; the 805,000 total is stated to include ~170,000 silent events; no CI supplied |
| Worldwide silent MI count | — | — | NOT ESTIMATED | — | No representative global surveillance. Deliberately omitted rather than extrapolated |
4. How many people have absolutely no symptoms
Three groups need separating: those who experienced nothing; those with mild or atypical symptoms that were misinterpreted; and those with recognizable symptoms that nonetheless did not produce a diagnosis. Most epidemiological studies do not measure all three reliably and separately.
The Framingham evidence remains the most informative direct measurement. More than a quarter of 708 infarctions were unrecognized; of those, almost half were described as silent and the remainder caused atypical symptoms [2]. The unrecognized proportion was higher in women (35%) than men (28%) [15]. This establishes that truly unnoticed events exist and gives an order of magnitude for their frequency in that cohort.
It does not license taking half of a modern percentage to manufacture a current symptom-free estimate. The diagnostic era, interview methods, and population all differ. Retrospective recall is an intrinsic limitation in both directions: people forget brief illnesses and normalize fatigue, but they also reinterpret old symptoms after seeing a scan, and non-specific symptoms are common in people with no infarct at all.
Modern presentation data address the question from another angle. Among 1,143,513 patients with confirmed myocardial infarction in the National Registry of Myocardial Infarction, 35.4% presented without chest pain — 42.0% of women versus 30.7% of men — and younger women without chest pain had higher in-hospital mortality than similarly aged men without chest pain [18]. These data describe presentation without chest pain among hospitalized MI patients; they do not quantify how many infarctions were completely symptom-free or previously unrecognized.
| Why the word matters
Asymptomatic is a claim about a person’s experience. Unrecognized is a claim about the medical record. Nearly all published figures measure the second and are reported as though they measured the first. |
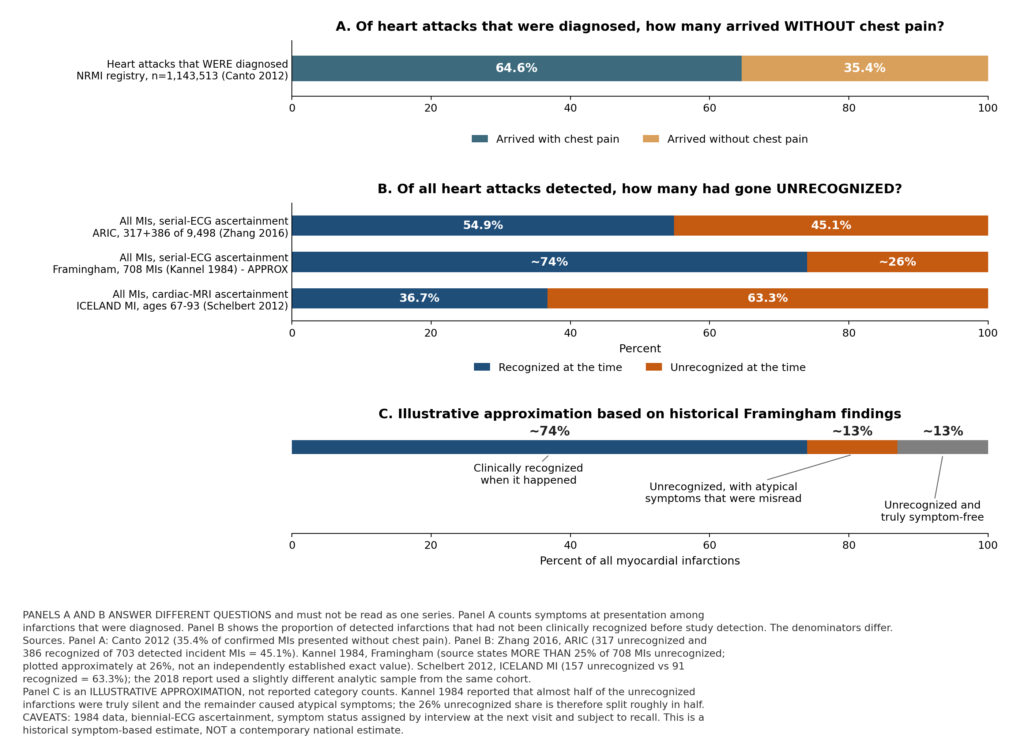
Figure 1 (repeated from Part One). Panel A: among diagnosed infarctions, the share presenting without chest pain [18]. Panel B: among all infarctions detected, the share that went unrecognized — a different denominator [2,11,16]. Panel C: an illustrative approximation of the Framingham symptom split, not reported category counts [2].
5. Symptoms that are commonly overlooked
Ischemic discomfort may present as pressure, heaviness, tightness, or burning, and may be located in the arm, shoulder, jaw, back, or upper abdomen rather than the chest. Breathlessness and unusual fatigue can be anginal equivalents. Nausea, sweating, light-headedness, or faintness may accompany an episode. A new or reproducible decline in exercise tolerance warrants evaluation, though it is not diagnostic — infection, anemia, lung disease, and medication effects produce similar changes.
Two calibrations matter. First, chest discomfort remains the most common presenting symptom of acute coronary syndromes in both sexes, and absence of chest pain should not be portrayed as the usual female presentation [19]. What the registry data show is a difference in proportion, not a reversal of the typical picture [18]. Second, current chest-pain guidance discourages using the word atypical as shorthand for harmless [19]; it describes terminology used in older studies, not a category of benign symptoms.
For the brain, abrupt facial or limb weakness, unilateral numbness, language difficulty, visual loss, or a new severe balance disturbance may indicate stroke even when brief or mild [4,20]. Gradual forgetfulness alone does not establish that a silent stroke occurred; clinical assessment connects the timing and pattern of symptoms with imaging.
| Symptom | How it typically presents | Why it gets dismissed |
| Unexplained fatigue or weakness | Tiredness disproportionate to activity, sometimes for days beforehand | Attributed to overwork, poor sleep, aging, or a virus |
| Shortness of breath | Breathlessness on exertion or at rest, without chest pain | Attributed to deconditioning, weight, asthma, or anxiety |
| Nausea, indigestion, upper abdominal discomfort | Epigastric burning or fullness, sometimes with belching | Treated as reflux; antacids taken and the episode passes |
| Sweating | Cold, clammy perspiration without exertion or heat | Attributed to anxiety, menopause, or infection |
| Dizziness or faintness | Light-headedness, near-syncope, unsteadiness | Attributed to dehydration, standing too fast, or medication |
| Jaw, back, shoulder or arm discomfort | Aching or pressure with no chest component | Attributed to musculoskeletal strain or dental problems |
| Decline in exercise capacity | A previously routine effort becomes hard, then recovers | Attributed to a bad day, illness, or aging — particularly by fit people |
6. Who is most vulnerable
| A distinction that changes the interpretation
For several groups the evidence cannot separate two very different explanations: that the group truly experiences more silent events, or that its events are simply less likely to be diagnosed. Observed differences may reflect event incidence, symptom expression, recognition, healthcare access and ascertainment. Where the literature cannot distinguish them, this review says so rather than choosing. |
6.1 Reasonably consistent evidence
- Older age — the strongest and most consistent association for both silent myocardial infarction and covert brain infarction [16,21,22,23].
- Diabetes — cardiac-MRI-detected unrecognized infarction reached 21% in the ICELAND MI diabetic subgroup against 17% overall [16]. Cardiac autonomic neuropathy is a plausible mechanism; UKPDS examined prognosis of silent infarction in newly diagnosed type 2 diabetes [24]. Neither diagnosis proves an event will be symptom-free.
- Chronic kidney disease — raises cardiovascular risk and complicates interpretation of chronically elevated troponin [8,25,26].
- Hypertension — particularly prominent in covert cerebral disease [21,5].
- Smoking, obesity, metabolic syndrome, and existing coronary, carotid or peripheral atherosclerosis — established drivers of events generally [6,7,27].
- Elevated LDL cholesterol, apolipoprotein B, and lipoprotein(a) — causal drivers of atherosclerosis, with an expanded formal role in the 2026 guideline [28]. None is a validated measure of whether an infarction will be noticed.
- Cognitive impairment and communication barriers — impair both perception and reporting, and complicate history-taking afterwards [4].
6.2 Genuinely mixed evidence
Sex. In ARIC, absolute rates of both recognized and unrecognized infarction were higher in men — silent infarction 5.08 per 1,000 person-years in men versus 2.93 in women — while the unrecognized share of all detected infarctions was relatively greater in women, and the mortality consequences trended worse in women [11]. Framingham likewise found a higher unrecognized proportion in women [15], and registry data show women far more likely to present without chest pain [18]. Rotterdam analyses examined prognosis by sex separately [29]. These findings are compatible: men may sustain more silent infarctions while women’s infarctions may be more likely to go unrecognized when they occur. The evidence does not settle it.
Race and ethnicity. In ARIC, Black participants had a numerically higher unrecognized-infarction incidence than White participants (4.45 versus 3.69 per 1,000 person-years) but the difference was not statistically significant, while White participants had a significantly higher rate of clinically recognized infarction (5.04 versus 3.24, p=0.002) [11]. These differences may reflect event incidence, recognition, healthcare access and ascertainment; these data cannot isolate their separate contributions. Rewriting either as a universal biological rule would be unwarranted; symptom interpretation, healthcare access, risk-factor distribution, and statistical uncertainty all contribute.
6.3 Plausible but poorly quantified
High fitness and pain tolerance are often proposed as reasons events go unrecognized in athletes and manual workers. Being fit does not establish absence of atherosclerosis, and tolerating strenuous exercise does not make a new symptom benign. But the quantitative cohorts in this review do not supply an estimate of elevated silent-infarction risk in the highly fit, and assigning one would be unjustified. New unexplained exercise symptoms should be evaluated on their own merits [19,30].
Limited access to healthcare is the clearest instance of the recognition-versus-occurrence problem. Fewer clinical encounters mean fewer opportunities for an event to be diagnosed as it happens, and fewer electrocardiograms in which an old infarction might later be noticed. This may increase the proportion of events that remain unrecognized in under-served populations, without implying any difference in biology.
7. How serious are silent heart attacks
An infarction is irreversible tissue injury, but its functional consequences vary. A small scar can coexist with preserved pumping function and normal daily activity; a larger one can impair contraction, reduce exercise reserve, and support abnormal electrical circuits. Location, scar burden, ejection fraction, remaining ischemia, and coexisting disease matter more clinically than whether the original episode hurt.
7.1 Infarct size and ventricular function
Cardiac MRI studies of unrecognized non-Q-wave infarction in patients with suspected coronary disease found infarcts averaging about 8% of left ventricular mass (SD 7%) with mean ejection fraction 52% (SD 18%), a spread that reflects wide variation rather than uniformly preserved function [31]. Mortality in that cohort was markedly elevated, with an all-cause hazard ratio of 11.4 (95% CI 2.5–51.1). Those intervals are extraordinarily wide — the study was small — and the estimate, while numerical, is too imprecise to generalize as an elevenfold risk for all silent infarction. In patients presenting with signs or symptoms of coronary disease, unrecognized myocardial scar on cardiac MRI was the strongest independent predictor of major adverse cardiac events among the variables examined [32]. Later studies also associated unrecognized infarction with adverse outcomes, although the association in Nordenskjöld et al. was no longer statistically significant after adjustment for age and coronary disease severity [33]; a subsequent multicenter study retained an independent prognostic association [34].
7.2 Mortality and the ten-year convergence
The ICELAND MI cohort provides the cleanest comparison, because the same population was characterized by cardiac MRI at baseline and followed prospectively for up to 13.3 years. At 3 years, mortality after unrecognized infarction was indistinguishable from no infarction (3% for both) and lower than after recognized infarction (9%). At 5 years, unrecognized infarction had risen to 13%, above no infarction at 8% but below recognized infarction at 19%. By 10 years, unrecognized and recognized infarction were not statistically different at 49% and 51%, and both far exceeded no infarction at 30% (p<0.001) [17].
Adjusted for age, sex, and diabetes, unrecognized infarction versus no infarction carried hazard ratios of 1.61 (95% CI 1.27–2.04) for death, 1.56 (1.26–1.93) for major adverse cardiac events, 2.09 (1.45–3.03) for subsequent infarction, and 1.52 (1.09–2.14) for heart failure [17]. Earlier follow-up at 6.4 years had already shown unrecognized infarction by MRI independently associated with mortality (HR 1.45, 95% CI 1.02–2.06) and improving risk stratification, whereas unrecognized infarction defined by ECG did not [16].
A 2020 synthesis is a meta-analysis of 30 prospective studies, 253,425 participants, and 1,621,920 person-years. ECG-defined unrecognized infarction was associated with all-cause mortality HR 1.50 (95% CI 1.30–1.73), cardiovascular mortality 2.33 (1.66–3.27), and major adverse cardiac events 1.61 (1.38–1.89) versus no infarction. MRI-defined estimates were higher — all-cause mortality 3.21 (1.43–7.23), cardiovascular mortality 10.79 (4.09–28.42), major adverse cardiac events 3.23 (2.10–4.95) — but with very wide intervals and significant heterogeneity [35]. Those wide intervals reflect few studies in selected referral populations and do not establish that MRI-detected infarcts are intrinsically more dangerous than ECG-detected ones.
In ARIC, silent infarction versus no infarction carried hazard ratios of 3.06 (95% CI 1.88–4.99) for coronary heart disease death and 1.34 (1.09–1.65) for all-cause mortality, against 4.74 and 1.55 after recognized infarction [11].
7.3 Heart failure and sudden death
For heart failure, ARIC reported incidence of 7.8 per 1,000 person-years with no infarction, 16.2 with silent infarction, and 30.4 with clinically recognized infarction; the adjusted hazard ratio for silent infarction was 1.35 (95% CI 1.02–1.78) against 2.85 (2.31–3.51) for recognized infarction [36].
For sudden cardiac death the ordering differed between cohorts. In CHS the corresponding adjusted hazard ratios were 1.70 for silent and 4.08 for recognized infarction; the pooled estimates were 2.65 and 3.99. Over a median 25.4 years in ARIC, the multivariable hazard ratio was 5.20 (95% CI 3.81–7.10) after silent infarction and 3.80 (2.76–5.23) after clinically recognized infarction [37]. A plausible reading is that recognized infarction brings beta-blockade, revascularization, device evaluation, and follow-up, while silent infarction leaves an arrhythmogenic scar in a patient whose infarction-specific treatment may be incomplete. That is inference from observational data, not a demonstrated mechanism.
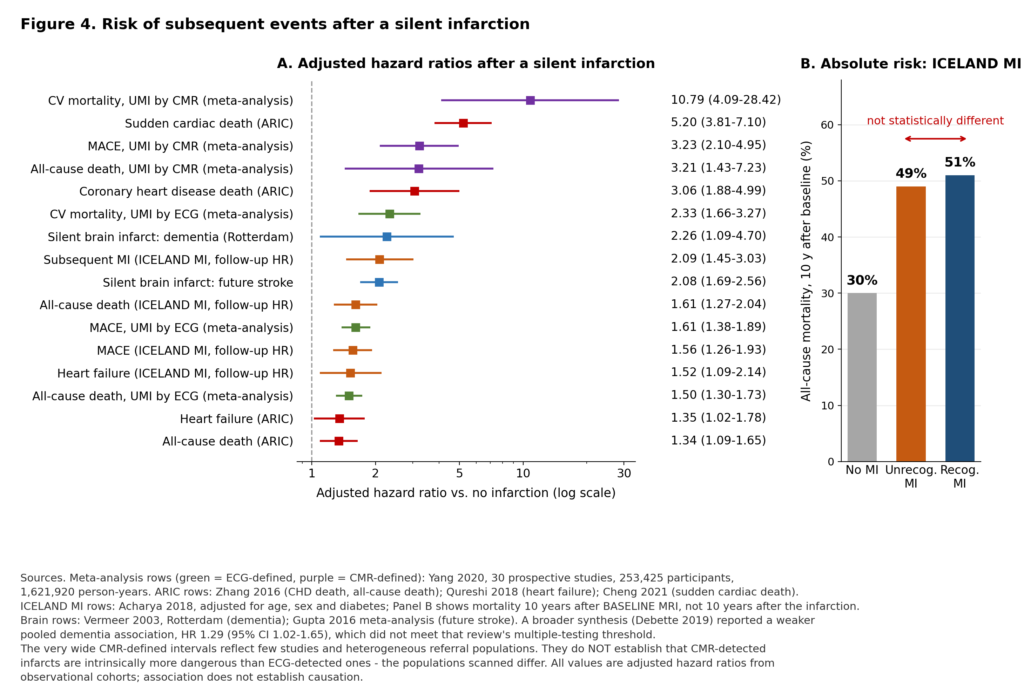
Figure 4. Adjusted hazard ratios [11,17,35,36,37,38,39] and absolute 10-year mortality [17]. Association does not establish causation.
7.4 Biologically less severe, or merely less noticed?
Unrecognized infarcts may be smaller while still carrying substantial long-term risk. These observational studies cannot determine how much prognosis reflects infarct characteristics, underlying disease, treatment differences or survivor selection. Silent infarcts are on average smaller, more often subendocardial and non-Q-wave, and associated with better preserved ejection fraction. If severity were the whole story, prognosis should be correspondingly better — and in the short term it is. What the ten-year data show is that mortality was initially lower in the unrecognized group and similar between groups ten years after baseline assessment [17]. This does not establish equivalent prognosis across populations, or explain why the groups differed. Preventive treatment was less common in the unrecognized-MI group. These observational data cannot determine how much that difference contributed to subsequent outcomes.
One selection effect deserves naming. Studies that identify old scars in living volunteers necessarily miss people who died before enrollment. This survivor selection can make imaging cohorts look less acutely severe than the full event population.
8. How serious are silent brain infarctions
A small infarct may spare the pathways needed for obvious speech or limb function while still injuring networks involved in attention, memory, processing speed, or gait. Multiple lesions can be cumulative. At the same time, a single incidental lesion does not establish dementia or explain every later cognitive complaint.
8.1 Prevalence
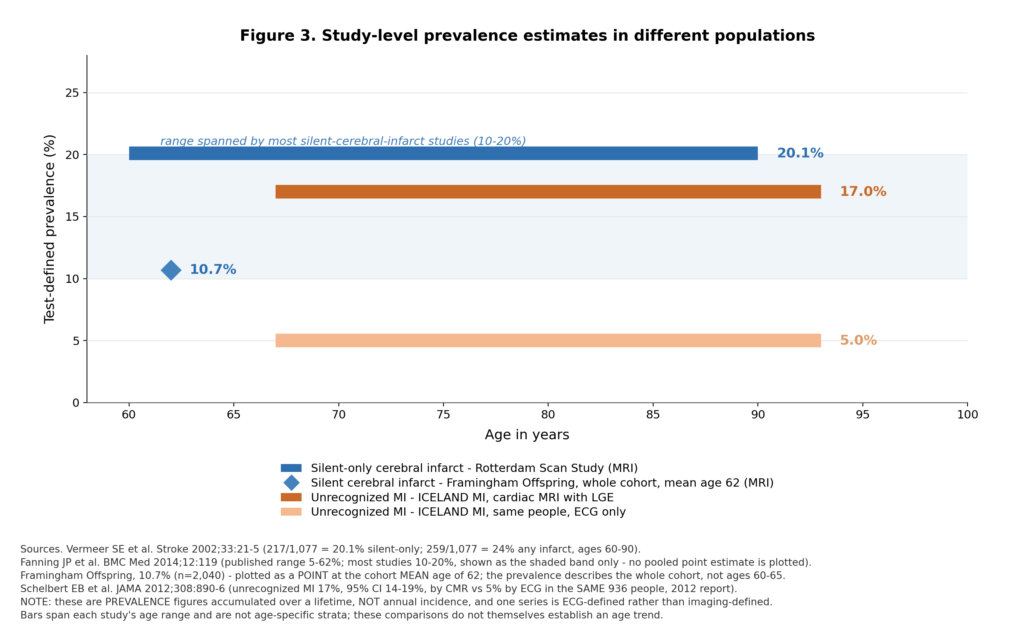
In the Rotterdam Scan Study, 259 of 1,077 participants aged 60 to 90 (24%) had at least one infarct on MRI, and 217 had silent infarcts only; silent infarcts were roughly five times more prevalent than symptomatic ones [21]. Repeat imaging in the same study found 81 of 668 participants (12.1%) developed new silent infarcts over a mean 3.4 years — a longitudinal observation subject to return-for-scan selection, and not an annual rate [40]. In the Framingham Offspring Study, silent cerebral infarction was present in 10.7% of 2,040 stroke-free participants with mean age 62, scanned between 1999 and 2005 [22]. A systematic review found published prevalence from 5% to 62%, most studies clustering between 10% and 20%, with annual incidence of 2% to 4% [23]. The AHA/ASA statement summarizes prevalence as approximately 25% among people older than 80 [4].
The wide published range reflects population age, MRI field strength and sequence, and lesion definition rather than genuine disagreement about biology.
8.2 Consequences
Cognition and dementia. In 1,015 Rotterdam Scan Study participants aged 60 to 90 and free of stroke and dementia at baseline, 30 developed dementia during a mean 3.6 years. Baseline silent infarction was associated with dementia at HR 2.26 (95% CI 1.09–4.70), and steeper decline in global cognition; the pattern was lesion-dependent, with thalamic infarcts associated with memory decline and non-thalamic infarcts with psychomotor slowing. A broader meta-analysis found a smaller association between covert brain infarcts and dementia: HR 1.29 (95% CI 1.02–1.65; p=0.04), which did not meet the authors’ multiple-comparison threshold of p<0.003, indicating less robust evidence than for subsequent stroke [5]. Decline was concentrated among those who accrued new infarcts [38]. The figure of 30 of 1,015 describes the whole cohort and must not be substituted for absolute dementia risk among those with a silent infarct.
Future clinical stroke. A meta-analysis of 13 studies and 14,764 subjects found a crude relative risk of 2.94 (95% CI 2.24–3.86) and an adjusted hazard ratio of 2.08 (1.69–2.56); in stroke-free cohorts the adjusted hazard was 2.06 (1.64–2.59) among approximately 9,483 people, with silent infarction present in about 18% [39]. This is a doubling of hazard over follow-up, not a statement that half of affected people will have a stroke.
Mortality and other markers. A broader meta-analysis of MRI markers of vascular brain injury associated covert infarcts with subsequent stroke and with all-cause death at HR 1.64 (95% CI 1.40–1.91) [5]. Findings for white matter hyperintensity or microbleeds require their own labels; a strong association for one MRI marker is not the effect size for a silent ischemic infarct.
Gait and balance disturbance, depressive symptoms, and loss of functional independence are also described in silent cerebrovascular disease [4], though the evidence there is thinner and effect sizes less firmly established. The evidence does not support a single depression probability caused by one incidental infarct.
Table 2. Silent (covert) cerebral infarction
| Estimate | Population / period | Method | Value | Limitations |
| Prevalence, ages 60–90 | Rotterdam Scan Study, 1995–1996 MRI [21] | Brain MRI | 24% with ≥1 infarct; 217/1,077 (20.1%) with silent infarcts only | Cross-sectional prevalence; no CI supplied for the proportion; single country |
| Ratio to symptomatic | Rotterdam Scan Study [21] | Brain MRI | Silent ~5× more prevalent than symptomatic | Ratio of prevalences, not of annual events |
| New silent infarcts | Rotterdam repeat MRI, 1999–2000 [40] | Serial brain MRI | 81/668 (12.1%) over mean 3.4 years | Not 12.1% per year; return-for-scan selection applies |
| Prevalence, mean age 62 | Framingham Offspring, MRI 1999–2005 [22] | Brain MRI | 10.7% of 2,040 stroke-free participants | Community cohort; CI not quoted; no national extrapolation |
| Prevalence, age >80 | AHA/ASA statement [4] | Brain MRI, pooled summary | ~25% with ≥1 silent brain infarct | Age-group summary; no single pooled denominator or CI |
| Published prevalence range | Systematic review, 2014 [23] | Brain MRI, varied protocols | 5% to 62%; most studies 10–20% | Range driven by age, protocol, and lesion definition |
| Annual incidence | Systematic review, 2014 [23] | Serial brain MRI | 2% to 4% per year | Requires repeat imaging; few cohorts have it |
| Future clinical stroke | Meta-analysis, 13 studies, n=14,764, 2016 [39] | Baseline MRI, clinical follow-up | Crude RR 2.94 (2.24–3.86); adjusted HR 2.08 (1.69–2.56) | Heterogeneous component studies; residual confounding by shared risk factors |
| Dementia | Rotterdam Scan Study, n=1,015 [38] | Brain MRI, prospective follow-up | HR 2.26 (1.09–4.70) | Wide interval; 30 dementia cases in the whole cohort over mean 3.6 years |
| All-cause death | Meta-analysis of MRI markers, 2019 [5] | Brain MRI | HR 1.64 (1.40–1.91) | Association with vascular injury and underlying disease; not a causal attributable fraction |
| U.S. annual count | Extrapolation published 2003 [41] | Modeled from age-specific MRI prevalence applied to the 1998 U.S. population | ~9 million people with a first silent MRI infarct | MODELED. Converts cross-sectional prevalence into modeled incidence; not measured; not a 2026 figure; silent hemorrhages must be kept separate |
| Worldwide prevalence | — | — | NOT ESTABLISHED | No representative global imaging data; extrapolation not attempted |
Table 3. Outcomes after silent versus recognized events
| Outcome | Silent / unrecognized | Clinically recognized | Reference group | Source |
| All-cause mortality, 10 y (absolute) | 49% | 51% (not statistically different) | 30%, no MI | ICELAND MI [17] |
| All-cause mortality (adj. HR) | 1.61 (1.27–2.04) | — | No MI = 1.0 | ICELAND MI, adjusted follow-up HR [17] |
| All-cause mortality (adj. HR) | 1.34 (1.09–1.65) | 1.55 (1.30–1.85) | No MI = 1.0 | ARIC [11] |
| All-cause mortality, UMI by ECG (adj. HR) | 1.50 (1.30–1.73) | — | No MI = 1.0 | Meta-analysis, 30 studies [35] |
| All-cause mortality, UMI by CMR (adj. HR) | 3.21 (1.43–7.23) | — | No MI = 1.0 | Meta-analysis [35] |
| Cardiovascular mortality, UMI by ECG | 2.33 (1.66–3.27) | — | No MI = 1.0 | Meta-analysis [35] |
| Cardiovascular mortality, UMI by CMR | 10.79 (4.09–28.42) | — | No MI = 1.0 | Meta-analysis [35] — very wide interval |
| Coronary heart disease death (adj. HR) | 3.06 (1.88–4.99) | 4.74 (3.26–6.90) | No MI = 1.0 | ARIC [11] |
| Major adverse cardiac events (adj. HR) | 1.56 (1.26–1.93) | — | No MI = 1.0 | ICELAND MI, adjusted follow-up HR [17] |
| Major adverse cardiac events, UMI by ECG | 1.61 (1.38–1.89) | — | No MI = 1.0 | Meta-analysis [35] |
| Heart failure (absolute rate) | 16.2 per 1,000 py | 30.4 per 1,000 py | 7.8 per 1,000 py | ARIC [36] |
| Heart failure (adj. HR) | 1.35 (1.02–1.78) | 2.85 (2.31–3.51) | No MI = 1.0 | ARIC [36] |
| Heart failure (adj. HR) | 1.52 (1.09–2.14) | — | No MI = 1.0 | ICELAND MI, adjusted follow-up HR [17] |
| Subsequent MI (adj. HR) | 2.09 (1.45–3.03) | — | No MI = 1.0 | ICELAND MI, adjusted follow-up HR [17] |
| Sudden cardiac death (adj. HR) | 5.20 (3.81–7.10) | 3.80 (2.76–5.23) | No MI = 1.0 | ARIC, median 25.4 y [37] |
| Future clinical stroke after silent brain infarct | 2.08 (1.69–2.56) | — | No silent infarct = 1.0 | Meta-analysis [39] |
| Dementia after silent brain infarct | 2.26 (1.09–4.70) | — | No silent infarct = 1.0 | Rotterdam Scan Study [38] |
| All-cause death with covert brain infarcts | 1.64 (1.40–1.91) | — | No covert infarct = 1.0 | Meta-analysis of MRI markers [5] |
All hazard ratios are adjusted, from observational cohorts, with 95% confidence intervals where published. The 2012 and 2018 ICELAND MI reports concern the same cohort but use slightly different analytic samples. Dashes indicate values not displayed here. Composite-event definitions and adjustment variables differ across studies; these estimates are not head-to-head comparisons. A hazard ratio is not a cumulative risk ratio. Cardiac and cerebral outcomes are listed separately and are never combined. Missing absolute risks are not created by multiplying hazard ratios by an arbitrary baseline.
9. Short- and long-term aftereffects
9.1 Immediate and structural
Myocardial necrosis is irreversible. Tissue lost during an infarction is replaced by collagenous scar, which does not contract and alters the mechanical loading of surrounding myocardium. In the brain the corresponding lesion is infarcted tissue that may cavitate into a lacune. Acute complications can occur despite minimal outward illness — impaired contraction or arrhythmia in the heart, a focal deficit in the brain.
9.2 Intermediate
Over weeks and months, ventricular remodeling may follow as geometry changes in response to altered loading; whether it does depends on infarct size, location and accompanying disease. Remaining myocardium can compensate, but compensation does not erase the injury. Because silent infarcts are on average smaller, remodeling is on average less pronounced — though it is not necessarily absent, and an unrecognized infarction does not by itself mean cardiac function has never been assessed. In the brain, rehabilitation and neural adaptation may improve function even though tissue has been lost; the effects of small lesions depend heavily on location and accompanying disease [38].
9.3 Long-term
Reduced cardiac reserve can be the intermediate consequence: a heart with scar meets resting demand but has less capacity under stress, which may present as a decline in exercise tolerance attributed to age. Heart failure is a possible clinical endpoint of that trajectory, not an inevitable one [36]. Scar-related electrical instability is a plausible contributor to the observed sudden-death association [37]. On the cerebral side, consequences may be subtle and can accumulate with additional injury — decrements in memory, attention, processing speed, and executive function, with the pattern depending on lesion location [38] — alongside gait disturbance and loss of independence [4].
9.4 Psychological
An incidental diagnosis carries its own burden: anxiety about what else may be undetected, distress about a body that gave no warning, and difficulty trusting future symptom perception. Clinicians delivering these results should anticipate it. It is also a genuine harm of screening and belongs in the harms column of section 11. Emotional distress after an unexpected scan result deserves attention without assuming the scan predicts imminent decline.
9.5 An important consequence: delayed secondary prevention
The ICELAND MI investigators reported that statin use was less common in participants with unrecognized than with recognized infarction [16]. A population with a demonstrated infarct — one that by any reasonable clinical standard warrants intensive risk-factor treatment — received preventive treatment less often. These observational data cannot separate the contribution of that treatment gap from underlying disease, scar characteristics and survivor selection, so the recoverable fraction of the excess risk is unquantified.
No randomized trial has tested whether treating a screening-detected silent infarction with guideline-directed secondary prevention improves outcomes, and the observation does not quantify how much later risk would disappear if every silent infarct were detected [17].
10. How silent events are discovered
| Modality | What it detects | Limitations |
| Resting electrocardiogram | Pathological Q waves, which may indicate previous infarction | Insensitive; Q waves may regress; mimics exist. ECG-based prevalence depends on the diagnostic criteria used [11]. The Fifth Universal Definition notes limited specificity and recommends imaging confirmation [8]. An automated ‘old infarct’ report needs clinical confirmation |
| Echocardiography | Regional wall-motion abnormality, ejection fraction, alternative explanations | A normal study cannot exclude every small scar; small subendocardial infarcts may not produce a detectable abnormality |
| Cardiac troponin | Myocardial injury; a rise and/or fall supports acute myocardial injury, but diagnosing acute MI additionally requires evidence of ischemia | Rises and falls, so a normal level long after a suspected episode does not exclude prior infarction; chronic elevation has several causes. High-sensitivity assays are chronic risk markers, not retrospective diagnostics [25,26] |
| Cardiac MRI with late gadolinium enhancement | Myocardial scar including subendocardial non-Q-wave infarction; subendocardial or transmural pattern in a coronary distribution supports ischemic injury | Reference standard. Midwall or subepicardial patterns suggest other processes; the ischemic/non-ischemic distinction is essential when interpreting a scar count [12]. Cost, availability, gadolinium exposure |
| Coronary CT angiography | Coronary anatomy and plaque burden | Primarily assesses coronary anatomy and plaque; some CT findings can suggest previous infarction, but it is not interchangeable with dedicated MRI scar assessment; radiation and iodinated contrast |
| Coronary artery calcium scoring | Calcified plaque burden | Measures plaque, not previous myocardial necrosis. A risk-refinement tool, not a test for past infarction [28] |
| Brain MRI (FLAIR, DWI) | Covert infarcts; DWI distinguishes acute from chronic; lacunes distinguishable from white matter hyperintensity | Lesion definitions vary across studies and drive much of the published prevalence range; mimics such as enlarged perivascular spaces must be excluded [4,9] |
| Brain CT | Established, especially larger and cavitated infarcts | Substantially less sensitive than MRI for small covert lesions |
| Ambulatory rhythm monitoring | Atrial fibrillation and other arrhythmias contributing to cerebral infarction | Identifies a mechanism, not the infarct; yield depends on monitoring duration |
| Carotid and peripheral vascular imaging | Carotid plaque and stenosis; ankle-brachial index for peripheral disease | Identifies atherosclerosis or PAD, not a previous cardiac or cerebral infarction [7,27] |
| Incidental detection | Findings on imaging performed for other reasons, or in research cohorts | Ascertainment is non-systematic, so incidental case series cannot estimate population prevalence |
10.1 Why ECG and cardiac MRI disagree
The most important methodological point in this review is contained in one comparison. In ICELAND MI, the same 936 people were assessed both ways: cardiac MRI found unrecognized infarction in 17%, electrocardiography in 5% [16]. The people did not change. The measurement did.
Electrocardiography detects prior infarction through pathological Q waves, whose presence depends on infarct size, location and several other factors, and which do not reliably classify an infarction as transmural or subendocardial. Subendocardial infarction — which much silent infarction turns out to be — frequently produces no Q wave. Cardiac MRI with late gadolinium enhancement images scar directly and resolves very small lesions.
Two consequences follow, pointing in opposite directions. ECG-based studies almost certainly underestimate the true burden of myocardial scarring, though imperfect specificity and differing denominators mean their figures are not guaranteed lower bounds. Conversely, highly sensitive imaging may detect small scars whose ischemic origin is uncertain, and MESA’s inclusion of non-ischemic scar patterns illustrates the problem [12]. Neither modality is simply right, and pooling their outputs into a single prevalence estimate is not defensible. ECG and MRI identify overlapping but nonidentical sets of unrecognized infarctions.
11. Screening: what helps, what is unproven, what may harm
| Four questions that are routinely conflated
1. Does the test detect atherosclerotic risk? For coronary calcium scoring, yes. 2. Does it detect obstructive disease or ischemia? For stress testing and CT angiography, yes. 3. Does it detect a previous silent infarction? For cardiac MRI, yes, better than anything else. 4. Does screening asymptomatic people with it prevent the next clinical event? A separate question, and for most modalities the randomized answer is negative or absent. A test can be excellent at 1, 2, and 3 and still fail 4. |
11.1 Randomized evidence
DIAD randomized 1,123 asymptomatic adults with type 2 diabetes to stress myocardial perfusion screening or no screening. Over approximately five years, cardiac death or nonfatal infarction occurred in 2.7% versus 3.0% (HR 0.88, 95% CI 0.44–1.8). The trial did not demonstrate benefit, though the wide interval means absence of significance is not proof of identical effects. Roughly 22% had abnormal scans, but these included perfusion and non-perfusion findings and should not all be called silent infarction or even the same form of silent ischemia [42].
FACTOR-64 randomized 900 asymptomatic patients with diabetes to coronary CT angiography screening or usual care. The primary outcome occurred in 6.2% versus 7.6% over about four years (HR 0.80, 95% CI 0.49–1.32), without significant reduction [43]. FACTOR-64 did not demonstrate improved outcomes from the CT screening strategy it tested in that diabetic population.
DANCAVAS randomized 46,611 Danish men aged 65 to 74; 16,768 were initially allocated to an invitation to comprehensive cardiovascular screening, 16,736 remained after pre-invitation exclusions, and 10,471 attended. All-cause mortality was not significantly reduced (HR 0.95, 95% CI 0.90–1.00, p=0.06), with a pre-specified subgroup aged 65 to 69 suggesting benefit (HR 0.89, 95% CI 0.83–0.96) [44]. Subgroup and secondary-outcome intervals were not adjusted for multiple comparisons, and the secondary stroke endpoint (HR 0.93, 95% CI 0.86–0.99) needs the same caution. DANCAVAS II, among 31,268 men aged 60 to 64, found seven-year mortality of 9.3% versus 9.9% (HR 0.94, 95% CI 0.86–1.03) and more severe bleeding (6.0% versus 5.1%; HR 1.18, 95% CI 1.05–1.32) [45].
No randomized trial has evaluated screening asymptomatic adults with cardiac MRI for silent infarction, or with brain MRI for covert infarction, using clinical events as the endpoint. This is the central evidence gap in the field.
11.2 Guideline positions
The USPSTF recommends against screening with resting or exercise electrocardiography in asymptomatic adults at low cardiovascular risk (grade D), and finds evidence insufficient at intermediate or high risk (I statement) [46]. It recommends against screening for asymptomatic carotid artery stenosis (grade D) [47], and finds evidence insufficient for ankle-brachial index screening in asymptomatic adults (I statement) [48]. None of this is a recommendation to ignore an abnormal ECG or a new symptom.
Coronary artery calcium occupies a narrower, guideline-supported role: refining risk when a preventive treatment decision remains uncertain. The 2026 dyslipidemia guideline adopts a calculate–personalize–reclassify approach, estimating ten-year risk with the PREVENT equations and using coronary calcium selectively to reclassify [28]. Crucially it can move a person either way; in selected primary-prevention patients a score of zero can support deferral, but not in established ASCVD, severe or familial hypercholesterolemia, diabetes after age 40, current smoking, or strong premature family history. Multimodality appropriate-use guidance permits selected testing in patients at high risk of silent ischemia [30], and in stable chronic coronary disease routine periodic testing without a change in clinical or functional status is not recommended [49].
11.3 Harms
- False positives, leading to further testing that carries its own risk.
- Incidental findings — pulmonary nodules on cardiac CT, aneurysms or tumors on brain MRI — triggering cascades of uncertain benefit.
- Ionizing radiation from CT and nuclear testing; iodinated contrast; gadolinium exposure with cardiac MRI, with kidney function to consider.
- Unnecessary invasive testing, including angiography prompted by abnormalities that would never have caused events.
- Overtreatment, including bleeding risk from preventive antithrombotic therapy started on the strength of a screening finding.
- Anxiety and the burden of being labeled (section 9.4).
- Cost, with opportunity cost for interventions of proven benefit.
These trade-offs differ by test and should not be collapsed into a generic warning about all imaging.
11.4 Where individualized evaluation may be reasonable
Nothing here supports routine cardiac or brain MRI screening for old infarcts in all asymptomatic adults, and no major guideline body recommends it. Individualized evaluation through shared decision-making may nonetheless be reasonable when a statin decision is genuinely balanced at intermediate estimated risk; in diabetes or chronic kidney disease, where risk is elevated and symptom perception may be unreliable; with a strong family history of premature ASCVD; with markedly abnormal lipid parameters including elevated lipoprotein(a) or apolipoprotein B; or when an abnormal examination, ECG, functional change, or embolic imaging pattern raises a sufficiently specific clinical question [28,30]. The purpose is to sharpen a treatment decision, not to search for disease for its own sake.
12. Prevention and clinical implications
An incidental finding should first be confirmed and classified. The next questions are what caused it, whether symptoms were missed, whether cardiac or cerebral function is affected, and which preventive measures would change outcomes.
12.1 A confirmed previous coronary infarction
The 2018 Multisociety Cholesterol Guideline defined clinical ASCVD to include acute coronary syndromes, history of myocardial infarction, stable or unstable angina, coronary or other arterial revascularization, stroke, transient ischemic attack, and peripheral arterial disease of atherosclerotic origin [50]. That guideline has been retired and replaced by the 2026 ACC/AHA Multisociety Dyslipidemia Guideline, which is more granular than a binary primary-versus-secondary split [28]:
- Clinical ASCVD at very high risk: LDL-C goal below 55 mg/dL. Very high risk means multiple major ASCVD events — acute coronary syndrome within 12 months, prior myocardial infarction other than that, prior ischemic stroke, or symptomatic peripheral arterial disease — or one major event plus multiple high-risk conditions such as age over 65, prior revascularization, current smoking, diabetes, heart failure, hypertension, or LDL-C above 100 mg/dL despite maximally tolerated statin plus ezetimibe.
- Clinical ASCVD not at very high risk: goal below 70 mg/dL.
- Primary prevention in severe hypercholesterolemia (LDL-C at or above 190 mg/dL): below 70 mg/dL where there is heterozygous familial hypercholesterolemia, one or more additional ASCVD risk factors, or documented coronary calcification. Separately, calcium-stratified goals are specified — below 100 mg/dL for scores of 1 to 99 Agatston units and below the 75th percentile for age, sex, and race; below 70 mg/dL for 100 to 299 or at or above the 75th percentile; below 70 mg/dL for 300 to 999, where intensification toward below 55 mg/dL is reasonable; and below 55 mg/dL for scores at or above 1,000. The guideline pairs these absolute targets with percentage reductions: 30 to 49% for the mild-calcium category and at least 50% for the higher categories.
So objectively documenting a prior silent myocardial infarction places a person in the clinical ASCVD category, and prior myocardial infarction is explicitly among the major events defining very high risk. Beyond lipid targets, this brings antiplatelet decisions based on ischemic and bleeding risk, blood-pressure and glycemic control, smoking cessation, physical activity and rehabilitation where appropriate, evaluation of left ventricular function, and structured follow-up [49]. An ECG suggestion alone, or a non-ischemic scar pattern, does not establish the same diagnosis.
12.2 An incidental silent brain infarct — a genuine difference
It is not accurate to assume that every covert brain infarct automatically demands the standard secondary-stroke antiplatelet regimen. The AHA/ASA statement recommends primary-prevention principles in this setting, with evaluation directed by lesion pattern and risk factors [4]. The European Stroke Organisation guideline specifically advises against aspirin for covert cerebral small-vessel disease in the absence of another indication [9]. Atrial fibrillation or another established condition may create a separate indication. Broader primary stroke prevention guidance applies [20].
This is a real asymmetry between the cardiac and cerebral cases, and collapsing the two — as several popular accounts do — would produce a treatment recommendation the evidence does not support.
| The honest limit of the reclassification argument
Guidelines define who should be treated based on the totality of evidence about risk. They do not demonstrate that a screening-detected silent infarction treated as clinical ASCVD yields the same benefit that treatment yields after a recognized infarction. That trial has not been run. The argument draws on the adverse prognosis associated with confirmed unrecognized MI and on the broader evidence supporting prevention after coronary infarction. Equal prognosis and equal treatment benefit have not been established for every subgroup. |
The shared priorities across both cases are sustained control of vascular risk and a plan for new symptoms. Healthy dietary patterns, regular activity, smoking cessation, hypertension treatment, diabetes management, and appropriate lipid therapy have a stronger clinical foundation than repeated scanning in search of silent injury. Prevention cannot guarantee that an event will never occur, but feeling well is not a reason to leave established risk untreated.
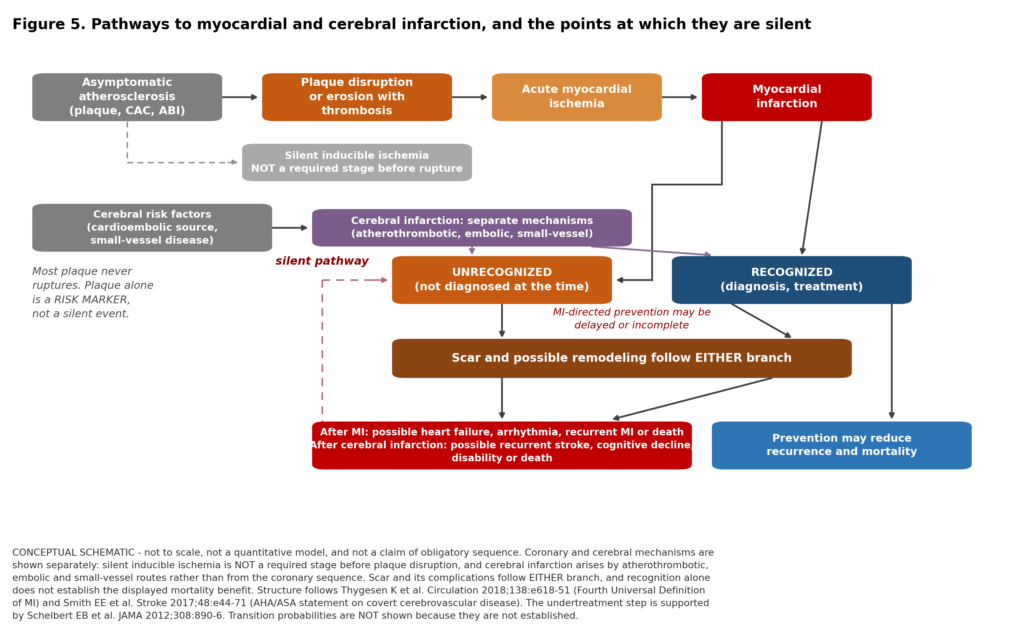
Figure 5. Conceptual pathway. Arrows show possibilities, not obligatory stages, time intervals, or quantified transition probabilities. Cerebral infarction can arise through atherothrombotic, embolic or small-vessel mechanisms; its evaluation and prevention depend on the cause [1,4,9,3,49].
13. Evidence gaps and uncertainties
- No randomized trial has tested whether guideline-directed secondary prevention delivers the same benefit after a silent infarction as after a recognized one.
- Randomized evidence on stroke prevention specifically in people with covert brain infarcts is sparse and inconclusive; the small SILENCE study did not establish a reliable preventive benefit of aspirin [51], and adequately powered trials are still needed.
- The contemporary annual U.S. and worldwide incidence of imaging-confirmed silent infarction is unknown.
- The proportion of unrecognized infarctions that are genuinely symptom-free has been measured directly in Framingham, in a different diagnostic era [2]. This review did not identify a reliable contemporary population-wide equivalent.
- The fraction of covert brain infarcts specifically attributable to atherosclerosis, as opposed to embolic or small-vessel mechanisms, is not established [4,9].
- Small late-gadolinium-enhancement lesions require classification by imaging pattern and clinical context; a subendocardial pattern in a coronary distribution supports ischemic injury, while nonischemic fibrosis should not be counted as myocardial infarction [12].
- Disentangling higher event rates from lower diagnosis rates across sex, race, and healthcare-access strata remains unresolved, and is a question about health systems as much as biology [11].
- Age-stratified prevalence is not reported comparably across cohorts, which is why Figure 3 presents study-level estimates rather than a smooth age curve. Neither the figures nor the tables are a personal risk calculator.
- Differences in detection can be larger than differences between populations. ECG surveys miss infarcts MRI detects; MRI studies differ in thresholds, sequences, and eligibility; screening volunteers differ from those who cannot participate; older cohorts reflect earlier treatment eras [11,16,12,35,22].
This is a focused narrative evidence review, not a registered systematic review with exhaustive duplicate screening. Publication dates and underlying data years are distinguished throughout. Confidence intervals are reported where available and are not invented where unavailable.
14. Warning signs requiring urgent evaluation
| Call 911 in the United States, or the local emergency number elsewhere
New chest pressure, tightness, heaviness, or discomfort, which may radiate to the arm, jaw, neck, back, or shoulder — especially with breathlessness, sweating, nausea, or faintness. Shortness of breath that is new, unexplained, or disproportionate to activity, with or without chest discomfort. New severe unexplained fatigue, or a sudden fall in exercise tolerance. Light-headedness, near-fainting, or fainting. Sudden one-sided weakness or numbness, facial droop, difficulty speaking or understanding speech, visual loss, or a new severe balance disturbance — even if it resolves. Note the last time the person was known to be well. A person who is unresponsive and not breathing normally needs an emergency call, CPR, and an AED as soon as one is available. |
Do not wait for severe pain, and do not drive yourself when a heart attack is suspected. A brief improvement does not establish that the problem is over: a deficit that clears in twenty minutes may have been a transient ischemic attack, and a resolving episode of chest discomfort may be unstable angina. The absence of chest pain does not rule out a heart attack — roughly a third of confirmed infarctions present without it, with a higher proportion in women, older adults, and people with diabetes [18].
This review is educational and is not a substitute for individual medical advice.
15. Conclusion
How much of the total ASCVD burden occurs silently? A substantial share, and the honest answer must name the ascertainment method before giving a number. By cardiac MRI in older adults, unrecognized infarctions outnumbered recognized ones roughly two to one in ICELAND MI [16]. By serial electrocardiography, silent infarction accounted for 45.1% of detected incident events in ARIC [11] and more than a quarter in Framingham [2]. In the brain, covert infarcts outnumber diagnosed strokes several-fold in community-dwelling older adults [21]. There is no single correct number, and any source offering one without naming its modality should be treated with suspicion.
How much is genuinely symptom-free rather than merely unrecognized? Less than the word silent suggests. The historical Framingham cohort described above found that roughly half of unrecognized infarctions were truly silent and the rest caused atypical symptoms [2] — which, applied to that cohort’s own unrecognized share, puts genuinely symptom-free events at something near one in eight of all infarctions there. A separate presentation finding is that 35.4% of confirmed hospitalized infarctions occurred without chest pain [18]. This does not estimate the proportion of unrecognized infarctions that caused no symptoms. That registry records the absence of chest discomfort; it does not establish what else was felt, or that misattribution is the dominant route by which an event goes unrecognized.
What does a silent event mean for a person’s future health? That a piece of heart or brain has died and that a scar is present, warranting assessment of its cause and of current vascular risk. In ICELAND MI, ten-year mortality after unrecognized infarction reached 49% against 51% after recognized infarction and 30% with no infarction [17]. A meta-analysis of 30 studies found consistently adverse prognosis [35]. In ARIC, silent infarction carried a fivefold adjusted hazard of sudden cardiac death, though the ordering against recognized infarction differed in the other cohort analyzed [37]. Covert brain infarcts roughly double the risk of future stroke and are associated with dementia, with estimates varying across studies [38,39]. By ten years after baseline assessment, mortality in this older cohort was similar in the recognized and unrecognized groups; a nonsignificant difference is not a demonstration of equivalence.
The most actionable conclusion is also the least comfortable. Failure to recognize an infarction may delay appropriate prevention, though the contribution of that delay to later outcomes is uncertain. People with unrecognized infarction have been shown to be less likely to receive the medications that protect people with recognized infarction [16]. The lesion was smaller; preventive treatment was less often in place. That is a gap clinical recognition can close, and it is why finding an old silent infarction should prompt not reassurance but a shift into secondary-prevention care — while an incidental covert brain infarct warrants a more cautious, cause-directed response rather than the same reflex [4,9].
None of this translates into a recommendation for routine population-wide cardiac MRI or brain MRI screening of asymptomatic adults to find old infarcts. The randomized evidence is negative or absent, the harms are real, and no guideline body endorses screening of that kind; selectively indicated testing is a separate question. It translates into two more modest propositions: that the overlooked presentations in section 5 deserve to be as widely known as the classic ones, and that when a silent infarction is found — by whatever route — it should be treated as what it is.
16. References
All entries are peer-reviewed journal publications.
- Thygesen K, Alpert JS, Jaffe AS, et al. Fourth Universal Definition of Myocardial Infarction (2018). Circulation. 2018;138(20):e618–e651. doi:10.1161/CIR.0000000000000617.
- Kannel WB, Abbott RD. Incidence and prognosis of unrecognized myocardial infarction: an update on the Framingham Study. N Engl J Med. 1984;311(18):1144–1147. doi:10.1056/NEJM198411013111802. PMID: 6482932.
- Vähätalo JH, Huikuri HV, Holmström LTA, et al. Association of silent myocardial infarction and sudden cardiac death. JAMA Cardiol. 2019;4(8):796–802. doi:10.1001/jamacardio.2019.2210. PMID: 31290935.
- Smith EE, Saposnik G, Biessels GJ, et al. Prevention of Stroke in Patients With Silent Cerebrovascular Disease: A Scientific Statement From the American Heart Association/American Stroke Association. Stroke. 2017;48(2):e44–e71. doi:10.1161/STR.0000000000000116.
- Debette S, Schilling S, Duperron MG, Larsson SC, Markus HS. Clinical significance of magnetic resonance imaging markers of vascular brain injury: a systematic review and meta-analysis. JAMA Neurol. 2019;76(1):81–94. doi:10.1001/jamaneurol.2018.3122.
- Bergström G, Persson M, Adiels M, et al. Prevalence of subclinical coronary artery atherosclerosis in the general population. Circulation. 2021;144(12):916–929. doi:10.1161/CIRCULATIONAHA.121.055340.
- Gornik HL, Aronow HD, Goodney PP, et al. 2024 ACC/AHA/AACVPR/APMA/ABC/SCAI/SVM/SVN/SVS/SIR/VESS Guideline for the Management of Lower Extremity Peripheral Artery Disease. J Am Coll Cardiol. 2024.
- Joint ESC/ACC/AHA/WHF Task Force for the Universal Definition of Myocardial Infarction. Fifth Universal Definition of Myocardial Infarction (2026). Circulation. 2026. doi:10.1161/CIR.0000000000001477.
- Wardlaw JM, Debette S, Jokinen H, et al. ESO Guideline on covert cerebral small vessel disease. Eur Stroke J. 2021;6(2):CXI–CLXII. doi:10.1177/23969873211012132.
- Martin SS, Aday AW, Allen NB, et al. 2025 Heart Disease and Stroke Statistics: A Report of US and Global Data From the American Heart Association. Circulation. 2025;151(8):e41–e660. PMID: 39866113.
- Zhang ZM, Rautaharju PM, Prineas RJ, et al. Race and sex differences in the incidence and prognostic significance of silent myocardial infarction in the Atherosclerosis Risk in Communities (ARIC) Study. Circulation. 2016;133(22):2141–2148. PMID: 27185168.
- Turkbey EB, Nacif MS, Guo M, et al. Prevalence and correlates of myocardial scar in a US cohort. JAMA. 2015;314(18):1945–1954. doi:10.1001/jama.2015.14849.
- Marijon E, Uy-Evanado A, Dumas F, et al. Warning symptoms are associated with survival from sudden cardiac arrest. Ann Intern Med. 2016;164(1):23–29. doi:10.7326/M14-2342.
- GBD 2021 Stroke Risk Factor Collaborators. Global, regional, and national burden of stroke and its risk factors, 1990–2021: a systematic analysis for the Global Burden of Disease Study 2021. Lancet Neurol. 2024;23(10):973–1003.
- Kannel WB. Silent myocardial ischemia and infarction: insights from the Framingham Study. Cardiol Clin. 1986;4(4):583–591. PMID: 3779719.
- Schelbert EB, Cao JJ, Sigurdsson S, et al. Prevalence and prognosis of unrecognized myocardial infarction determined by cardiac magnetic resonance in older adults. JAMA. 2012;308(9):890–896. doi:10.1001/2012.jama.11089. PMID: 22948699.
- Acharya T, Aspelund T, Jonasson TF, et al. Association of unrecognized myocardial infarction with long-term outcomes in community-dwelling older adults: the ICELAND MI study. JAMA Cardiol. 2018;3(11):1101–1106. doi:10.1001/jamacardio.2018.3285. PMID: 30304454.
- Canto JG, Rogers WJ, Goldberg RJ, et al. Association of age and sex with myocardial infarction symptom presentation and in-hospital mortality. JAMA. 2012;307(8):813–822. doi:10.1001/jama.2012.199. PMID: 22357832.
- Gulati M, Levy PD, Mukherjee D, et al. 2021 AHA/ACC/ASE/CHEST/SAEM/SCCT/SCMR Guideline for the Evaluation and Diagnosis of Chest Pain. Circulation. 2021. doi:10.1161/CIR.0000000000001029.
- Bushnell C, Kernan WN, Sharrief AZ, et al. 2024 Guideline for the Primary Prevention of Stroke: A Guideline From the American Heart Association/American Stroke Association. Stroke. 2024. doi:10.1161/STR.0000000000000475.
- Vermeer SE, Koudstaal PJ, Oudkerk M, Hofman A, Breteler MMB. Prevalence and risk factors of silent brain infarcts in the population-based Rotterdam Scan Study. Stroke. 2002;33(1):21–25. doi:10.1161/hs0102.101629. PMID: 11779883.
- Das RR, Seshadri S, Beiser AS, et al. Prevalence and correlates of silent cerebral infarcts in the Framingham Offspring Study. Stroke. 2008;39(11):2929–2935. doi:10.1161/STROKEAHA.108.516575.
- Fanning JP, Wong AA, Fraser JF. The epidemiology of silent brain infarction: a systematic review of population-based cohorts. BMC Med. 2014;12:119. doi:10.1186/s12916-014-0119-0.
- Davis TME, Coleman RL, Holman RR; UKPDS Group. Prognostic significance of silent myocardial infarction in newly diagnosed type 2 diabetes mellitus: UKPDS 79. Circulation. 2013;127(9):980–987. doi:10.1161/CIRCULATIONAHA.112.000908.
- Blankenberg S, Salomaa V, Makarova N, et al. Troponin I and cardiovascular risk prediction in the general population: the BiomarCaRE consortium. Eur Heart J. 2016;37(30):2428–2437. doi:10.1093/eurheartj/ehw172. PMID: 27174290.
- Willeit P, Welsh P, Evans JDW, et al. High-sensitivity cardiac troponin concentration and risk of first-ever cardiovascular outcomes in 154,052 participants. J Am Coll Cardiol. 2017;70(5):558–568. doi:10.1016/j.jacc.2017.05.062.
- Song P, Fang Z, Wang H, et al. Global and regional prevalence, burden, and risk factors for carotid atherosclerosis: a systematic review, meta-analysis, and modelling study. Lancet Glob Health. 2020;8(5):e721–e729.
- Blumenthal RS, Morris PB, Gaudino M, et al. 2026 ACC/AHA/AACVPR/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Dyslipidemia. J Am Coll Cardiol. 2026;87(19):2624–2757. PMID: 41824590. Also Circulation, doi:10.1161/CIR.0000000000001423.
- Dehghan A, Leening MJG, Solouki AM, et al. Comparison of prognosis in unrecognized versus recognized myocardial infarction in men versus women >55 years of age (from the Rotterdam Study). Am J Cardiol. 2014;113(1):1–6. doi:10.1016/j.amjcard.2013.09.005.
- Winchester DE, Maron DJ, Blankstein R, et al. 2023 Multimodality Appropriate Use Criteria for the Detection and Risk Assessment of Chronic Coronary Disease. J Am Coll Cardiol. 2023.
- Kim HW, Klem I, Shah DJ, et al. Unrecognized non-Q-wave myocardial infarction: prevalence and prognostic significance in patients with suspected coronary disease. PLoS Med. 2009;6(4):e1000057. doi:10.1371/journal.pmed.1000057.
- Kwong RY, Chan AK, Brown KA, et al. Impact of unrecognized myocardial scar detected by cardiac magnetic resonance imaging on event-free survival in patients presenting with signs or symptoms of coronary artery disease. Circulation. 2006;113(23):2733–2743. doi:10.1161/CIRCULATIONAHA.105.570648.
- Nordenskjöld AM, Hammar P, Ahlström H, et al. Unrecognized myocardial infarction assessed by cardiac magnetic resonance imaging — prognostic implications. PLoS One. 2016;11(2):e0148803. doi:10.1371/journal.pone.0148803.
- Antiochos P, Ge Y, Steel K, et al. Imaging of clinically unrecognized myocardial fibrosis in patients with suspected coronary artery disease. J Am Coll Cardiol. 2020;76(8):945–957. doi:10.1016/j.jacc.2020.06.063.
- Yang Y, Li W, Zhu H, et al. Prognosis of unrecognised myocardial infarction determined by electrocardiography or cardiac magnetic resonance imaging: systematic review and meta-analysis. BMJ. 2020;369:m1184. doi:10.1136/bmj.m1184. PMID: 32381490.
- Qureshi WT, Zhang ZM, Chang PP, et al. Silent myocardial infarction and long-term risk of heart failure: the ARIC Study. J Am Coll Cardiol. 2018;71(1):1–8. doi:10.1016/j.jacc.2017.10.071. PMID: 29301615.
- Cheng YJ, Jia YH, Yao FJ, et al. Association between silent myocardial infarction and long-term risk of sudden cardiac death. J Am Heart Assoc. 2021;10(1):e017044. doi:10.1161/JAHA.120.017044.
- Vermeer SE, Prins ND, den Heijer T, Hofman A, Koudstaal PJ, Breteler MMB. Silent brain infarcts and the risk of dementia and cognitive decline. N Engl J Med. 2003;348(13):1215–1222. doi:10.1056/NEJMoa022066. PMID: 12660385.
- Gupta A, Giambrone AE, Gialdini G, et al. Silent brain infarction and risk of future stroke: a systematic review and meta-analysis. Stroke. 2016;47(3):719–725. doi:10.1161/STROKEAHA.115.011889. PMID: 26888534.
- Vermeer SE, den Heijer T, Koudstaal PJ, et al. Incidence and risk factors of silent brain infarcts in the population-based Rotterdam Scan Study. Stroke. 2003;34(2):392–396.
- Leary MC, Saver JL. Annual incidence of first silent stroke in the United States: a preliminary estimate. Cerebrovasc Dis. 2003;16(3):280–285. doi:10.1159/000071128. MODELED ESTIMATE — see Table 2 limitations.
- Young LH, Wackers FJT, Chyun DA, et al. Cardiac outcomes after screening for asymptomatic coronary artery disease in patients with type 2 diabetes: the DIAD study, a randomized controlled trial. JAMA. 2009;301(15):1547–1555. doi:10.1001/jama.2009.476.
- Muhlestein JB, Lappé DL, Lima JAC, et al. Effect of screening for coronary artery disease using CT angiography on mortality and cardiac events in high-risk patients with diabetes: the FACTOR-64 randomized clinical trial. JAMA. 2014;312(21):2234–2243. doi:10.1001/jama.2014.15825.
- Lindholt JS, Søgaard R, Rasmussen LM, et al. Five-year outcomes of the Danish Cardiovascular Screening (DANCAVAS) trial. N Engl J Med. 2022;387(15):1385–1394. PMID: 36027560.
- Lindholt JS, Mejldal A, Rasmussen LM, et al. Outcomes of cardiovascular screening in men aged 60–64 years: the DANCAVAS II trial. Eur Heart J. 2026;47(15):1814–1825. doi:10.1093/eurheartj/ehaf704.
- US Preventive Services Task Force. Screening for cardiovascular disease risk with electrocardiography: US Preventive Services Task Force recommendation statement. JAMA. 2018;319(22):2308–2314.
- US Preventive Services Task Force. Screening for asymptomatic carotid artery stenosis: US Preventive Services Task Force recommendation statement. JAMA. 2021;325(5):476–481.
- US Preventive Services Task Force. Screening for peripheral artery disease and cardiovascular disease risk assessment with the ankle-brachial index: US Preventive Services Task Force recommendation statement. JAMA. 2018;320(2):177–183.
- Virani SS, Newby LK, Arnold SV, et al. 2023 AHA/ACC/Multisociety Guideline for the Management of Patients With Chronic Coronary Disease. Circulation. 2023. doi:10.1161/CIR.0000000000001168.
- Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC/Multisociety Guideline on the Management of Blood Cholesterol. Circulation. 2019;139(25):e1082–e1143. doi:10.1161/CIR.0000000000000625. RETIRED and replaced by ref 28; cited for the historical definition of clinical ASCVD.
- Maestrini I, Altieri M, Di Clemente L, et al. Longitudinal study on low-dose aspirin versus placebo administration in silent brain infarcts: the SILENCE study. Stroke Res Treat. 2018;2018:7532403. doi:10.1155/2018/7532403.
Further reading (not cited in the text)
- Sheifer SE, Gersh BJ, Yanez ND 3rd, et al. Prevalence, predisposing factors, and prognosis of clinically unrecognized myocardial infarction in the elderly. J Am Coll Cardiol. 2000;35(1):119–126.
- Boland LL, Folsom AR, Sorlie PD, et al. Occurrence of unrecognized myocardial infarction in subjects aged 45 to 65 years (the ARIC study). Am J Cardiol. 2002;90(9):927–931.
- Barbier CE, Bjerner T, Johansson L, Lind L, Ahlström H. Prevalence of unrecognized myocardial infarction detected with magnetic resonance imaging and its relationship to cerebral ischemic lesions in both sexes. J Am Coll Cardiol. 2011;58(13):1372–1377.
- Detrano R, Guerci AD, Carr JJ, et al. Coronary calcium as a predictor of coronary events in four racial or ethnic groups. N Engl J Med. 2008;358(13):1336–1345.
- Song P, Rudan D, Zhu Y, et al. Global, regional, and national prevalence and risk factors for peripheral artery disease in 2015: an updated systematic review and analysis. Lancet Glob Health. 2019;7(8):e1020–e1030.
Disclosure and scope. This review is educational. It is not individual medical advice and does not establish a clinician–patient relationship. Numerical values are reproduced as published; where a confidence interval was not reported in the source, none has been constructed. Observational hazard ratios describe association and do not establish causation.

