
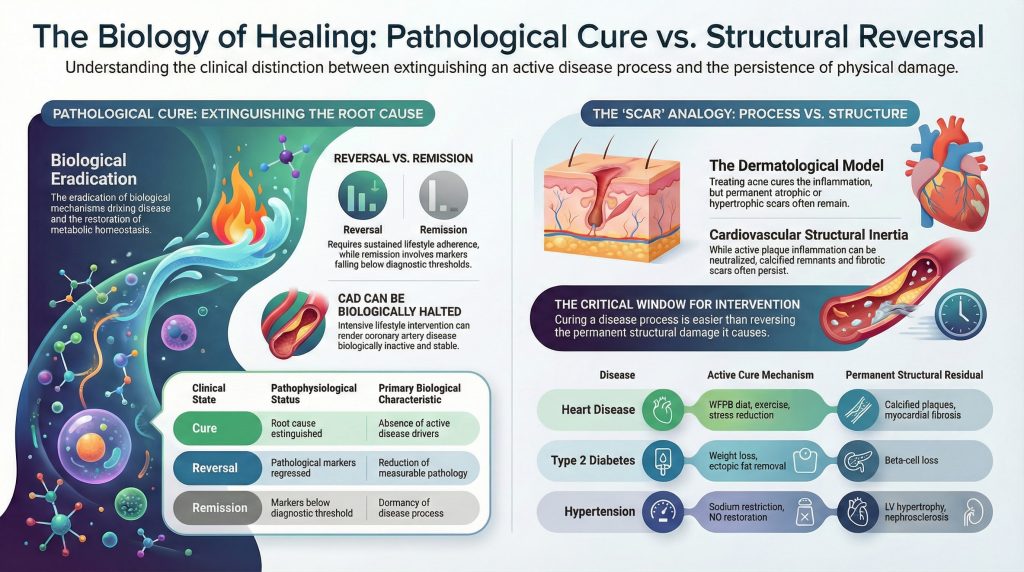
Clinical Paradigms of Disease Resolution: Biological Differentiation between the Cure of Pathological Processes and the Reversal of Structural Damage
The medical community has historically distinguished between the resolution of acute illness and the long-term management of chronic disease. As lifestyle medicine has matured into a formal clinical discipline, it has exposed a critical gap in medical taxonomy: the failure to clearly differentiate between the cure of an active pathological process and the reversal of structural damage produced by that process. Within dominant clinical paradigms, most chronic diseases are treated through symptom control, risk reduction, and delay of complications rather than through complete elimination of all underlying biological drivers.¹ Nevertheless, a growing body of empirical evidence—most prominently from the longitudinal work of Dean Ornish and Caldwell Esselstyn—demonstrates that coronary artery disease (CAD), a major cause of global mortality, can in some patients show halted progression, improved vascular function, plaque stabilization, and even modest regression when cardiovascular risk factors are intensively controlled through comprehensive lifestyle and risk-factor intervention.² This state can reasonably be described, within the conceptual framework developed here, as a functional or pathophysiological “cure” of active disease, even though it does not invariably result in complete restoration of normal vascular anatomy or elimination of pre-existing structural injury.⁵ This use of “cure,” however, is not standard terminology in contemporary cardiovascular guidelines.
The conceptual challenge of distinguishing cure from reversal is well illustrated by the dermatological example of severe acne vulgaris. In acne, the disease process consists of inflammation associated with follicular hyperkeratinization, excess sebum production, Cutibacterium acnes activity, and host inflammatory responses.⁷ When treated effectively, this process can resolve, resulting in the cessation of new lesions. Yet many patients are left with permanent atrophic or hypertrophic scars—structural alterations of the skin that no longer represent active disease.¹⁰ This distinction provides a clinically useful analogy and conceptual framework for cardiovascular medicine: a patient may achieve substantial suppression or stabilization of active atherosclerotic disease and experience substantially reduced risk of acute coronary events while still retaining calcified plaques or ischemic limitations that represent historical damage and may coexist with residual disease activity and cardiovascular risk.⁶
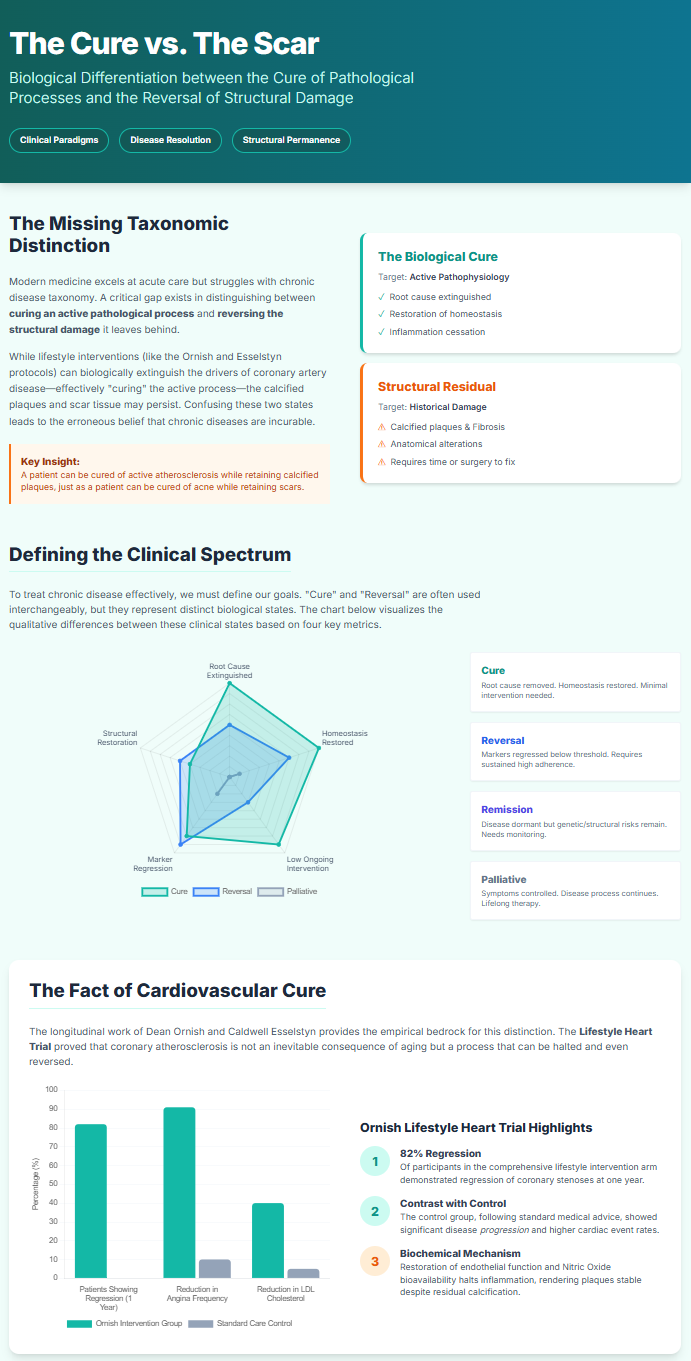
Taxonomic Definitions in Chronic Disease Management
To navigate chronic disease resolution with precision, clinicians must distinguish the status of the pathological process from the condition of the affected organ’s structure. For purposes of the conceptual framework proposed in this paper, the following terms distinguish suppression of an active pathological process from regression of established structural pathology. These definitions should not be interpreted as universally accepted clinical definitions. A cure within this framework denotes durable suppression or elimination of the dominant biological processes driving disease, with restoration toward physiological homeostasis. In chronic cardiometabolic disease, continued control of causal risk factors may still be required to maintain this state.¹⁴ Reversal, in contrast, refers to regression of measurable disease markers—such as hyperglycemia or arterial stenosis—toward or below clinically defined thresholds, typically requiring sustained behavioral adherence to prevent recurrence.³
Clinical State | Pathophysiological Status | Required Intervention Post-Resolution | Primary Biological Characteristic
Cure | Dominant disease-driving processes durably suppressed or eliminated | Continued risk-factor control may be necessary | Absence or marked suppression of measurable active disease drivers
Reversal | Pathological markers regressed | Sustained lifestyle adherence | Reduction of measurable pathology
Remission | Markers below diagnostic threshold | Continuous monitoring | Absence of currently detectable disease activity or expression without assurance of permanent eradication
Palliative | Symptoms and disease burden managed; underlying disease may persist | Ongoing supportive treatment | Relief without curative intent
This distinction is particularly relevant in type 2 diabetes mellitus (T2D). Remission is defined as an A1C below 6.5% for at least three months without pharmacologic therapy, yet the condition is rarely labeled a cure because genetic susceptibility and residual beta-cell dysfunction persist.²² International expert consensus therefore favors the term “remission” rather than “cure.”²² Environmental stressors, such as weight regain, can reactivate the disease process.¹⁵ Similarly, in CAD, patients may achieve biological stability in which plaque inflammation and rupture risk are substantially reduced, even though calcified or fibrotic remnants of prior disease remain.⁶
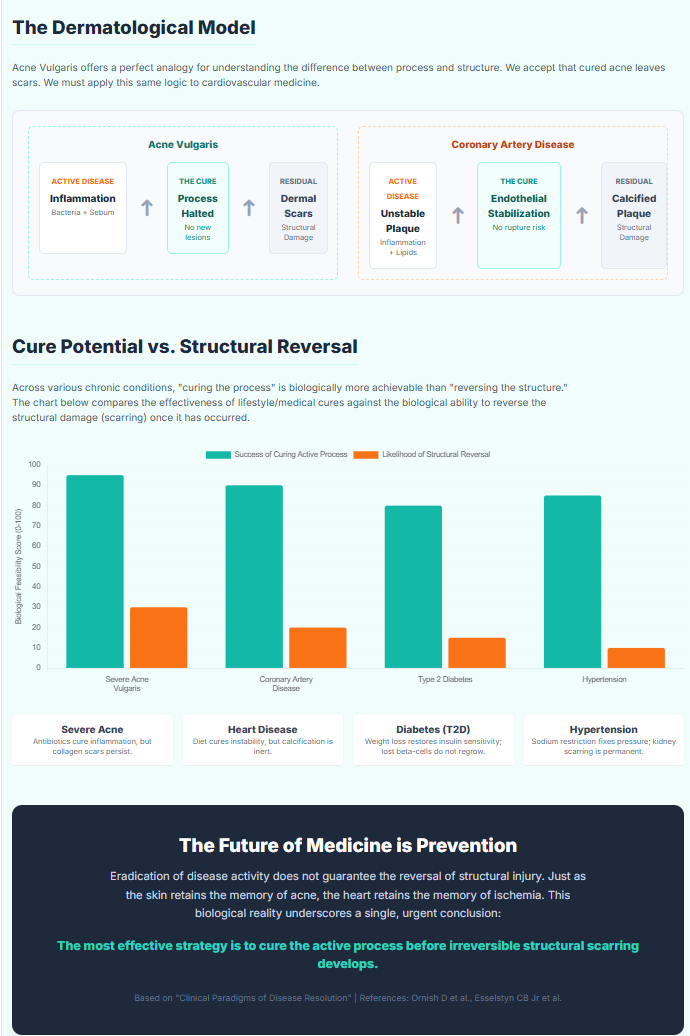
The Dermatological Model: Curing the Process versus Reversing the Scar
The analogy between acne and atherosclerosis is biologically informative because both disorders involve mechanisms of inflammation-driven tissue remodeling. Acne targets the pilosebaceous unit, where Cutibacterium acnes can contribute to immune cascades that may culminate in follicular rupture and dermal injury.⁹ When treated with retinoids, antibiotics, or hormonal modulation, the active inflammatory process can resolve or enter sustained remission as pathogenic mechanisms are suppressed.⁷
Despite resolution of the active inflammatory process, structural sequelae often remain. These scars are classified by collagen dynamics:
Atrophic scars (ice‑pick, boxcar, rolling) result from collagen loss and dermal matrix destruction during intense inflammation.⁸
Hypertrophic scars and keloids reflect excessive collagen deposition, sometimes extending beyond the original lesion.⁸
These residual structural changes may exert lasting psychological and functional effects long after the active disease process has resolved.¹¹ Analogously, individuals with stabilized CAD may retain fixed stenoses or myocardial scars that impair perfusion despite substantial reduction in plaque instability and associated inflammatory activity.⁵ Thus, suppressing or resolving an inflammatory disease process is biologically more achievable than reversing the structural damage it leaves behind.
The Evidence for Cardiovascular Disease Resolution: Ornish and Esselstyn Paradigms
Contrary to the belief that CAD is an inevitable consequence of aging, extensive clinical research demonstrates that atherosclerosis is a multifactorial disease strongly influenced by modifiable metabolic and lifestyle risk factors, and that its progression can be substantially slowed and, in some selected populations receiving intensive intervention, may be halted or partially reversed.¹² This conclusion is supported by decades of peer-reviewed investigation.
The Ornish Lifestyle Heart Trial
Dean Ornish provided important early randomized evidence that coronary atherosclerosis progression could, in some participants, be halted or modestly reversed without lipid-lowering drugs.² Using quantitative coronary arteriography and positron emission tomography, the Lifestyle Heart Trial evaluated the effects of a comprehensive intervention including a low-fat, whole-food, plant-based diet, moderate exercise, stress management, and social support.² Eighty-two percent of participants in the intervention arm demonstrated measurable regression in coronary atherosclerosis at one year.² At five years, this group exhibited further average angiographic regression and significantly fewer cardiac events than controls receiving standard dietary advice.²³
The Esselstyn Protocol and Endothelial Stabilization
Caldwell Esselstyn’s work emphasized nutritional primacy in restoring endothelial function.⁴ By eliminating animal products and added oils, his protocol aims to normalize nitric oxide bioavailability and suppress endothelial inflammation.¹² Long-term observational follow-up of patients with advanced CAD demonstrated a very low rate of recurrent major cardiovascular events among adherent participants.¹³ These findings are clinically notable but should be interpreted cautiously because the evidence is observational rather than derived from a randomized controlled trial. Esselstyn has proposed that very low LDL levels together with improved endothelial function may markedly suppress the biological processes responsible for atherosclerotic progression.¹²
Biological Mechanisms Underlying Disease Stabilization
Lifestyle-mediated risk reduction and disease stabilization reflect coordinated biochemical shifts rather than isolated pharmacologic effects. Endothelial nitric oxide restoration improves vasodilation, inhibits leukocyte adhesion, and reduces thrombogenicity.¹² Some studies have shown that high-fat meals can acutely impair endothelial function, whereas nitrate-rich plant foods can enhance nitric oxide bioavailability.¹²
Trimethylamine N-oxide (TMAO) has emerged as a diet-related biomarker associated with increased cardiovascular risk.¹⁷ TMAO production depends on gut microbial metabolism of dietary precursors including carnitine and choline, which are present in varying amounts in both animal-derived and plant-derived foods, with carnitine particularly abundant in red meat and choline present in several animal and plant sources. Individuals adhering to strict plant-based diets demonstrate markedly reduced TMAO generation, although whether lowering TMAO itself independently mediates cardiovascular event reduction remains uncertain.¹⁷
Why Disease Stabilization Outpaces Structural Reversal
While inflammatory atherogenesis can respond to intensive modification of metabolic risk factors, structural damage exhibits biological inertia. Plaque calcification represents a regulated, osteogenic-like process involving, among other mechanisms, vascular smooth muscle cell phenotypic differentiation.⁵ Early lipid-rich plaques are more amenable to regression, whereas mature calcified lesions often persist despite disease quiescence.¹⁶ Genomic studies demonstrate that early and advanced plaques are governed by distinct regulatory networks, limiting reversibility in late-stage disease.¹⁸
Myocardial infarction further illustrates this principle: necrotic myocardium is replaced by fibrotic scar tissue that lacks normal myocardial contractile function.¹⁹ Comprehensive secondary prevention, including lifestyle intervention, can reduce the risk of subsequent infarction but cannot readily regenerate lost myocardium, leading to chronic ischemic limitations.²⁰
Residual Cardiovascular Risk
Residual cardiovascular risk refers to the continuing risk of cardiovascular events despite treatment and control of major recognized risk factors.⁶ Contributors include persistent calcification, arterial stiffness, incomplete plaque stabilization, and low-grade inflammation.⁶ These risks are potentially attributable to both persistent structural abnormalities and ongoing biological processes, including residual inflammatory, thrombotic, lipid-related, and metabolic risk. In this respect, persistent cardiovascular damage partially parallels residual structural sequelae in other chronic diseases.
Comparative Disease Models
This active-disease-versus-residual-damage distinction recurs throughout medicine. In T2D, substantial loss of ectopic hepatic and pancreatic fat can restore insulin sensitivity and improve beta-cell function in some patients, yet prolonged disease may result in irreversible beta-cell loss.³ In hypertension, blood pressure normalization may not fully reverse left ventricular hypertrophy or nephrosclerosis once structural remodeling has occurred.²¹
Disease | Mechanism of Disease Control/Resolution | Permanent Structural Residual
Severe Acne | Anti-inflammatory, keratinization-directed, antimicrobial, and/or hormonal therapy | Dermal scarring
Heart Disease | Comprehensive risk-factor modification, including dietary improvement, exercise, smoking cessation when applicable, stress management, and evidence-based medical therapy | Calcified plaques, myocardial fibrosis
Type 2 Diabetes | Substantial weight loss, reduction of ectopic liver/pancreatic fat, and restoration of metabolic function | Beta-cell loss
Hypertension | Blood-pressure control through dietary modification, physical activity, weight management, sodium reduction, and antihypertensive therapy when indicated | LV hypertrophy, nephrosclerosis
Conclusion
Coronary artery disease is not necessarily an inexorably progressive condition. Intensive lifestyle and risk-factor intervention can halt progression in some patients, promote plaque stabilization, improve vascular function, and in selected cases produce measurable regression of coronary atherosclerosis.² However, successful suppression of disease activity does not guarantee reversal of structural injury. As with resolved inflammatory acne leaving dermal scars, the stabilized heart may retain calcified lesions, myocardial scar, fixed stenoses, or other structural sequelae of prior disease.⁵ If “cure” is defined narrowly as durable control or resolution of the active pathological process rather than restoration of pristine anatomy or permanent elimination of susceptibility, these findings provide a biological basis for considering the concept of a functional or pathophysiological cure. This terminology, however, extends beyond the conventional language of current cardiovascular guidelines and should not be interpreted as meaning that established CAD requires no continuing prevention, monitoring, or treatment. This reality underscores the urgency of early intervention: the most effective strategy is to suppress the disease process before irreversible structural damage develops.¹⁶ The future of medicine lies not in managing inevitable decline, but in applying effective disease-modifying interventions early enough to prevent permanent damage from forming.
References
- Can we say “cure”? J Eval Clin Pract. Accessed via PubMed Central.
- Ornish D, Brown SE, Scherwitz LW, et al. Can lifestyle changes reverse coronary atherosclerosis? The Lifestyle Heart Trial. Lancet. 1990;336(8708):129-133.
- Joslin Diabetes Center. Can type 2 diabetes be reversed? Accessed online.
- Esselstyn CB Jr, Gendy G, Doyle J, Golubic M, Roizen MF. A way to reverse CAD? J Fam Pract. 2014;63(7):356-364.
- Demer LL, Tintut Y. Calcification: a physiologic defense? In: Inflammatory Atherosclerosis. NCBI Bookshelf.
- Libby P. Residual cardiovascular risk—Is inflammation the primary cause? Am J Cardiol. Accessed via PubMed Central.
- Fabbrocini G, Annunziata MC, D’Arco V, et al. Acne scarring: pathogenesis, evaluation, and treatment options. Clin Cosmet Investig Dermatol. Accessed via PubMed Central.
- Goodman GJ, Baron JA. Acne scars: pathogenesis, classification and treatment. Dermatol Surg. Accessed via PubMed Central.
- Tan J, Bhate K. Acne vulgaris and the epidermal barrier. Clin Dermatol. Accessed via PubMed Central.
- DermNet NZ. Acne scarring. https://dermnetnz.org.
- Tan JK, Bhate K. The psychological impact of acne scarring. Medicine Today.
- Esselstyn CB Jr. Resolving the coronary artery disease epidemic through plant-based nutrition. Prev Cardiol. Accessed via PubMed Central.
- Esselstyn CB Jr, et al. Long-term outcomes of plant-based nutrition in coronary artery disease. J Fam Pract.
- Beyond Type 1. Diabetes remission vs cure vs reversal. Accessed online.
- Liv Hospital. Can type 2 diabetes be reversed? Accessed online.
- Shanahan CM, Cary NR, Salisbury JR, Proudfoot D, Weissberg PL, Edmonds ME. Mechanisms and clinical consequences of vascular calcification. Lancet. Accessed via PubMed Central.
- Tang WHW, Hazen SL. Microbiome, trimethylamine N-oxide, and cardiovascular risk. Circ Res. Accessed via PubMed Central.
- Fisher EA, et al. Distinct mechanisms of early versus late atherosclerosis regression. Icahn School of Medicine at Mount Sinai.
- Sutton MG, Sharpe N. Left ventricular remodeling after myocardial infarction. Circulation. Accessed via PubMed Central.
- Velazquez EJ, et al. Outcomes in ischemic cardiomyopathy. N Engl J Med. Accessed via PubMed Central.
- Bidani AK, Griffin KA. Pathophysiology of hypertensive renal damage. Hypertension. Accessed via PubMed Central.
- Riddle MC, Cefalu WT, Evans PH, et al. Consensus report: definition and interpretation of remission in type 2 diabetes. Diabetes Care. 2021;44(10):2438-2444.
- Ornish D, Scherwitz LW, Billings JH, et al. Intensive lifestyle changes for reversal of coronary heart disease. JAMA. 1998;280(23):2001-2007.

