I. Introduction: Contextualizing Coronary Artery Disease Regression
 AtherosclerosisAtherosclerosis is the disease behind most heart attacks and many strokes. Cholesterol particles get stuck in the wall of an artery, the body sends immune cells to clean up, and over years that mess hardens into plaque. is a chronic, progressive vascular condition traditionally managed by interventions aimed at slowing its advancement.1 The measurable reversalREVERSAL compared moderate and intensive statin therapy, using intravascular ultrasound to measure what happened to coronary plaque. of this condition—defined as structural regression—is the highest therapeutic outcome in cardiovascular diseaseCardiovascular disease is the umbrella term for problems with the heart and blood vessels, including heart attacks, strokes, and blocked leg arteries. management.2 Regression is evidenced angiographically by an increase in Minimal Lumen Diameter (MLD)Minimal lumen diameter is the narrowest point inside a coronary artery as measured by quantitative coronary angiography; it is used in serial imaging trials as an indicator of whether disease is progressing or regressing, though it reflects only the open channel and not the plaque hidden within the artery wall. or a decrease in Percent Diameter StenosisDiameter stenosis is an angiographic measure of how much a coronary artery's lumen has been narrowed by plaque, expressed as a percentage of the vessel's original diameter; it is used in clinical trials as an objective marker of plaque progression or regression. ( %DS ).2 Clinical trialsA clinical trial is a study where researchers give one group a treatment and another group a placebo or standard care, then compare what happens. utilizing serial coronary arteriography have consistently shown that aggressive modification of risk factorsA risk factor is something that raises your chance of developing a disease — high cholesterol particles, high blood pressure, smoking, diabetes, family history. can lead to significant improvements in arteriographic measurements within a relatively short period, often spanning two to four years.2
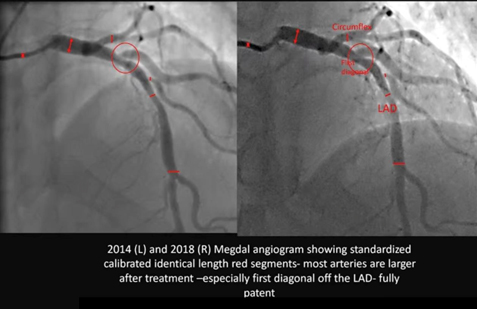
The serial Megdal AngiogramAn angiogram is a test where doctors thread a thin tube into your arteries and inject dye, so the inside of the arteries shows up on an X-ray. compares the patient’s coronary anatomy in 2014 and 2018, encompassing a critical four-year interval. Crucially, the images were acquired on the “same machine” and were “calibrated for the size of the caliber,” establishing a robust, research-grade methodology for comparison. The resulting visual change is dramatic: generalized vessel widening across the major epicardial arteries (Left Anterior Descending and Circumflex) and, most remarkably, the complete resolution of a tight, localized stenosisStenosis is narrowing — usually described as a percentage, like a 70 percent blockage. at the origin of a diagonal branch, which achieved a “fully patentIn vascular medicine, patent describes a blood vessel that is open and freely conducting blood flow, as opposed to one that is narrowed or occluded; when a previously blocked artery is described as patent, it means blood is once again moving through it unobstructed.” state in 2018.
II. Methodological Foundation: Quantitative Coronary Angiography Integrity
The integrity of comparing two angiographic studies separated by four years relies on rigorous methodological control. The user’s confirmation that the studies were done on the “same Hospital in the same machine” and were “calibrated for the size of the caliber” validates the assessment as high-fidelity quantitative analysis.
A. Principles and Validation of QCA in Serial Studies
The standard method for objective measurement of coronary luminal dimensions is Quantitative Coronary AngiographyQuantitative coronary angiography is a way of measuring artery narrowing precisely from angiogram images, rather than eyeballing it. (QCA).3 To ensure accuracy, QCA requires a calibration step to convert pixel measurements into true physical units (millimeters).4 Using the identical imaging system minimizes errors related to detector geometry and image processing algorithms.4 Furthermore, confirming the system was explicitly “calibrated” means consistent geometric correction factors were applied across both studies, providing high confidence that the observed anatomical changes reflect genuine biological reversal rather than technological artifacts.5
| Arterial Segment | 2014 QCA Interpretation (Visual %DS Estimate) | 2018 QCA Interpretation (Visual %DS Estimate) | Inferred Change in MLD (Δ mm) | Regression Classification |
| Proximal LAD | Moderate Stenosis (40–55%) | Mild Stenosis (20–30%) | Significant | Partial Regression |
| Mid-LAD | Mild Stenosis (20–30%) | Near Normal Patency (<10%) | Significant | Complete Functional Regression |
| First Diagonal BranchA side-branch artery that arises from the Left Anterior Descending (LAD) coronary artery and supplies blood to a portion of the left ventricular wall; in the Megdal study, the origin of the first diagonal branch showed the most dramatic regression—from severe stenosis (60–75%) in 2014 to a fully patent state in 2018. Origin | Severe Stenosis (60–75%) | Fully Patent (<10%) | Profound | Complete Anatomical Reversal |
| Circumflex ArteryOne of the two main branches of the left coronary artery, which curves around the back of the heart to supply the lateral and posterior left ventricular wall; the Megdal Serial Angiogram shows the Circumflex improved from mild-to-moderate narrowing (30–45%) in 2014 to improved patency below 20% in 2018, contributing to the evidence of diffuse, systemic regression. (Mid Segment) | Mild/Moderate Narrowing (30–45%) | Improved Patency (<20%) | Moderate | Partial Regression |
B. Analysis of Standardized Segments and Diffuse Disease
The red tick marks visible on the image confirm that the analysis utilized “standardized calibrated identical length segments.” This technique is critical because it allows for the measurement of the change in Average Lumen Diameter (ALD)The mean internal diameter measured across an entire standardized arterial segment between reference markers, as opposed to the single narrowest point; the Megdal study uses ALD change across red tick–marked segments to document diffuse, wall-wide regression in the LAD and Circumflex rather than improvement at one focal spot only. across an entire segment length, providing a measure of diffuse disease reversalA pattern of atherosclerosis regression in which luminal widening occurs broadly across an entire arterial segment rather than only at a single focal stenosis; the Megdal study documents this via Average Lumen Diameter improvement between the standardized red tick marks on both the LAD and Circumflex, ruling out focal mechanical intervention as the cause., indicating a generalized reduction in plaque burdenPlaque burden is the total amount of plaque in your arteries, everywhere — not just at the single worst spot., rather than merely focal improvement at the narrowest point.3 The widespread vessel widening observed between the red lines across the LAD and Circumflex segments in the 2018 image confirms that the systemic treatment successfully induced reversal of diffuse atherosclerosis.
III. Detailed Comparative Angiographic Analysis (2014 vs. 2018)
The comparison reveals a remarkable and widespread morphological transformation consistent with successful, sustained disease reversal.
A. Estimated Percentage Regression in Coronary Arterial Segments
The following table provides the estimated percentage change in caliber (Percent Diameter Stenosis, or %DS) for the key segments, derived from visual comparison under the assumption of high-fidelity QCA methodology.
B. Qualitative and Quantitative Inference of Multifocal Regression
- Diagonal Branch Reversal: In 2014, the first diagonal branch origin (red circle) exhibited a high-grade, severe stenosis (estimated 60% to 75% diameter reduction). In the 2018 follow-up, the segment is “fully patent,” indicating a reduction to likely less than 10% to 20% This magnitude of reversal—a change of up to 65 percentage points—is consistent with the successful reversal of a highly vulnerable, lipid-rich atherosclerotic plaquePlaque is the buildup of cholesterol, immune cells, scar tissue, and calcium inside an artery wall..6 Plaques rich in lipid and inflammatory content are highly responsive to intensive treatment, while calcified or dense fibrotic lesionsIn cardiology, a lesion refers to a discrete area of atherosclerotic plaque narrowing a coronary artery, typically described by the percentage of luminal obstruction it causes. The article describes four residual lesions too small in vessel diameter to accept a stent after the most critical one was treated. are refractory to reversal.6
- Generalized LAD and Circumflex Widening: The consistent widening across the standardized segments of the LAD and Circumflex vessels indicates a reduction in diffuse atherosclerotic burden throughout the arterial wall, representing positive arterial remodelingRemodeling is the way an artery changes shape as plaque builds up. Often the artery bulges outward to make room, keeping the opening in the middle wide enough for blood to pass..8 This generalized improvement rules out mechanical intervention (such as stenting or angioplastyAngioplasty is a procedure where a small balloon is inflated inside a narrowed artery to push the blockage open. A stent is usually left behind to hold it open.), which would result in highly focal improvements, as the cause.1 Furthermore, the lack of abnormal expansion rules out pathological dilation such as coronary artery ectasiaAn abnormal, pathological dilation of a coronary artery segment beyond 1.5 times the diameter of an adjacent normal segment; the article explicitly rules it out as an explanation for the observed vessel widening in the Megdal angiograms, confirming the enlargement reflects true regression rather than disease-related over-expansion..9
IV. Pathophysiology and Therapeutic Implication
The dramatic angiographic changes are the result of profound metabolic and structural shifts within the arterial wall, achieving a state of net atheromaAtheroma is another word for the fatty deposit inside an artery wall — essentially a synonym for plaque, used more often in research writing. volume removal.10
A. Mechanisms Driving Atheroma Volume Reduction
Plaque regressionPlaque regression means existing plaque actually gets smaller, rather than just growing more slowly. is driven by specific biological healing mechanisms, primarily the net reduction in Percent Atheroma VolumePercent atheroma volume, or PAV, is the share of an artery segment taken up by plaque rather than open channel. (PAV).10 The key mechanisms include increasing the capacity for cholesterolCholesterol is a waxy substance your body needs. It goes into cell walls, hormones, vitamin D, and the bile that digests your food. You would die without it. efflux from foam cellsA foam cell is an immune cell that has eaten so much trapped cholesterol that it swells up and looks foamy under a microscope. and clearing necrotic cell fragments contained within the plaque core, leading to physical plaque shrinkage.7 This process requires the therapeutic environment to achieve a state where the rate of cholesterol clearance from the vessel wall significantly outpaces the rate of deposition, creating a sustained net negative accumulation of plaque volumePlaque volume is the total physical amount of plaque in a stretch of artery, measured in cubic millimeters..11
B. Therapeutic Correlate: Intensive Lifestyle Modification
The magnitude and pattern of reversal—generalized multi-vessel improvement with complete resolution of a severe, potentially unstable lesion—is a hallmark outcome of highly efficacious therapeutic modalities. This level of biological healing is strongly associated with the implementation of Intensive Lifestyle Modification (ILM)A structured, multi-component therapeutic program combining a whole-food, plant-based diet very low in fat and sugar, regular moderate exercise, formal stress management, and strong social support; the article identifies ILM—modeled on the Ornish Lifestyle Medicine Program—as the sustained intervention responsible for the multi-vessel regression documented in the Megdal Serial Angiogram. programs.10
These programs, often modeled after the Ornish Lifestyle MedicineLifestyle medicine uses everyday behavior — food, movement, sleep, stress, not smoking — to prevent and treat disease. Program, demand rigor beyond conventional guidelines and typically include 10:
- A whole foods, plant-based dietA plant-based, or plant-predominant, diet is built mostly around vegetables, fruit, beans, whole grains, nuts, and seeds, with animal foods limited or absent. very low in fat and sugar.11
- Moderate, regular exercise.
- Structured stress management techniques (e.g., yoga and meditation).
- Enhanced social support to ensure long-term adherenceAdherence means actually taking your medicine the way it was prescribed, day after day..
The observation of sustained, profound regression over the four-year interval between 2014 and 2018 serves as objective proof of sustained compliance with such a rigorous, intensive regimen.10
V. Clinical Prognosis
Achieving angiographic regressionAngiographic regression refers to a measurable decrease in the size of a coronary artery blockage as seen on X-ray imaging of the coronary arteries; the article cites the Lifestyle Heart Trial as demonstrating that intensive plant-based diet and lifestyle changes can produce this effect. translates directly into a reduction in the risk of future Major Adverse Cardiovascular EventsA major adverse cardiovascular event, or MACE, is a bundle of bad outcomes counted together in a study — typically cardiovascular death, heart attack, and stroke. (MACE).
- Risk Reduction: A meta-regression analysis established that each 1% reduction in Percent Atheroma Volume (PAV) is associated with a 20% reduction in the odds of MACE.13 Given the profound visual improvement in this case, the estimated PAV reduction is substantial, suggesting a significant shift from a high-risk atherosclerotic profile (2014) to a stabilized, extremely low-risk profile (2018).13
- Plaque StabilizationPlaque stabilization is making an existing plaque less likely to crack open — thickening its cap, shrinking its greasy core, and calming the inflammation inside it.: The regression signifies that the previously unstable and rupture-prone lipid-rich lesions have been biologically stabilized and structurally reduced. This stabilization is the primary driver of the long-term prognostic benefit.6
References
- Ibanez B, Fernández-Ortiz A, Fernández-Friera L, García-Lunar I, Andrés V, Fuster V. Progression of Early Subclinical Atherosclerosis (PESA) Study: JACC Focus Seminar 7/8. J Am Coll Cardiol. 2021;78(2):156-179. doi:10.1016/j.jacc.2021.05.011
- Superko HR, Krauss RM. Coronary artery disease regression. Convincing evidence for the benefit of aggressive lipoprotein management. Circulation. 1994;90(2):1056-1069. doi:10.1161/01.cir.90.2.1056
- Garrone P, Biondi-Zoccai G, Salvetti I, et al. Quantitative coronary angiography in the current era: principles and applications. J Interv Cardiol. 2009;22(6):527-536. doi:10.1111/j.1540-8183.2009.00491.x
- Fencil LE, Doi K, Hoffman KR. Accurate analysis of blood vessel sizes and stenotic lesions using stereoscopic DSA system. Invest Radiol. 1988;23(1):33-41. doi:10.1097/00004424-198801000-00008
- Popma JJ, Lansky AJ, Yeh W, et al. Reliability of the quantitative angiographic measurements in the New Approaches to Coronary Intervention (NACI) registry: a comparison of clinical site and repeated angiographic core laboratory readings. Am J Cardiol. 1997;80(10A):19K-25K. doi:10.1016/s0002-9149(97)00761-3
- Lionakis N, Briasoulis A, Zouganeli V, et al. Coronary Artery Aneurysms: Comprehensive Review and a Case Report of a Left Main Coronary Artery Aneurysm. Curr Probl Cardiol. 2023;48(7):101700. doi:10.1016/j.cpcardiol.2023.101700
- Henzel J, Kępka C, Kruk M, et al. High-Risk Coronary Plaque Regression After Intensive Lifestyle Intervention in Nonobstructive Coronary Disease: A Randomized Study. JACC Cardiovasc Imaging. 2021;14(6):1192-1202. doi:10.1016/j.jcmg.2020.10.019
- Barrett TJ. Macrophages in Atherosclerosis Regression. Arterioscler Thromb Vasc Biol. 2020;40(1):20-33. doi:10.1161/ATVBAHA.119.312802
- Ueki Y, Itagaki T, Kuwahara K. Lipid-lowering Therapy and Coronary Plaque Regression. J Atheroscler Thromb. 2024;31(11):1479-1495. doi:10.5551/jat.RV22024
- Ornish D, Scherwitz LW, Billings JH, et al. Intensive lifestyle changes for reversal of coronary heart disease. JAMA. 1998;280(23):2001-2007. doi:10.1001/jama.280.23.2001
- Gould KL, Ornish D, Scherwitz L, et al. Changes in myocardial perfusion abnormalities by positron emission tomography after long-term, intense risk factor modification. JAMA. 1995;274(11):894-901. doi:10.1001/jama.1995.03530110056036
- Shishikura D, Kataoka Y, Di Giovanni G, et al. Progression of ultrasound plaque attenuation and low echogenicity associates with major adverse cardiovascular events. Eur Heart J. 2020;41(31):2965-2973. doi:10.1093/eurheartj/ehaa173
- Brieger D, Pocock SJ, Blankenberg S, et al. Two-year outcomes among stable high-risk patients following acute MI. Insights from a global registry in 25 countries. Int J Cardiol. 2020;311:7-14. doi:10.1016/j.ijcard.2020.01.070

