
The clinical assessment of coronary artery calcium (CAC)Coronary artery calcium is a measure of calcified plaque deposits in the walls of the coronary arteries, quantified by CT scan and expressed as an Agatston score; higher scores indicate greater cumulative plaque burden and predict future cardiovascular events. has undergone a paradigm shift over the past three decades, evolving from a research tool to a central instrument in cardiovascular risk stratification. Central to this transformation is the concept of the coronary artery calcium scoreA coronary artery calcium score, or CAC score, comes from a quick CT scan that measures how much hardened plaque is in your heart's arteries. No dye, no needles, about ten minutes. of zero—commonly referred to as the “power of zero”—which has emerged as one of the most powerful negative risk markers in preventive cardiology [1]. In appropriately selected populations, a CAC score of zero confers substantial short- and intermediate-term prognostic reassurance. However, the interpretation of CAC = 0 is not uniform across clinical contexts. Residual riskResidual risk is the risk that remains after you have done the obvious things — cholesterol treated, blood pressure controlled, not smoking. diverges significantly between asymptomatic individuals undergoing primary preventionPrimary prevention is treating someone who has never had a heart attack or stroke, to keep the first one from happening. screening and symptomatic patients presenting with chest pain.
The presence of coronary calcium represents a biologic response to chronic lipid infiltration and inflammationInflammation is your immune system's response to injury or something it treats as an invader. It brings swelling, heat, and cleanup cells. within the arterial intimaThe intima is the innermost layer of an artery wall, sitting just beneath the smooth lining. [2]. CalcificationCalcification is when calcium gets deposited into a plaque, turning part of it hard and bony. reflects advanced atherosclerotic remodeling involving osteogenic differentiationA biological process in which vascular smooth muscle cells or other arterial wall cells adopt a bone-cell-like phenotype and deposit calcium-containing mineral, driving plaque calcification; it is a key mechanism underlying the formation of coronary artery calcium. and extracellular matrixThe extracellular matrix is the scaffolding of collagen and other fibers that holds tissue together and gives an artery wall its strength. changes. However, calcification detectable on non-contrast CT captures only macroscopic mineralization and does not quantify non-calcified plaqueNon-calcified plaque is the soft, fatty portion of a plaque that has not hardened with calcium. It shows up dark on a CT scan. components, including lipid-rich necrotic coresThe lipid-rich necrotic core is the soft, fat- and inflammatory-cell-laden interior of an advanced atherosclerotic plaque; it is the most rupture-prone compartment and the one most responsive to lipid lowering, which can shrink and stabilize it even when surrounding calcified tissue remains. and fibrous tissue [3]. Thus, absence of calcium does not equate to absence of atherosclerosisAtherosclerosis is the disease behind most heart attacks and many strokes. Cholesterol particles get stuck in the wall of an artery, the body sends immune cells to clean up, and over years that mess hardens into plaque..
Biological Foundations of Coronary Calcification
CAC scoring is performed using non-contrast, ECG-gated CTA CT imaging technique that synchronizes image acquisition to the electrical signal of the heart recorded by an electrocardiogram, minimizing motion blur so that coronary structures can be measured accurately; it is the standard method for CAC scoring. imaging. The Agatston scoreThe Agatston score is the specific formula used to turn a calcium CT scan into a single number, weighting each calcium deposit by how dense and how large it is. multiplies plaquePlaque is the buildup of cholesterol, immune cells, scar tissue, and calcium inside an artery wall. area by a density weighting factor derived from peak attenuation ≥130 Hounsfield Units (HU)A standardized scale of radiodensity used in CT imaging, where water is defined as 0 HU and denser materials register higher values; in CAC scoring, a threshold of ≥130 HU is used to identify calcified coronary plaque when applying the Agatston method. [2]. LesionsIn cardiology, a lesion refers to a discrete area of atherosclerotic plaque narrowing a coronary artery, typically described by the percentage of luminal obstruction it causes. The article describes four residual lesions too small in vessel diameter to accept a stent after the most critical one was treated. below this threshold are not considered calcified.
In contrast-enhanced coronary CT angiographyCoronary CT angiography, or CCTA, is a CT scan done with dye in your veins that produces detailed pictures of your heart's arteries. (CCTA), plaque characterization differentiates necrotic coreThe necrotic core is the dead, mushy center of an advanced plaque, built from immune cells that ate trapped cholesterol and then died in place., fibrofatty, fibrous, and calcified components based on attenuation ranges [3]. Importantly, rupture-prone plaques frequently contain large necrotic cores with thin fibrous capsThe fibrous cap is the tough layer of tissue covering a plaque, separating its greasy core from the bloodstream. and minimal macrocalcificationLarge, macroscopic deposits of calcium within atherosclerotic plaque that are visible on standard non-contrast CT imaging; macrocalcification generally reflects plaque stabilization and healing rather than active instability. [4].
A critical mechanistic distinction exists between macrocalcification and microcalcificationMicroscopic calcium deposits within atherosclerotic plaque that fall below the resolution threshold of conventional CT; unlike dense macrocalcification, microcalcifications can generate mechanical stress within the fibrous cap and increase plaque rupture susceptibility.. Dense macrocalcification visible on CT often reflects plaque stabilizationPlaque stabilization is making an existing plaque less likely to crack open — thickening its cap, shrinking its greasy core, and calming the inflammation inside it. and healing. In contrast, microscopic calcifications—below CT resolution—can generate mechanical stress within the fibrous cap and increase rupture susceptibility [5]. Therefore, CAC = 0 excludes macroscopic calcification but does not exclude microcalcific activity or vulnerable plaqueA vulnerable plaque is one at high risk of cracking open: a thin cap, a large greasy core, active inflammation, and often outward bulging of the artery. biology.
The Asymptomatic Population: The Power of Zero
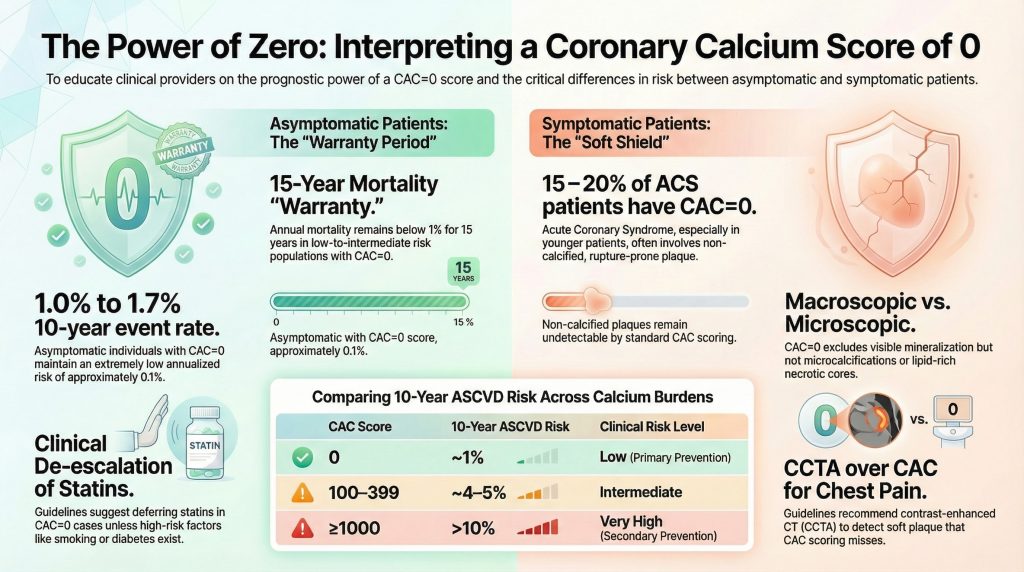
In the Multi-Ethnic Study of Atherosclerosis (MESA)A large prospective cohort study of adults initially free of cardiovascular disease that has provided foundational data on coronary artery calcium scoring, demonstrating a strong graded association between CAC burden and future coronary events and validating the risk implications of a CAC score of zero., approximately 50% of middle-aged asymptomatic adults demonstrated CAC = 0 at baseline [6]. Long-term follow-up revealed 10-year ASCVD event rates of approximately 1–1.7% among these individuals, corresponding to an annualized risk near 0.1% [6,7]. These event rates are substantially lower than predicted by traditional risk models in many intermediate-risk individuals.
Even minimal calcification (CAC 1–10) confers approximately a threefold increase in coronary heart diseaseCoronary heart disease is the narrowing or blockage of the arteries that supply blood to the heart muscle, caused by the buildup of atherosclerotic plaque; it is the leading cause of heart attack and cardiac death worldwide. risk compared with CAC = 0 [6]. Thus, CAC = 0 represents a biologically distinct low-risk phenotype rather than merely the lowest point on a continuum.
Graded Risk Across CAC Categories
Risk increases stepwise with rising calcium burden [7,8]:
- CAC = 0: ~1% 10-year risk
- CAC 1–99: ~1.9% 10-year risk
- CAC 100–399: ~4–5% 10-year risk
- CAC ≥400: ~7–9% 10-year risk
- CAC ≥1000: >10%, approaching secondary-prevention populations
Individuals with CAC ≥1000 exhibit cardiovascular mortality rates comparable to stable secondary-prevention cohorts, including those similar to FOURIER trialThe FOURIER trial evaluated the PCSK9 inhibitor evolocumab added to statin therapy and demonstrated that aggressively lowering ApoB-containing particles reduced cardiovascular events; analysis also showed that patients who achieved very low LDL-C but retained high hs-CRP still faced elevated residual risk, supporting the dual-risk model of atherogenesis. participants [8]. This observation supports aggressive lipid-lowering strategies in extreme CAC categories.
NNT Modeling and Therapeutic Allocation
CAC scoring refines statinA statin slows the enzyme your liver uses to make cholesterol. Your liver responds by pulling more cholesterol out of your blood, which is where the real benefit comes from. allocation efficiency. Among intermediate-risk individuals:
- CAC = 0: 5-year Number Needed to TreatNumber needed to treat, or NNT, is how many people must take a treatment for one of them to benefit. (NNT) often exceeds 100
• CAC >100: 5-year NNT often ranges between 12–25 [1,9]
Most absolute statin benefit accrues to patients with measurable calcified burden. The 2018 ACC/AHA cholesterol guidelinesA major United States clinical practice guideline for blood cholesterol management that incorporated CAC scoring as a decision aid; it recommends that statin therapy may be deferred in asymptomatic intermediate-risk individuals who have a CAC score of zero, unless diabetes, active smoking, or strong family history of premature cardiovascular disease is present. recommend that statin therapy may be deferred in asymptomatic individuals with CAC = 0 unless diabetesDiabetes is a condition where blood sugar stays too high, either because the body makes too little insulin or because it stops responding to the insulin it makes., smokingSmoking damages the lining of your blood vessels, raises blood pressure, makes blood clot more easily, and speeds up plaque growth., or strong family historyFamily history means whether your close relatives developed heart disease, and how young they were when it happened. is present [9].
Soft Plaque and “Warranty” Periods
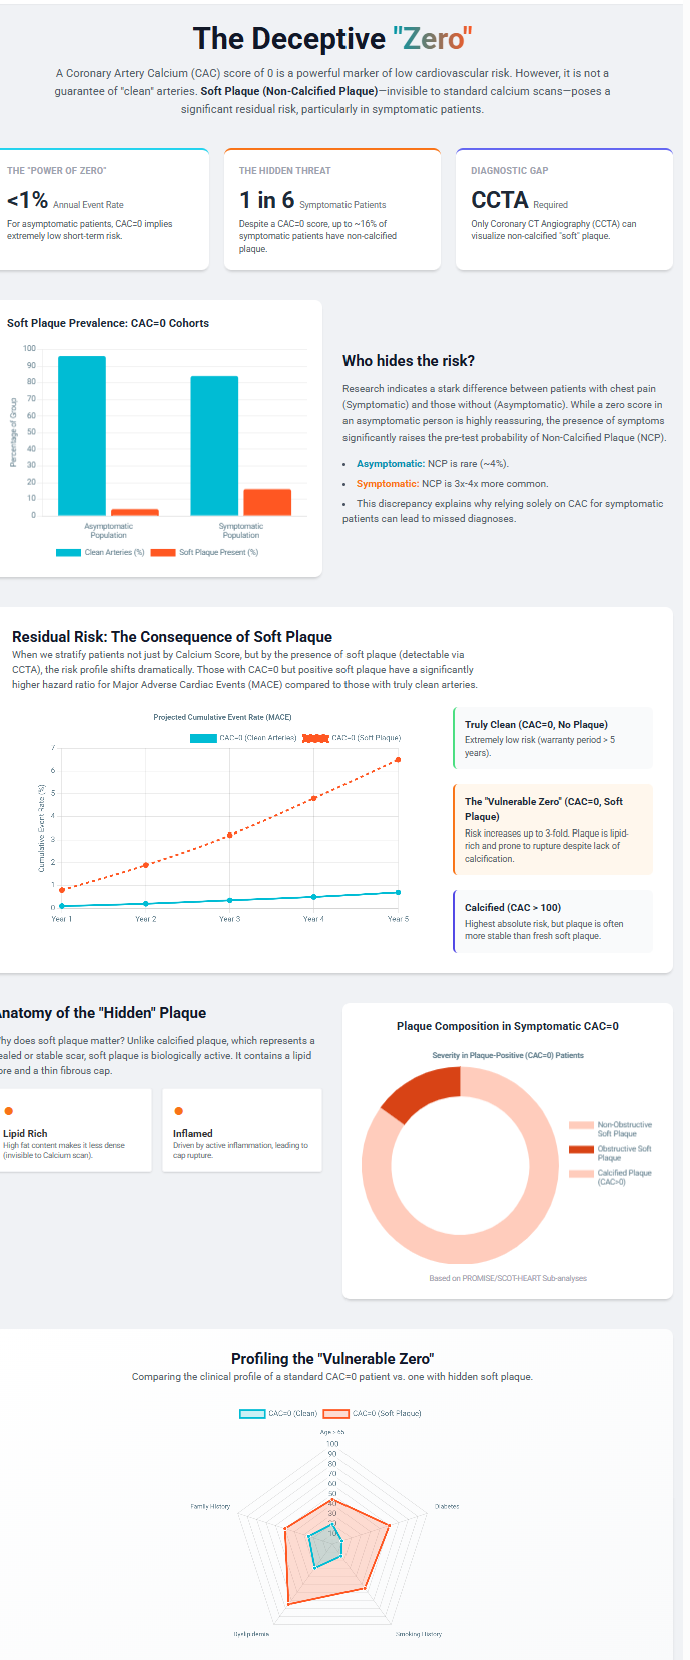
The Miami Heart Study demonstrated that approximately 16% of asymptomatic individuals with CAC = 0 have non-calcified plaque on CCTA [10]. However, obstructive stenosisStenosis is narrowing — usually described as a percentage, like a 70 percent blockage. (≥50%) was present in only 0.8%, and high-risk plaque features were uncommon. Thus, while soft plaqueNon-calcified, lipid-rich atherosclerotic plaque that does not appear bright on a standard calcium score scan but is detectable by CT angiography; it is considered higher risk for rupture than fully calcified plaque. is detectable, it rarely reaches clinical significance in asymptomatic zero-CAC individuals.
A prospective study of 9,715 asymptomatic individuals demonstrated that CAC = 0 confers a 15-year mortality “warranty period” in low-to-intermediate risk populations [11]. Annual mortality remained below 1% during this interval. However, this warranty is shortened in diabetics and heavy smokers due to accelerated plaque progression [12].
Sex-Specific Nuance and Ethnic Variability
Women generally exhibit lower absolute CAC prevalence compared with men but may harbor a greater proportion of non-calcified plaque [13]. Consequently, while CAC = 0 remains prognostically powerful in women, symptomatic female patients may require more cautious interpretation. Women presenting with chest pain frequently demonstrate non-obstructive CAD or microvascular dysfunctionMicrovascular dysfunction is disease in the smallest blood vessels of the heart, too small to see on any angiogram., conditions not reliably captured by CAC scoring alone.
MESAMESA, the Multi-Ethnic Study of Atherosclerosis, followed thousands of adults with no known heart disease, scanning their arteries and tracking outcomes. demonstrated significant ethnic heterogeneity in CAC prevalence [6]. White individuals exhibit the highest CAC prevalence, followed by Hispanic, Black, and Chinese American populations. Despite differences in prevalence, event rates at comparable CAC levels are similar across ethnic groups, reinforcing that CAC = 0 confers prognostic reassurance across diverse populations.
The Symptomatic Population: Residual Risk
In patients presenting with stable chest pain, CAC = 0 does not exclude coronary disease. Approximately 7–16% demonstrate plaque on CCTA, and 1–2% have obstructive CAD ≥50% [14]. In the PROMISE trialA large randomized trial that evaluated CT angiography versus functional stress testing in symptomatic patients with stable chest pain; findings cited here showed that 16.5% of zero-CAC participants had non-obstructive coronary artery disease and 1.5% had obstructive disease, illustrating residual risk despite a zero calcium score., 16.5% of symptomatic zero-CAC patients had non-obstructive CAD, and 1.5% had obstructive disease [15].
Acute Coronary Syndrome and Zero CAC
Pooled analyses demonstrate that 15–20% of patients presenting with acute coronary syndromeAcute coronary syndrome (ACS) is the umbrella term for any sudden drop in blood flow to the heart — from unstable angina to a full heart attack — caused by a plaque suddenly rupturing or eroding. (ACS)—particularly younger individuals—may have CAC = 0 at presentation [16]. These findings reflect the predominance of non-calcified, rupture-prone plaque. Accordingly, the 2021 AHA/ACC Chest Pain Guideline recommends CCTA rather than CAC scoring when evaluating possible acute coronary syndrome [17].
Detailed Plaque Morphology: ICONIC Insights
The ICONIC trialA coronary CT angiography study that quantified specific plaque components in symptomatic patients with a CAC score of zero who subsequently developed acute coronary syndrome, revealing substantially greater fibrous, fibrofatty, and necrotic-core plaque volumes compared with matched controls who did not develop events. quantified plaque components in symptomatic zero-CAC patients who subsequently developed ACS [4]:
- Fibrous plaque: 29.4 mm³ (ACS) vs 5.5 mm³ (controls)
• Fibrofatty plaque: 27.3 mm³ vs 1.3 mm³
• Necrotic-core plaque: 2.8 mm³ vs 0.0 mm³
These quantitative differences confirm that substantial vulnerable plaque burdenPlaque burden is the total amount of plaque in your arteries, everywhere — not just at the single worst spot. may exist in the absence of detectable calcification.
Bayesian Interpretation and Risk Modifiers
Diagnostic performance depends on pre-test probabilityThe estimated likelihood that a patient has a particular condition before a diagnostic test is performed, based on symptoms, risk factors, and clinical context; in CAC interpretation, a symptomatic patient has a higher pre-test probability of coronary disease, so a zero score still leaves meaningful residual risk. [18]. In asymptomatic individuals with low baseline risk, CAC = 0 reduces post-test probability to near-negligible levels. In symptomatic patients with higher pre-test probability, residual risk remains clinically meaningful despite a zero score.
Additional risk modifiers must be considered. Parental premature cardiovascular diseaseCardiovascular disease is the umbrella term for problems with the heart and blood vessels, including heart attacks, strokes, and blocked leg arteries. independently increases risk, even among individuals with CAC = 0 [19]. Furthermore, an elevated Atherogenic Index of Plasma (AIP)A logarithmically derived ratio of triglycerides to HDL cholesterol used as a marker of atherogenic lipoprotein particle size and cardiovascular risk; the article notes that an elevated AIP correlates with coronary calcium burden and major adverse cardiovascular events independent of traditional risk factors. correlates with calcification burden and major adverse cardiovascular eventsA major adverse cardiovascular event, or MACE, is a bundle of bad outcomes counted together in a study — typically cardiovascular death, heart attack, and stroke. independent of traditional risk factorsA risk factor is something that raises your chance of developing a disease — high cholesterol particles, high blood pressure, smoking, diabetes, family history. [20].
Conclusion
The coronary arteryAn artery is a blood vessel that carries blood away from the heart to the rest of the body. calcium scoreA calcium score (coronary artery calcium score) is a number derived from a CT scan that quantifies the total amount of calcified plaque in the coronary arteries; a score of zero indicates no detectable calcified plaque, while higher scores reflect greater plaque burden and elevated cardiovascular risk. of zero is among the most powerful negative risk markers in cardiovascular medicine. In asymptomatic individuals, it confers a prolonged mortality warranty and supports selective de-escalation of pharmacotherapy. In symptomatic patients, however, CAC = 0 represents a “soft shield”—associated with lower risk than positive scores but insufficient to exclude obstructive or vulnerable plaque. Future risk stratification must integrate calcified and non-calcified plaque assessment, clinical phenotype, and individualized risk modifiers rather than relying solely on binary calcium absence.
References
- Hussain A, Ballantyne CM, Nambi V. Zero Coronary Artery Calcium Score: Desirable, but Enough?. Circulation. 2020;142(10):917-919. doi:10.1161/CIRCULATIONAHA.119.045026
- Czaja-Ziółkowska MZ, Wasilewski J, Gąsior M, Głowacki J. An update on the coronary calcium score: a review for clinicians. Postepy Kardiol Interwencyjnej. 2022;18(3):201-205. doi:10.5114/aic.2022.121035
- Vatsa N, Faaborg-Andersen C, Dong T, Blaha MJ, Shaw LJ, Quintana RA. Coronary Atherosclerotic Plaque Burden Assessment by Computed Tomography and Its Clinical Implications. Circ Cardiovasc Imaging. 2024;17(8):e016443. doi:10.1161/CIRCIMAGING.123.016443
- Jonas RA, Nurmohamed NS, Crabtree TR, et al. CTA-Derived Plaque Characteristics and Risk of Acute Coronary Syndrome in Patients With Coronary Artery Calcium Score of Zero: Insights From the ICONIC Trial. AJR Am J Roentgenol. 2025;225(1):e2431476. doi:10.2214/AJR.24.31476
- Hutcheson JD, Goettsch C, Bertazzo S, et al. Genesis and growth of extracellular-vesicle-derived microcalcification in atherosclerotic plaques. Nat Mater. 2016;15(3):335-343. doi:10.1038/nmat4519
- Detrano R, Guerci AD, Carr JJ, et al. Coronary calcium as a predictor of coronary events in four racial or ethnic groups. N Engl J Med. 2008;358(13):1336-1345. doi:10.1056/NEJMoa072100
- Budoff MJ, Shaw LJ, Liu ST, et al. Long-term prognosis associated with coronary calcification: observations from a registry of 25,253 patients. J Am Coll Cardiol. 2007;49(18):1860-1870. doi:10.1016/j.jacc.2006.10.079
- Dzaye O, Razavi AC, Michos ED, et al. Coronary artery calcium scores indicating secondary prevention level risk: Findings from the CAC consortium and FOURIER trial. Atherosclerosis. 2022;347:70-76. doi:10.1016/j.atherosclerosis.2022.02.006
- Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol: A Report of the American College of Cardiology/American Heart Association Task Force on Clinical Practice Guidelines. Circulation. 2019;139(25):e1082-e1143. doi:10.1161/CIR.0000000000000625
- Nasir K, Cainzos-Achirica M, Valero-Elizondo J, et al. Coronary Atherosclerosis in an Asymptomatic U.S. Population: Miami Heart Study at Baptist Health South Florida. JACC Cardiovasc Imaging. 2022;15(9):1604-1618. doi:10.1016/j.jcmg.2022.03.010
- Valenti V, Ó Hartaigh B, Heo R, et al. A 15-Year Warranty Period for Asymptomatic Individuals Without Coronary Artery Calcium: A Prospective Follow-Up of 9,715 Individuals. JACC Cardiovasc Imaging. 2015;8(8):900-909. doi:10.1016/j.jcmg.2015.01.025
- McClelland RL, Jorgensen NW, Budoff M, et al. 10-Year Coronary Heart Disease Risk Prediction Using Coronary Artery Calcium and Traditional Risk Factors: Derivation in the MESA (Multi-Ethnic Study of Atherosclerosis) With Validation in the HNR (Heinz Nixdorf Recall) Study and the DHS (Dallas Heart Study). J Am Coll Cardiol. 2015;66(15):1643-1653. doi:10.1016/j.jacc.2015.08.035
- Shaw LJ, Raggi P, Callister TQ, Berman DS. Prognostic value of coronary artery calcium screening in asymptomatic smokers and non-smokers. Eur Heart J. 2006;27(8):968-975. doi:10.1093/eurheartj/ehi750
- Wang X, Le EPV, Rajani NK, et al. A zero coronary artery calcium score in patients with stable chest pain is associated with a good prognosis, despite risk of non-calcified plaques. Open Heart. 2019;6(1):e000945. Published 2019 Apr 11. doi:10.1136/openhrt-2018-000945
- Foldyna B, Mayrhofer T, Lu MT, et al. Prognostic value of CT-derived coronary artery disease characteristics varies by ASCVD risk: insights from the PROMISE trial. Eur Radiol. 2023;33(7):4657-4667. doi:10.1007/s00330-023-09430-5
- Gottlieb I, Miller JM, Arbab-Zadeh A, et al. The absence of coronary calcification does not exclude obstructive coronary artery disease or the need for revascularization in patients referred for conventional coronary angiography. J Am Coll Cardiol. 2010;55(7):627-634. doi:10.1016/j.jacc.2009.07.072
- Gulati M, Levy PD, Mukherjee D, et al. 2021 AHA/ACC/ASE/CHEST/SAEM/SCCT/SCMR Guideline for the Evaluation and Diagnosis of Chest Pain: A Report of the American College of Cardiology/American Heart Association Joint Committee on Clinical Practice Guidelines. Circulation. 2021;144(22):e368-e454. doi:10.1161/CIR.0000000000001029
- Greenland P, Bonow RO, Brundage BH, et al. ACCF/AHA 2007 clinical expert consensus document on coronary artery calcium scoring by computed tomography in global cardiovascular risk assessment and in evaluation of patients with chest pain: a report of the American College of Cardiology Foundation Clinical Expert Consensus Task Force (ACCF/AHA Writing Committee to Update the 2000 Expert Consensus Document on Electron Beam Computed Tomography). Circulation. 2007;115(3):402-426. doi:10.1161/CIRCULATIONAHA..107.181425
- Lloyd-Jones DM, Nam BH, D’Agostino RB Sr, et al. Parental cardiovascular disease as a risk factor for cardiovascular disease in middle-aged adults: a prospective study of parents and offspring. JAMA. 2004;291(18):2204-2211. doi:10.1001/jama.291.18.2204
- Yao H, Feng G, Liu Y, Chen Y, Shao C, Wang Z. Coronary artery calcification burden, atherogenic index of plasma, and risk of adverse cardiovascular events in the general population: evidence from a mediation analysis. Lipids Health Dis. 2024;23(1):258. Published 2024 Aug 20. doi:10.1186/s12944-024-02255-1

