
The Causal Role of Low-Density Lipoprotein in Atherosclerotic Cardiovascular Disease: Evidence Synthesis, Metabolic Context, and Scientific Epistemology
Abstract
The identification of low-density lipoproteinA lipoprotein is a tiny package that carries fat and cholesterol through your bloodstream. Since fat won't dissolve in water, it needs a protein wrapper to travel. (LDLLDL, or low-density lipoprotein, is the main particle that carries cholesterol through your blood — and the main one that gets stuck in artery walls.) as a causal agent in atherosclerotic cardiovascular diseaseCardiovascular disease is the umbrella term for problems with the heart and blood vessels, including heart attacks, strokes, and blocked leg arteries. (ASCVD) represents one of the most rigorously tested paradigms in modern medicine. This conclusion is supported by converging evidence from lifelong genetic exposure studies using Mendelian randomizationMendelian randomization is a clever research method that uses the genes people were born with as a natural experiment., large-scale prospective epidemiologyEpidemiology is the study of health patterns in large groups of people — who gets sick, where, and what they had in common., and randomized controlled trialsA randomized controlled trial assigns people to a treatment or a comparison group purely by chance, then follows both groups. (RCTs). In recent years, an intellectual movement has emerged, primarily within the ketogenic and low-carbohydrate communities, challenging the universality of this causal relationship. This movement is exemplified by the ‘Lean Mass Hyper-ResponderA lean mass hyper-responder is someone lean and athletic whose LDL cholesterol rises enormously on a low-carbohydrate diet — sometimes to levels normally seen only in inherited disorders.’ (LMHR) phenotype and the associated ‘Lipid Energy Model’ (LEM), which propose that in individuals with high insulin sensitivityInsulin sensitivity is how well your cells respond to insulin. It is the opposite of insulin resistance. and lean body mass, elevated LDL-C may not carry equivalent pathological implications. This paper analyzes the epistemological landscape of this debate, evaluates the strength of evidence on both sides, and proposes a framework for productive clinical communication with metabolically informed skeptics.
1. Introduction
The existence of skepticism regarding LDL’s causal role in ASCVD frequently arises from legitimate inquiry into the limitations of population-level data when applied to unique metabolic contexts. Healthy scientific skepticism serves as a necessary mechanism for paradigm refinement, ensuring that models account for edge cases and anomalous data. Within lipidology, this skepticism is often catalyzed by the observation of high-functioning, metabolically healthy individuals who exhibit lipid profilesA blood test panel that measures total cholesterol, LDL cholesterol, HDL cholesterol, and triglycerides, used to assess cardiovascular risk and monitor the effect of dietary or drug interventions. that traditional guidelines would classify as high-risk.
Distinguishing between healthy skepticism, contrarianism, and conspiracy-style reasoning is essential for productive dialogue. Healthy skepticism seeks to expand models to include new data. Contrarianism defines itself in opposition to institutional consensus, often prioritizing a single contradictory data set over the totality of the field. Conspiracy-style reasoning goes further, suggesting that the consensus is intentionally deceptive, sometimes citing pharmaceutical industry influence on clinical guidelines. Labeling all dissent as ‘misinformation’ can be counterproductive, as it alienates intelligent observers who perceive such labeling as an appeal to authority rather than transparent engagement with underlying data.
2. The Persuasiveness of Contemporary Skeptical Arguments
Arguments presented by proponents of the Lipid Energy Model resonate with a specific audience because they provide a sophisticated, mechanistic narrative that addresses the felt experience of individuals on carbohydrate-restricted diets (CRDs). Their communication strategies are characterized by several distinct patterns that build internal consistency within their models.
2.1 The Lipid Energy Model and Metabolic Context
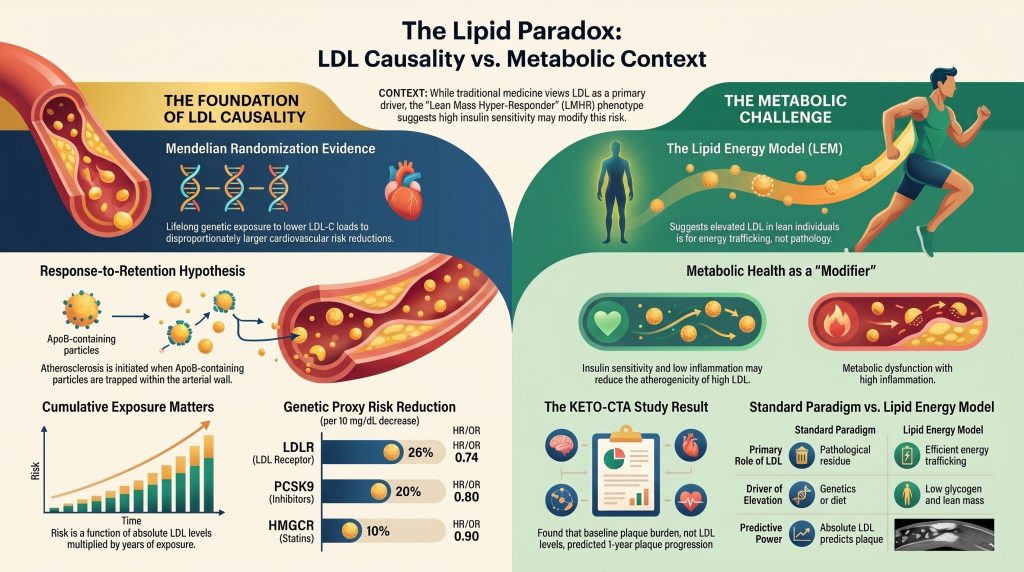
The cornerstone of modern LDL skepticism is the transition from evaluating LDL-C as an isolated risk factorA risk factor is something that raises your chance of developing a disease — high cholesterol particles, high blood pressure, smoking, diabetes, family history. to assessing it within a broader metabolic framework. Skeptics emphasize markers of insulinInsulin is a hormone made by your pancreas. Its main job is letting sugar move out of your blood and into your cells for fuel. sensitivity—such as a low triglyceride to HDL-C ratio—arguing that high-quality metabolic markers render elevated LDL-C benign. The Lipid Energy Model (LEM)The Lipid Energy Model proposes that in lean, insulin-sensitive individuals with low hepatic glycogen—such as those on ketogenic diets—the liver upregulates VLDL export to supply fat fuel to peripheral tissues, causing LDL-C to rise as a downstream consequence of efficient energy metabolism rather than as a sign of classical dyslipidemia. provides the mechanistic rationale, proposing that in lean individuals with low hepatic glycogenHepatic glycogen is the storage form of glucose held in liver cells; when depleted—as occurs during carbohydrate restriction—the liver shifts toward increased production and secretion of VLDL particles to export fat as fuel, which the Lipid Energy Model argues explains the rise in LDL-C on ketogenic diets., the liver upregulates export of Very Low-Density Lipoprotein (VLDLVLDL, or very-low-density lipoprotein, is the particle your liver makes to ship triglycerides out to the rest of the body.) to traffic triglyceridesTriglycerides are the main form of fat in your blood and in your body's storage. to peripheral tissues, leading to elevated LDL-C as a downstream consequence of efficient lipid metabolism rather than dyslipidemiaDyslipidemia is the medical word for an unhealthy pattern of fats in the blood. It can mean high LDL, high triglycerides, low HDL, or some combination. in the classical sense.
Table 1. Comparison of the Standard Lipid Paradigm and the Lipid Energy Model
| Component | Standard Lipid Paradigm | Lipid Energy Model (LEM) | Key Distinction |
| Primary Role of LDL | Pathological residue of lipid transport. | Result of efficient energy trafficking via VLDL turnover. | Mechanism vs. pathology distinction. |
| Contextual Modifier | Risk is additive with other cardiovascular risk factors. | Risk is context-dependent; proposed to be benign if insulin sensitive. | Population vs. individual risk framing. |
| Primary Driver of Elevation | Genetic defect (e.g., FH) or high saturated fatSaturated fat is the kind that stays solid at room temperature — butter, the fat in red meat, coconut oil, and palm oil. intake. | Low hepatic glycogen and lean massThe portion of body weight attributable to muscle, bone, and organs rather than fat; higher lean mass is associated with better metabolic health and is identified in the article as an upstream genetic driver of both VO₂ max and longevity. driving upregulated VLDL export. | Metabolic state as a proposed modulator. |
| Predictive Power | Absolute ApoBApoB is a protein that sits on the outside of every cholesterol particle that can get stuck in your artery wall and cause plaque. Each of those particles carries exactly one ApoB./LDL-C predicts atherosclerotic plaque burdenPlaque burden is the total amount of plaque in your arteries, everywhere — not just at the single worst spot.. | Baseline plaquePlaque is the buildup of cholesterol, immune cells, scar tissue, and calcium inside an artery wall. burden predicts progression; circulating lipid levels may be secondary. | Disputed by longitudinal data lacking an adequate control group. |
This model is particularly persuasive because it offers testable predictions, such as an inverse association between BMI and LDL-C increase on a ketogenic dietA ketogenic diet is very low in carbohydrates and very high in fat, which pushes the body to burn fat and make ketones for fuel.. When intelligent skeptics observe these predictions confirmed in small cohorts or self-experiments, it reinforces the belief that the mainstream model is incomplete or misapplied to their phenotype.
2.2 Rhetorical Framing and the Burden of Proof
Skeptical communicators often highlight perceived absurdities in current guidelines through dramatic experiments designed to reveal discordanceSee ApoB Discordance for the full entry. between LDL-C and other metabolic markers. By demonstrating that a specific dietary or pharmacological intervention can lower LDL-C in a metabolically neutralMetabolically neutral describes a drug or compound that does not meaningfully alter blood pressure, lipid levels, insulin sensitivity, or other metabolic parameters; micronized progesterone is described this way because, unlike synthetic progestins, it does not worsen cholesterol or raise blood pressure. context, they raise the evidentiary burden for the ‘LDL-as-toxin’ narrative. Furthermore, they highlight discordance between risk markers—such as a zero Coronary Artery Calcium (CAC)Coronary artery calcium is a measure of calcified plaque deposits in the walls of the coronary arteries, quantified by CT scan and expressed as an Agatston score; higher scores indicate greater cumulative plaque burden and predict future cardiovascular events. score in the presence of very high LDL-C—to question the predictive validity of population-level risk equations in individual cases.
3. The Robust Case for LDL Causality: Convergence of Evidence
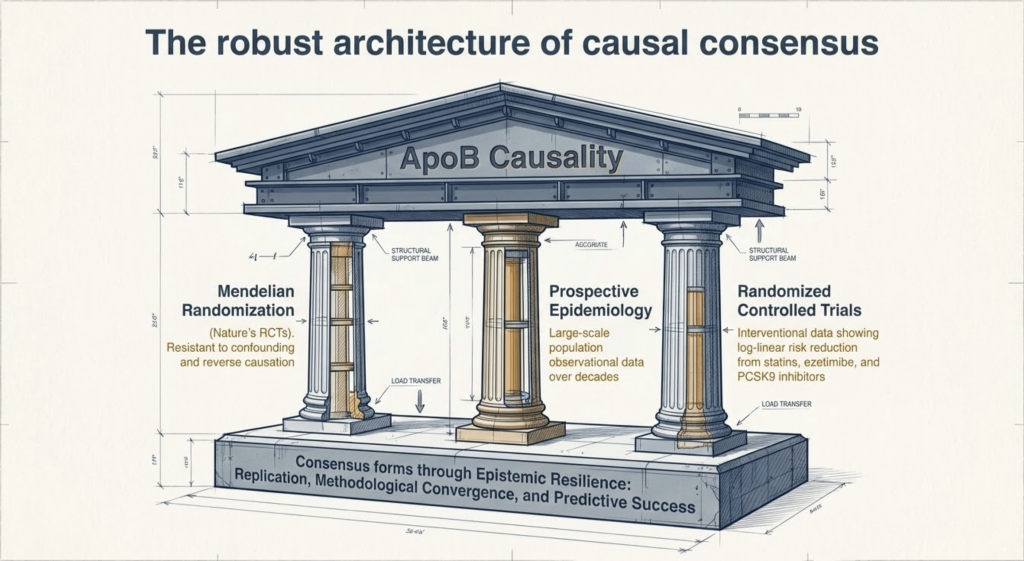
The scientific consensus that LDL is causal in ASCVD is not built on a single study but on the convergence of independent lines of evidence that collectively satisfy the Bradford Hill criteriaThe Bradford Hill criteria are a set of nine principles—including strength of association, consistency, biological plausibility, and dose-response—used to evaluate whether an observed statistical association between an exposure and a disease is likely to be causal. for causality. This convergence is critical because each method possesses different strengths and limitations, yet they all point to the same conclusion: cumulative exposureCumulative exposure is the total amount of harmful cholesterol particles your arteries have been soaked in across your entire life — how high, multiplied by how long. to ApoB-containing lipoproteins is the primary determinant of atherosclerotic development.
3.1 Genetic Evidence and Mendelian Randomization
Mendelian randomizationRandomization is the process of assigning trial participants to treatment or control groups by chance, ensuring that known and unknown confounding factors are evenly distributed; when randomization fails—as auditors found occurred in PREDIMED—the groups may differ in ways that distort the apparent treatment effect. (MR) provides perhaps the strongest evidence for causality by utilizing the random assortment of genetic variants at conception to mimic a lifelong randomized controlled trial, largely resistant to confoundingConfounding is when a hidden third factor makes two unrelated things look connected. and reverse causationReverse causation is when the arrow points the other way — the illness caused the exposure rather than the exposure causing the illness.. Variants in genes encoding the LDL receptorThe LDL receptor is a docking port on liver cells that grabs LDL particles out of the blood and pulls them in to be broken down. (LDLRLDLR is the gene that builds the LDL receptor, the docking port your liver uses to pull cholesterol particles out of circulation.), PCSK9PCSK9 is a protein made by your liver that destroys the docking ports your liver uses to pull cholesterol out of your blood., HMG-CoA reductaseHMG-CoA reductase is the rate-limiting enzyme in the liver's cholesterol biosynthetic (mevalonate) pathway; statins work by competitively blocking it, reducing the liver's own cholesterol production and prompting it to pull more LDL out of the bloodstream. (HMGCRHMGCR is the gene for HMG-CoA reductase, the enzyme that performs the rate-limiting step in making cholesterol. It is the exact target of every statin.), NPC1L1NPC1L1 is the transporter in your intestine that absorbs cholesterol from food and bile. Ezetimibe blocks it., and APOB all affect LDL-C through distinct biological pathways, yet they consistently demonstrate that lower lifelong exposure to LDL-C leads to a disproportionately larger reduction in cardiovascular risk compared to short-term pharmacological interventions initiated later in life.
Table 2. Mendelian Randomization Estimates of Cardiovascular Risk Reduction by Genetic Proxy (per 10 mg/dL decrease in LDL-C)
| Genetic Proxy (Drug Target) | Risk Reduction per 10 mg/dL LDL-C Decrease | Hazard/Odds Ratio (95% CI) |
| LDLR (LDL Receptor / FH model) | 26% | 0.74 (0.66–0.82) |
| PCSK9 (PCSK9 InhibitorA PCSK9 inhibitor is a medicine that blocks that cholesterol-destroying protein, leaving more docking ports available to clear particles from the blood. proxy) | 20% | 0.80 (0.75–0.86) |
| HMGCR (StatinA statin slows the enzyme your liver uses to make cholesterol. Your liver responds by pulling more cholesterol out of your blood, which is where the real benefit comes from. proxy) | 10% | 0.90 (0.86–0.94) |
| NPC1L1 (EzetimibeEzetimibe is a pill that blocks your intestines from absorbing cholesterol. proxy) | 15% | 0.85 (0.79–0.91) |
The magnitude of risk reduction per unit of LDL-C lowering in MR studies is approximately three times greater than that observed in statin trials of similar LDL-C reduction. This highlights the ‘cumulative exposure’ principle: the risk of ASCVD is a function of both the absolute level of ApoB particles and the duration of exposure. This ‘area under the curve’ concept explains why individuals with familial hypercholesterolemiaFamilial hypercholesterolemia, or FH, is an inherited condition where the liver cannot clear cholesterol from the blood properly. Levels are very high from birth. (FH) develop premature disease, while those with genetically determined low LDL-C are protected throughout their lives.
3.2 Pathophysiology: The Response-to-Retention Model
The biological mechanism for LDL causality is established through the ‘response-to-retention’ model, which identifies the subendothelial entrapment of ApoB-containing lipoproteins as the necessary initiating event of atherosclerosisAtherosclerosis is the disease behind most heart attacks and many strokes. Cholesterol particles get stuck in the wall of an artery, the body sends immune cells to clean up, and over years that mess hardens into plaque.. The process begins with the movement of LDL and other ApoB-containing particlesLipoproteins—including LDL, IDL, VLDL, and their remnants—that each carry one molecule of apolipoprotein B on their surface; particle number (rather than cholesterol mass alone) is a key driver of atherosclerosis because each particle can be retained in the arterial wall. across the arterial endotheliumThe endothelium is the ultra-thin, slippery lining on the inside of every blood vessel. It is only one cell thick. via transcytosisTranscytosis is the process by which a cell picks something up on one side, carries it across, and releases it on the other.. Once in the arterial intimaThe intima is the innermost layer of an artery wall, sitting just beneath the smooth lining., positively charged residues on the apolipoproteinAn apolipoprotein is a protein attached to a fat-carrying particle in your blood. Fat and water don't mix, so these proteins act like a wrapper that lets fat travel safely through the bloodstream. B-100 proteinProtein is the nutrient your body uses to build and repair muscle and tissue. interact with negatively charged glycosaminoglycanGlycosaminoglycans are long, negatively charged sugar chains that are major components of the arterial extracellular matrix and plaque connective tissue; in cynomolgus macaque plaques they are prominent structural constituents that persist after regression of the lipid-rich components. (GAG) chains of extracellular matrixThe extracellular matrix is the scaffolding of collagen and other fibers that holds tissue together and gives an artery wall its strength. proteoglycans, particularly biglycanBiglycan is a small leucine-rich proteoglycan present in the arterial subendothelial matrix that, along with versican and decorin, binds apoB-containing lipoprotein particles through ionic interactions, contributing to their retention in the intima as an initiating step in atherosclerosis. and versicanVersican is a large sulfated proteoglycan found in the arterial intima whose negatively charged glycosaminoglycan chains bind ionically to apoB-100 on lipoprotein particles, contributing to their retention in the artery wall as an early step in atherosclerosis..
Table 3. Phases of AtherogenesisAtherogenesis is the step-by-step process of a plaque forming. According to the Response-to-Retention ModelThe response-to-retention model holds that atherogenesis begins when ApoB-containing lipoproteins cross the endothelial barrier and become trapped by proteoglycans in the arterial intima, triggering oxidative modification, immune cell recruitment, foam-cell formation, and eventual plaque development.
| Phase | Pathological Event | Mechanism | Key Evidence |
| Initiation | Lipoprotein Retention | ApoB-100ApoB-100 is the full-length form of apolipoprotein B found on LDL, VLDL, IDL, and remnant lipoproteins; its positively charged amino-acid domains bind ionically to negatively charged proteoglycan side chains in the arterial wall, physically trapping the particle in the intima and initiating plaque formation. binding to intimal proteoglycans (biglycan, versican) via electrostatic interaction. | Site-directed mutagenesis reducing ApoB-proteoglycan affinity markedly attenuates atherosclerosis in animal models. |
| Modification | Aggregation and Oxidation | Secretory sphingomyelinaseSecretory sphingomyelinase is an enzyme present in the arterial wall that modifies retained LDL particles after they become trapped in the intima, promoting their aggregation and making them far more atherogenic than native LDL., lipolytic enzymes, and ROS modify retained particles. | Modified LDL is markedly more atherogenic than native LDL ex vivo. |
| Inflammatory Response | Monocyte Recruitment and Differentiation | Modified LDL signals endothelial VCAM-1VCAM-1 is a sticky molecule that appears on an inflamed vessel lining and grabs passing white blood cells so they can burrow into the wall./ICAM-1ICAM-1 is a molecule that appears on the surface of the blood vessel lining and acts like Velcro, catching passing immune cells. upregulation; monocyte-to-macrophage differentiation. | Consistent with the ‘response-to-injury’ hypothesis at the molecular level. |
| Plaque Formation | Foam CellA foam cell is an immune cell that has eaten so much trapped cholesterol that it swells up and looks foamy under a microscope. Accumulation | MacrophagesA macrophage is a large immune cell that swallows debris and invaders. The name literally means "big eater." ingest modified LDL via scavenger receptors, becoming foam cells that cannot exit the intima. | Core finding of response-to-retention model (Williams & Tabas, 1995). |
| Progression | Plaque Growth, CalcificationCalcification is when calcium gets deposited into a plaque, turning part of it hard and bony., and Rupture Risk | Sustained retention and chronic maladaptive inflammationInflammation is your immune system's response to injury or something it treats as an invader. It brings swelling, heat, and cleanup cells. drive necrotic coreThe necrotic core is the dead, mushy center of an advanced plaque, built from immune cells that ate trapped cholesterol and then died in place. formation and cap thinning. | Explains why cumulative LDL exposure (‘cholesterol-yearsCholesterol-years is a cumulative-exposure metric that multiplies a person's average LDL-C level (in mg/dL) by the number of years they have carried that level, analogous to pack-years for tobacco. The concept holds that it is the total lifetime burden of apoB-containing lipoproteins, not any single reading, that determines when and how severely atherosclerosis develops.’) predicts events. |
Research utilizing site-directed mutagenesis to create LDL particles with reduced proteoglycan-binding affinity has demonstrated that even under conditions of severe hyperlipidemia, these modified particles cause significantly less atherosclerosis in animal models. This confirms that it is not merely the presence of cholesterolCholesterol is a waxy substance your body needs. It goes into cell walls, hormones, vitamin D, and the bile that digests your food. You would die without it., but the retention of ApoB-containing particles, that drives the atherogenic process—a distinction of fundamental mechanistic importance.
3.3 Randomized Controlled Trials and Clinical Outcomes
The efficacy of LDL-C lowering has been validated across numerous large-scale RCTs involving statins, ezetimibe, and PCSK9 inhibitors. A meta-analysisA meta-analysis statistically combines the results of many separate studies into one overall estimate. of 26 randomized trials involving 170,000 participants demonstrated that each 1 mmol/L (approximately 39 mg/dL) reduction in LDL-C produces a consistent ~22% relative reduction in major cardiovascular events. Critically, this relationship is log-linear and holds true even at very low levels of LDL-C, supporting the ‘lower is better’ principle, with no identified threshold below which further reduction loses benefit.
Critiques of these trials often focus on changes in post-2005 trial conduct regulations, suggesting that earlier efficacy estimates were inflated. However, large-scale meta-analyses and trials of newer agents—including PCSK9 inhibitors—have continued to affirm the log-linear relationshipA log-linear relationship between LDL-C and cardiovascular risk means that each successive equal reduction in LDL-C produces a proportionally consistent percentage reduction in heart events, with no threshold below which further lowering stops being beneficial—supporting the 'lower is better' principle. between LDL-C reduction and cardiovascular risk reduction across all major contemporary trials.
4. Analysis of Skeptical Counter-Evidence
4.1 The ‘Elderly Paradox’ and Reverse Causation
A common skeptical argument holds that high LDL-C is associated with longevity in the elderly. Systematic reviewsA systematic review searches for every study on a question using a pre-declared method, then assesses them by consistent criteria. of cohort studies in populations aged 60 years and older have found that those with higher LDL-C often survive as long as or longer than those with lower levels. However, this observation is substantially complicated by several well-characterized methodological factors.
First, reverse causationCausation means one thing actually makes another thing happen. It is different from correlation, which only means two things tend to show up together.: chronic diseases such as malignancy and terminal infections reliably lower cholesterol levels in the years preceding death, inflating apparent mortality in the low-LDL group. Second, immune function: LDL participates in innate immunity by inactivating microbial pathogens and their toxins; in the elderly, where infection is a leading cause of mortality, this protective role may attenuate all-cause mortalityAll-cause mortality means death from any cause at all, not just heart disease — the broadest, hardest-to-game outcome a study can measure. benefits even as atherosclerotic risk accumulates. Third, survivor biasSurvivor bias in the elderly paradox refers to the statistical artifact whereby people who reach old age with high LDL may represent a genetically hardy subset who were never vulnerable to LDL-driven atherosclerosis, making high LDL appear safe in that age group when the susceptible individuals already died younger.: individuals genetically susceptible to LDL-driven atherosclerosis are more likely to have experienced fatal cardiovascular events earlier in life, leaving an enriched cohort of survivors in older age brackets who are less biologically vulnerable to LDL-mediated atherogenesis.
4.2 The Role of Metabolic Health as a Risk Modifier
Skeptics correctly identify that the absolute cardiovascular risk associated with a given LDL-C level is significantly modified by other factors. High insulin sensitivity, low systemic inflammation (as measured by high-sensitivity C-reactive proteinC-reactive protein, or CRP, is a substance your liver makes when there is inflammation somewhere in your body. A sensitive version of the test, hs-CRP, is used to estimate heart risk.), and optimal blood pressureBlood pressure is the force of blood pushing against your artery walls. It is written as two numbers, like 120/80. The top number is the pressure when your heart squeezes, the bottom is when it relaxes. can lower the probability that a retained LDL particle triggers a maladaptive inflammatory cascade. This does not, however, eliminate the role of LDL as the primary initiating agent of atherosclerosis. Rather, it suggests that some individuals have greater arterial resilience and fewer co-amplifying stressors—modifiers of rate and impact, not of causal mechanism.
5. The KETO-CTA Study: New Data and Its Limitations
The recent publication of longitudinal data from the KETO-CTAKETO-CTA is a study that used coronary CT angiography to assess plaque burden in individuals on ketogenic diets with markedly elevated LDL-C, finding that despite a high prevalence of zero CAC scores, non-calcified (soft) plaque volume increased approximately 42% over one year. trial has become a focal point of the LDL debate. This study followed approximately 100 individuals meeting criteria for the LMHR or ‘near-LMHR’ phenotype over one year, using coronary computed tomographyComputed tomography, or CT, takes X-ray images from many angles and reconstructs them into cross-sections of the body. angiography (CCTA) to quantify plaque progression.
5.1 Key Findings
The study reported that baseline plaque burden was the strongest predictor of future plaque progression, whereas traditional lipid markers—including ApoB and LDL-C—and cumulative exposure during a ketogenic diet did not significantly correlate with progression in this cohort over the one-year follow-up. The authors interpreted these findings as evidence that elevated ApoB and LDL-C do not drive atherosclerosis in a dose-dependent manner in metabolically healthy individuals.
Table 4. Key Metrics from the KETO-CTA Cohort and Mainstream Cardiology Context
| Metric | KETO-CTA Cohort Result | Mainstream Cardiology Context |
| Mean LDL-C | ~272 mg/dL (mean) | Classified as very high risk; exceeds typical FH diagnostic threshold (~190 mg/dL). |
| 1-Year NCPV Change | +42% median increase | Substantially higher than low-risk reference cohorts and comparable high-risk groups including those with FH or diabetesDiabetes is a condition where blood sugar stays too high, either because the body makes too little insulin or because it stops responding to the insulin it makes.. |
| Zero CAC at Baseline | 57% of participants | Suggests initial resilience; however, absence of calcified plaqueCalcified plaque is the hardened, calcium-filled part of a plaque. It shows up brightly on a CT scan, which is what a calcium scan measures. does not exclude non-calcified plaqueNon-calcified plaque is the soft, fatty portion of a plaque that has not hardened with calcium. It shows up dark on a CT scan. burden. |
| ApoB Prediction of Progression | No statistically significant association | Conflicts with population-level dose-responseA dose-response relationship means more of something produces more of an effect, in a consistent gradient. data from Mendelian randomization and meta-analyses; may reflect insufficient power or follow-up duration. |
| Control Group | Absent | Prevents determination of whether observed progression rates are ‘modest’ or elevated relative to metabolically healthy individuals with low LDL-C. |
5.2 Critical Methodological Limitations
The interpretation offered by the KETO-CTA authors has attracted substantial criticism from the broader scientific community, culminating in an Expression of Concern issued by the Journal of the American College of Cardiology. Several critical methodological limitations undermine the authors’ conclusions.
The observation that ‘plaque begets plaque’ is a well-established phenomenon across all population groups and does not constitute evidence against the factors that initiated the plaque in the first place. The absolute rate of non-calcified plaque volumePlaque volume is the total physical amount of plaque in a stretch of artery, measured in cubic millimeters. (NCPV) progression reported—approximately 42% over one year—is markedly higher than progression rates observed in high-risk groups such as those with diabetes or established FH in comparable longitudinal imaging studies.
The absence of a control group of lean, metabolically healthy individuals with low LDL-C makes it impossible to determine whether the progression observed was modest or alarming in relative terms. Without this comparator, the KETO-CTA data remains an intriguing but isolated observation that cannot be used to overturn decades of convergent causal evidence. The study’s one-year duration is also fundamentally insufficient to capture the decades-long kinetics of atherogenesis that Mendelian randomization studies reveal.
6. How ‘Sophisticated Doubt’ Functions in Scientific Discourse
‘Sophisticated doubt’ is a rhetorical technique that employs nuance, partial truths, and the amplification of scientific uncertainty to make established conclusions appear weaker than the totality of the evidence warrants. In the context of the LDL debate, this manifests in several recognizable patterns.
The ‘mass balance’ challenge: critics of the LEM argue that the model fails to account for where the additional cholesterol in LMHR LDL particles comes from if not from over-synthesis or under-clearance, an argument from basic lipid homeostasis that proponents address with mechanistic complexity but frequently without resolution at the level of first principles. Selective burden of proof: demanding a 10-year RCT in LMHR individuals—which would be ethically untenable if substantial cardiovascular risk is presumed—while accepting a one-year observational imaging study as definitive evidence of safety. Confounding relative and absolute riskAbsolute risk is the real chance that something will happen to you, written as a percentage. If your absolute risk of a heart attack in the next ten years is 12 percent, that means about 12 out of every 100 people like you would have one.: invoking the strong negative predictive value of a zero CAC score to imply that the relative atherogenic risk of extreme hyperlipidemia is negligible.
By framing the debate as a conflict between ‘individualized medicine’ and ‘population-level dogma,’ communicators tap into the contemporary zeitgeist of patient autonomy and institutional distrust—a rhetorically powerful but epistemologically incomplete position.
7. How Scientific Consensus Forms
It is a common misconception that scientific consensus is produced by a single definitive experiment. In reality, consensus emerges through the accumulation of ‘epistemic resilience’ via multiple independent processes. First, replication: the same association must be observed in different populations, by independent researchers, using methodologically distinct approaches. Second, convergence of methods: when genetic studies (nature’s experiments), epidemiological cohorts (observational data), and RCTs (interventional data) converge on the same directional finding, the probability of systematic error across all domains simultaneously approaches a very low threshold. Third, predictive success: a causal model must not only explain existing data but successfully predict the outcomes of novel interventions. The consistent reduction in cardiovascular events across hundreds of trials using diverse LDL-lowering mechanisms constitutes powerful prospective validation of the causal model.
In contrast, doubt is often constructed rhetorically by identifying a single anomaly—such as the elderly paradox or the LMHR phenotype—and using it to question the entire causal foundation. In science, an anomaly is an invitation to refine a model (for example: ‘LDL is causal, but its impact is modified by baseline insulin sensitivity and inflammatory milieu’) rather than to discard it wholesale. The two positions are not equivalent; one expands scientific understanding while the other selectively dismantles it.
8. Communication Strategies for Engaging the Skeptical Thinker
Effective clinical communication with LDL-skeptical patients requires moving beyond the ‘deficit model’—the assumption that providing more facts will resolve disagreement—toward an engagement model built on shared goals and collaborative reasoning.
8.1 Leading with Shared Goals
Rather than leading with a corrective posture, begin by affirming the shared objective of long-term health optimization. For example: ‘The metabolic improvements you’ve achieved on a carbohydrate-restricted diet are genuinely impressive and clinically meaningful. My concern is whether we can preserve those gains while also addressing the long-term implications of sustained, extreme elevations in circulating ApoB-containing particles.’ This framing positions the clinician as a collaborator rather than an adversary.
8.2 The Truth Sandwich and Prebunking
When addressing a specific claim, the ‘truth sandwich’ structure is effective: lead with the established fact, briefly address the misconception, and return to the established fact. For example: LDL particles play vital physiological roles including contributions to innate immunity and lipid transport. However, the claim that these functions render LDL categorically non-atherogenic is not supported by the mechanistic or outcomes evidence. The same particles that serve these functions, when present in excess over decades, become entrapped in the arterial intima—the necessary initiating event of atherosclerosis.
Prebunking involves inoculating the patient against specific misleading rhetorical tactics in advance: ‘You may encounter studies showing no correlation between LDL and plaque progression over a single year. Atherosclerosis is a decades-long process; one-year imaging snapshots, particularly without a control group, provide insufficient resolution to assess lifetime cumulative risk.’
8.3 Motivational Interviewing Example
Patient: “I’ve reviewed Dr. Norwitz’s data, and my metabolic markers are excellent. I don’t believe my elevated LDL is a meaningful risk factor in my specific case.”
Clinician (Reflective Listening): “It sounds like you’ve done considerable research and have concluded that your excellent metabolic healthMetabolic health describes how well your body handles blood sugar, blood pressure, fats, and body fat storage. substantially attenuates the usual risks associated with elevated LDL-C. Can you tell me more about what evidence would change your assessment?”
Clinician (Open-Ended Question): “If we were to find evidence—using imaging available now—that plaque is already accumulating in your coronaries at an accelerated rate despite your metabolic health, how would that change your thinking about your current approach?”
9. Historical Analogies and Their Limitations
LDL skeptics sometimes compare their position to historical instances of correct scientific dissent—such as Warren and Marshall’s discovery of H. pylori as the cause of peptic ulcer disease in opposition to the prevailing ‘acid paradigm.’ This analogy is instructive but ultimately inapposite: the H. pylori hypothesis was initially opposed by a single established paradigm and was validated by an immediate, verifiable therapeutic response. LDL causality, by contrast, is supported by convergent evidence from geneticsGenetics is the study of what you inherit from your parents., pathophysiology, epidemiology, and interventional trials—a qualitatively different evidentiary structure that is far more resistant to overturning by a single anomalous finding.
A more instructive analogy is the dose-response relationshipA dose-response relationship describes how the magnitude of a biological effect changes as the amount of an exposure (such as weekly exercise minutes) increases; in this article, resistance training shows a non-linear dose-response for mortality, with benefits plateauing around 120 minutes per week and a J-shaped curve emerging at very high volumes in older women. between cigarette smokingSmoking damages the lining of your blood vessels, raises blood pressure, makes blood clot more easily, and speeds up plaque growth. and lung cancer. Not every smoker develops cancer, and some non-smokers do—reflecting individual variability and the multifactorial nature of carcinogenesis. However, the causal role of smoking is undeniable because risk is a function of cumulative exposure: more pack-yearsPack-years is a standardized measure of cumulative tobacco exposure calculated by multiplying the number of packs smoked per day by the number of years of smoking; the article uses it as the conceptual model for thinking about cumulative apoB exposure, noting that both metrics are imperfect summaries of lifetime exposure that carry more prognostic weight than a single current measurement. predicts greater risk. Similarly, the LMHR individual claiming safety from atherosclerosis based on excellent metabolic health is analogous to a long-term smoker claiming safety based on superior pulmonary function and cardiovascular fitness. The fitness modifies the risk; it does not remove the causal exposure.
10. Conclusion
The most intellectually honest position currently available is one of cautious metabolic respect. We must respect the profound improvements in metabolic health that many individuals achieve through carbohydrateCarbohydrates are the sugars and starches in food — bread, rice, pasta, fruit, potatoes, sweets. restriction, and we must equally respect the overwhelming convergent evidence that elevated ApoB-containing lipoproteins are the primary drivers of atherosclerosis regardless of the metabolic context that generates the elevation.
The Lean Mass Hyper-Responder phenotype represents a fascinating natural experiment—one that warrants rigorous, well-controlled longitudinal investigation. The KETO-CTA study, rather than closing the debate, has highlighted the urgent need for prospective, controlled, long-duration research in this population. For individuals currently presenting with this phenotype, the most prudent approach is individualized risk assessment using advanced vascular imaging, with explicit acknowledgment that ‘excellent metabolic health’ has not yet been demonstrated to negate the long-term consequences of extreme, sustained hyperlipidemia.
10.1 Questions Skeptics Are Right to Ask
- To what quantitative degree does a near-zero inflammatory environment (hs-CRP <0.3 mg/L) attenuate the atherogenicity of a given ApoB particle concentration?
- Why do some individuals with LDL-C >300 mg/dL remain free of detectable plaque into their eighth decade of life?
- Is there a saturation threshold for proteoglycan bindingProteoglycan binding is the electrochemical interaction by which positively charged lysine- and arginine-rich regions of ApoB latch onto the negatively charged glycosaminoglycan chains of intimal matrix proteins such as biglycan, versican, perlecan, and decorin. This binding dramatically prolongs the residence time of a lipoprotein particle within the artery wall, making it far more susceptible t… beyond which higher LDL concentrations no longer increase retention in a linear fashion?
- Can functional biomarkersA biomarker is something measurable in the body that tells you about health or disease — a lab value, a scan result, a blood pressure reading. of LDL retention be developed that provide superior individualized risk stratification compared to circulating LDL-C or ApoB concentration alone?
10.2 What the Totality of Evidence Still Supports
- The subendothelial retentionSubendothelial retention is the process by which ApoB-containing lipoprotein particles that have crossed the endothelial barrier become electrostatically bound to proteoglycans in the arterial intima and are unable to diffuse back into the bloodstream; it is considered the non-redundant first step in atherosclerosis under the response-to-retention framework. of ApoB-containing lipoproteins is the necessary initiating event in atherosclerosis.
- Lifetime cumulative LDL-C exposure (‘cholesterol-years’) is a superior predictor of atherosclerotic risk compared to any single-point measurement.
- Genetic variants that lower LDL-C from birth confer profound protection against ASCVD, independent of other lifestyle factors.
- Lowering LDL-C and ApoB via any mechanism—diet, statins, ezetimibe, or PCSK9 inhibitors—consistently reduces major cardiovascular events across the full spectrum of baseline risk.
- Metabolic health modifies the rate and clinical impact of plaque progression but has not been demonstrated to negate the fundamental causal role of LDL in the atherosclerotic process.
References
The following references are limited to peer-reviewed journal articles and evidence-based scientific sources. Non-peer-reviewed sources including blog posts, podcasts, and popular media that appeared in earlier drafts have been removed from this reference list.
- Nordestgaard BG, Chapman MJ, Humphries SE, et al. Familial hypercholesterolaemia is underdiagnosed and undertreated in the general population: guidance for clinicians to prevent coronary heart disease. Eur Heart J. 2013;34(45):3478-3490. doi:10.1093/eurheartj/eht273
- Ference BA, Ginsberg HN, Graham I, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease. 1. Evidence from genetic, epidemiologic, and clinical studies. A consensus statement from the European Atherosclerosis Society Consensus Panel. Eur Heart J. 2017;38(32):2459-2472. doi:10.1093/eurheartj/ehx144
- Tabas I, Williams KJ, Boren J. Subendothelial lipoprotein retention as the initiating process in atherosclerosis: update and therapeutic implications. Circulation. 2007;116(16):1832-1844. doi:10.1161/CIRCULATIONAHA.106.676890
- Ference BA, Bhatt DL, Catapano AL, et al. Association of genetic variants related to combined exposure to lower low-density lipoproteins and lower systolic blood pressure with lifetime risk of cardiovascular disease. JAMA. 2019;322(14):1381-1391. doi:10.1001/jama.2019.14120
- Rawlings AM, Sharrett AR, Schneider ALC, et al. Diabetes in midlife and cognitive change over 20 years: a cohort study. Ann Intern Med. 2014;161(11):785-793.
- Norwitz NG, Feldman D, Soto-Mota A, Kalayjian T, Ludwig DS. Elevated LDL cholesterol with a carbohydrate-restricted diet: evidence for a ‘lean mass hyper-responder’ phenotype. Curr Dev Nutr. 2022;6(1):nzab144. doi:10.1093/cdn/nzab144
- Norwitz NG, Soto-Mota A, Feldman D, Budoff M, Rapaport S. The Lipid Energy Model: reimagining lipoprotein function in the context of carbohydrate-restricted diets. Metabolites. 2022;12(5):460. doi:10.3390/metabo12050460
- Lawler PR, Akinkuolie AO, Ridker PM, et al. Discordance between circulating atherogenic cholesterol mass and lipoprotein particle concentration in relation to future coronary events in women. Clin Chem. 2017;63(1):314-323. doi:10.1373/clinchem.2016.263566
- Ravnskov U, Diamond DM, Hama R, et al. Lack of an association or an inverse association between low-density-lipoprotein cholesterol and mortality in the elderly: a systematic review. BMJ Open. 2016;6(6):e010401. doi:10.1136/bmjopen-2015-010401
- Baigent C, Blackwell L, Emberson J, et al; Cholesterol Treatment Trialists’ (CTT) Collaboration. Efficacy and safety of more intensive lowering of LDL cholesterol: a meta-analysis of data from 170,000 participants in 26 randomised trials. Lancet. 2010;376(9753):1670-1681. doi:10.1016/S0140-6736(10)61350-5
- Silverman MG, Ference BA, Im K, et al. Association between lowering LDL-C and cardiovascular risk reduction among different therapeutic interventions: a systematic review and meta-analysis. JAMA. 2016;316(12):1289-1297. doi:10.1001/jama.2016.13985
- Sabatine MS, Giugliano RP, Keech AC, et al. Evolocumab and clinical outcomes in patients with cardiovascular disease. N Engl J Med. 2017;376(18):1713-1722. doi:10.1056/NEJMoa1615664
- Soto-Mota A, Norwitz NG, Evans RD, Clarke K, Barber TM. Cholesterol is not created equal: the effect of the Oreo cookie experiment in context. Curr Opin Endocrinol Diabetes Obes. 2023;30(2):128-136. doi:10.1097/MED.0000000000000786
- Budoff MJ, Mayrhofer T, Ferencik M, et al. Prognostic value of coronary artery calcium in the PROMISE study (Prospective Multicenter Imaging Study for Evaluation of Chest Pain). Circulation. 2017;136(21):1993-2005. doi:10.1161/CIRCULATIONAHA.117.030578
- Soto-Mota A, Norwitz NG, Budoff M, et al. Plaque begets plaque, ApoB does not: longitudinal data from the KETO-CTA trial. JACC Adv. 2025;4(5):101480. doi:10.1016/j.jacadv.2025.101480 [Expression of Concern issued by the Journal]
- Williams KJ, Tabas I. The response-to-retention hypothesis of atherogenesis reinforced. Curr Opin Lipidol. 1998;9(5):471-474. doi:10.1097/00041433-199810000-00012
- Ference BA, Yoo W, Alesh I, et al. Effect of long-term exposure to lower low-density lipoprotein cholesterol beginning early in life on the risk of coronary heart disease: a Mendelian randomization analysis. J Am Coll Cardiol. 2012;60(25):2631-2639. doi:10.1016/j.jacc.2012.09.017
- Grundy SM, Stone NJ, Bailey AL, et al. 2018 AHA/ACC/AACVPR/AAPA/ABC/ACPM/ADA/AGS/APhA/ASPC/NLA/PCNA Guideline on the Management of Blood Cholesterol. J Am Coll Cardiol. 2019;73(24):e285-e350. doi:10.1016/j.jacc.2018.11.003
- Davey Smith G, Hemani G. Mendelian randomization: genetic anchors for causal inference in epidemiological studies. Hum Mol Genet. 2014;23(R1):R89-R98. doi:10.1093/hmg/ddu328
- Boren J, Williams KJ. The central role of arterial retention of cholesterol-rich apolipoprotein-B-containing lipoproteins in the pathogenesis of atherosclerosis: a triumph of simplicity. Curr Opin Lipidol. 2016;27(5):473-483. doi:10.1097/MOL.0000000000000330
- Ridker PM, Everett BM, Thuren T, et al. Antiinflammatory therapy with canakinumab for atherosclerotic disease. N Engl J Med. 2017;377(12):1119-1131. doi:10.1056/NEJMoa1707914
- Khera AV, Kathiresan S. Genetics of coronary artery disease: discovery, biology and clinical translation. Nat Rev Genet. 2017;18(6):331-344. doi:10.1038/nrg.2016.160
- Catapano AL, Pirillo A, Bonacina F, Norata GD. HDL in innate and adaptive immunity. Cardiovasc Res. 2014;103(3):372-383. doi:10.1093/cvr/cvu150
- Swerdlow DI, Preiss D, Kuchenbaecker KB, et al; DIAGRAM Consortium; MAGIC Consortium; InterAct Consortium. HMG-coenzyme A reductase inhibition, type 2 diabetes, and bodyweight: evidence from genetic analysis and randomised trials. Lancet. 2015;385(9965):351-361. doi:10.1016/S0140-6736(14)61183-1
- Toth PP, Larsen WE, Zhu X, et al. Causal relationship between drug target genes of LDL-cholesterol lowering pharmacotherapies and cardiovascular disease: a drug target Mendelian randomization study. Front Cardiovasc Med. 2025;12:1484521. doi:10.3389/fcvm.2025.1484521

